




























Patient Reviews 4.9/5 10.000+ Happy Patients 37 Countries

Gum Treatment in Antalya — Periodontology

✦ Tedaviler

Gum Treatment in Antalya — Periodontology

Gum treatment in Muratpasa, Antalya for bleeding, recession and calculus — periodontal care aimed at halting bone loss.

✦ Our Patients

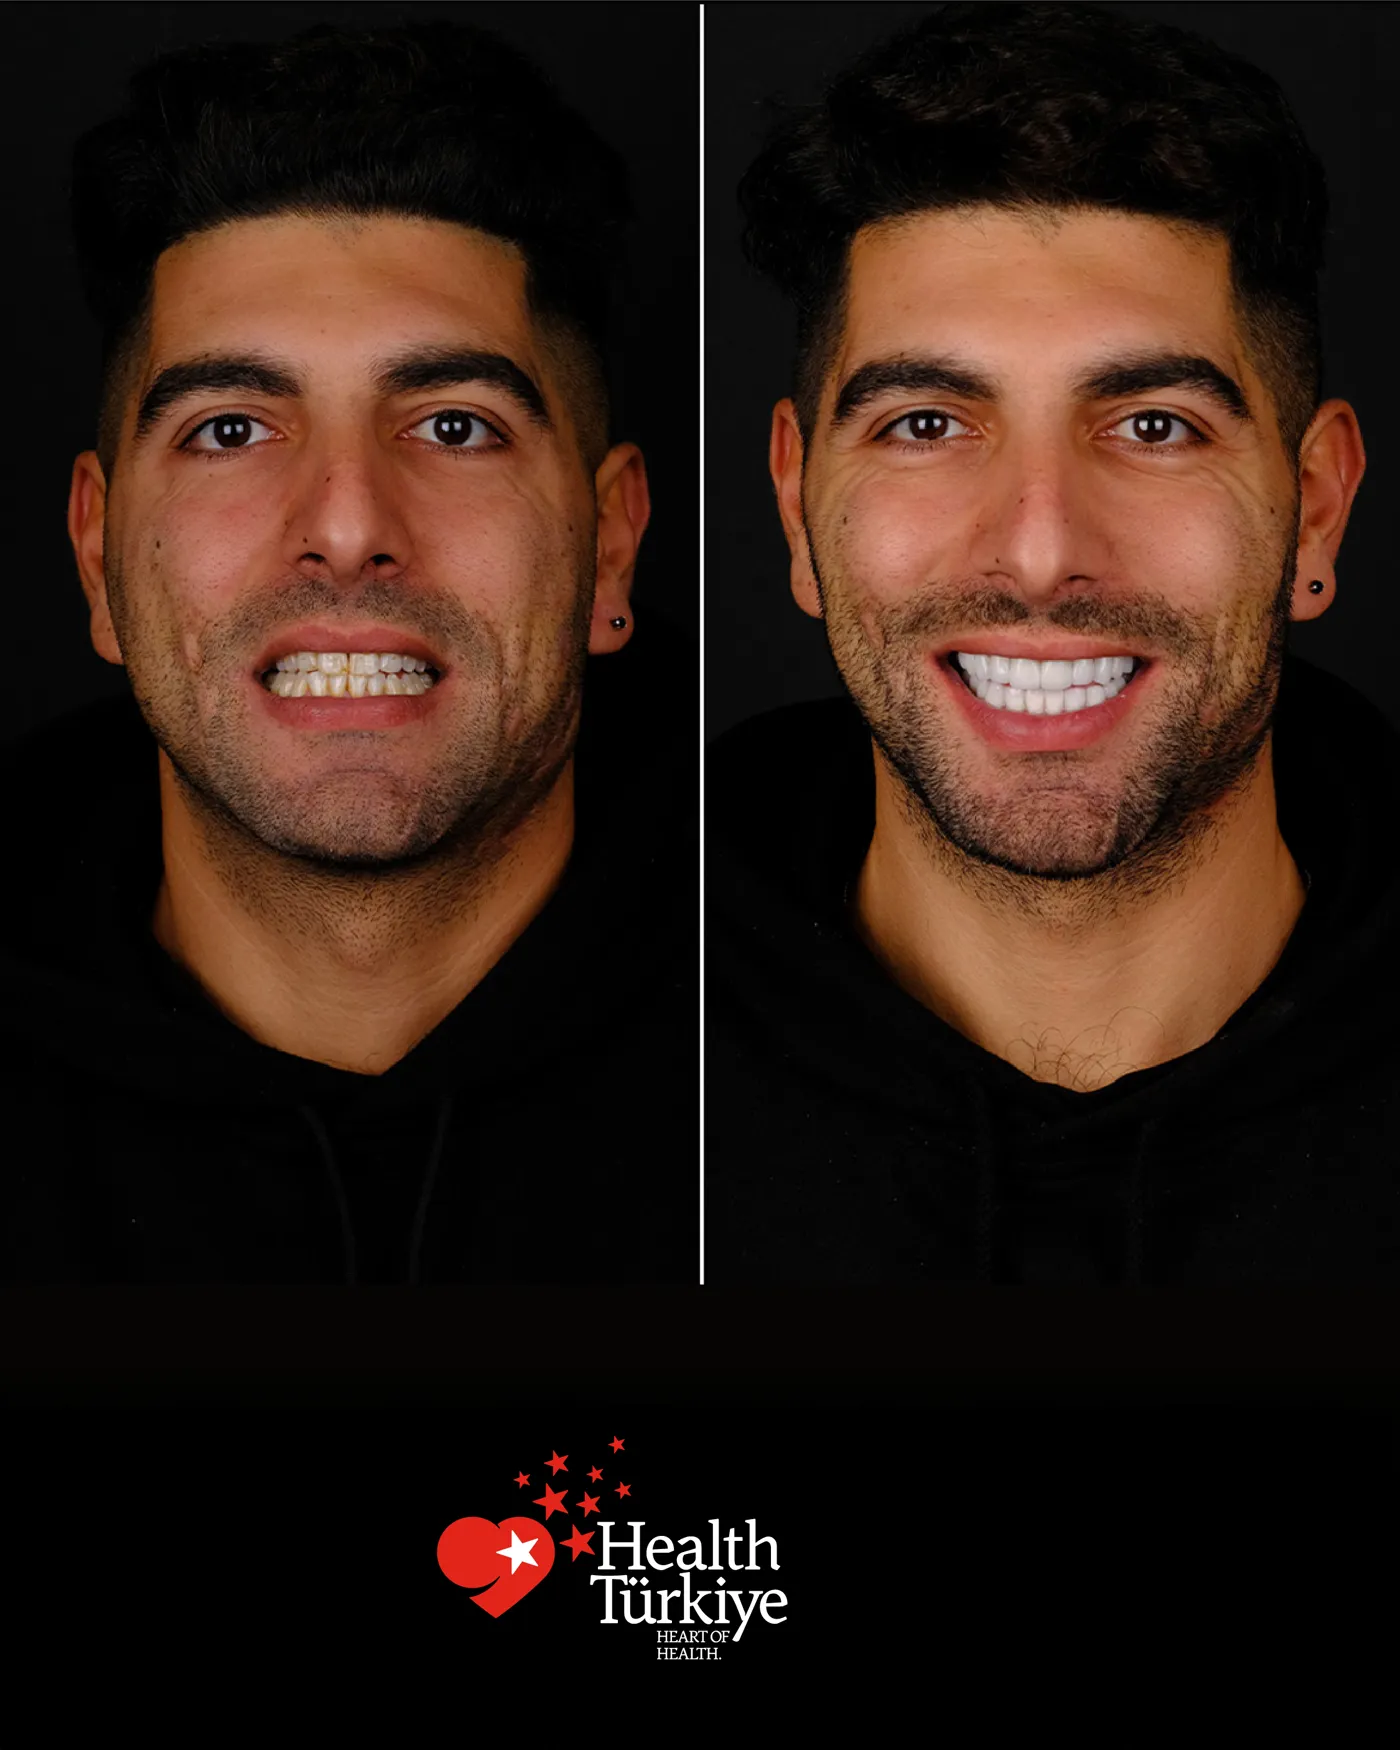
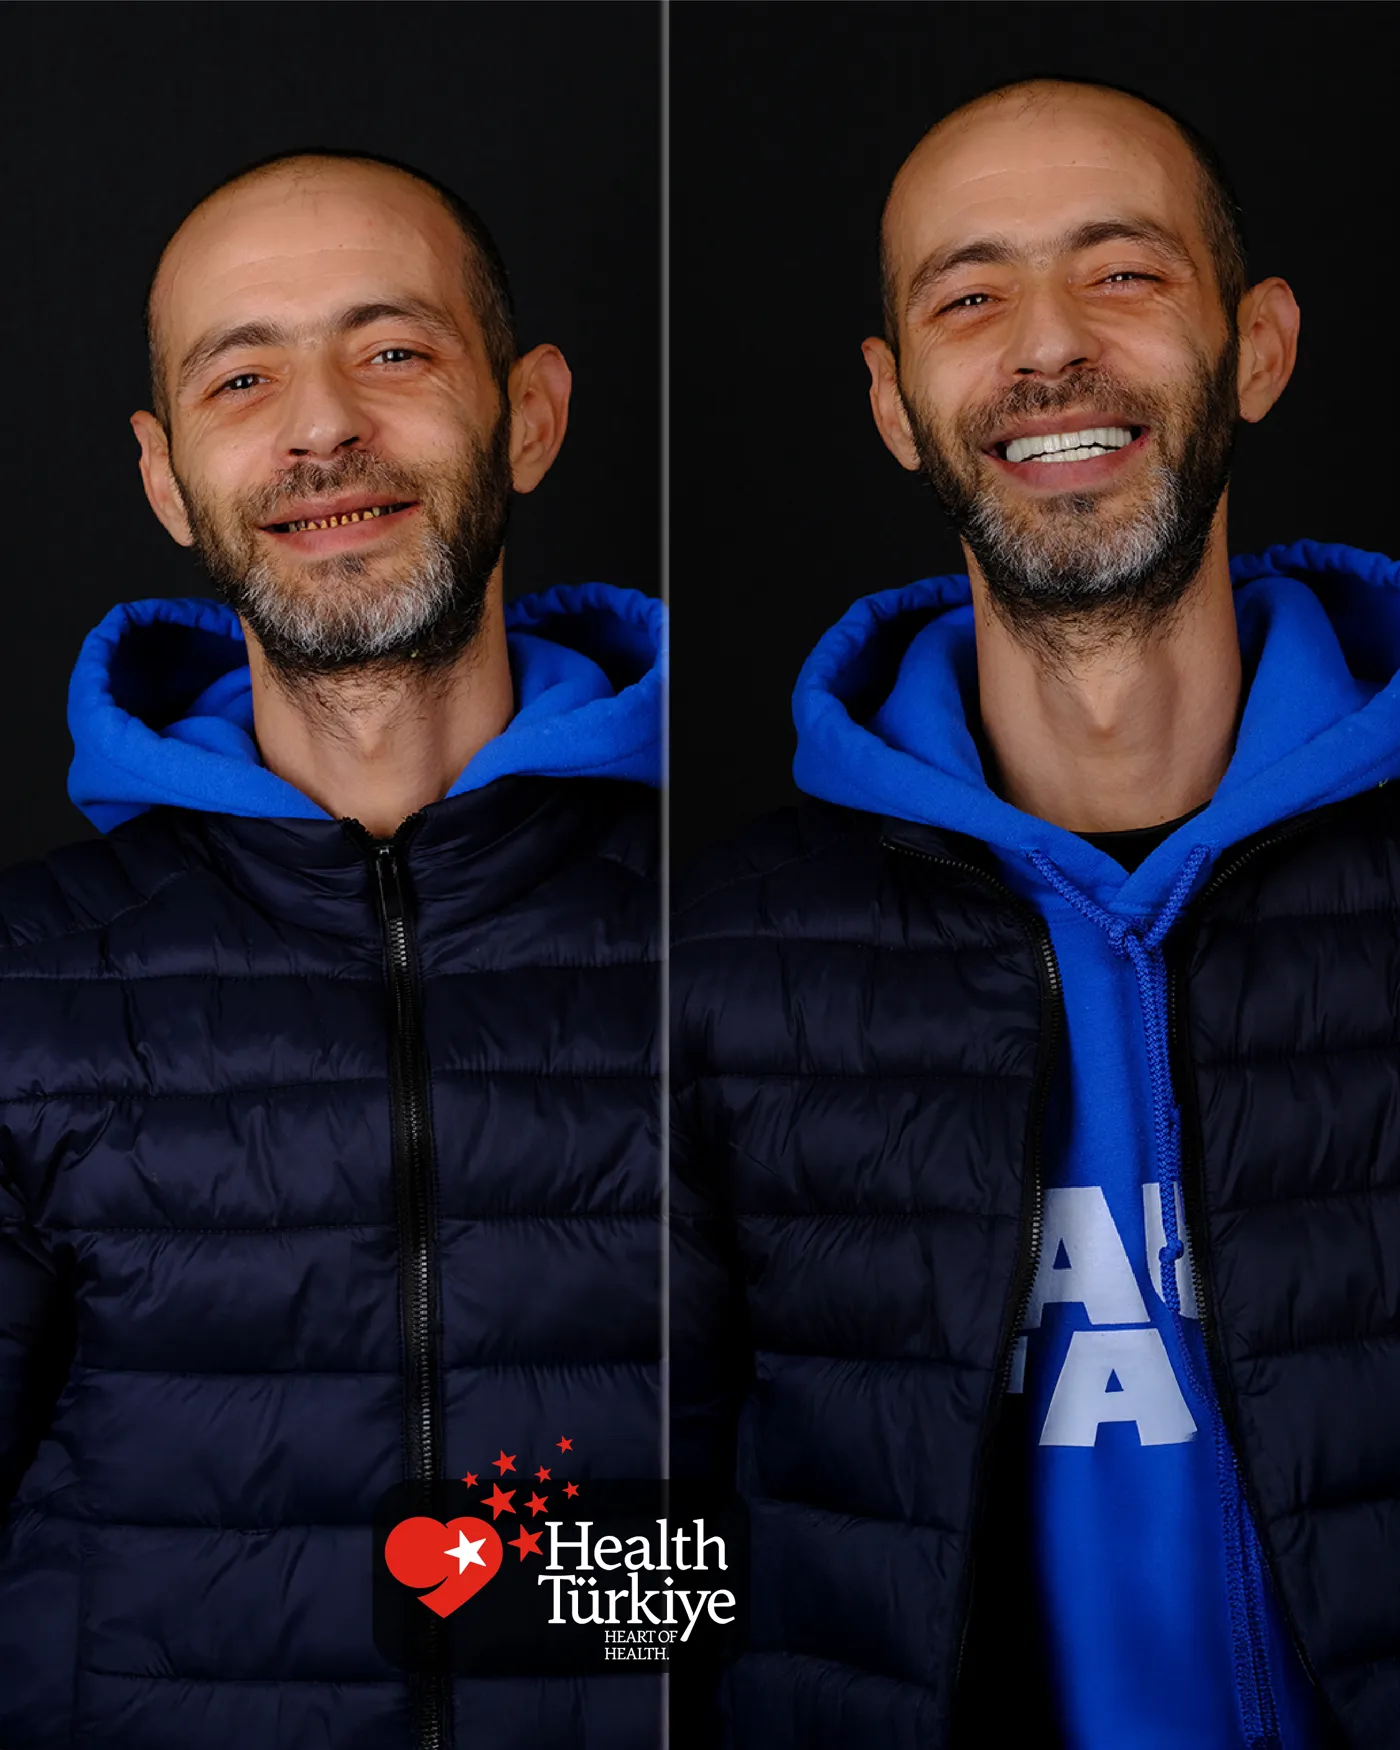
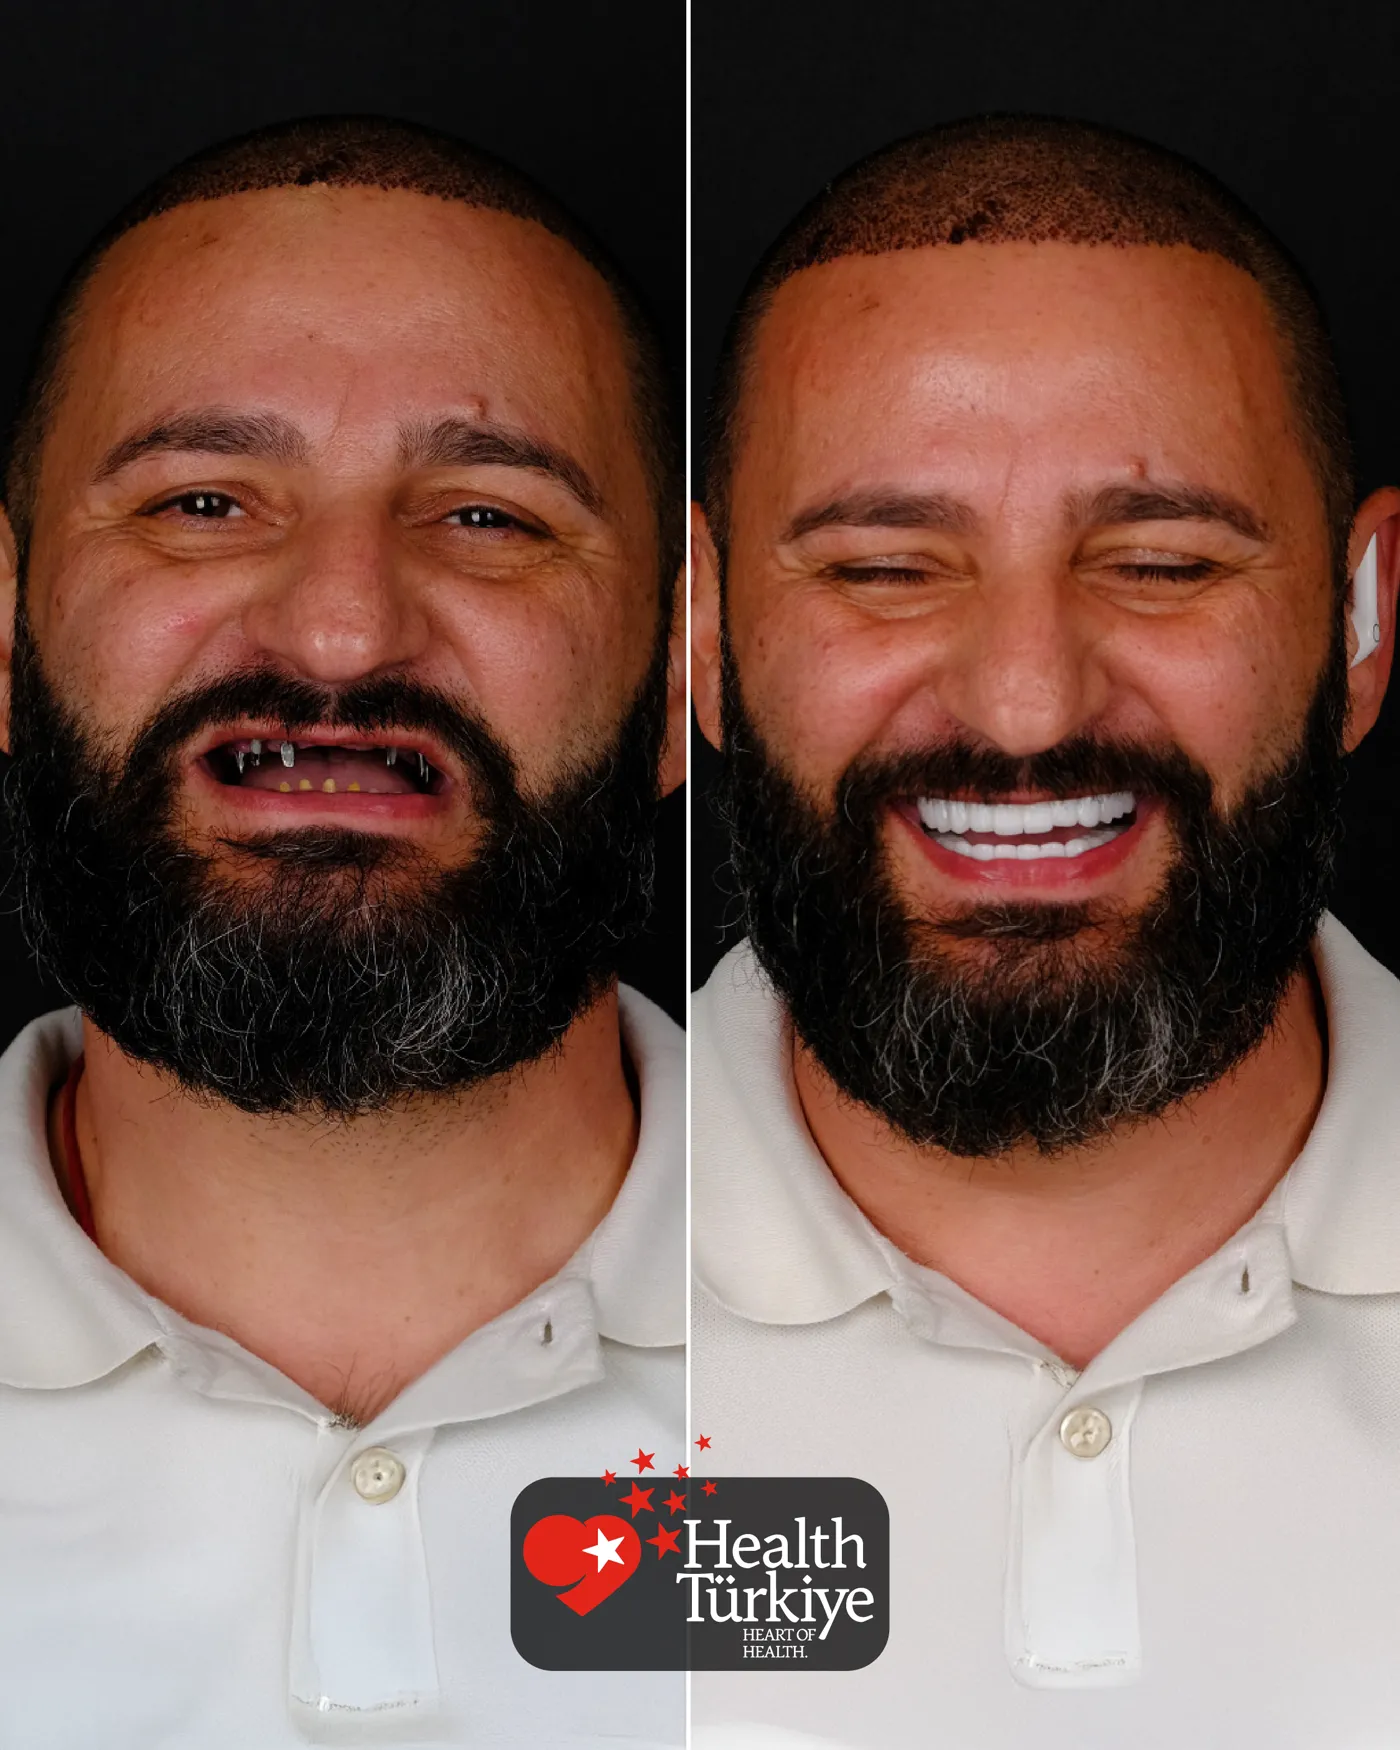
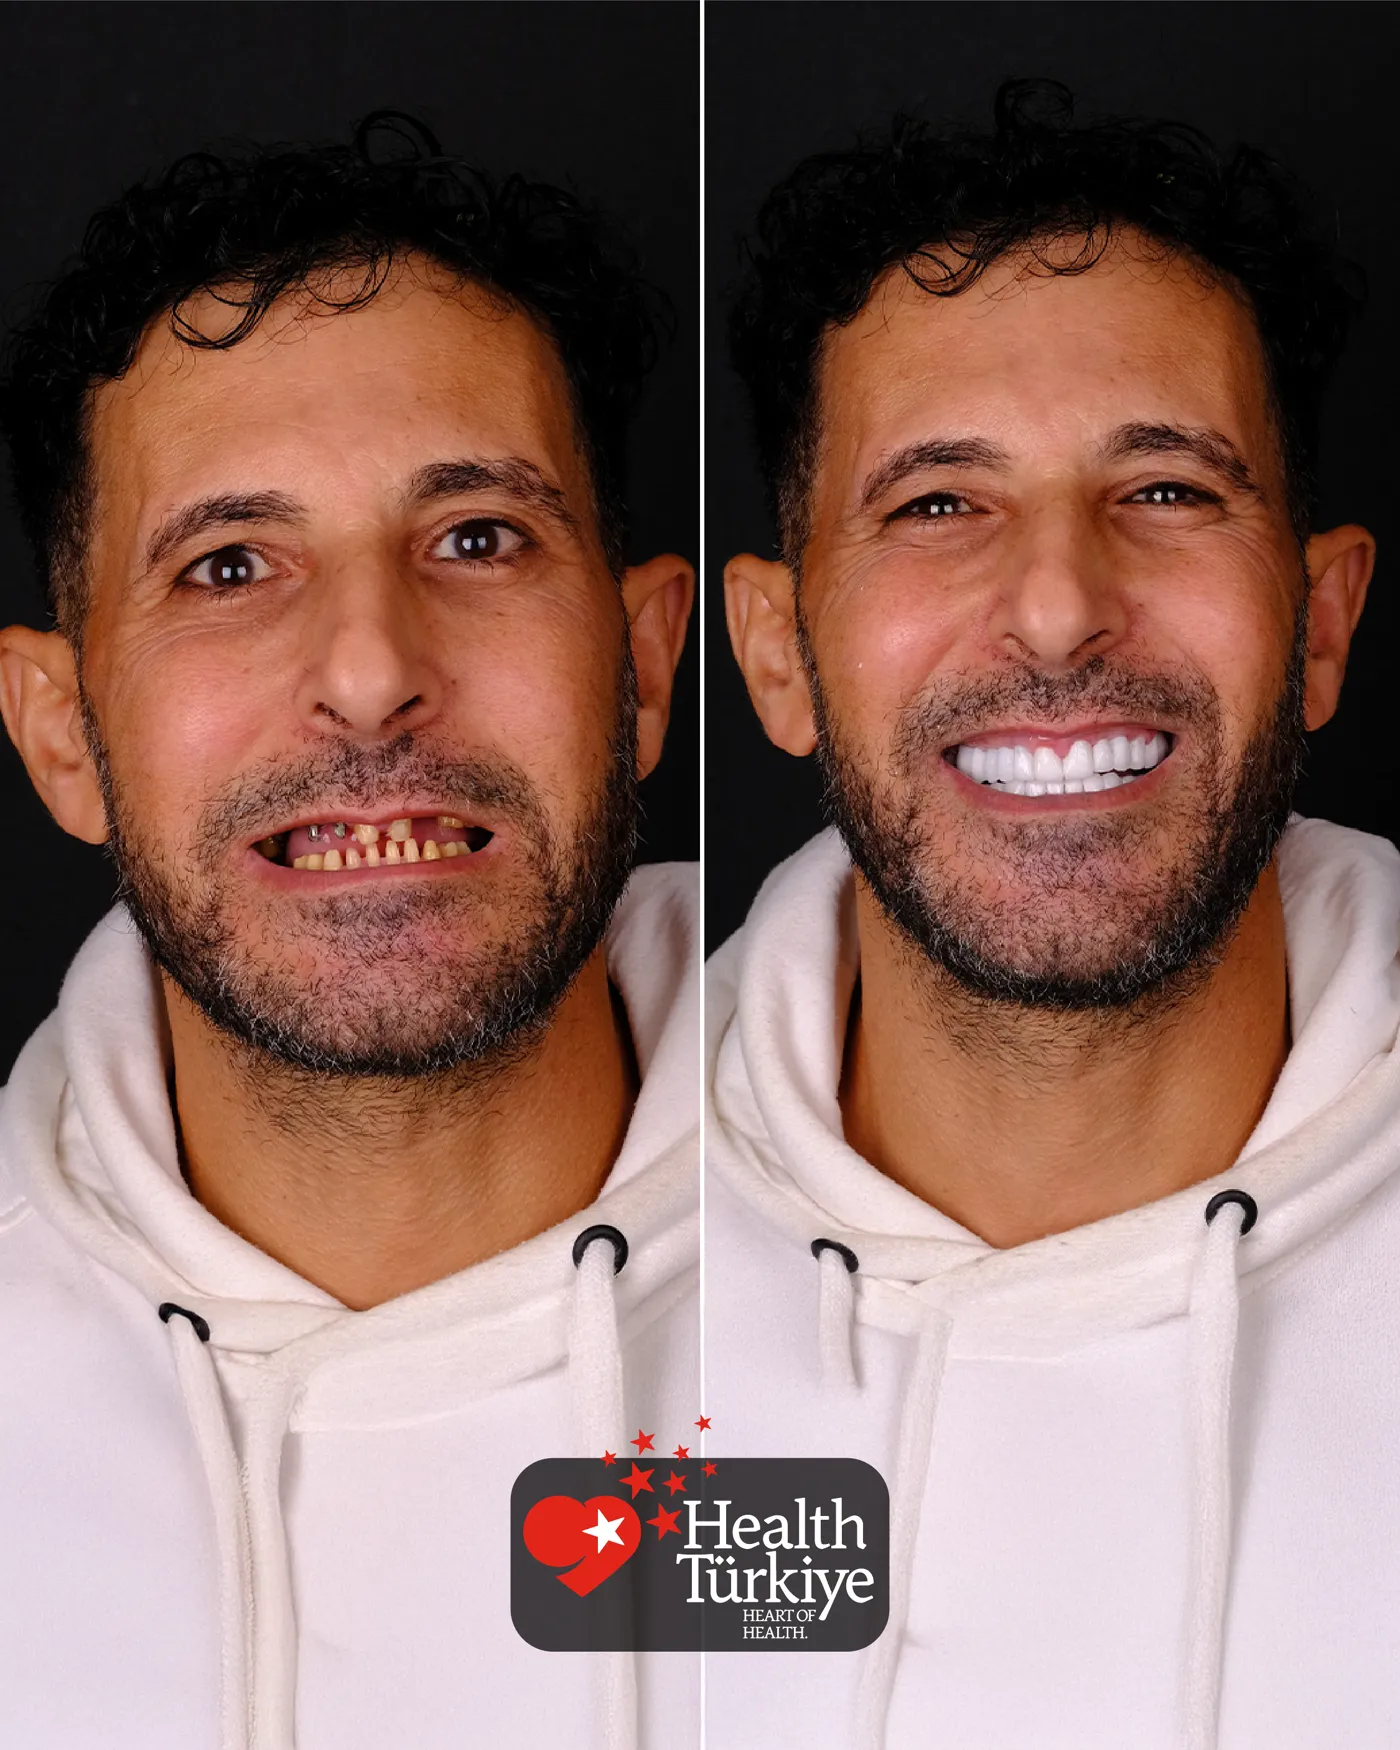
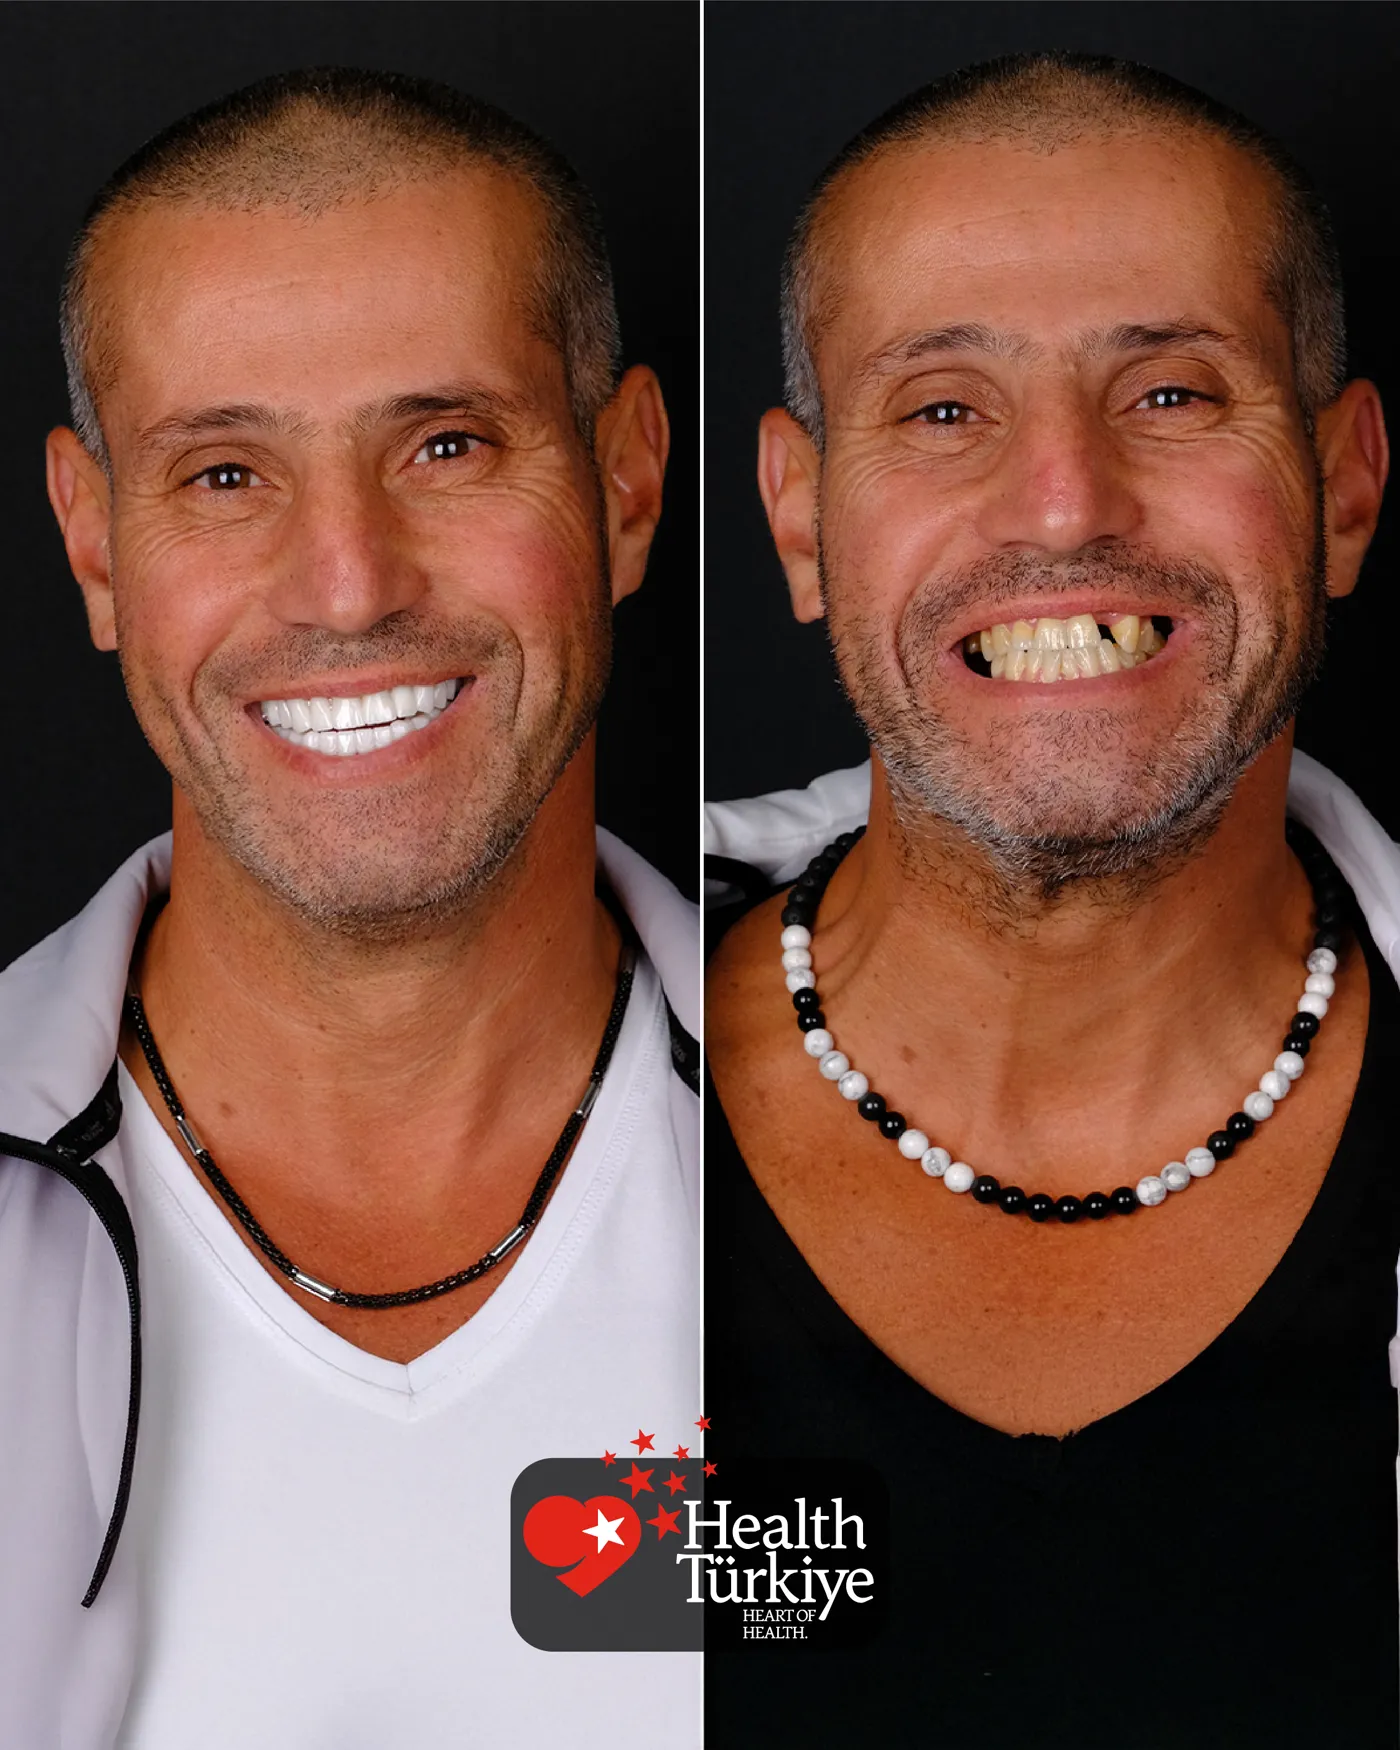
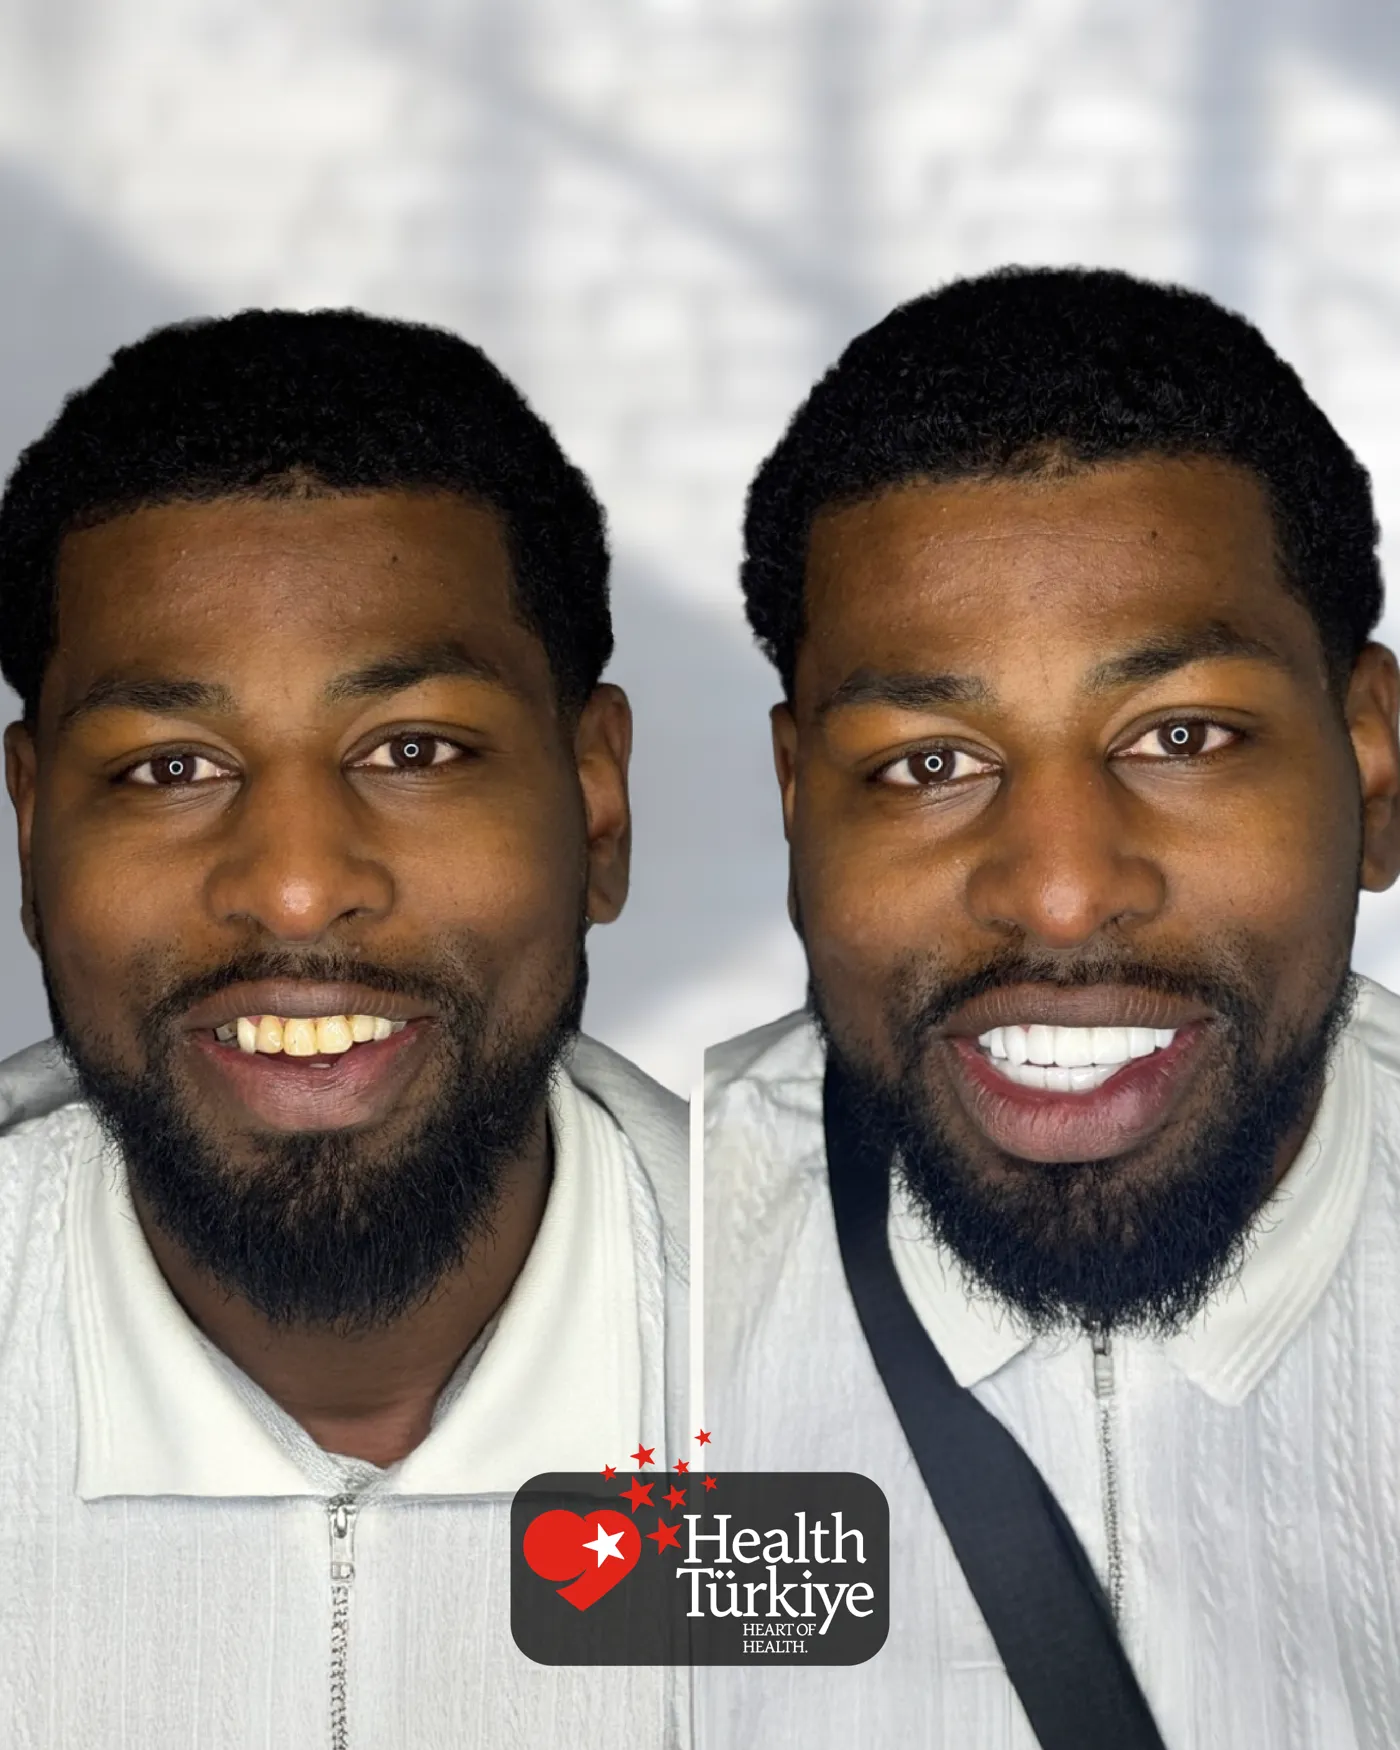
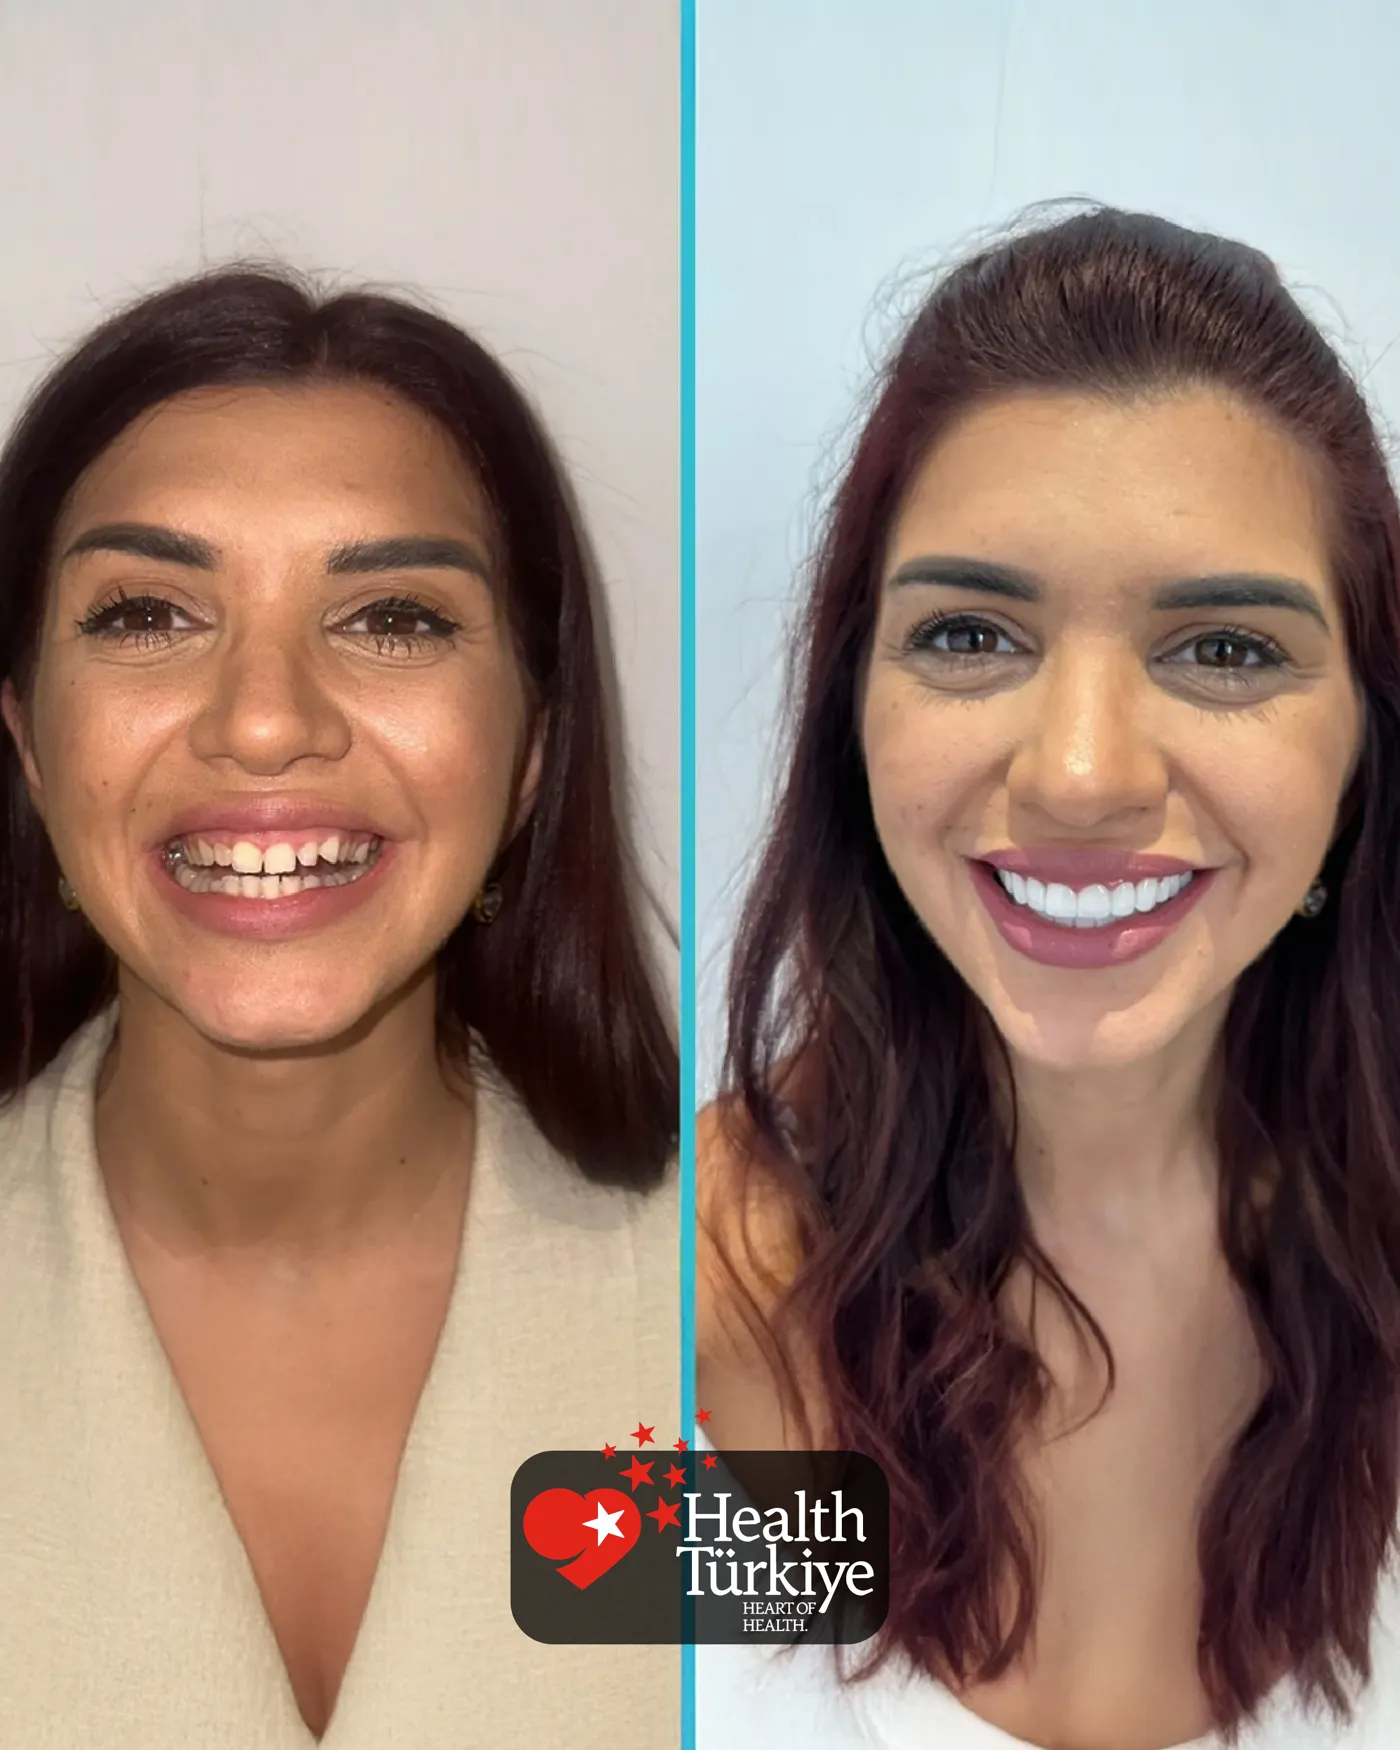
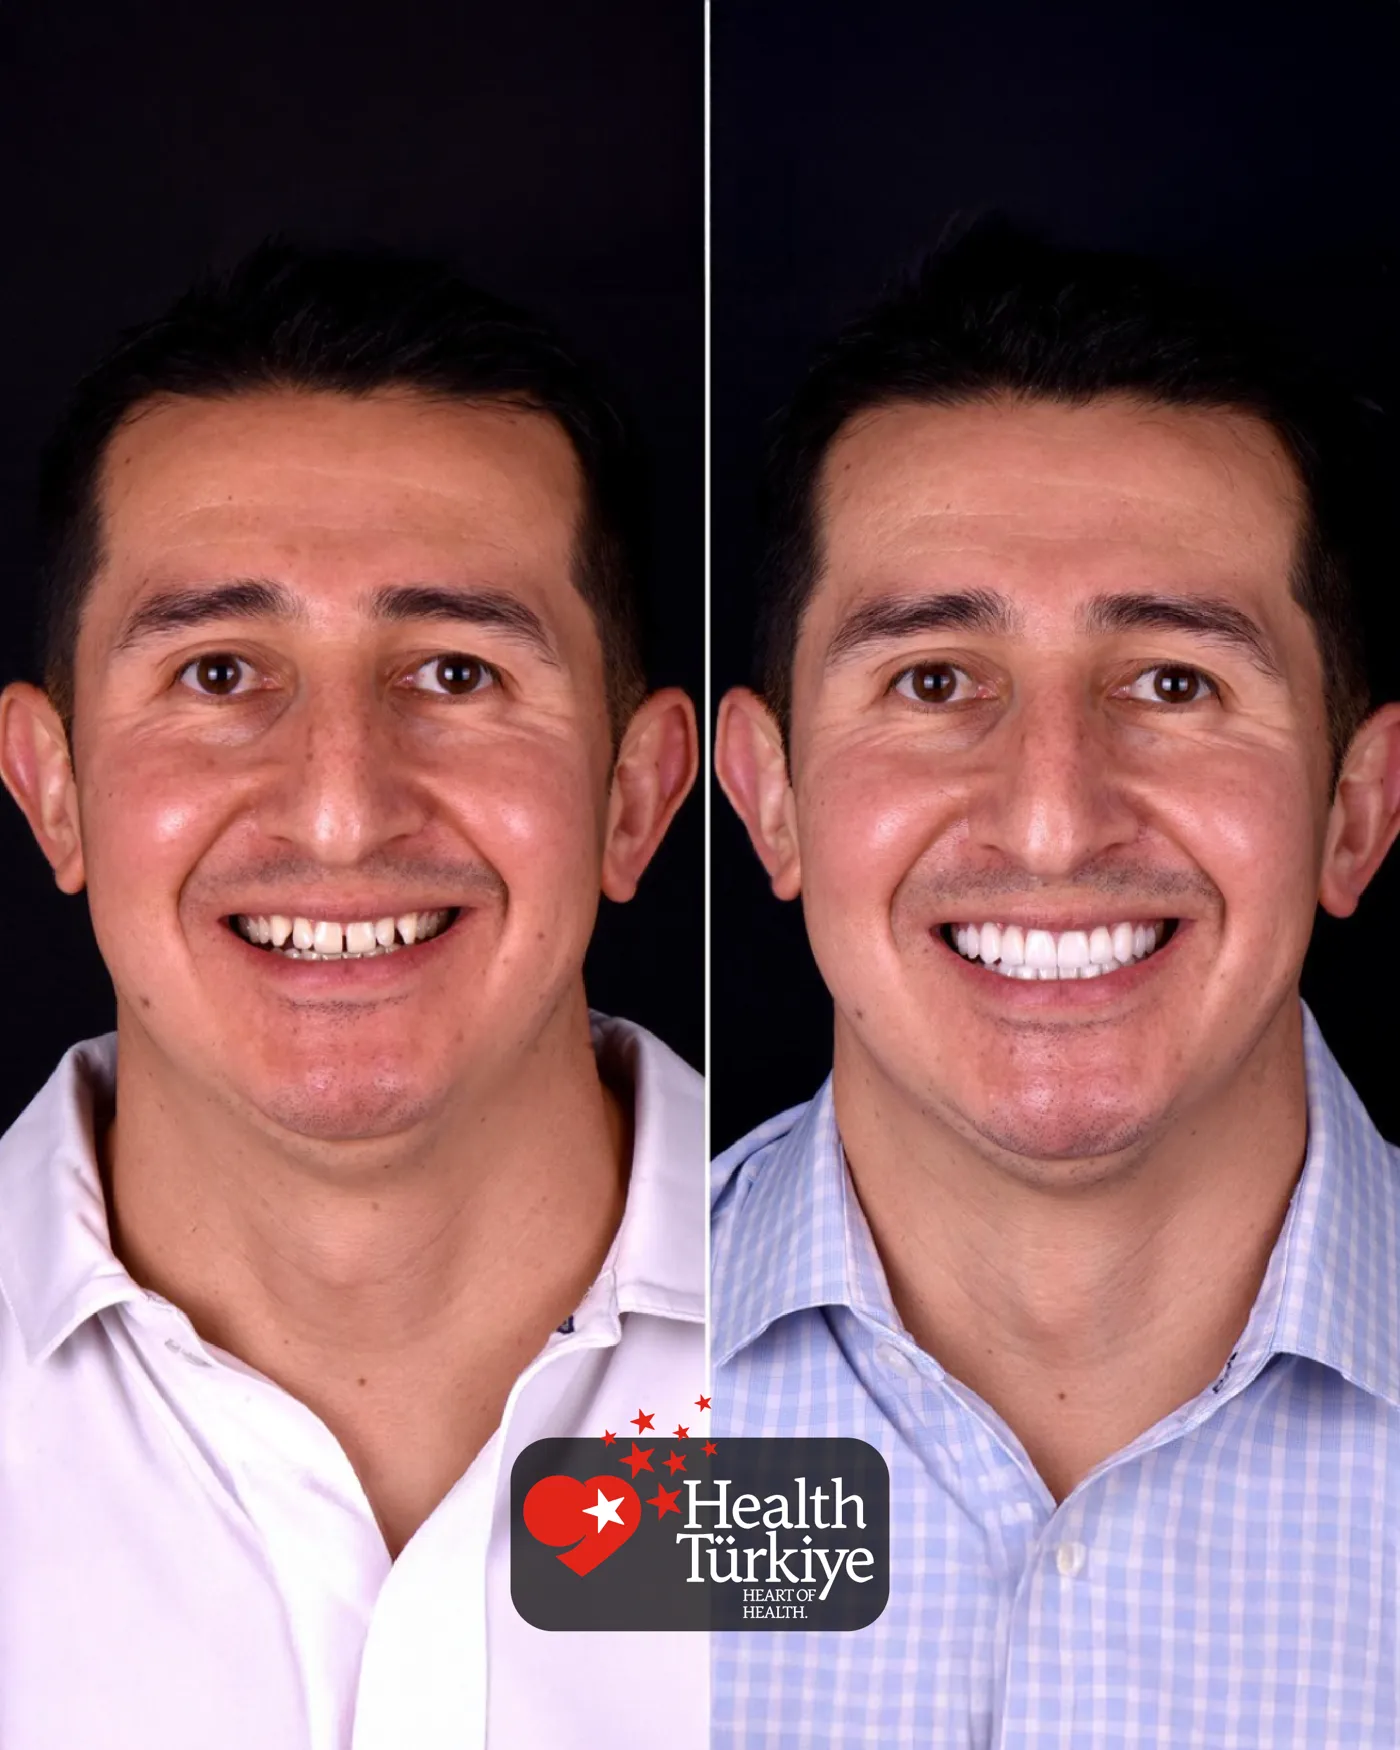
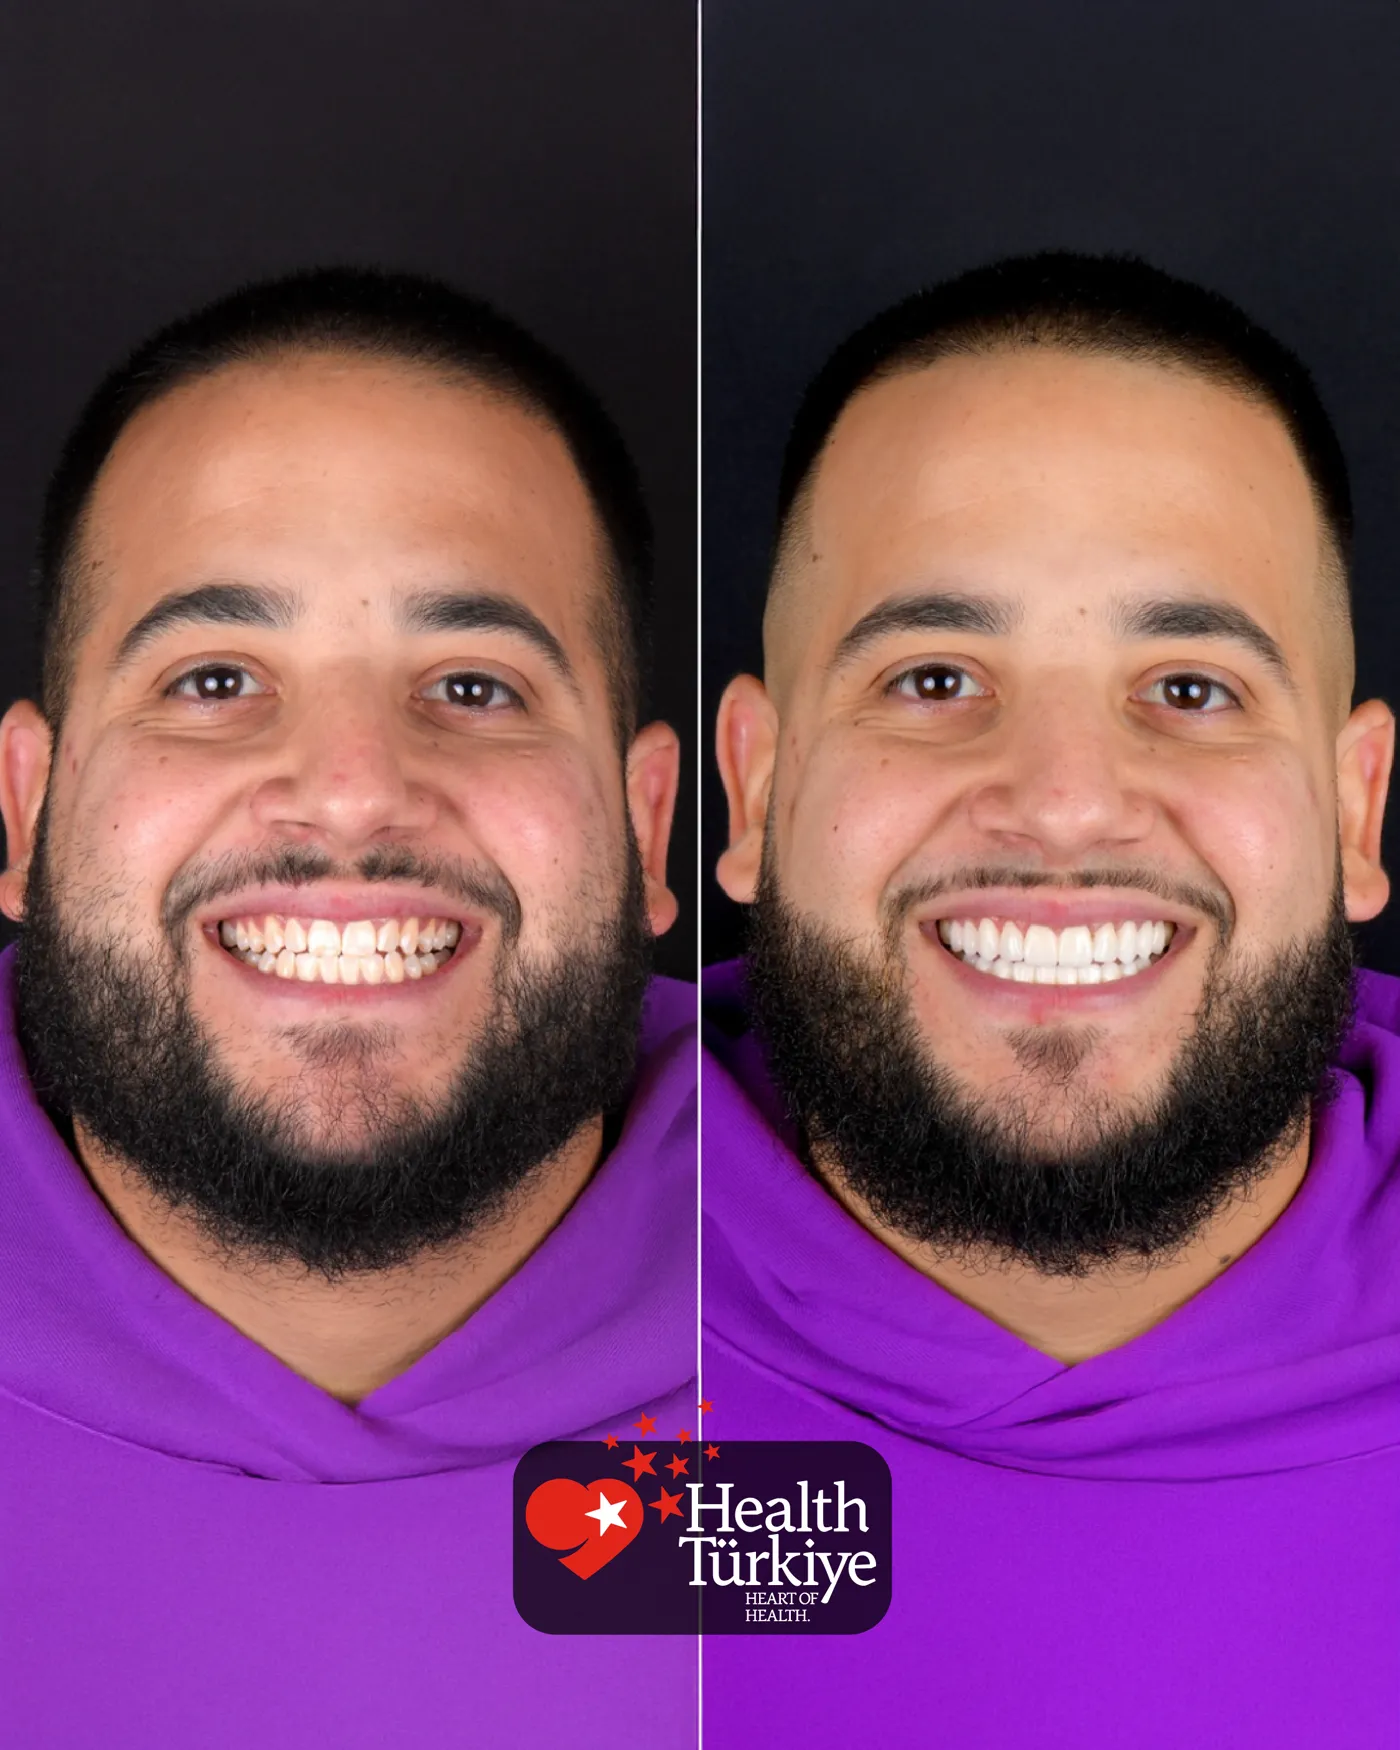
Photos from treatments performed at our clinic

Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
✦ Our Clinic
kliniğimiz
kliniğimiz
kliniğimiz
kliniğimiz

Gum disease is inflammation of the tissues that surround and support the teeth, and one of the most common causes of tooth loss in adults — usually more silent than decay.

It has two stages. Gingivitis affects only the gum and is fully reversible. Untreated, the inflammation reaches the bone and becomes periodontitis, at which point lost bone does not return on its own.

That distinction is why gum treatment should not be postponed.

Signs and Causes of Gum Disease

Because it advances painlessly, most patients present late; recognising the signs allows early treatment.

Signs to watch for

  • Bleeding when brushing or flossing
  • Red, swollen or tender gums
  • Persistent bad breath or taste
  • Receding gums and teeth appearing longer
  • Cold sensitivity from exposed root surfaces
  • Loose teeth or a changing bite
  • Pus discharge from the gum

Plaque and calculus

The primary cause is bacterial plaque, which mineralises into calculus. Its rough surface holds more plaque, cannot be brushed off, and extends into the sulcus to form a pocket where bacteria are sheltered — a self-reinforcing cycle.

Risk factors

Smoking is the strongest risk factor: it constricts vessels and suppresses bleeding, hiding progression and reducing response to treatment. Uncontrolled diabetes impairs healing, and the relationship runs both ways.

Gum recession

Recession is not always inflammatory: hard brushing, poor technique and a stiff brush also cause it. Receded gum does not grow back, and the exposed root is sensitive and prone to decay; grafting may be considered.

Stages of Periodontal Treatment

Treatment is staged, with the response assessed before moving on.

Examination and pocket charting

Pocket depths are measured with a probe and recorded, while a radiograph shows bone level. Together they determine the diagnosis and plan, and are repeated afterwards to measure response objectively.

Scaling

Plaque and calculus are removed with ultrasonic and hand instruments; at the gingivitis stage this is often sufficient. Scaling does not erode teeth — the spaces felt afterwards were already there, filled with calculus.

Root planing

Where pockets have deepened, cleaning extends beneath the gum to the root surface under local anaesthesia, allowing the gum to reattach. Pockets are re-measured weeks later.

Surgical treatment and grafts

Where pockets are too deep for closed treatment, surgical access allows direct cleaning; grafting and guided tissue regeneration may recover some bone in suitable cases.

Maintenance and the Link With General Health

Periodontal treatment is ongoing care, not a one-off procedure.

Why maintenance is essential

Cleaned pockets re-colonise if plaque control lapses, and a previously affected mouth remains at higher risk. Maintenance intervals are set individually, and regular maintenance markedly reduces long-term tooth loss.

Home care

  • Brushing twice daily with a soft brush and correct technique
  • Floss or interdental brushes, since a brush cannot enter between teeth
  • Angling the brush 45 degrees to the gum margin
  • Avoiding hard brushing, which increases recession
  • Cleaning the tongue, a major source of halitosis
  • Stopping smoking, the factor with the greatest effect on outcome

Gum disease and general health

Gum inflammation is a chronic inflammatory focus contributing to the body's overall burden. The link with diabetes is two-way, so periodontal follow-up is part of care for diabetic patients.

Surgical and Supportive Treatment in Advanced Cases

When non-surgical cleaning is not sufficient, surgical approaches address deep pockets and bone loss.

When surgical treatment becomes necessary

Surgery is not the first step: tissues are reassessed after scaling and root planing. Where pockets remain too deep to clean, the gum is reflected to give direct access to the root surface and repositioned, creating an area that can actually be maintained.

Gum and bone grafts

In suitable defects, grafts and barrier membranes are used to regain lost bone; defect shape determines what is achievable. Connective tissue grafts can cover exposed roots where recession causes sensitivity or aesthetic concern. Controlled inflammation and not smoking strongly affect the outcome.

Gum problems around implants

Implants do not decay, but surrounding tissues react to plaque: peri-implant mucositis involves bleeding and swelling, while peri-implantitis adds bone loss. Early detection allows management with cleaning and hygiene changes; advanced cases require surgery.

Home Care: Correct Technique and Common Mistakes

The durability of clinical treatment depends largely on daily care between appointments.

Brushing technique and duration

The target zone is the margin where tooth meets gum: place the brush at about 45 degrees and use small vibratory strokes. Hard pressure does not clean better — it causes recession and abrasion. Around two minutes, evenly distributed, with a soft to medium brush.

Why interdental cleaning is indispensable

A brush cannot reach the surfaces between teeth, where gum inflammation typically begins. Floss suits tight contacts; interdental brushes suit wider spaces, and the correct size should be selected professionally. Early slight bleeding reflects inflammation and reduces with regular cleaning.

Common mistakes in gum care

  • Stopping brushing an area because it bleeds
  • Using a hard brush with heavy horizontal scrubbing
  • Skipping interdental cleaning altogether
  • Treating mouthwash as a substitute for brushing
  • Forcing toothpicks into the gum
  • Abandoning maintenance visits once symptoms subside
  • Requesting scaling only when calculus becomes visible

✦ SSS

Frequently Asked Questions 30

01

How many visits does gum treatment take?

It depends on the extent. Surface scaling is usually completed in one visit. Where there are deep pockets, the mouth is divided into areas and root planing is done over several visits, each under local anaesthetic. The number is given to you after the pockets are measured.
02

Do the teeth look longer after treatment?

As the inflammation resolves, swollen gum returns to its normal volume and a little more root surface can become visible. This is not a loss caused by the treatment but the existing situation, hidden by the inflammation, becoming apparent. Untreated, the loss would have continued and the result been far more marked.
03

Are root planing and scaling the same thing?

No. Scaling removes calculus from the visible surfaces and the gum margin. Root planing goes into the pocket to clean the bacterial layer and hardened deposits from the root surface, and requires local anaesthetic. The second is for deep pockets, where scaling alone is not enough.
04

Does bleeding stop completely after gum treatment?

With a good result it does; bleeding stopping is the most concrete measure of the treatment's success. If it continues, either home care is inadequate or a deep area remains unreachable. The pockets are then measured again and a surgical approach considered if necessary.
05

When is gum surgery needed?

Where pockets remain deep despite root planing, where a bone defect needs correcting, and where the area between the roots of a multi-rooted tooth cannot be reached. The aim is to gain access to an area that cannot be cleaned and, where possible, to improve the bony support. The decision rests on measurements and radiographs.
06

Is gum disease contagious?

The disease itself is not contagious, but the bacteria that cause it can pass through close contact. That transfer alone does not create disease; what decides is the person's immune response, oral hygiene, smoking and genetic susceptibility. Several family members being affected is usually explained by shared habits.
07

Can gum treatment be done during pregnancy?

It can be, and usually should be: gum inflammation increases with hormonal change in pregnancy and advances if untreated. The second trimester is the most suitable period. Tell us that you are pregnant and how many weeks; the timing and, where needed, the choice of medication follow from that.
08

Does a water flosser replace gum treatment?

It does not. A water flosser removes food debris and loose plaque; it cannot lift hardened calculus and cannot reach the bacterial layer inside a deep pocket. It is a valuable aid in maintenance after treatment, particularly around implants and bridges, but it does not replace professional cleaning.
09

How often is maintenance needed after gum treatment?

Periodontal treatment is not a one-off procedure but an ongoing programme. The maintenance interval is usually three to six months and is set by pocket depth, smoking and the quality of home care. When the programme is followed, the disease can be held in check for many years.
10

How long does gum disease take to cause tooth loss?

It takes years and varies greatly from person to person. That slowness is in fact the source of the danger: because progression is painless, patients do not notice and the loss accumulates silently. In smokers and in uncontrolled diabetes the process is markedly faster.
11

Is bleeding gums normal?

No. Healthy gums do not bleed when brushed; bleeding is the earliest sign of inflammation and fully reversible at that stage.
12

Does scaling damage the teeth?

No — this is a common misconception. The ultrasonic tips break up the calculus without eroding the enamel. The gaps you feel afterwards were already there, hidden under the deposit; cleaning reveals them rather than creating them. Leaving the calculus in place is what actually causes damage, through recession and bone loss.
13

Does receded gum grow back?

Receded gum does not grow back on its own. What can be done is to halt the progression, which is achievable in most cases, and in suitable cases to cover the exposed root with a gum graft. This is why acting early matters — the tissue you still have is easier to keep than to rebuild.
14

Is gum treatment painful?

Scaling is usually painless, and local anaesthetic can be used for those with sensitive teeth. Root planing, which cleans below the gum line, is carried out under local anaesthetic. Some sensitivity for a few days afterwards is normal as the exposed surfaces settle.
15

Can gum disease cause tooth loss?

Yes — it is one of the most common causes of adult tooth loss. A tooth that looks intact can be lost because the bone beneath has resorbed.
16

How often should I have my teeth scaled?

It varies with calculus formation rate, smoking, systemic conditions and home care; previously treated patients need shorter intervals.
17

How does smoking affect gum treatment?

Smoking impairs blood flow and tissue repair in the gums, masking warning signs such as bleeding while disease progresses. Response to treatment is generally weaker and surgical healing slower; stopping or reducing directly supports the outcome.
18

Can mouthwash replace brushing?

No. Rinses cannot mechanically disrupt the plaque biofilm; they only temporarily reduce surface bacteria. Antiseptic rinses are prescribed for limited periods, for example after surgery, and long-term use may cause staining and taste changes.
19

Is gum disease contagious?

The bacteria involved can be transmitted through saliva, but bacteria alone do not cause disease — hygiene, smoking, general health and immune response determine susceptibility. Clustering within families usually reflects shared habits and risk factors.
20

Does gum recession cause sensitivity?

Yes. Recession exposes root surfaces that lack enamel and react to hot, cold and sweet stimuli. Desensitising pastes, varnishes or composite coverage can help, but if aggressive brushing caused the recession, technique must be corrected first.
21

I was told I have decay between my teeth, but I cannot see anything in the mirror. How is that possible?

This is very common. The surfaces where two teeth touch cannot be seen with the eye, so decay spreads under the enamel while the tooth still looks intact. Such cavities are usually found on bitewing X-rays, or suspected when floss shreds and food packs into that spot. Early detection matters, because interproximal decay can also reach the neighbouring tooth.
22

How do you tell whether decay has reached the nerve?

It is judged from several findings together, not one symptom. The dentist measures the depth on an X-ray, watches how long the tooth reacts to a cold test, and taps it gently to check for inflammation at the root tip. Sensitivity lasting a few seconds usually suggests a vital, treatable nerve, while spontaneous throbbing may mean irreversible damage. Often the final decision is made while the decay is being removed.
23

If decay is at an early stage, can it be stopped without a filling?

Sometimes, at a very early stage. Chalky white spots where the enamel surface is still intact can remineralise with fluoride, proper brushing, interdental cleaning and fewer sugary or acidic exposures. Once the surface has collapsed into a real cavity, however, it cannot repair itself and needs a filling. An examination and X-ray decide which group your tooth belongs to.
24

Should I have a white filling or is a silver one stronger?

It depends on the tooth, how much structure is lost and your bite forces. Tooth-coloured composite bonds to the tooth, so less healthy tissue is removed, and it looks natural; it is widely used today in both front and back teeth. When a molar has lost a lot of structure, an inlay, onlay or crown may serve better than a filling. Your dentist compares the options after examining the tooth.
25

How many years will my filling last, does it stay for life?

Fillings are long-lasting restorations rather than permanent ones, and they are expected to be renewed one day. Size, position in the mouth, bite force, night-time clenching and oral hygiene all affect their lifespan. Small, well-cleaned fillings can serve for many years, while very large ones may fracture or leak sooner. Regular check-ups let a worn filling be replaced before the problem grows.
26

After my filling the tooth stings with cold water. Did something go wrong?

In most cases this is expected. Removing decay irritates the nerve, so brief cold sensitivity for a few days or weeks is common, and longer after a deep filling. What matters is that it steadily decreases. If the pain lingers for minutes after the cold is gone, starts on its own, wakes you at night or appears on biting, the tooth should be re-checked.
27

Since my filling, that tooth hits first when I close my mouth. Will it wear down by itself?

Do not wait for it to wear down; the adjustment takes only a few minutes. While you are still numb the bite feels unreliable, so a filling can be left slightly high. A high filling loads all the chewing force onto one tooth, causing pain on biting, a loose feeling, jaw muscle fatigue and even fracture. Marking the contacts with articulating paper and trimming them usually relieves it quickly.
28

My filling fell out while eating and there is no pain. Do I need to come in right away?

Even without pain, book an appointment soon. The exposed tooth tissue is unprotected, food packs into the gap and decay can deepen quickly toward the nerve. The weakened walls may also fracture while chewing, which turns a simple repair into a bigger treatment. Keep the area clean with gentle brushing, avoid chewing hard food on that side, and have the tooth checked promptly.
29

How long after a filling can I eat?

Tooth-coloured composite fillings are light-cured, so they are technically ready for chewing straight away. What you really wait for is the numbness to wear off, because biting your cheek or tongue while numb is very common. Avoid very hard or sticky food on the first day, and if the tooth feels sensitive, skip very hot and cold drinks for a while.
30

A temporary filling was placed in my tooth. How long can I manage with it?

Temporary fillings are designed only to protect the tooth during treatment, usually for a matter of weeks. The material is softer than a permanent filling, so it wears, can leak at the edges and let bacteria back in. Keep your next appointment, avoid hard and sticky food on that side, and slide floss out sideways there. Tell us if it breaks or falls out.

From Our Blog

✦ Our Brands
Straumann
Nobel Biocare
Astra Tech
Medentika
Bredent SKY
Straumann
Nobel Biocare
Astra Tech
Medentika
Bredent SKY
✦ Contact
Get in touch

Antalya Muratpaşa our central clinic

Sair Adem Dede St. No:31, 07030 Muratpasa / Antalya, Türkiye

Open in Google Maps