




























Patient Reviews 4.9/5 10.000+ Happy Patients 37 Countries

Dentures in Antalya — Removable and Fixed Prosthetics

✦ Tedaviler

Dentures in Antalya — Removable and Fixed Prosthetics

Dentures in Muratpasa, Antalya: complete, partial and implant-supported prosthetics with a planned process from impression to fitting.

✦ Our Patients

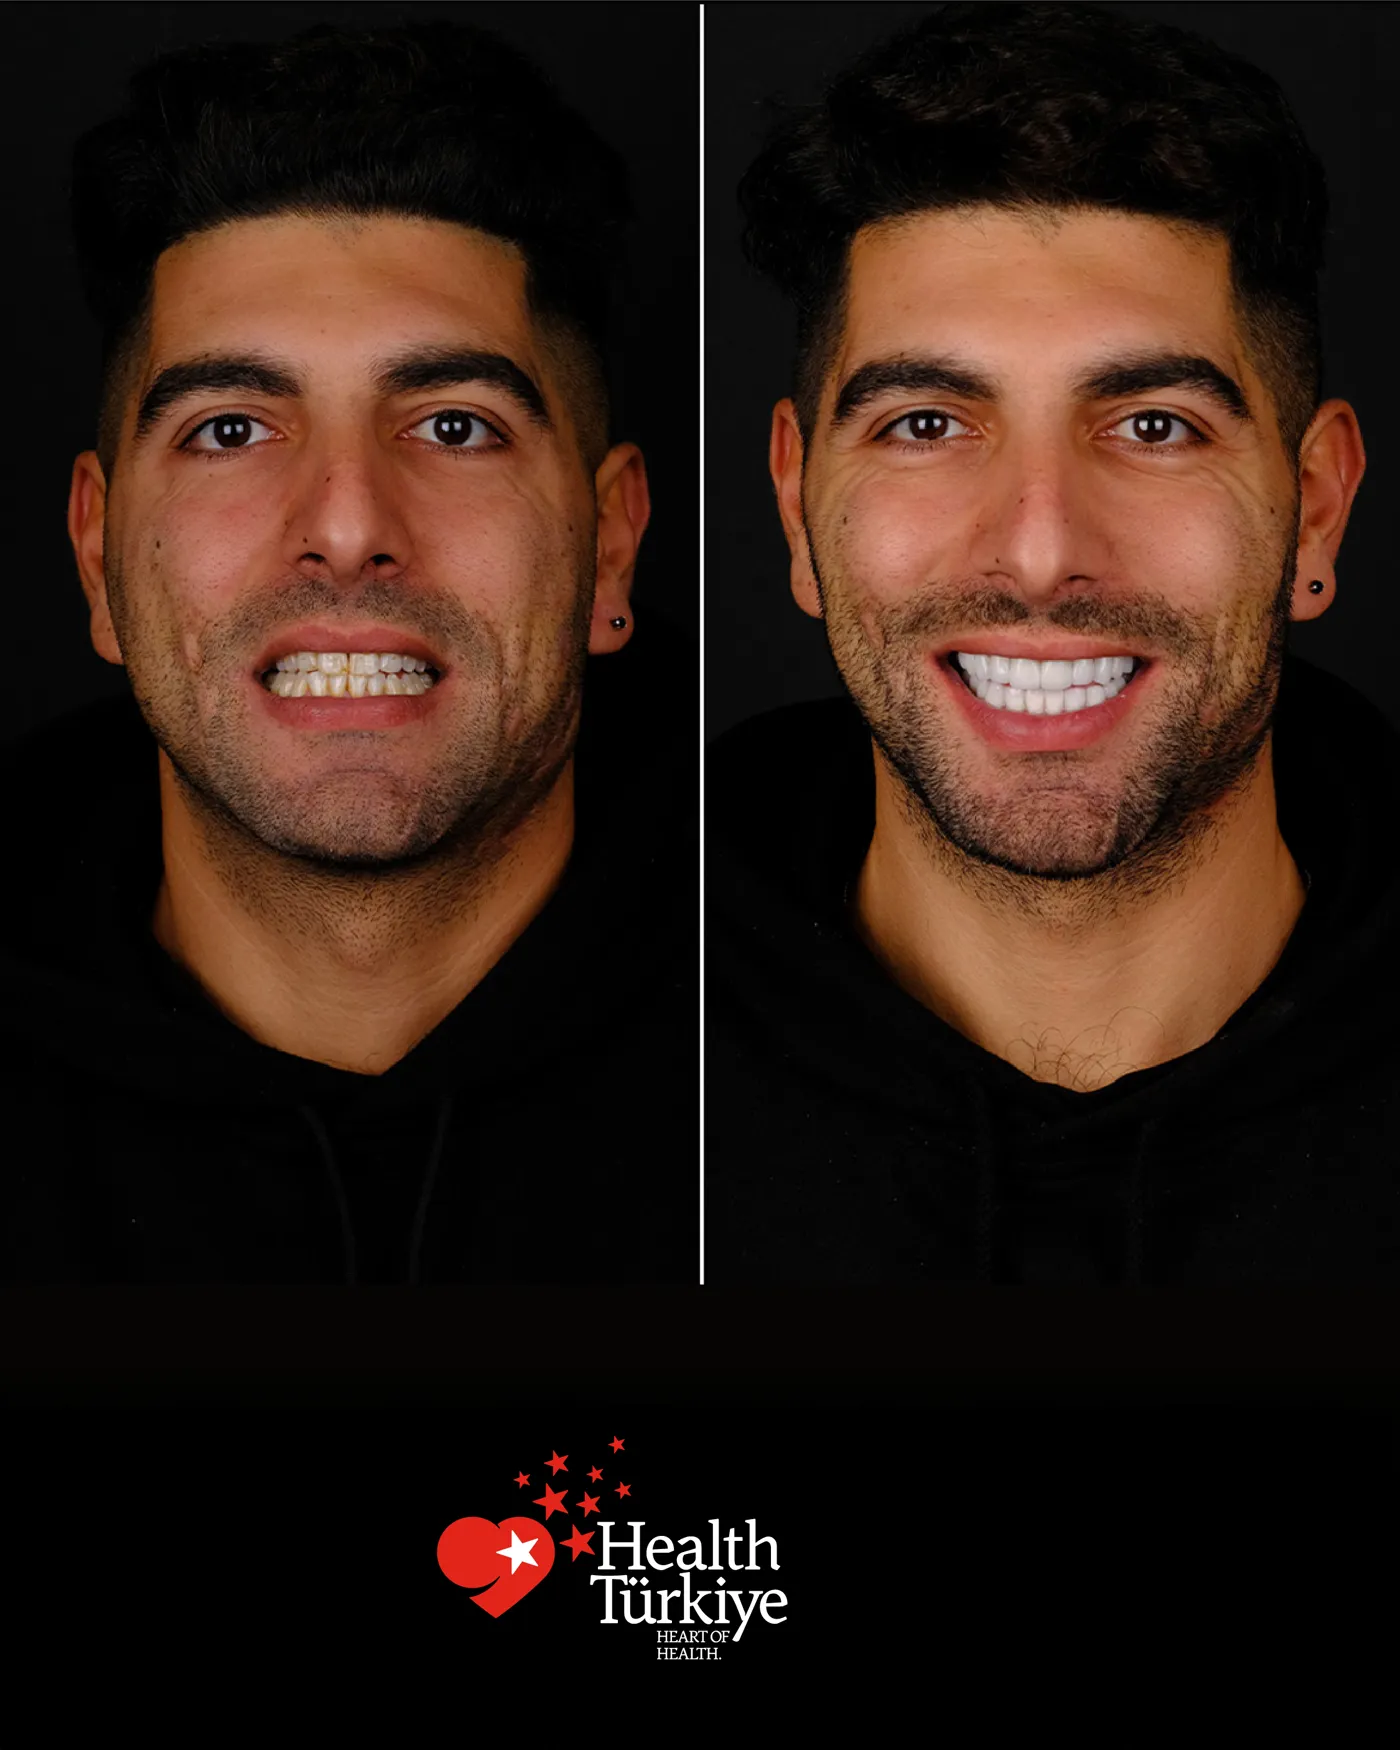
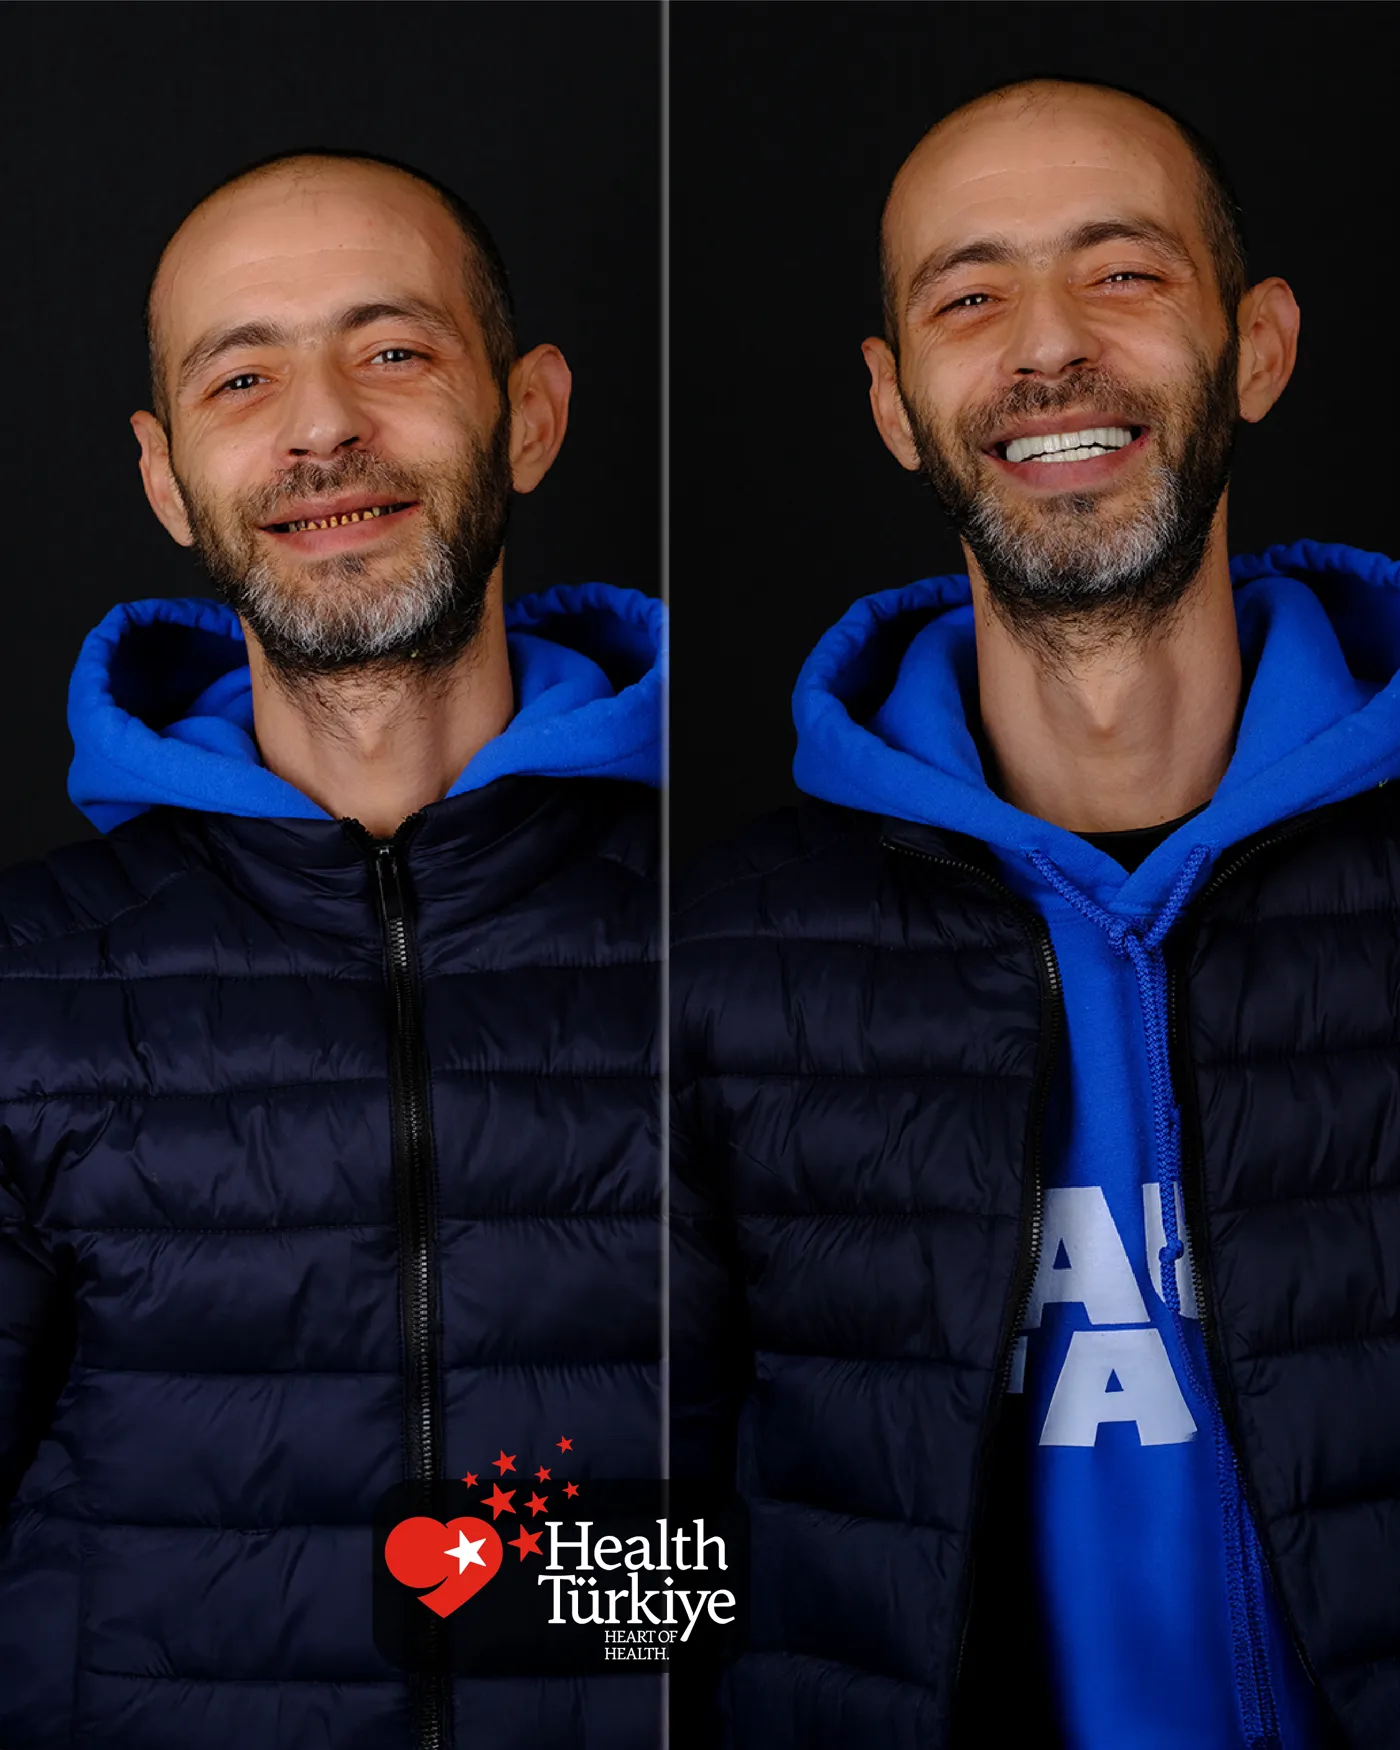
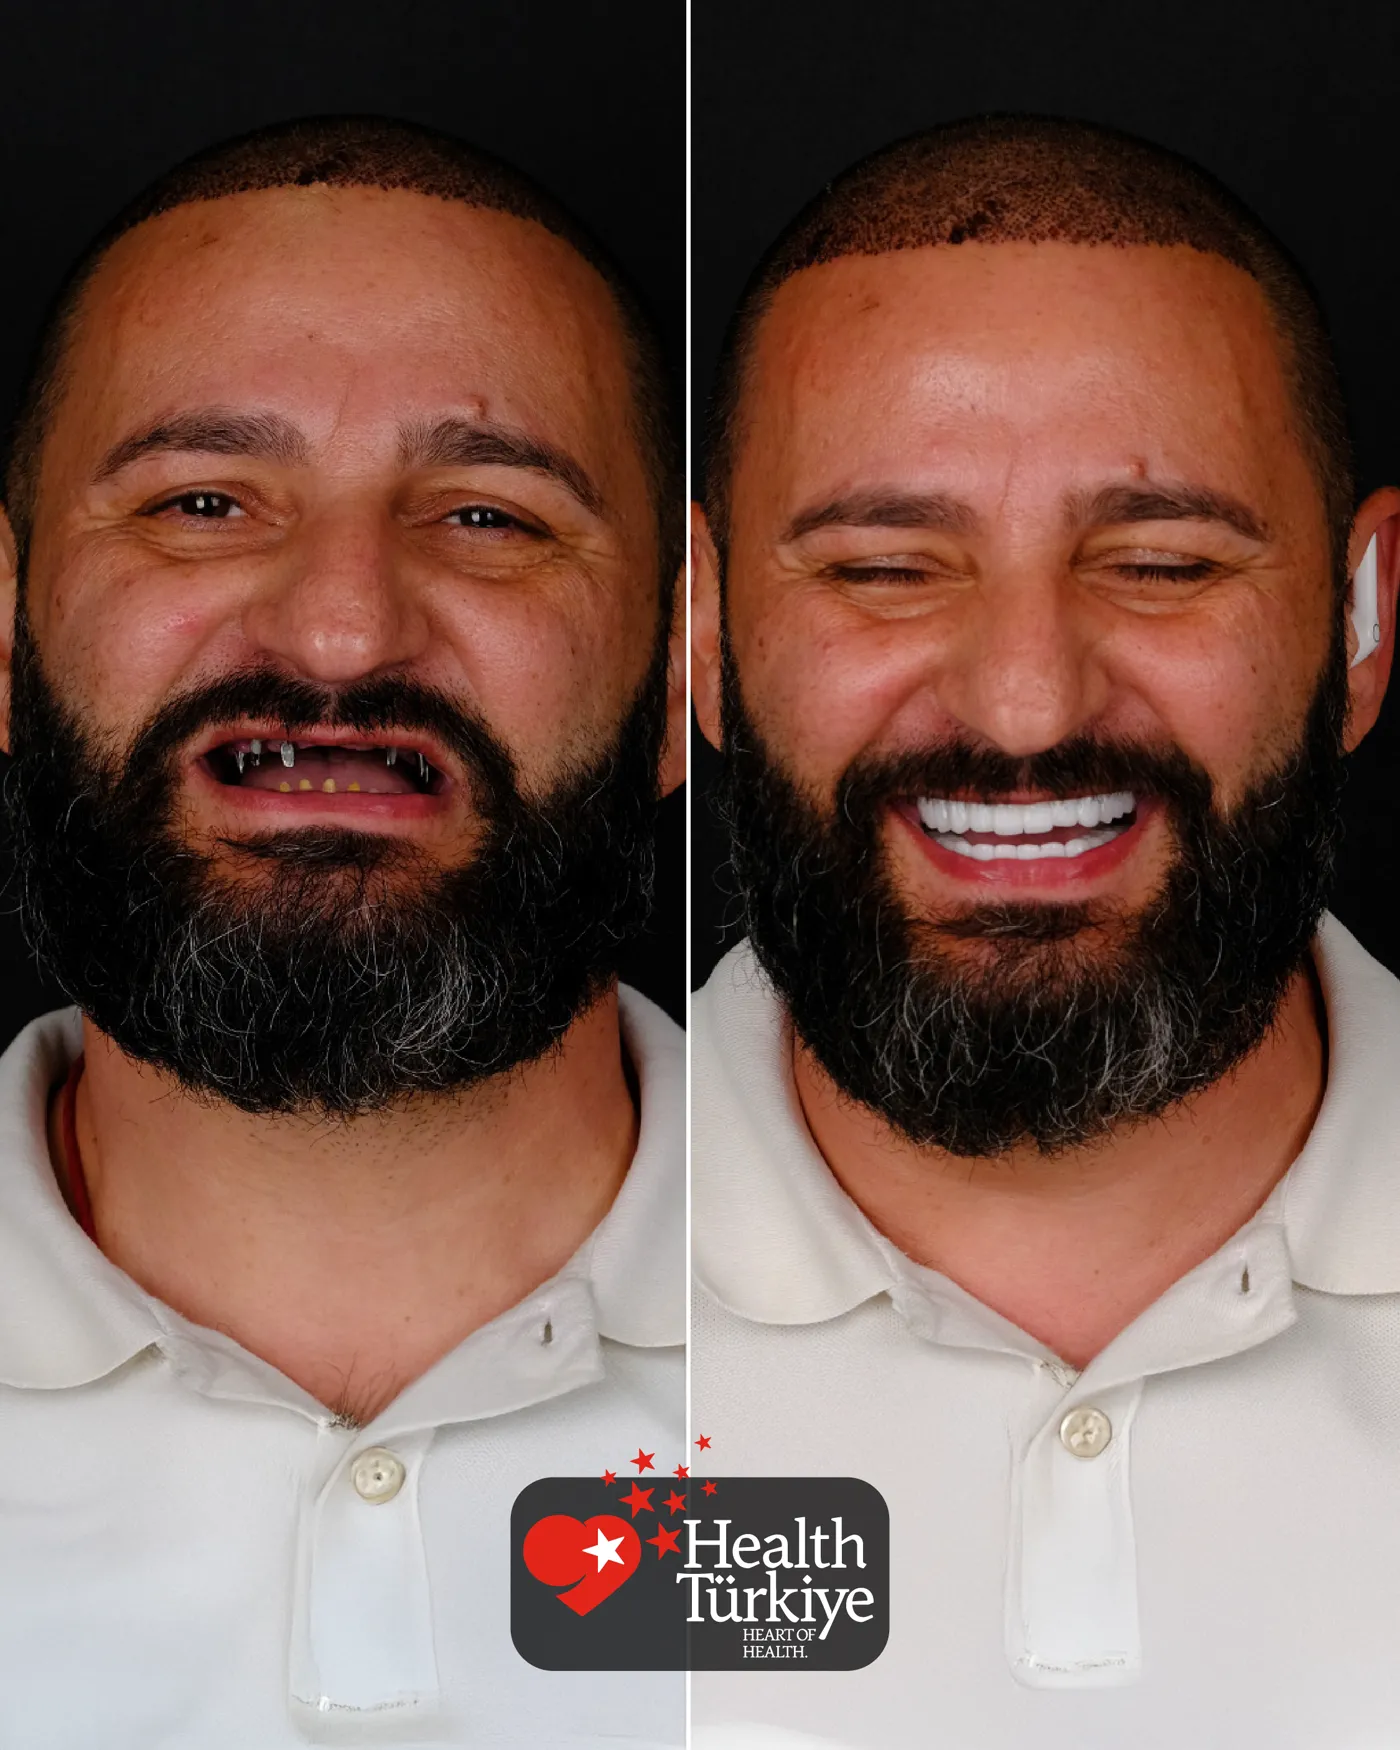
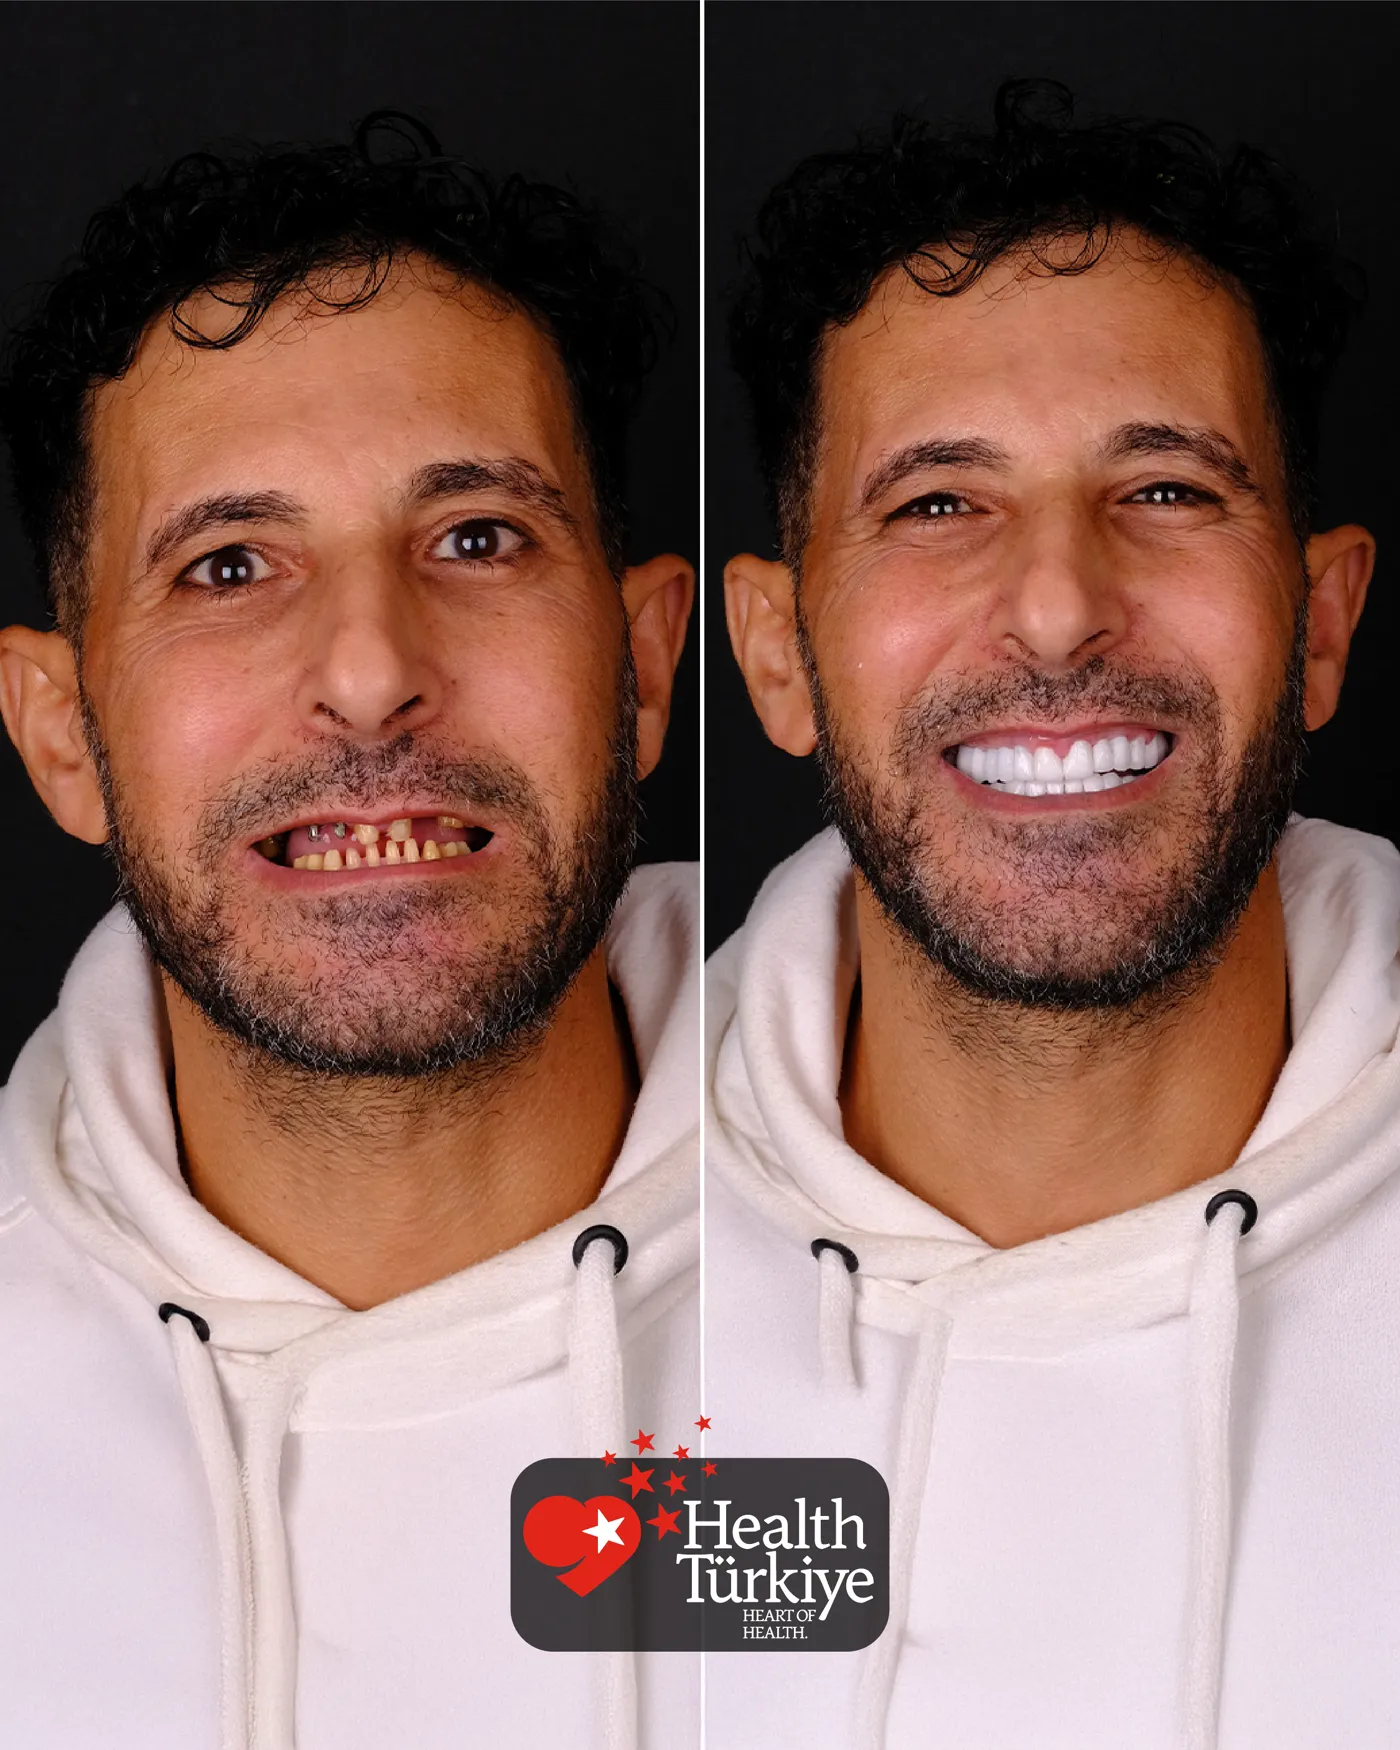
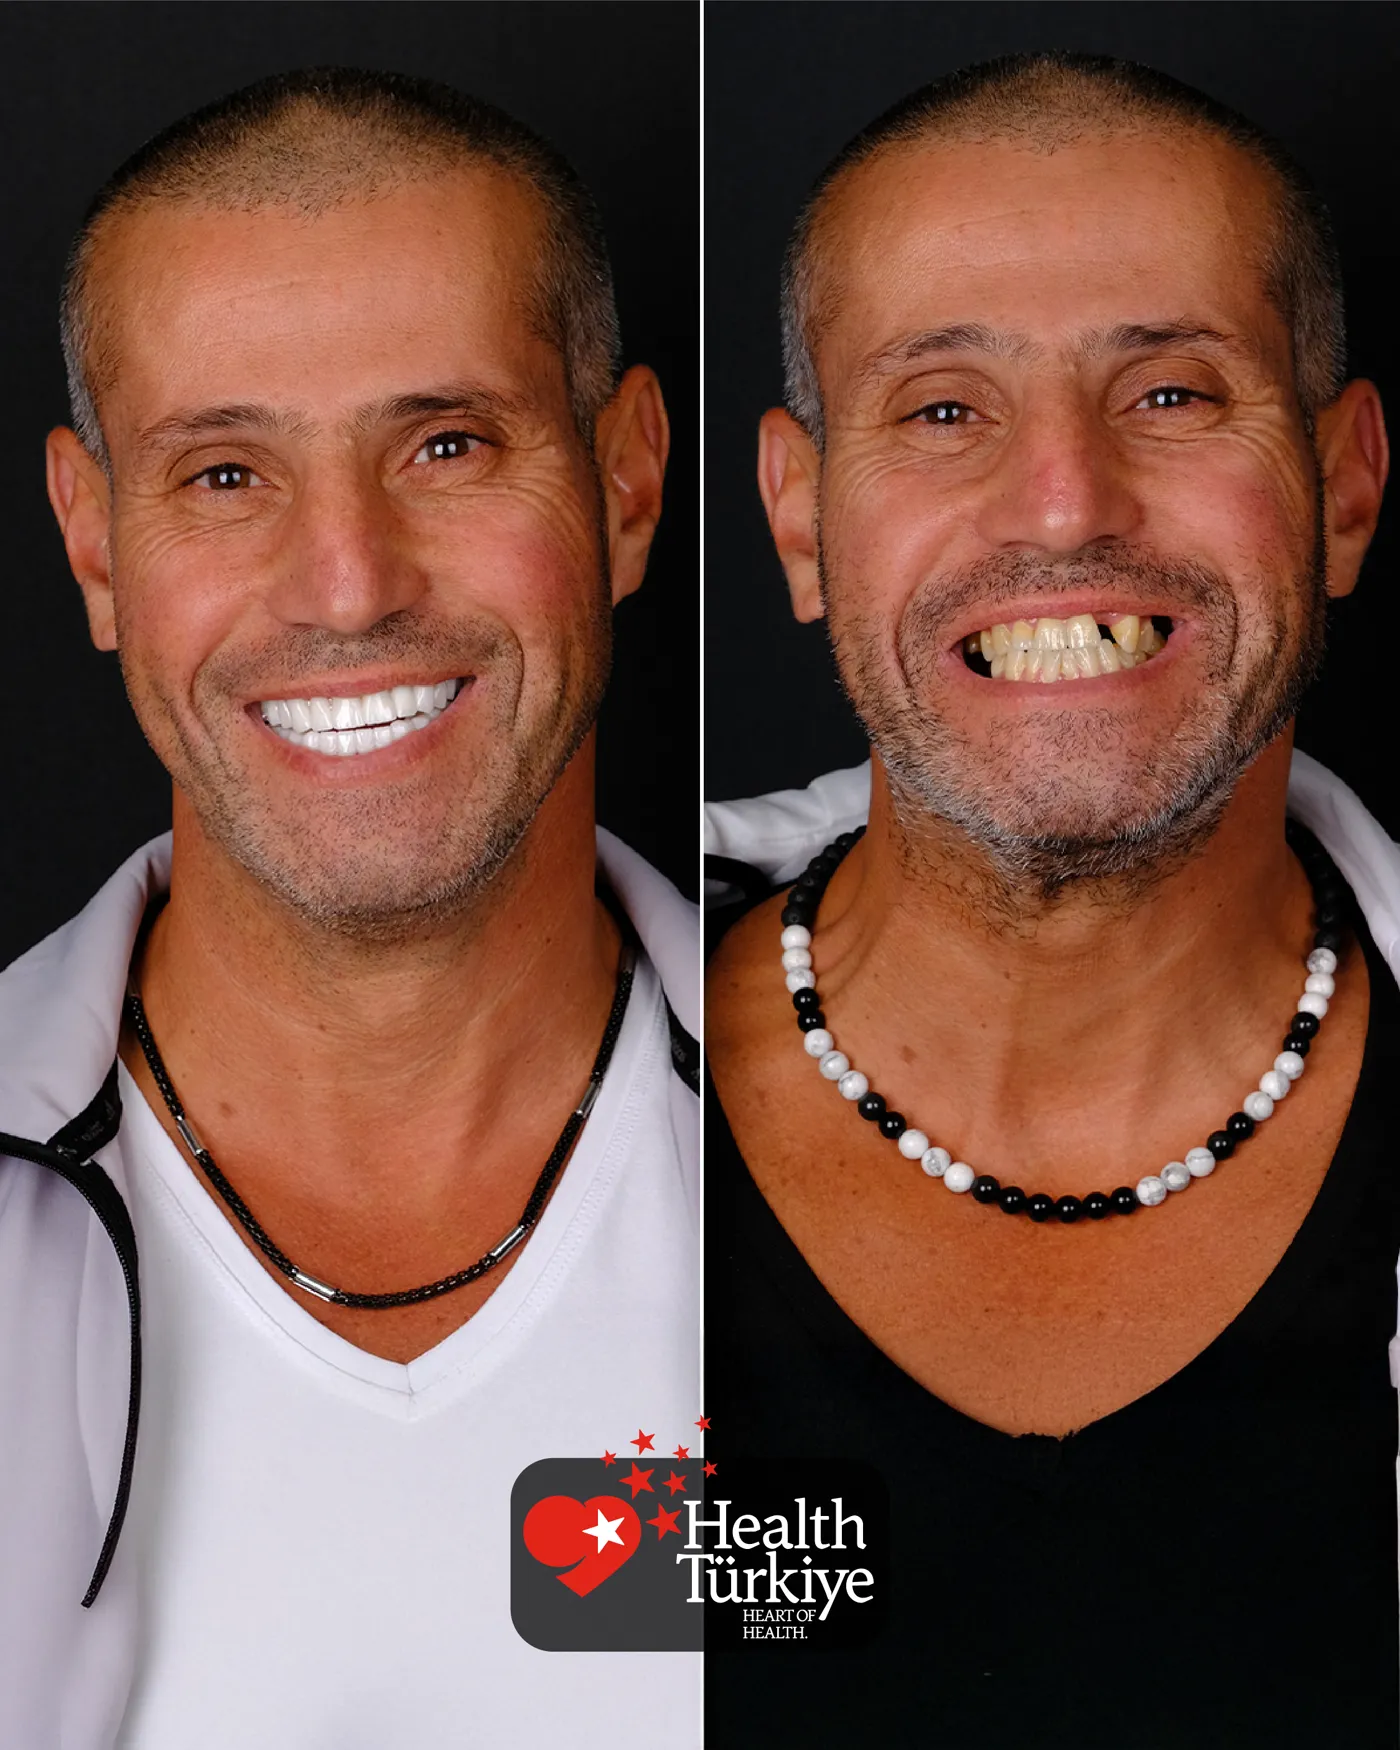
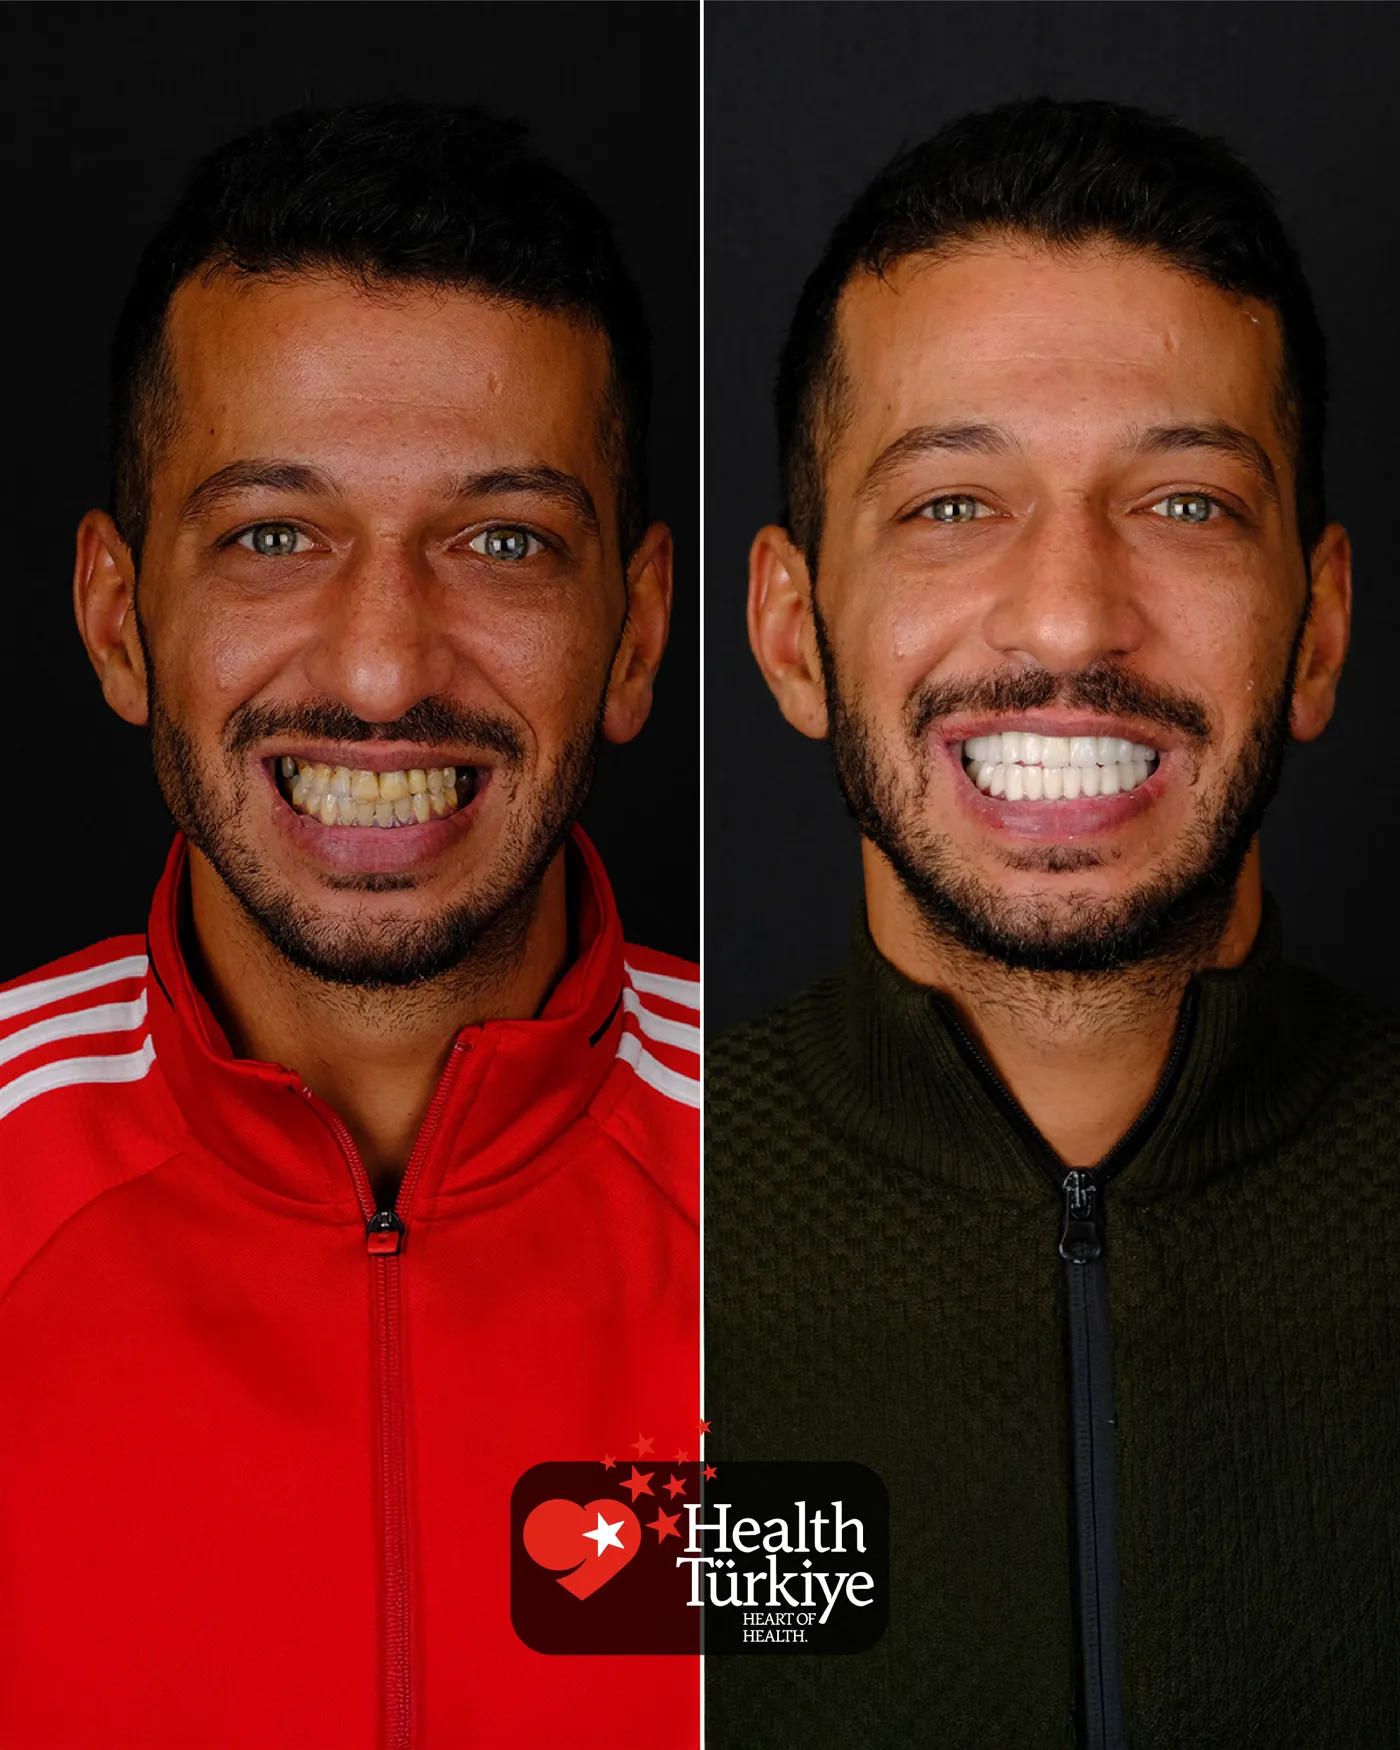
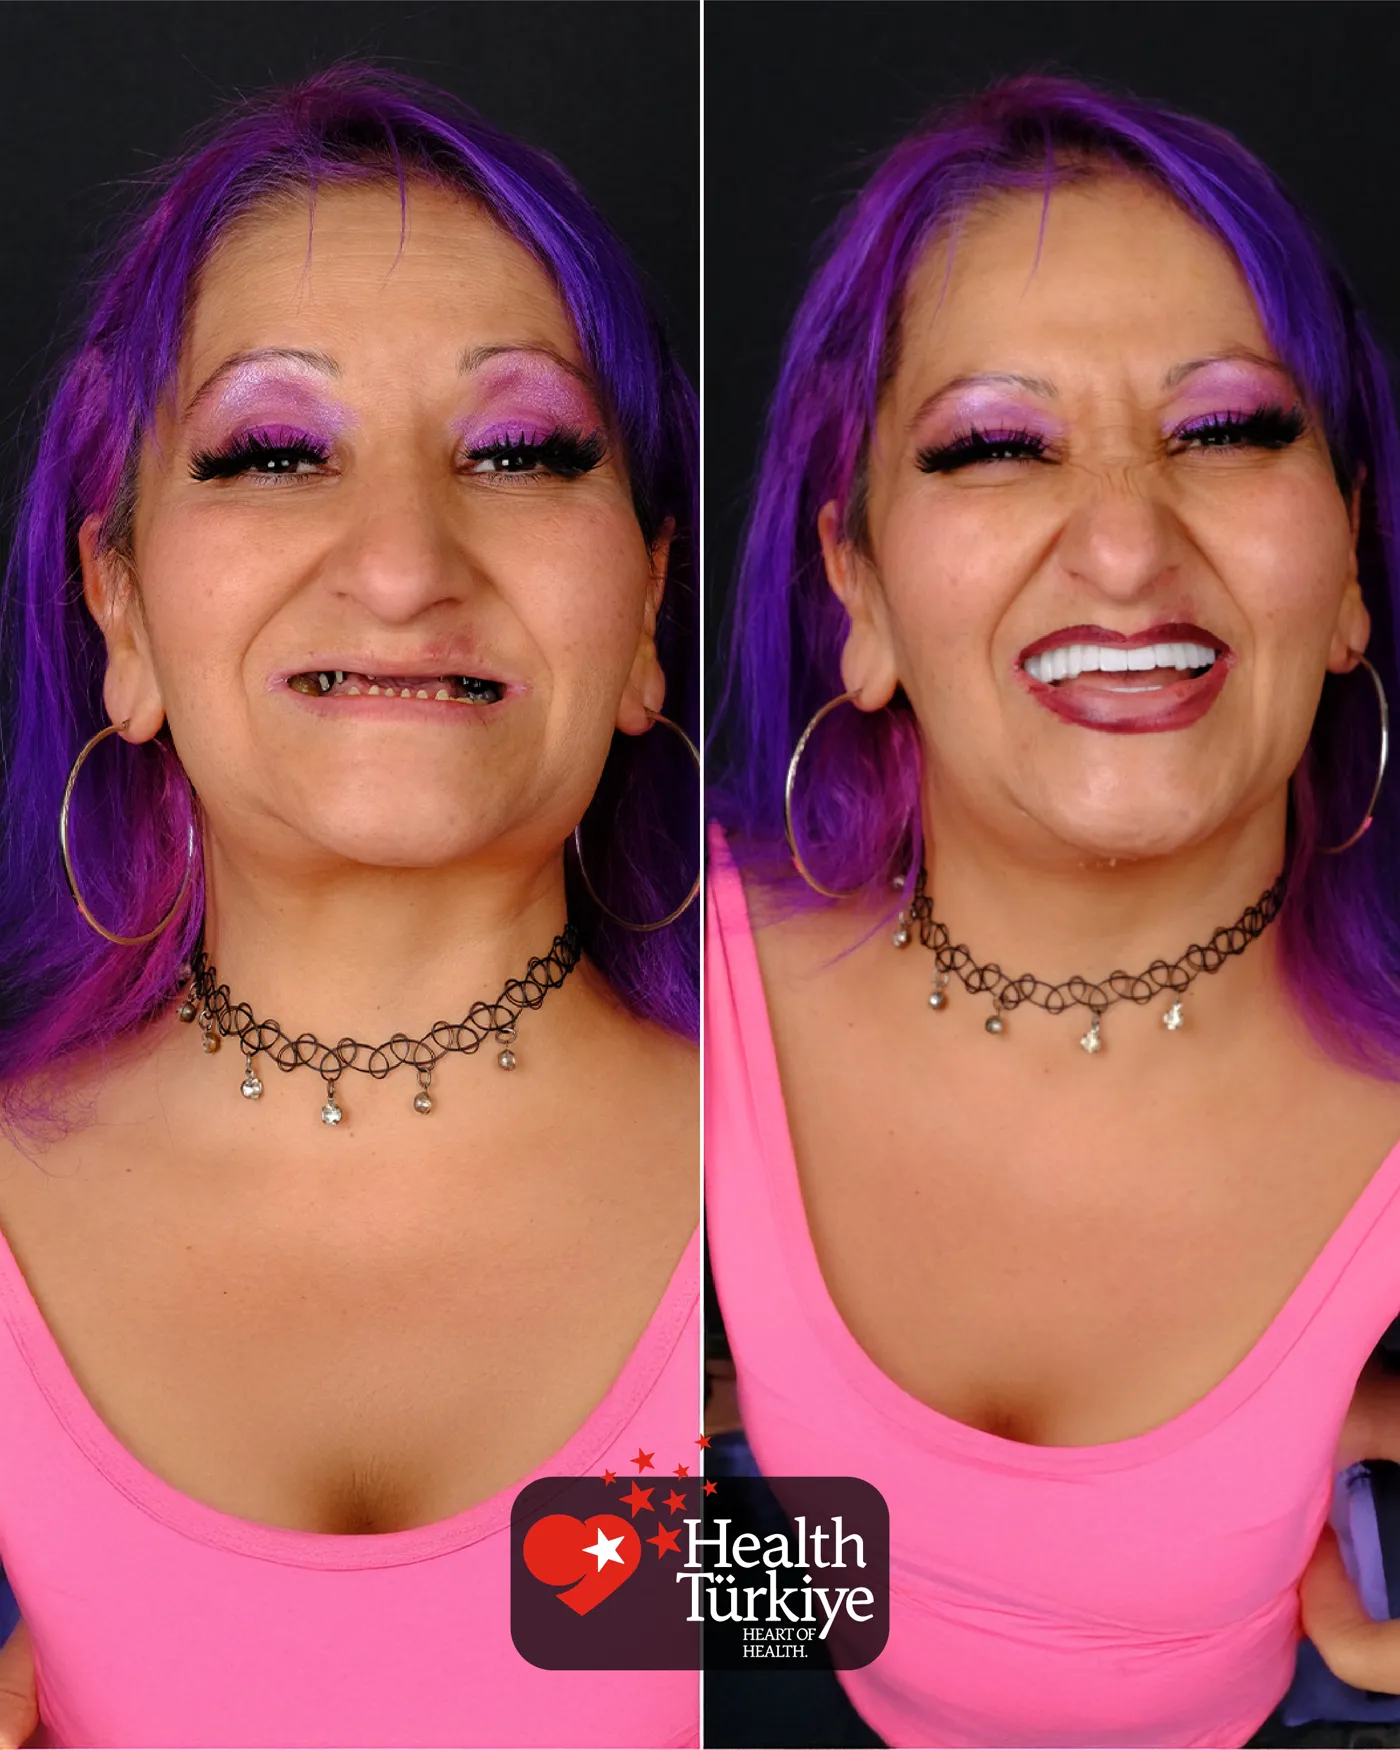
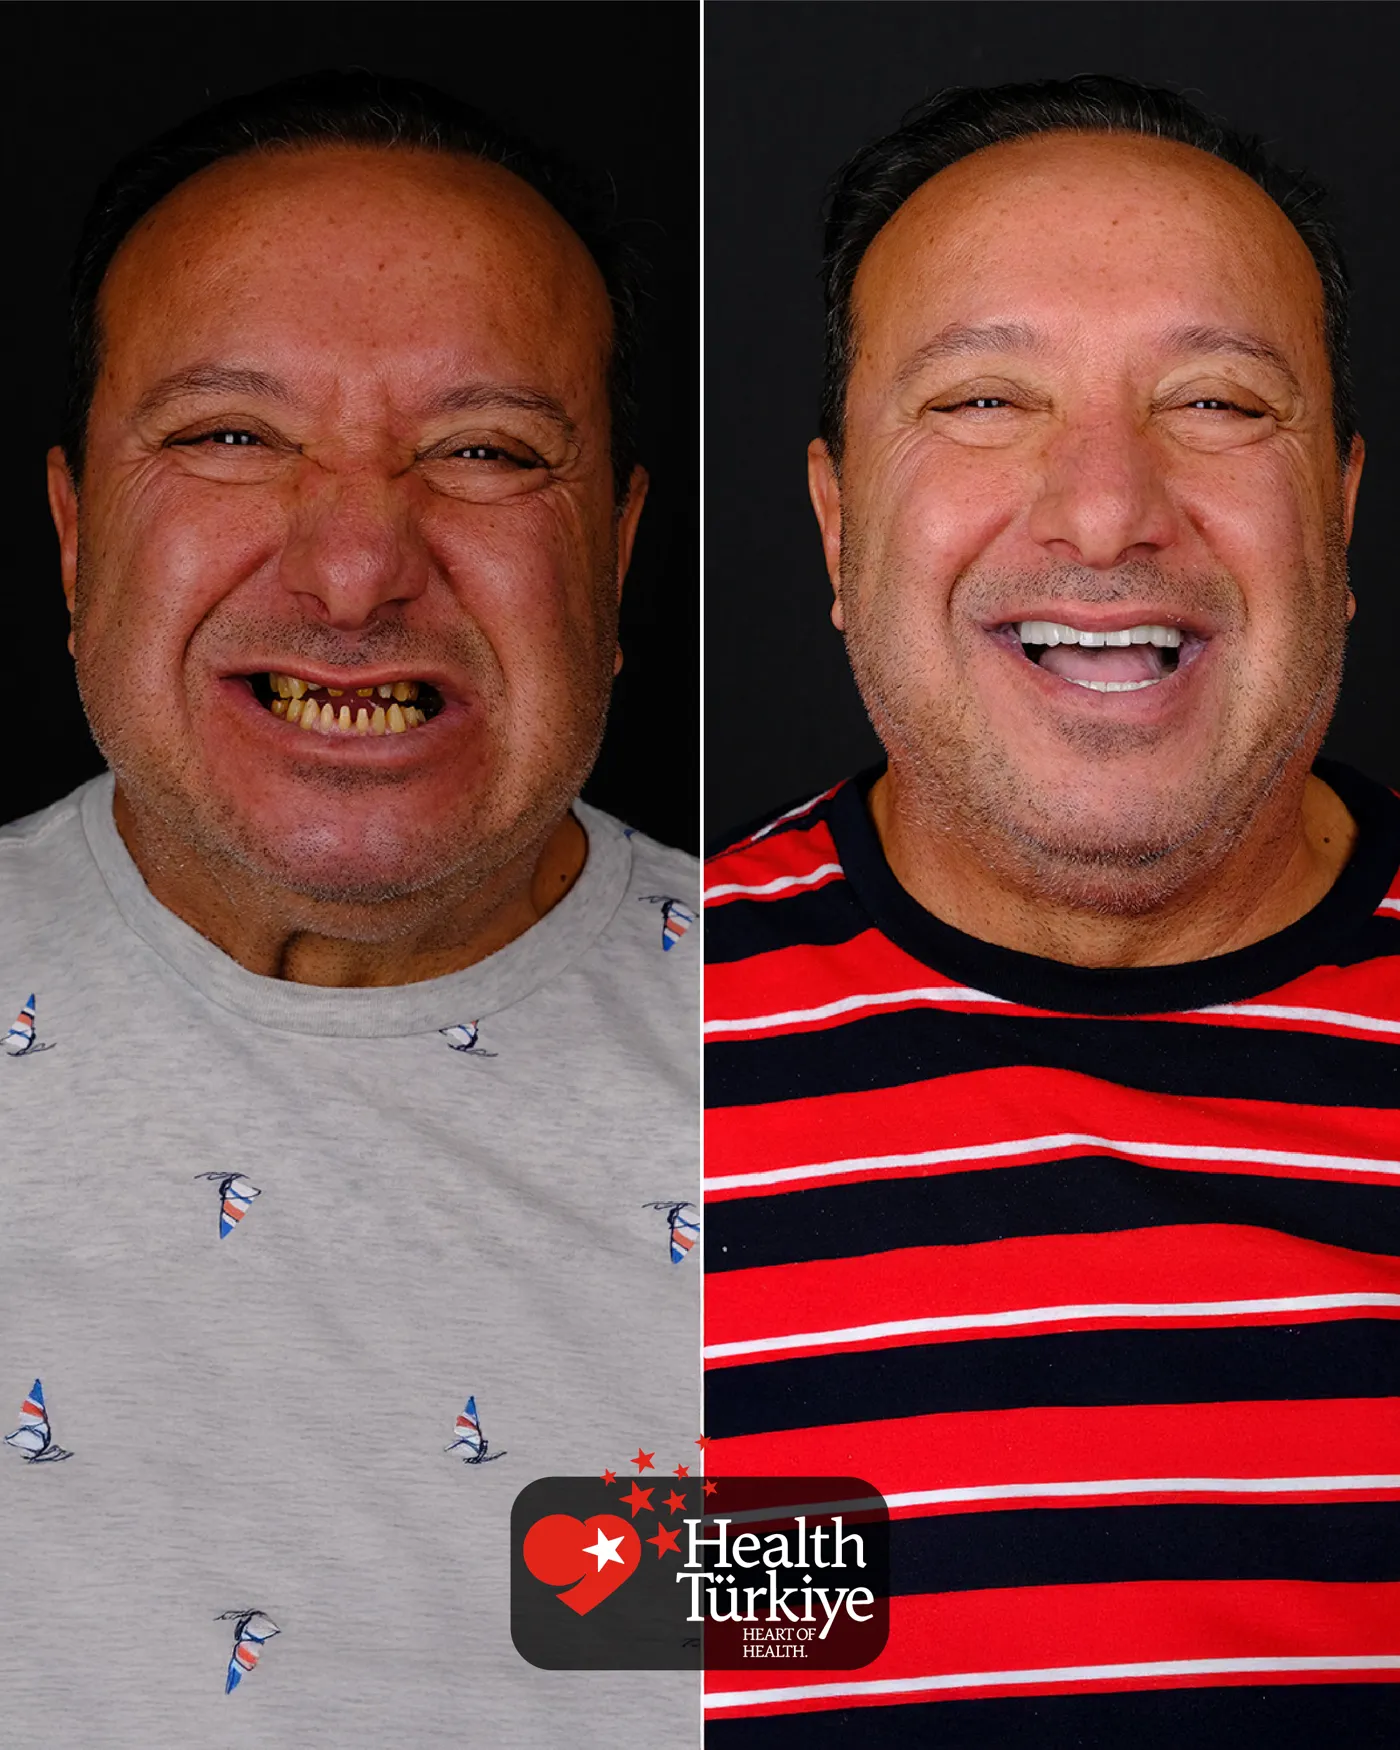
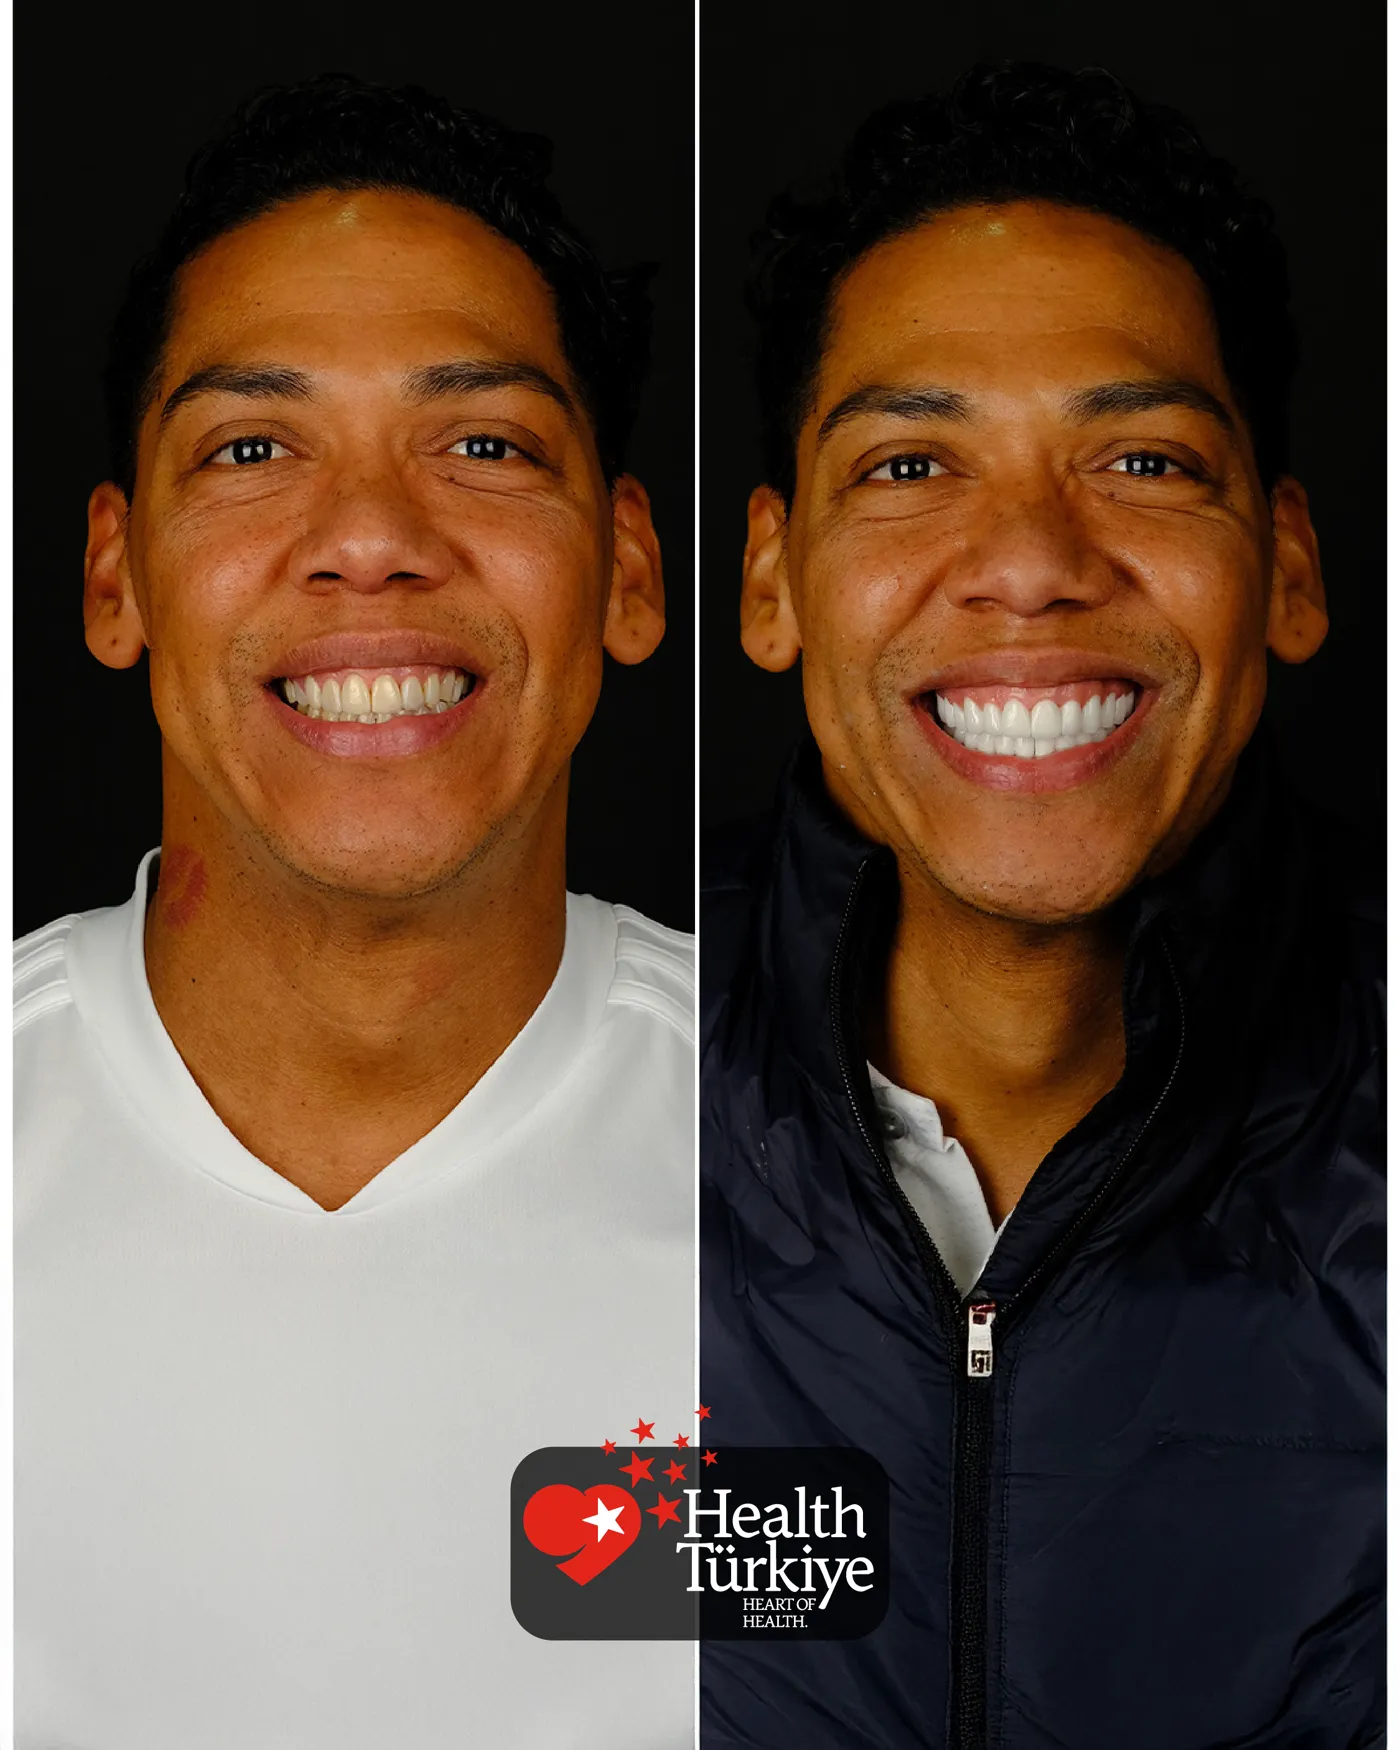
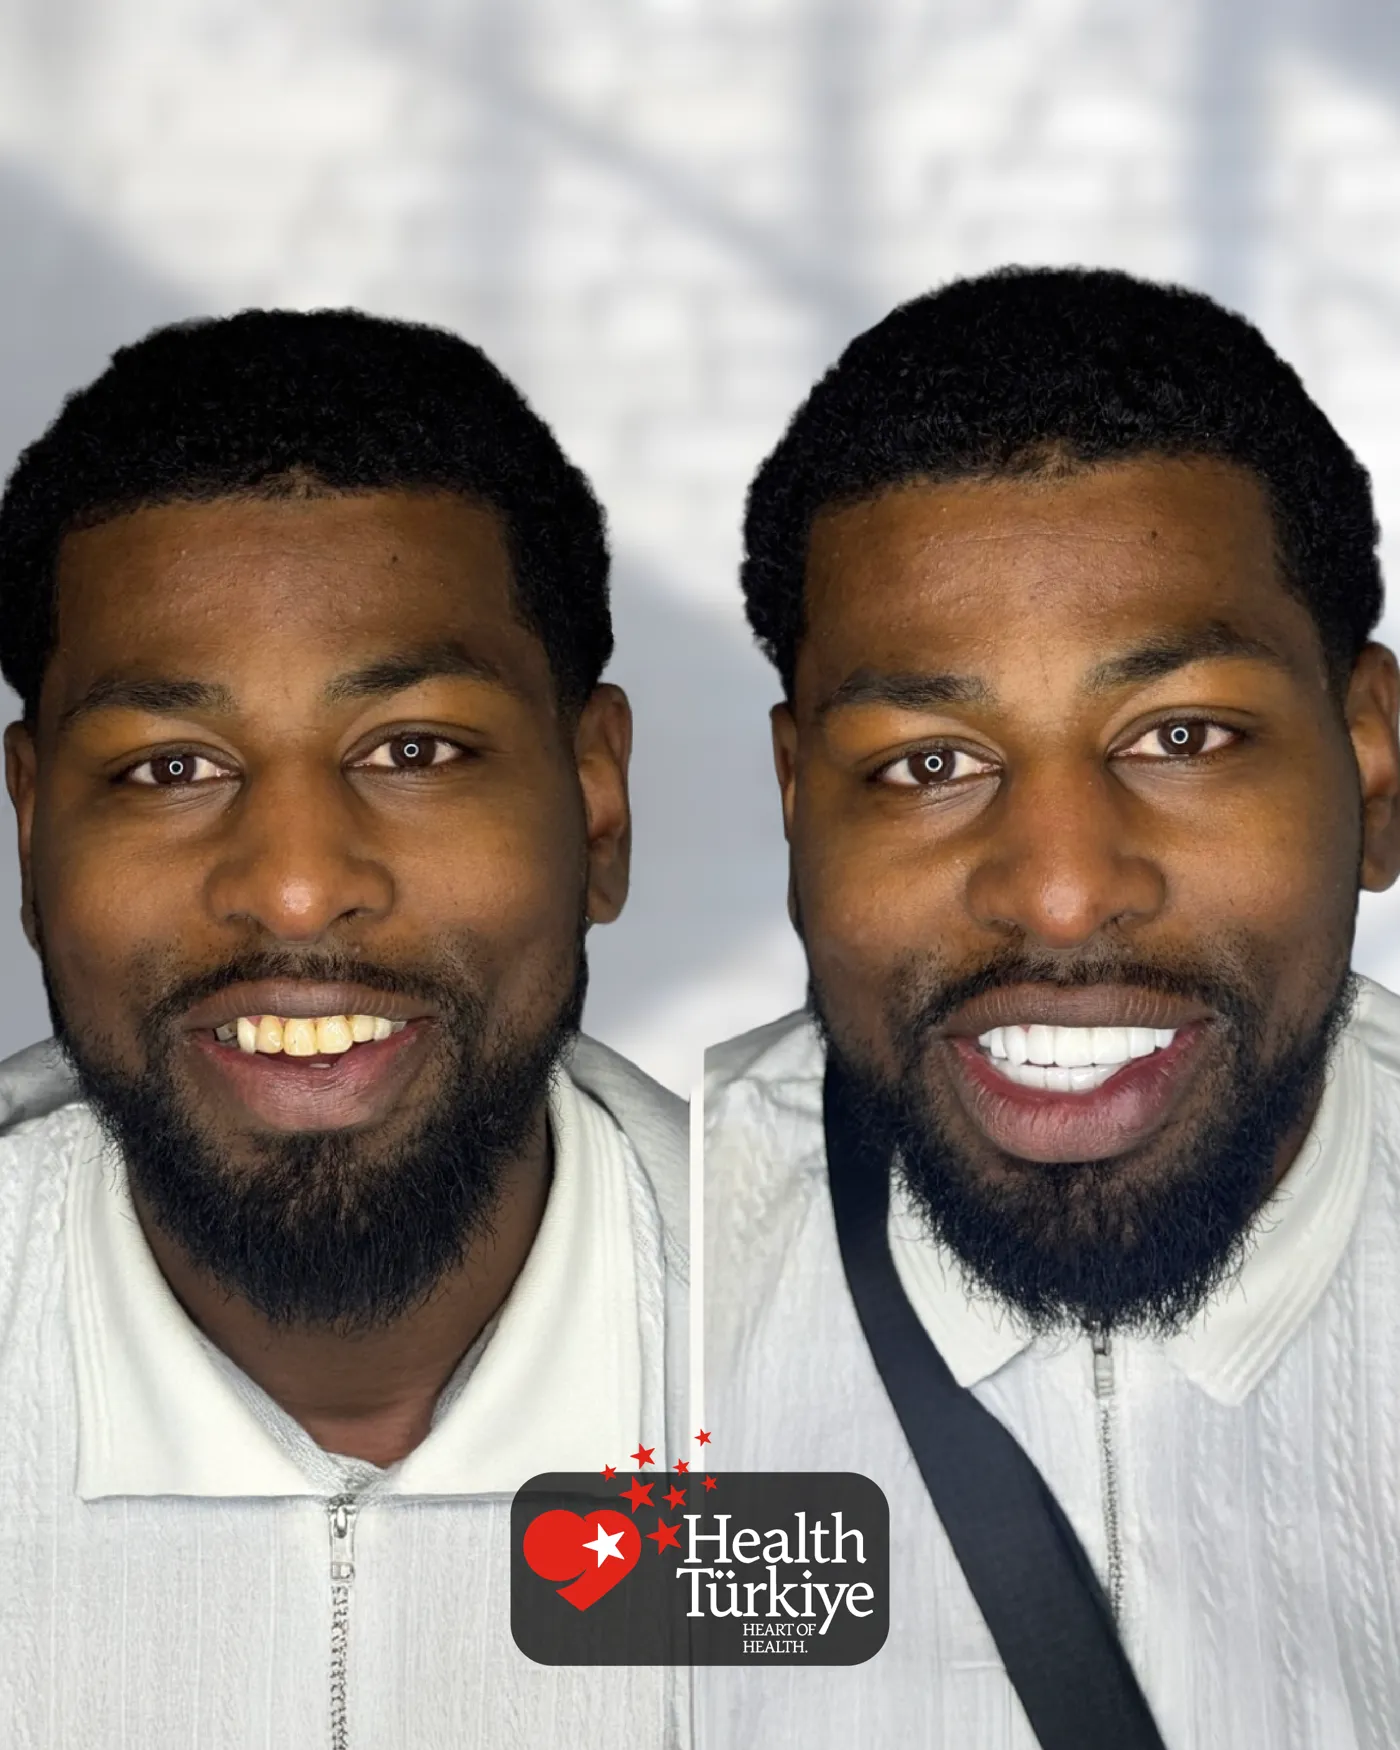
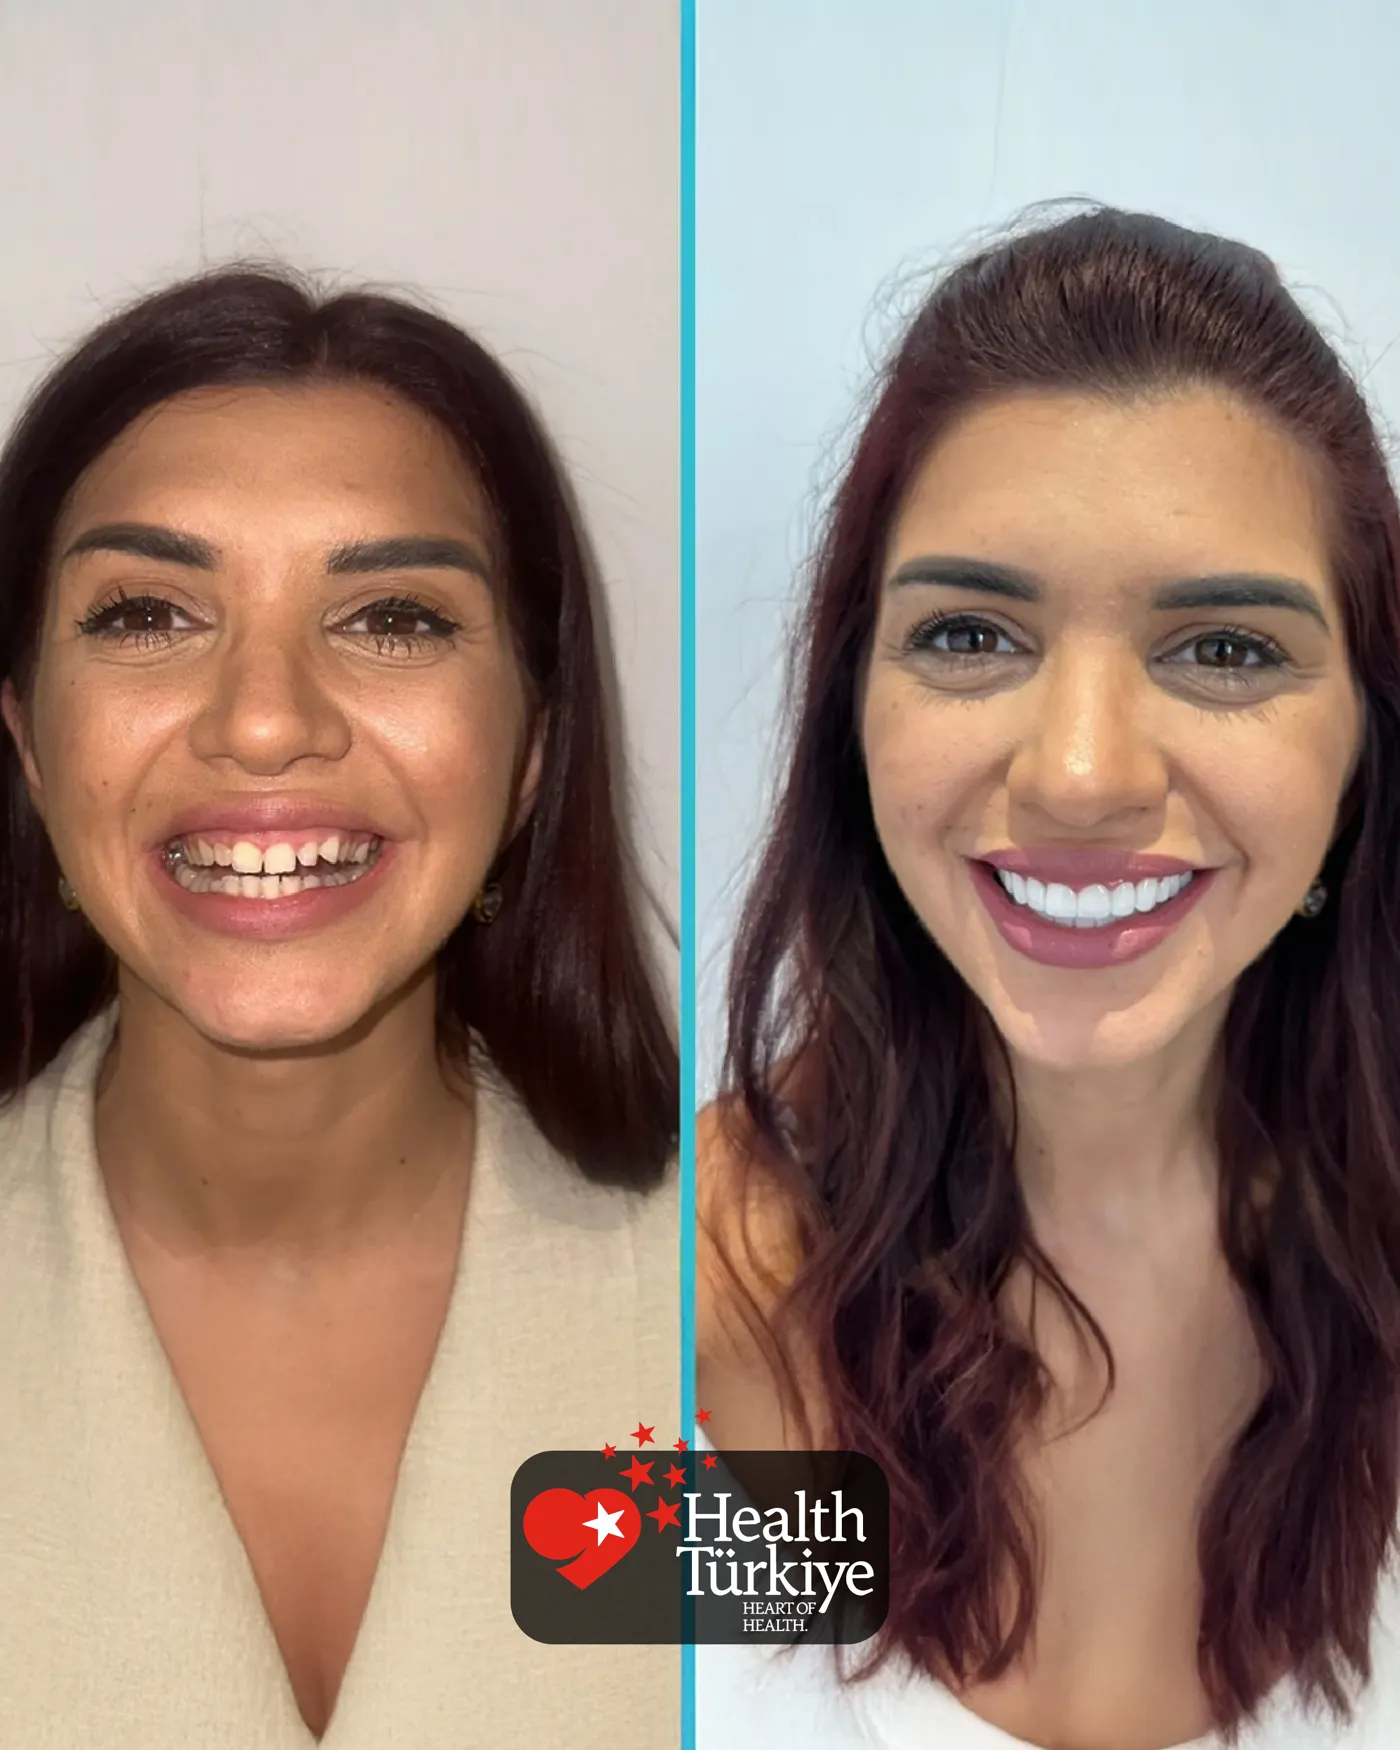
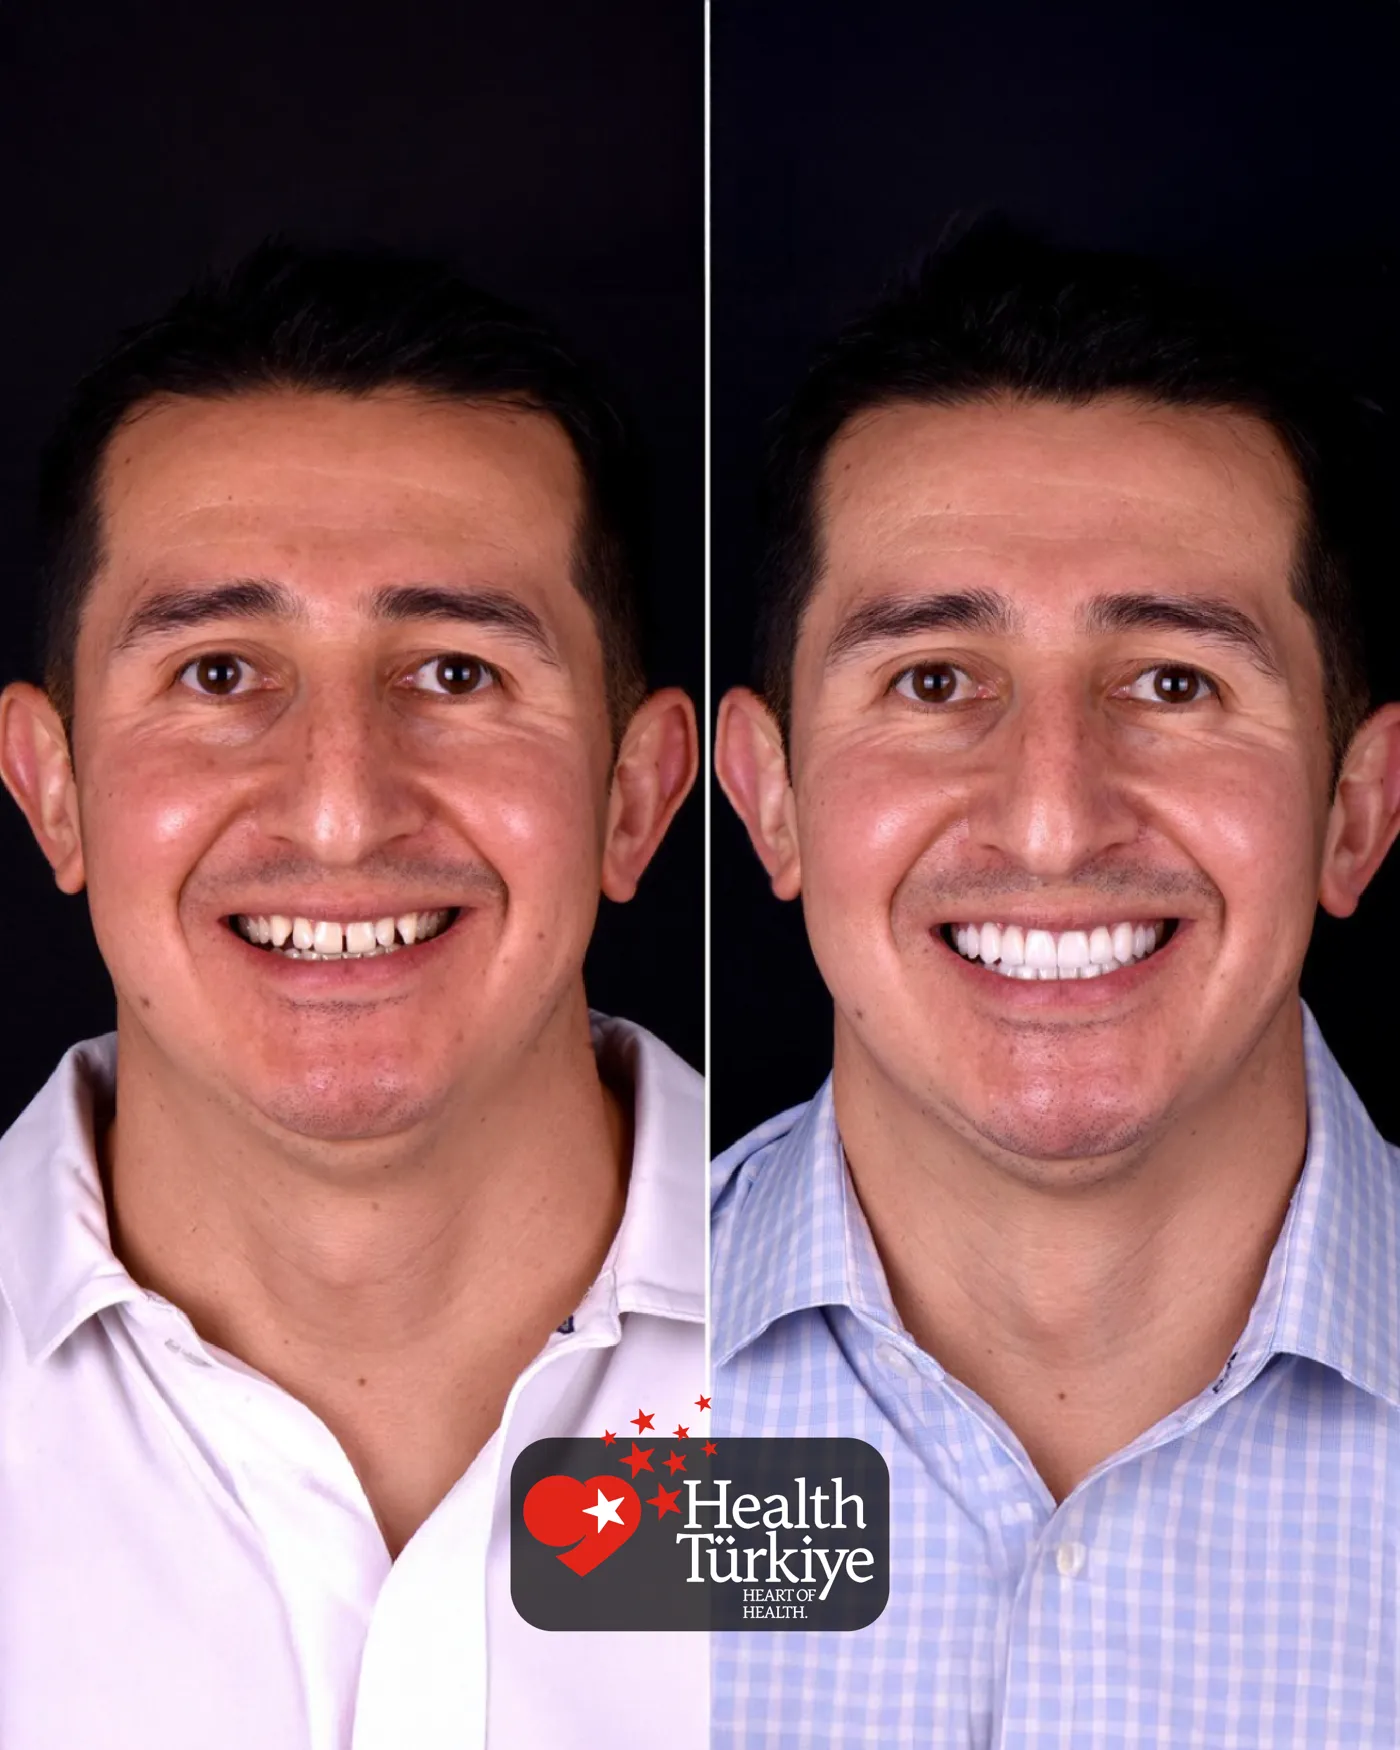
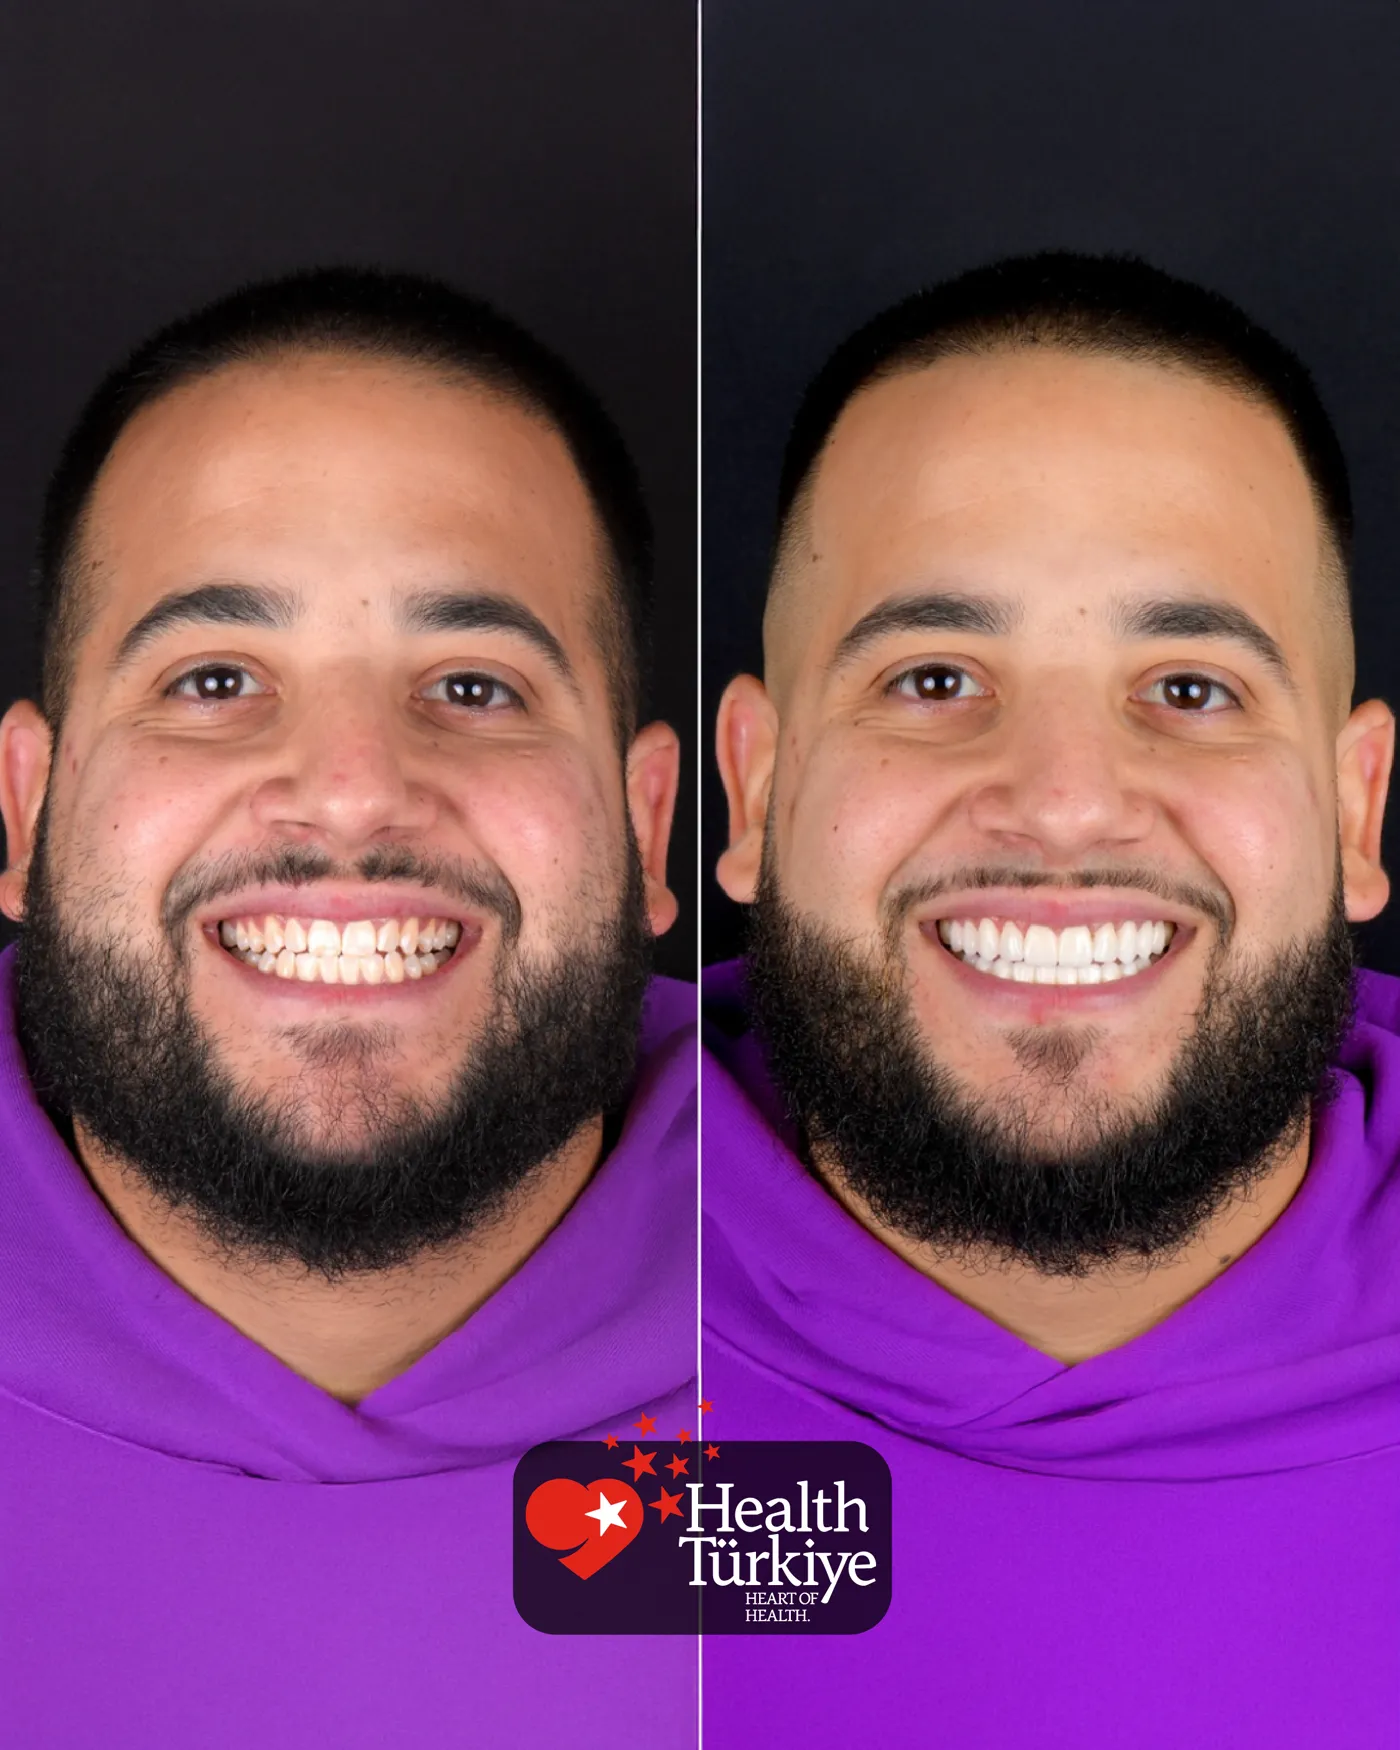
Photos from treatments performed at our clinic

Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
✦ Our Clinic
kliniğimiz
kliniğimiz
kliniğimiz
kliniğimiz

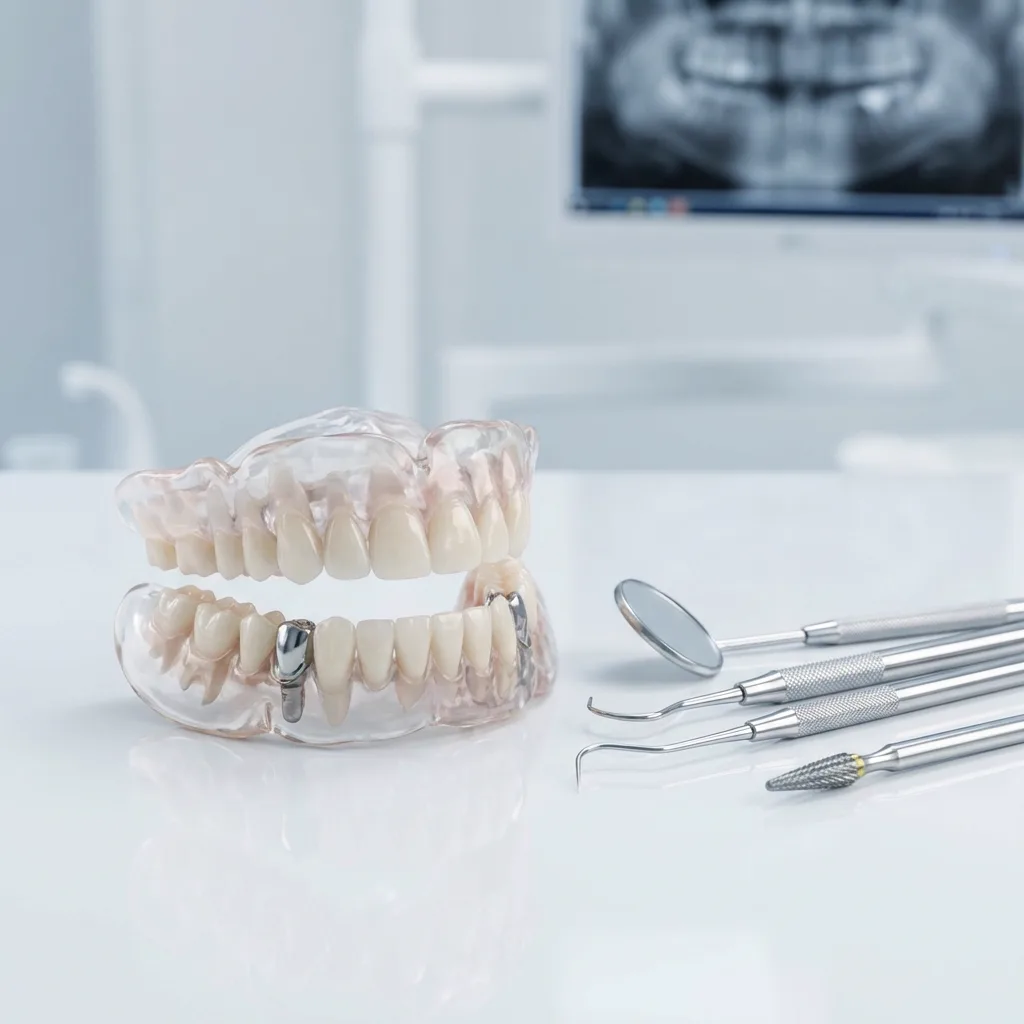
A denture replaces lost teeth and surrounding tissue — restoring chewing, speech and support for the lower third of the face.

When teeth are lost the alveolar bone is no longer stimulated and begins to resorb, hollowing the cheeks and shortening the face over the years. A denture provides support from outside but cannot stop this resorption; only implants can.

The choice is individual, based on remaining teeth, bone, gum health and daily expectations.

Types of Denture

Dentures fall into three groups according to how they are retained; the key difference is where the support comes from.

Complete dentures

Used when no teeth remain in a jaw. Upper dentures retain well by suction; lower ones are constantly displaced by tongue and lip movement — an anatomical fact rather than a fault. Two implants markedly improve lower denture comfort.

Partial dentures

Used when some teeth remain, retained by clasps or precision attachments. Protecting the abutment teeth is critical, as they carry extra load and are more vulnerable to decay if not cleaned well.

Implant-supported dentures

The denture is supported by implants, either removable (overdenture) or fixed. Reduced palatal coverage improves taste and speech, movement is eliminated, and the implants stimulate bone and slow resorption.

Immediate dentures

Fitted at the same visit as the extractions so the patient is never without teeth. It loosens as the ridge heals, which is expected, and is later relined or replaced.

The Denture Process

A denture is made individually, not mass-produced; the process needs several visits, each with its own purpose.

Examination and planning

Remaining teeth, gum health, bone height and jaw relationship are assessed with a panoramic radiograph, and the possibility of implant support is discussed.

Impressions and jaw relation

A preliminary impression is followed by a precise one in a custom tray. The jaw relationship and vertical dimension are then recorded — an error here compromises both appearance and function.

Try-in and fitting

The teeth are arranged in wax for a try-in — the stage at which shade, size, arrangement and smile line can still be changed easily. Speak up here; changes after processing are usually not possible.

Review appointments

Review appointments matter: pressure points appear in the first days and are relieved by adjustment. Enduring a rubbing denture causes ulcers and tissue change.

Living With a Denture: Care and Adaptation

Success depends as much on use as on manufacture; the first weeks are a learning process.

What to expect in the first days

Fullness, increased saliva and altered speech are normal while the tongue and cheeks adapt. Reading aloud helps, and chewing should start with soft food using both sides at once.

Cleaning

  • Rinse the denture after every meal
  • Use a denture brush and cleanser; ordinary toothpaste is abrasive
  • Clean over a bowl of water so it does not break if dropped
  • Brush and massage the palate and gums
  • Never use hot water — it distorts the denture
  • Remove at night and keep it in its container

Why it should be removed at night

The tissues beneath are under pressure all day and need to rest overnight; continuous wear invites fungal infection and inflammatory changes. Store it in clean water so it does not dry out.

When the denture becomes loose

Continuing bone resorption creates a gap and the denture moves. Relining or renewal is the answer; adhesives are a temporary measure and long-term use accelerates bone loss by retaining an ill-fitting denture.

Mouth Preparation and Assessment Before a Denture

How a denture will sit in the mouth is largely determined during the preparation stage, before the denture itself is made.

What Is Examined at the Assessment

Denture planning starts with a tooth-by-tooth assessment of whatever teeth remain. The dentist looks at mobility, decay and existing fillings, root canal history and gum health. Questionable roots and fractured fragments are dealt with before the denture is made, because they become far harder to reach once a denture is in place.

The clinical examination is usually accompanied by radiographs. Remaining bone height, the shape of the palate and lower ridge, mouth opening and tongue movement all influence which type of denture is appropriate. The same assessment notes conditions such as dry mouth, gum inflammation or denture-related fungal infection.

The Healing Period After Extractions

In patients who need extractions, the gum and bone change shape noticeably in the first weeks. A definitive denture made during that window quickly becomes loose. Healing is therefore allowed to settle first, and the waiting time is set individually according to the number of extractions, bone condition and general health.

An interim denture can be provided during this period so the patient is not left without teeth. It helps maintain chewing and speech and protects the healing tissue. Once healing is complete, the interim denture is replaced by the definitive one; this transition is a planned step, not a setback.

Factors That Shape the Plan

  • The number and position of remaining teeth and how much support they can provide
  • The height of the upper and lower ridges and the thickness of the gum tissue
  • The bite relationship and whether there is jaw joint pain, noise or restriction
  • Saliva flow, since a dry mouth makes denture retention more difficult
  • General health status and any medication taken regularly
  • Manual dexterity, which directly affects inserting, removing and cleaning the denture
  • The patient's day-to-day expectations and any previous denture experience

Changes That Appear Over Time With a Denture

Although a denture looks like a fixed appliance, the tissue beneath it changes over the years, so the fit has to be renewed periodically.

Loosening and the Need for Relining

Bone in an edentulous area slowly resorbs over the years under the pressure placed on it. Because the denture itself does not change, the fit deteriorates and the denture starts to rock or shift during meals. This means the underlying foundation has changed, not that the denture has failed.

In such cases it is usually enough to re-adapt the fitting surface to the new tissue shape rather than remake the denture; this procedure is called relining. Timely relining helps prevent accelerated bone loss from uneven pressure and sore spots on the gum.

Speech, Taste and the Gag Reflex

In the first days with a new denture it is normal for certain sounds to come out differently, for the tongue to catch on the borders and for saliva flow to increase. Reading aloud and continuing to talk speed up the tongue's adaptation to the new surface. If the complaint persists beyond the first weeks, the dentist reviews the borders and thickness.

In upper dentures, covering the palate can temporarily dull taste perception and reduce the sense of temperature. In patients with a pronounced gag reflex, the posterior border and palatal thickness can be adjusted, and implant-supported designs may leave the palate open. For this reason the exact nature of the complaint should be described in detail at the review appointment.

Common Mistakes in Denture Use

  • Using a denture that no longer fits for years without any check-up
  • Trying to trim the denture at home with scissors, files or similar tools
  • Attempting to repair a fractured denture with household adhesives or glue
  • Soaking it in hot water or boiling it to clean it, which distorts its shape
  • Scrubbing it with abrasive toothpaste, which scratches the surface and traps stains
  • Masking a poor fit by increasing the amount of denture adhesive
  • Postponing an appointment even when sore spots or ulcers have developed

✦ SSS

Frequently Asked Questions 30

01

How long does it take to get used to a denture?

It varies. Fullness, extra saliva and altered speech are normal at first; reading aloud and soft food help. Pain and ulcers, however, need adjustment.
02

Can I eat everything with a denture?

Chewing efficiency is lower than with natural teeth; start soft and progress gradually. Implant-supported dentures give markedly more chewing force.
03

My denture is rubbing — what should I do?

Come in and have it adjusted; the pressure points are relieved with a short adjustment. Putting up with it is the wrong approach — continuous irritation causes an ulcer and, over time, changes in the tissue itself. Never try to trim or sand the denture yourself: it is easy to ruin the fit beyond repair.
04

How long does a denture last?

The material itself can last a long time, but what really determines the lifespan is the bone underneath. As the ridge resorbs the denture stops fitting, and relining or remaking becomes necessary. Regular review is what identifies that at the right moment rather than after it has started causing sores.
05

What difference do implants make?

The denture no longer moves, chewing force increases markedly, palatal coverage can be reduced to improve taste and speech, and bone loss slows.
06

Can I sleep with my denture in?

Not recommended — the tissues need to rest, and continuous wear invites fungal infection. Store it in clean water overnight.
07

What is denture relining and when is it needed?

Relining means re-adapting the tissue-facing surface of a denture to the changed shape of the gum and bone. It comes onto the agenda when the denture loosens, moves during meals or starts causing sore spots. Whether it is needed is decided by the dentist after a clinical examination.
08

My denture has fractured; can it be repaired?

Fractures and cracks can usually be repaired in the clinic; keeping all the broken pieces and bringing them in together makes the repair easier. Using adhesive at home can bond the parts in the wrong position and complicate the repair. Since the underlying cause is often a poor fit, the fit is assessed along with the repair.
09

How often should I attend check-ups while wearing a denture?

Regular check-ups are advised even without complaints, because loss of fit and gum changes often progress painlessly. At the visit the seating of the denture, the bite relationship and the underlying tissues are assessed. If there is any sore spot, redness or unusual odour, an appointment should be made without waiting.
10

Is redness under the denture normal?

Persistent redness, a burning sensation or a whitish coating is not considered normal; it is usually linked to inadequate denture hygiene, wearing the denture overnight, or a poorly fitting denture. Once assessed, both the denture and the oral hygiene routine are addressed together. Rather than trying creams or mouthwashes independently, an examination is preferable.
11

After scaling there seem to be gaps between my teeth. Did the cleaning cause them?

The cleaning does not create gaps; it uncovers ones that were already there. Long-standing tartar fills and hides the spaces where inflammation has already caused the gum to recede. Removing it simply reveals the true tissue level. This is not a failed treatment but visible existing gum loss. With good home care the inflammation settles, the gum tightens, and the gaps often look smaller.
12

Will receded gum grow back on its own?

Receded gum does not return to its original level by itself, though in most cases further loss can be stopped. Controlling inflammation reduces swelling and tightens the tissue slightly, which is not true regrowth. Aggressive brushing, the wrong brush, clenching and untreated gum disease are the usual causes and are addressed first. Where appearance or sensitivity is a problem, gum grafting can be considered.
13

The dentist measured my gums and called out numbers. What do they mean?

They are pocket depths in millimetres, measured between the gum and the tooth. A thin, blunt-ended probe is slipped gently under the gum at several points around each tooth. Shallow readings suggest healthy attachment, while deeper ones mean an area has formed that a brush cannot reach. Bleeding on probing is recorded too. The chart guides which treatment each area needs.
14

A gum graft was suggested for my recession. Is it necessary for everyone?

No. Not every recession needs grafting. The decision depends on how much root is exposed, how thick the remaining gum is, the level of sensitivity, and whether the area shows when you smile. Limited, stable recession without symptoms is usually monitored after correcting brushing habits. Grafting is considered when the tissue is thin, the recession progresses, or sensitivity affects daily life.
15

I am not sure I brush correctly. What is the right technique?

Place the brush at about 45 degrees to the gumline and use small circular or vibrating strokes, staying a few seconds in each area. Long horizontal scrubbing wears the root surface and contributes to recession. Divide the mouth into sections and spend two minutes in total, including the inner surfaces and behind the last molars. Contact time matters more than pressure; flattened bristles mean you press too hard.
16

Does a hard toothbrush clean better? Which bristle firmness should I buy?

Hard bristles do not clean better. Plaque is a soft deposit that soft bristles remove easily, while stiff ones press on the gumline and contribute to abrasion and recession. A soft or medium-soft brush with a small head that reaches the back teeth is generally advised, ideally with rounded bristle tips. If you already have recession or sensitivity, choose soft bristles and lighten the pressure.
17

Is an electric toothbrush worth it compared with a manual one?

Used properly, both remove plaque; the advantage of an electric brush is that it makes the movement for you and most models include a timer and a pressure warning. People with limited dexterity, those in orthodontic treatment and heavy-handed brushers tend to benefit most. Even so, guide the head slowly along the gumline instead of scrubbing. No brush replaces cleaning between the teeth.
18

How do I know when to replace my toothbrush?

The usual rule is every three months, but the bristles decide. Once they splay, flatten or bend, the brush can no longer clean the gumline and should be replaced early. Bristles that wear out quickly usually mean you are pressing too hard. It is also sensible to change after an illness such as flu or a throat infection. Rinse the brush and store it upright in the open air.
19

There are dozens of toothpastes on the shelf. What should I look for?

Start with fluoride content; around 1450 ppm suits most adults. Then match the paste to your problem: a desensitising formula for sensitivity, a gum-care formula if your gums bleed. Avoid using highly abrasive whitening pastes every day. A pea-sized amount is enough, and remember that the cleaning comes from your technique and brushing time rather than from the paste itself.
20

Is fluoride toothpaste really necessary? Some say it is harmful.

Fluoride strengthens enamel against acid and helps repair very early decay; at toothpaste doses it is considered safe. The concern applies to young children swallowing large amounts over time while their teeth form, which is why an age-appropriate paste and amount are advised for them. Adults get more protection by spitting out the excess after brushing instead of rinsing heavily with water.
21

My gums bleed and hurt when I use floss. Am I doing it wrong?

In the first days, bleeding usually comes from inflamed gums rather than the floss itself and settles within a few days of regular use. Snapping the floss down into the gum, however, cuts the tissue. Guide it through the contact with a gentle sawing motion, then curve it in a C shape against each tooth and wipe up and down. If it shreds or catches, have that filling checked.
22

Should I use interdental brushes or floss? Do I need both?

It depends on how wide the spaces are. Where teeth touch tightly, floss fits best; where gaps are open, gums have receded, or you have bridges or implants, a correctly sized interdental brush is usually more effective. Many patients use floss at the front and brushes at the back. Never force a brush in: the right diameter is chosen at your appointment, since the wrong size injures the gum.
23

I bought a water flosser. Can I stop using floss now?

A water flosser is a useful addition but does not fully replace floss or interdental brushes. The jet flushes out food debris and loose material, yet it does not disrupt the sticky plaque film as well as mechanical wiping does. It is especially helpful with braces, bridges, implants and deeper pockets. The best results come from adding it to physical interdental cleaning, not substituting it.
24

Is there any harm in using mouthwash every single day?

It depends on the type. Alcohol-free fluoride rinses made for daily use are fine. Strong antiseptics such as chlorhexidine are prescribed for short courses, because prolonged use can stain teeth and temporarily alter taste. A rinse never replaces brushing; it is an addition. Rinsing straight after brushing washes away the fluoride from your paste, so use it at a different time of day.
25

There is a white coating on my tongue. Should I clean it too?

Yes, cleaning your tongue belongs to daily care. The grooved surface at the back holds bacteria and shed cells, and this coating is one of the commonest sources of bad breath. Sweep gently from back to front a few times with a tongue scraper or the soft bristles of your brush, then rinse. If you gag, start further forward. A coating that persists or hurts should be examined.
26

My breath still smells even though I brush regularly. What could cause it?

Most bad breath starts in the mouth: the bacterial coating on the tongue, uncleaned contact areas, tartar, inflamed gums, decay and old fillings with broken margins. A dry mouth and irregular eating make it more noticeable. If the smell persists after these are treated, sinus, tonsil, reflux or systemic causes are investigated. The sensible first step is a detailed dental examination.
27

My mouth is always dry. Can that harm my teeth, and what can I do?

Yes. Saliva buffers acid, returns minerals to enamel and washes debris away, so less of it means faster decay and more gum problems. Some blood-pressure, allergy, diuretic and antidepressant medicines, mouth breathing and certain conditions cause dryness. Sip water through the day, chew sugar-free gum, and cut down on caffeine and alcohol. Extra fluoride and more frequent check-ups are usually advised.
28

I smoke but my gums never bleed. Am I still at risk?

Yes. The absence of bleeding is not reassurance. Smoking constricts the small vessels in the gums, masking bleeding, the most visible sign of inflammation, so the disease advances quietly and is often noticed late. It also slows healing, increases tartar and staining, and worsens the outcome of gum treatment and implants. Smokers need more frequent pocket charting and support to quit.
29

I have diabetes. Do my gums need extra attention?

Yes, and the relationship runs both ways. Poorly controlled blood sugar impairs the response to infection and slows healing, so gum disease progresses faster. In turn, advanced gum inflammation can make blood sugar harder to control. Diabetic patients are therefore advised to have more frequent check-ups, regular scaling and careful interdental cleaning. Tell us your medicines and recent readings when you book.
30

Do I need to see a dentist when nothing hurts?

Yes, because early decay and early gum disease are usually painless. By the time it hurts, the problem is generally larger and the treatment more involved. A routine visit includes pocket measurements, a check of contact areas and old fillings, and radiographs where hidden areas need assessing. Six-monthly visits suit most adults, and higher-risk patients come more often. Our clinic is open around the clock.

From Our Blog

✦ Our Brands
Straumann
Nobel Biocare
Astra Tech
Medentika
Bredent SKY
Straumann
Nobel Biocare
Astra Tech
Medentika
Bredent SKY
✦ Contact
Get in touch

Antalya Muratpaşa our central clinic

Sair Adem Dede St. No:31, 07030 Muratpasa / Antalya, Türkiye

Open in Google Maps