01
How much of the tooth is removed when a filling is placed?
Only decayed tissue and the limited area needed for the filling to bond are removed. Because composite bonds chemically to the tooth, far less sound tissue is taken than in the amalgam era. The aim is to preserve the remaining walls as far as possible, because the tooth's strength depends on them.
02
Can decay start again at the edge of a filling?
It can; this is called secondary decay and develops in the micro-gap between filling and tooth. The risk rises where the margin is poorly adapted, overhanging or worn. If the area is not cleaned with floss the decay advances unnoticed, which is why it is assessed with a radiograph at reviews.
03
What if it hurts to bite after a filling?
This is usually because the filling is slightly high in the bite: the tooth contacts first at every bite and is overloaded. A short adjustment fixes it and should not be postponed, because a tooth under constant strain becomes sensitive and the pulp can become inflamed. The adjustment takes a few minutes.
04
What happens if the pulp is exposed in deep decay?
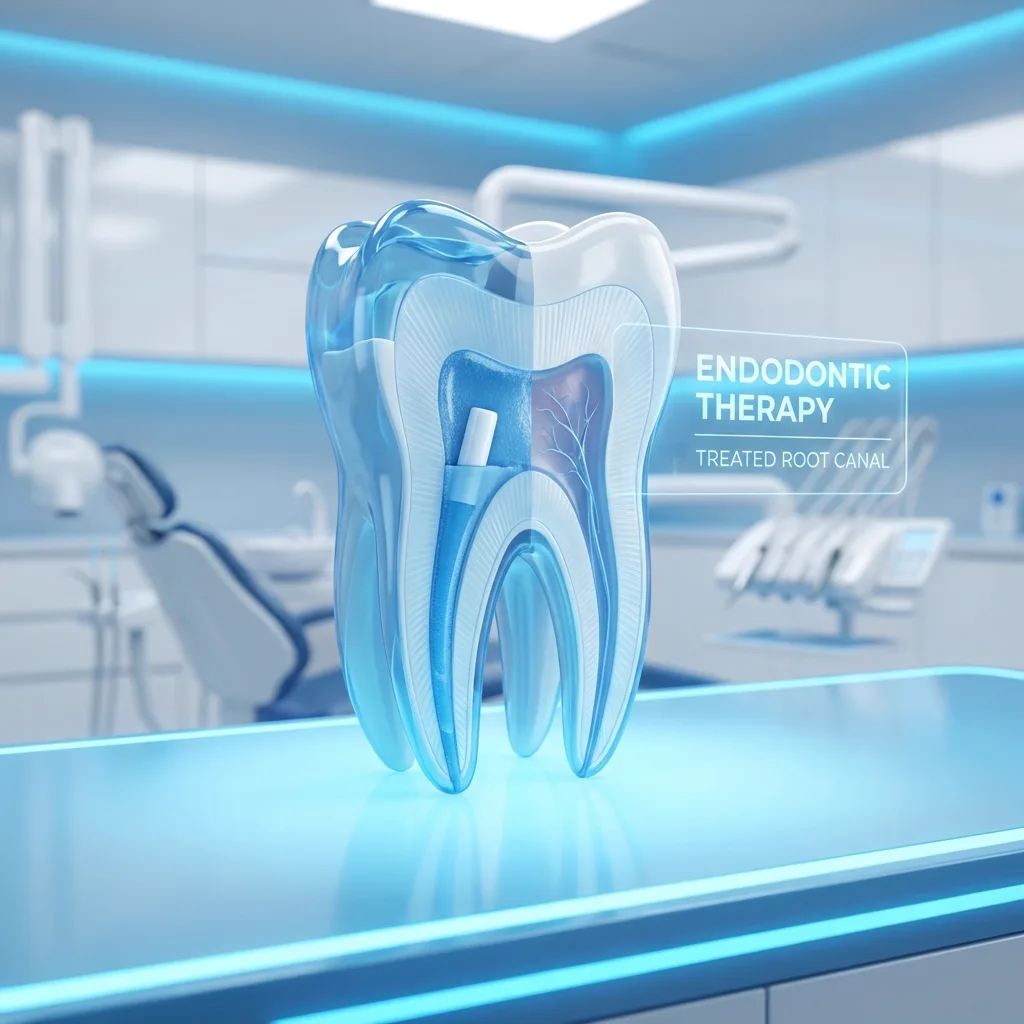
When decay comes very close to the pulp there are two routes: if the pulp looks vital and healthy a protective lining can be placed and the tooth monitored, or if it is affected, root canal treatment follows. The decision is made during the procedure and the possibility is explained to you beforehand.
05
Does a composite filling change colour?
Composite is more porous than porcelain and can pick up surface staining over time; coffee, tea, red wine and smoking accelerate it. Polishing at review appointments removes most of that surface staining. Darkening at the margin is different, however, and can indicate secondary decay.
06
How many times can the same tooth be filled?
There is no fixed number, but each replacement removes a little more tissue. Once the remaining walls are thin enough to flex under chewing, a filling is no longer the right choice and an onlay or crown is needed. Making that transition in time prevents the tooth being lost to a vertical fracture.
07
Are baby teeth filled?
They are, and they should be. A decayed baby tooth causes pain, disrupts chewing and the infection can affect the permanent tooth bud beneath. A baby tooth lost early also has its space closed by the neighbours, leaving no room for the permanent tooth. The 'it will fall out anyway' approach is wrong for these three reasons.
08
When is an onlay recommended instead of a filling?
When the loss of tooth substance is too great for a filling to carry. In back teeth that have lost one or more cusps in particular, an onlay wraps and supports the remaining walls and prevents the tooth splitting. It is made in a laboratory so needs an extra appointment, but it is safer in the long run.
09
Can I do something temporary if a filling comes out?
A temporary filling material from a pharmacy can close the cavity for a day or two and reduce sensitivity, but it does not stop the decay beneath and is not a lasting solution. Avoid chewing on that side and take care that any sharp edge does not irritate the tongue. Book an appointment as soon as you can.
10
How long does cold sensitivity last after a filling?
It usually fades within a few days to two weeks, and can take slightly longer with deep fillings. If it increases when it should be settling, if throbbing starts on its own, or if the pain continues after the stimulus is removed, the pulp may be affected and assessment is needed.
11
Does a white spot need a filling?
No, not at that stage. A white spot is an early lesion whose surface has not yet broken, and it can be arrested with fluoride, interdental cleaning and less frequent sugar. A filling is needed once the surface has broken, so catching it early removes the need for treatment.
12
Can filling materials cause an allergy?
It is rare but reported. Contact reactions to some resins in composite can occur. If you have a known allergy or have reacted to a dental material before, always say so; an alternative material can be chosen. Treating you without this information creates unnecessary risk.
13
Is having a filling painful?
Under local anaesthetic it is not painful. Very superficial decay may not need anaesthesia at all. Sensitivity to cold for a few days afterwards is normal and settles; sensitivity that gets worse rather than better should be checked, as it usually means the bite needs a small adjustment.
14
When can I eat after a filling?
A composite filling is set hard by the curing light immediately, so the material itself needs no waiting time. What you should wait for is the anaesthetic to wear off: while your lip and tongue are numb it is easy to bite them without noticing, and hot drinks can burn without you feeling it.
15
My filling feels high — will it settle?
It will not settle and must be adjusted; a high filling overloads the tooth and can cause pain or fracture. Adjustment is quick and painless.
16
How long does a filling last?
It depends on the size of the cavity, on your oral hygiene and on whether you clench or grind. Small, well-maintained fillings can serve for many years without trouble. Large restorations in heavily loaded back teeth come under more stress and need replacing sooner, which is why an onlay is sometimes the better choice.
17
I have no pain — do I still need a filling?
Yes. Early and moderate decay is usually completely painless — pain generally starts only once the decay approaches the pulp. Waiting for a symptom is what turns something a simple filling would have solved into a root canal treatment, so the absence of pain is not a reason to postpone.
18
Is composite as durable as amalgam?
Modern composites withstand normal chewing forces and preserve more tooth structure; very large cavities are better served by an inlay, onlay or crown.
19
My filling fell out — how soon should I be seen?
The exposed cavity traps food and leaves unprotected dentine where decay can progress quickly, and sharp edges may irritate the tongue. Even without pain it should be assessed promptly; our clinic on Şair Adem Dede Caddesi in Muratpaşa is open 24/7.
20
How long does sensitivity last after a filling?
Short-term cold sensitivity is expected after deep fillings and usually settles within days. Sharp pain on biting often means the filling is high and is easily adjusted; increasing or spontaneous night pain needs re-evaluation.
21
Is a filling enough for a root-treated tooth?
For front teeth with limited tissue loss a composite restoration may suffice. Posterior teeth carry higher loads and are more fracture-prone after root canal treatment, so cuspal coverage with an onlay or crown is usually preferred.
22
How long do implants last? Are they permanent once placed?
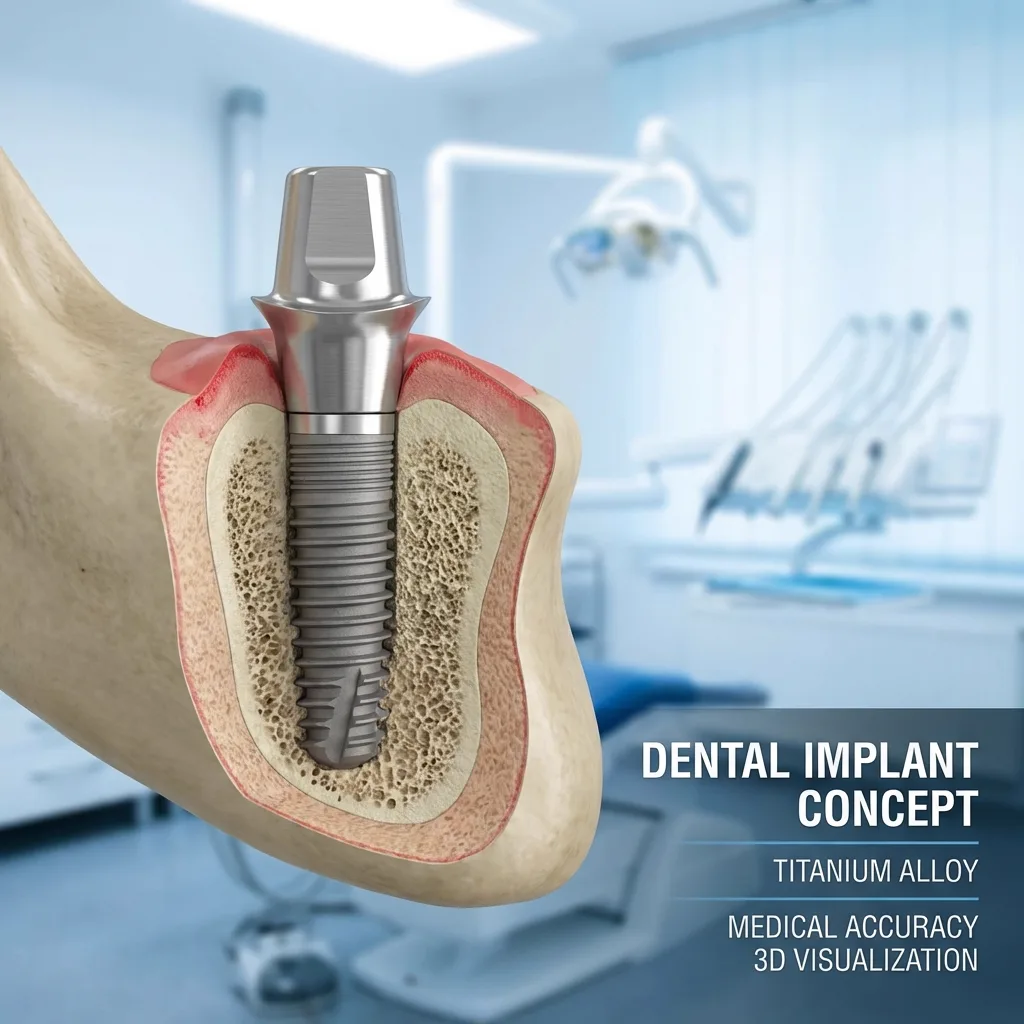
Implants are designed as long-term solutions, though no treatment can be promised for life. What matters most is the health of the surrounding gum and bone. Daily brushing, interdental cleaning and regular check-ups with professional cleaning support longevity. Smoking, uncontrolled diabetes, clenching and neglected maintenance raise the risk, and the crown itself may need renewal.
23
Do I brush an implant like a normal tooth, or is extra care needed?
Yes, brush it twice daily with a soft brush and paste, but do not stop there. Implants cannot decay, yet the gum around them is more sensitive to inflammation, so cleaning between teeth matters. Use floss, interdental brushes or a water flosser daily, avoid scraping with hard tools, and keep regular check-up and cleaning appointments.
24
The gum around my implant bleeds and is swollen. Is that dangerous?
These signs can mean the tissues around the
implant are inflamed and should be checked promptly. At an early, gum-only stage it is often reversible with professional cleaning and better home care. If it reaches the bone it becomes peri-implantitis, bone is lost and treatment is harder. Bleeding, swelling, odour or any mobility deserves an early appointment.
25
I smoke. Does that stop me from having implants?
Smoking is not an absolute barrier, but it is a known risk factor. Nicotine and smoke reduce blood flow, slowing healing and increasing the chance of inflammation around the implant. Stopping, or at least clearly reducing, before and during healing supports success. If you continue, we plan more frequent check-ups and a stricter maintenance routine.
26
I am diabetic and on blood pressure medication. Can I have implants?
Usually yes; what matters is how well the condition is controlled rather than the diagnosis itself. With stable blood sugar, healing generally goes smoothly, while poor control raises infection and delayed-healing risk. Bring recent test results and a full list of medicines, especially blood thinners and bone drugs, so we can plan with your physician if needed.
27
One tooth is missing. Should I choose an implant or a bridge?
Both replace the gap; the difference is their effect on neighbouring teeth. An implant stands alone, leaves healthy neighbours untouched and keeps the bone stimulated. A bridge requires reshaping both adjacent teeth, which can make sense if they already need crowns, and it finishes faster. Where surgery is unsuitable, a bridge is often preferred.
28
Food gets under my bridge. How do I clean underneath it?
The pontic rests on the gum and ordinary floss cannot pass beneath it, so you need special tools. Use superfloss or a floss threader to slide floss horizontally under the bridge and work it back and forth. Interdental brushes and a water flosser help too. Without this, decay and gum inflammation can develop on the supporting teeth.
29
I have three missing teeth in a row. Can a bridge cover that?
A bridge can only span a limited gap, decided by the number, root shape and bone support of the abutment teeth. Long spans flex under chewing and can overload the supports, causing loosening or fracture. For wider gaps, implant-supported solutions or partial dentures are usually considered, based on the span, the opposing teeth and radiographs.
30
Can a crowned tooth decay? A dark line appeared at its edge.
The crown itself cannot decay, but the natural tooth beneath it can. Decay typically starts at the margin where the crown meets the gum, if plaque is left there. A dark line may simply be a metal substructure showing or exposed root after gum recession, or it may be active decay. Examination and radiographs tell them apart.