

















































What the Type of Toothache Tells You
Toothache behaves differently depending on its source. The distinctions below help you assess your own situation and describe it accurately on the phone.
Brief sensitivity pain
Pain that starts with cold or heat and passes within seconds usually means sensitivity or shallow decay — not urgent, but not to be ignored.
Pain that lingers after the stimulus
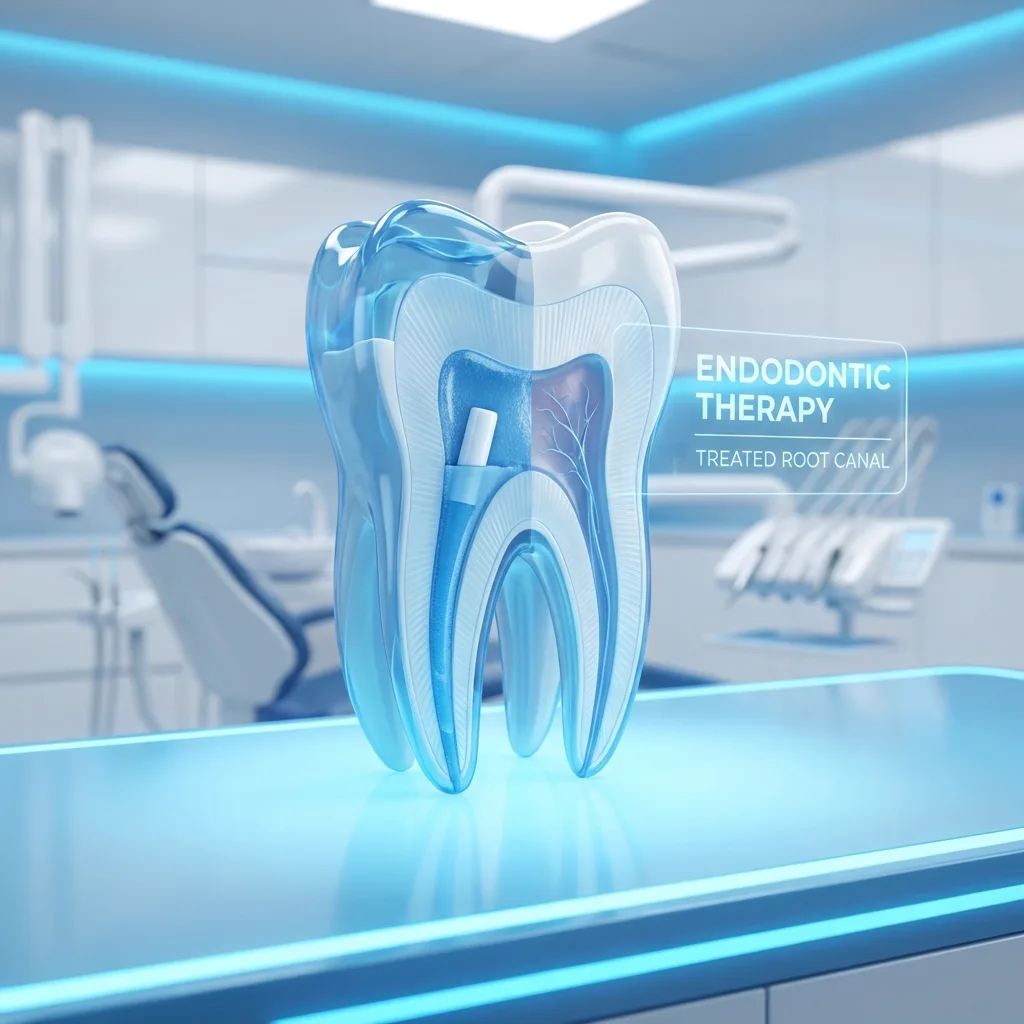
Pain lasting minutes after the stimulus is a key sign of irreversible pulpitis, which needs root canal treatment rather than a filling.
Pain on biting and touch
Pain on biting suggests inflammation has reached the root tip and surrounding bone. Cracked tooth syndrome gives a similar pain, sharp on release of biting.
Spontaneous throbbing pain
Spontaneous, pulsating pain that worsens at night is the most urgent group and usually does not respond adequately to painkillers.
Radiating pain with unclear origin
Pain radiating to the jaw, ear, temple or neck is hard to localise: lower jaw pain may come from the upper jaw, and upper molar pain from the sinus. A partly erupted wisdom tooth is another common cause.
First Aid for Toothache Until You Reach the Clinic
The measures below ease the pain somewhat. What to avoid matters just as much.
What you can do
- Keep your head elevated — it reduces pressure in the pulp chamber
- Cold compress on the cheek: 15 minutes on, 15 off
- Take a painkiller you have used safely before, without exceeding the dose
- Rinse gently with warm salt water
- Gently remove trapped food with dental floss
- Do not chew on that side; avoid very hot and cold drinks
What you must never do
- Placing a painkiller on the tooth or gum — it causes a chemical burn
- Heat in any form — it spreads the infection
- Applying alcohol, cologne or clove oil directly to the gum
- Starting leftover antibiotics — they do not relieve pain
- Trying to pierce the gum with a needle
- Cancelling treatment because the pain stopped — the pulp may have died
What if the pain stopped by itself?
This is where patients most often go wrong. Severe pain stopping usually means the pulp has died, not healed. Dead tissue remains in the canal, bacteria multiply and infection advances silently, returning later as an abscess.
How Toothache Is Treated at the Clinic
In the emergency session the priority is stopping the pain and controlling its source.
Examination and panoramic X-ray
We listen to your history, examine the mouth and take a panoramic X-ray, which reveals hidden decay, root-tip infection, impacted teeth and cysts.
Treatment for pulpal pain
For irreversible pulpitis, root canal treatment is started under local anaesthesia. Pain largely resolves as soon as the pressure is released.
Treatment for decay-related pain
Where decay has not reached the pulp, it is removed and the tooth restored with composite. With extensive loss, an onlay or crown is preferred.
Treatment for gum and surrounding tissue pain
If the source is the gum rather than the tooth, the approach differs: drainage and local cleaning for a gum abscess, cleaning the area in pericoronitis.
Toothache in Special Situations
The approach differs for some patient groups — always share this information.
Toothache during pregnancy
Delaying treatment in pregnancy usually carries more risk. Always state that you are pregnant and how many weeks, as this affects timing, X-rays, anaesthesia and medication.
Toothache in children
Children struggle to localise pain; it may show only as irritability or refusing to chew on one side. Decay advances quickly in milk teeth and infection can affect the developing permanent tooth.
Patients with chronic conditions
Diabetes, heart valve disease, blood thinners, bisphosphonates and cancer treatment history all affect the plan. In diabetes infection advances faster and healing is slower, making early treatment more important.