




























Patient Reviews 4.9/5 10.000+ Happy Patients 37 Countries

E-max Porcelain Veneers in Antalya

✦ Tedaviler

E-max Porcelain Veneers in Antalya

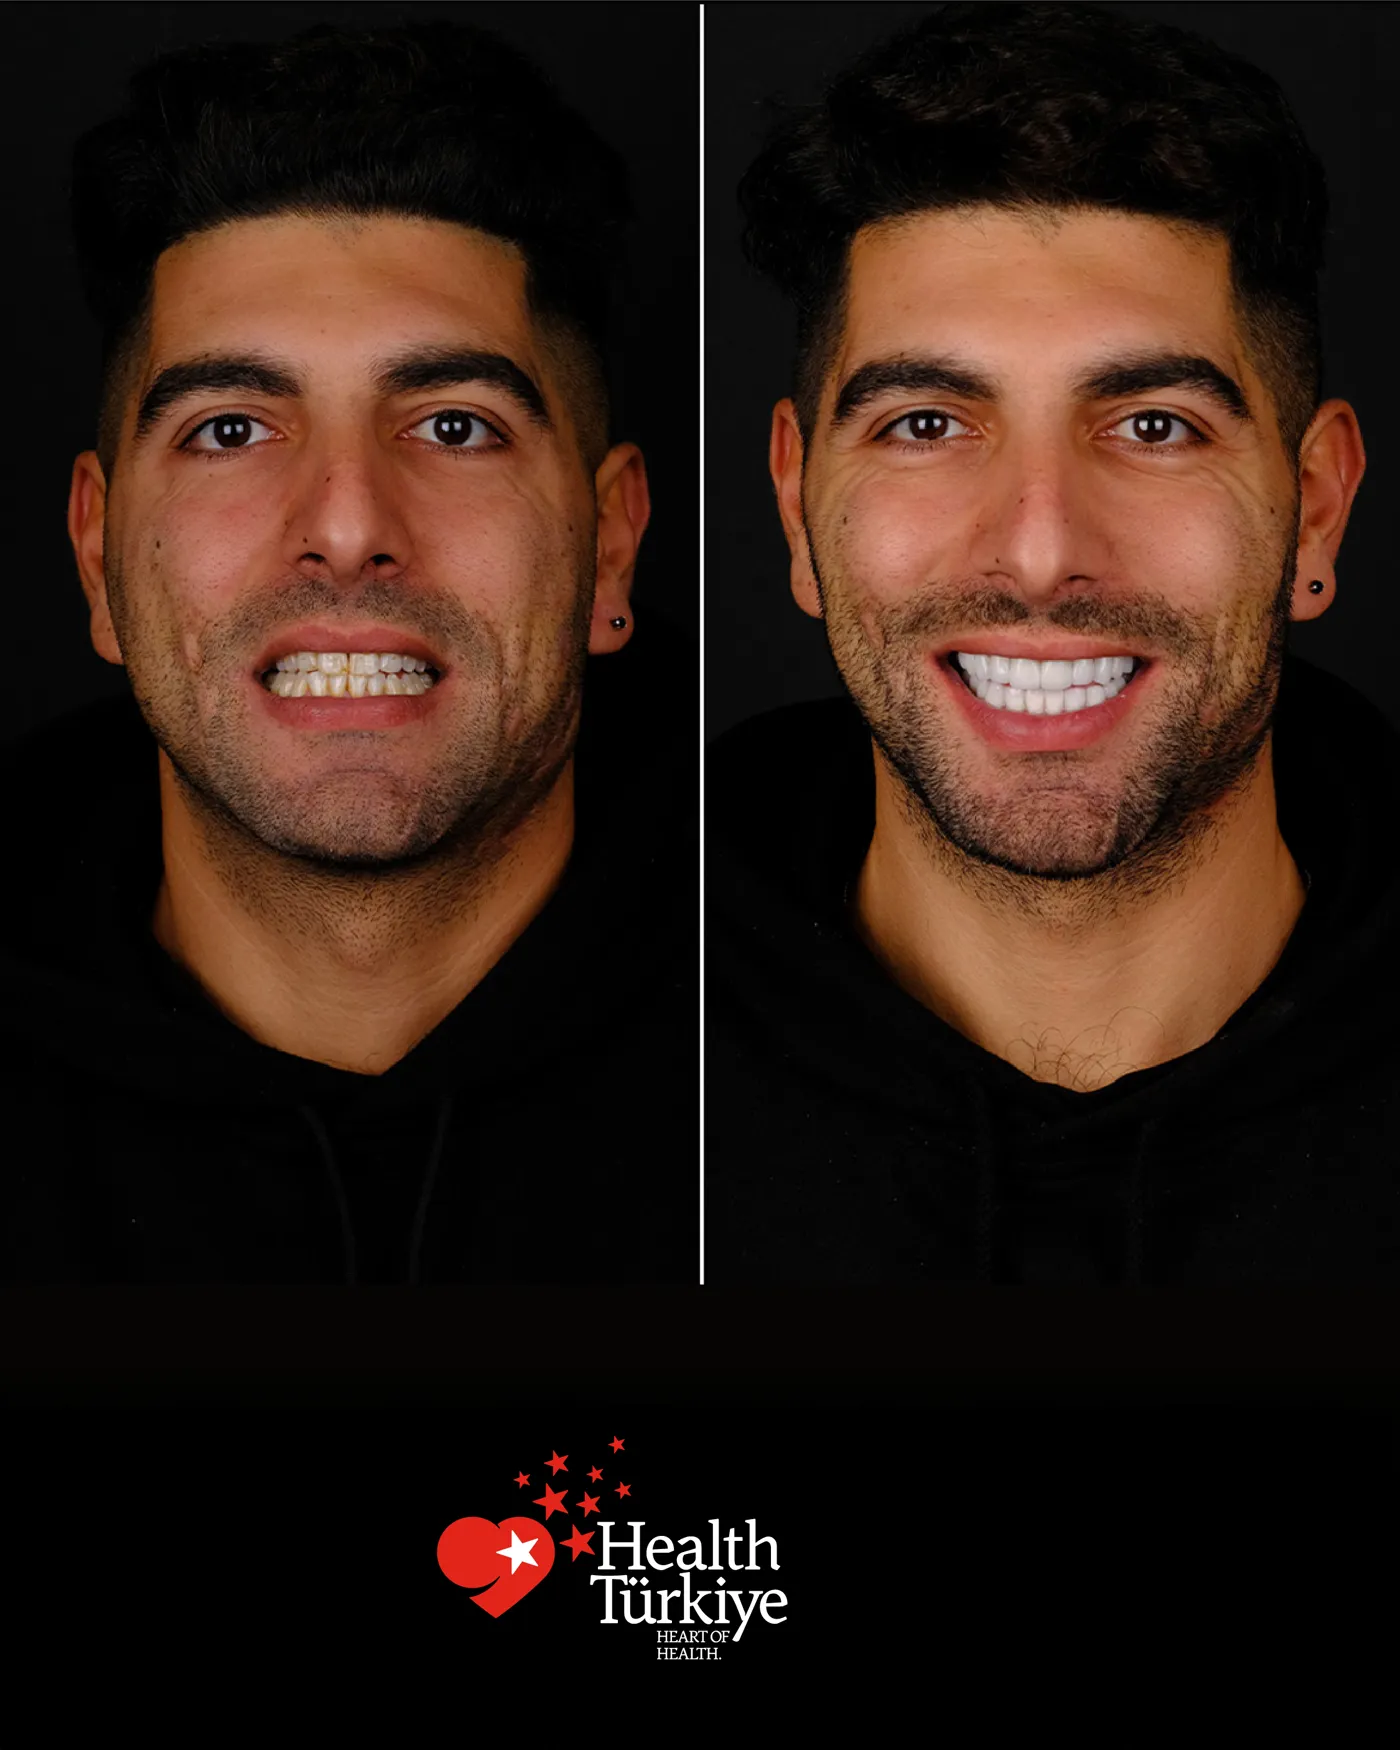
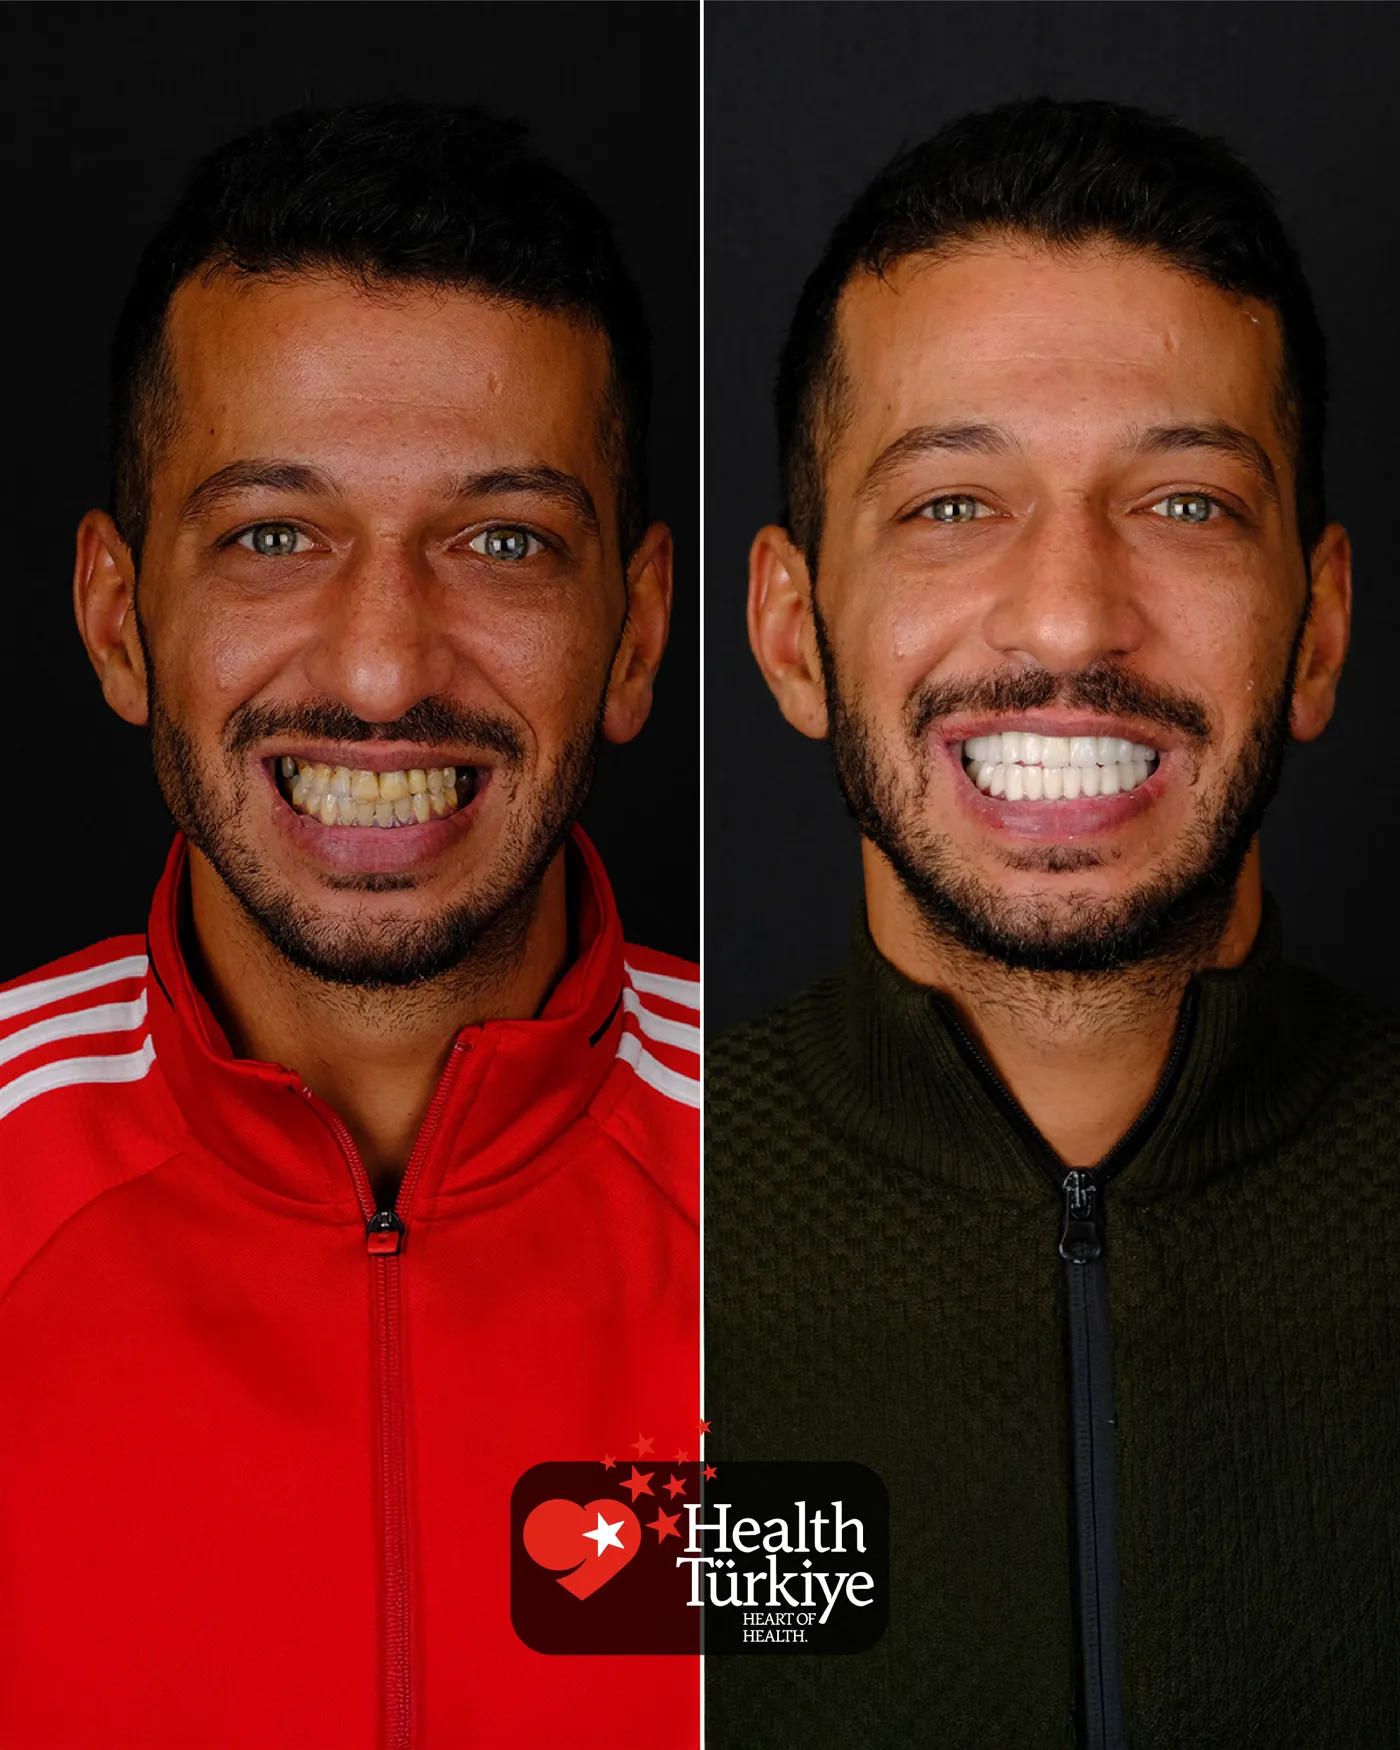
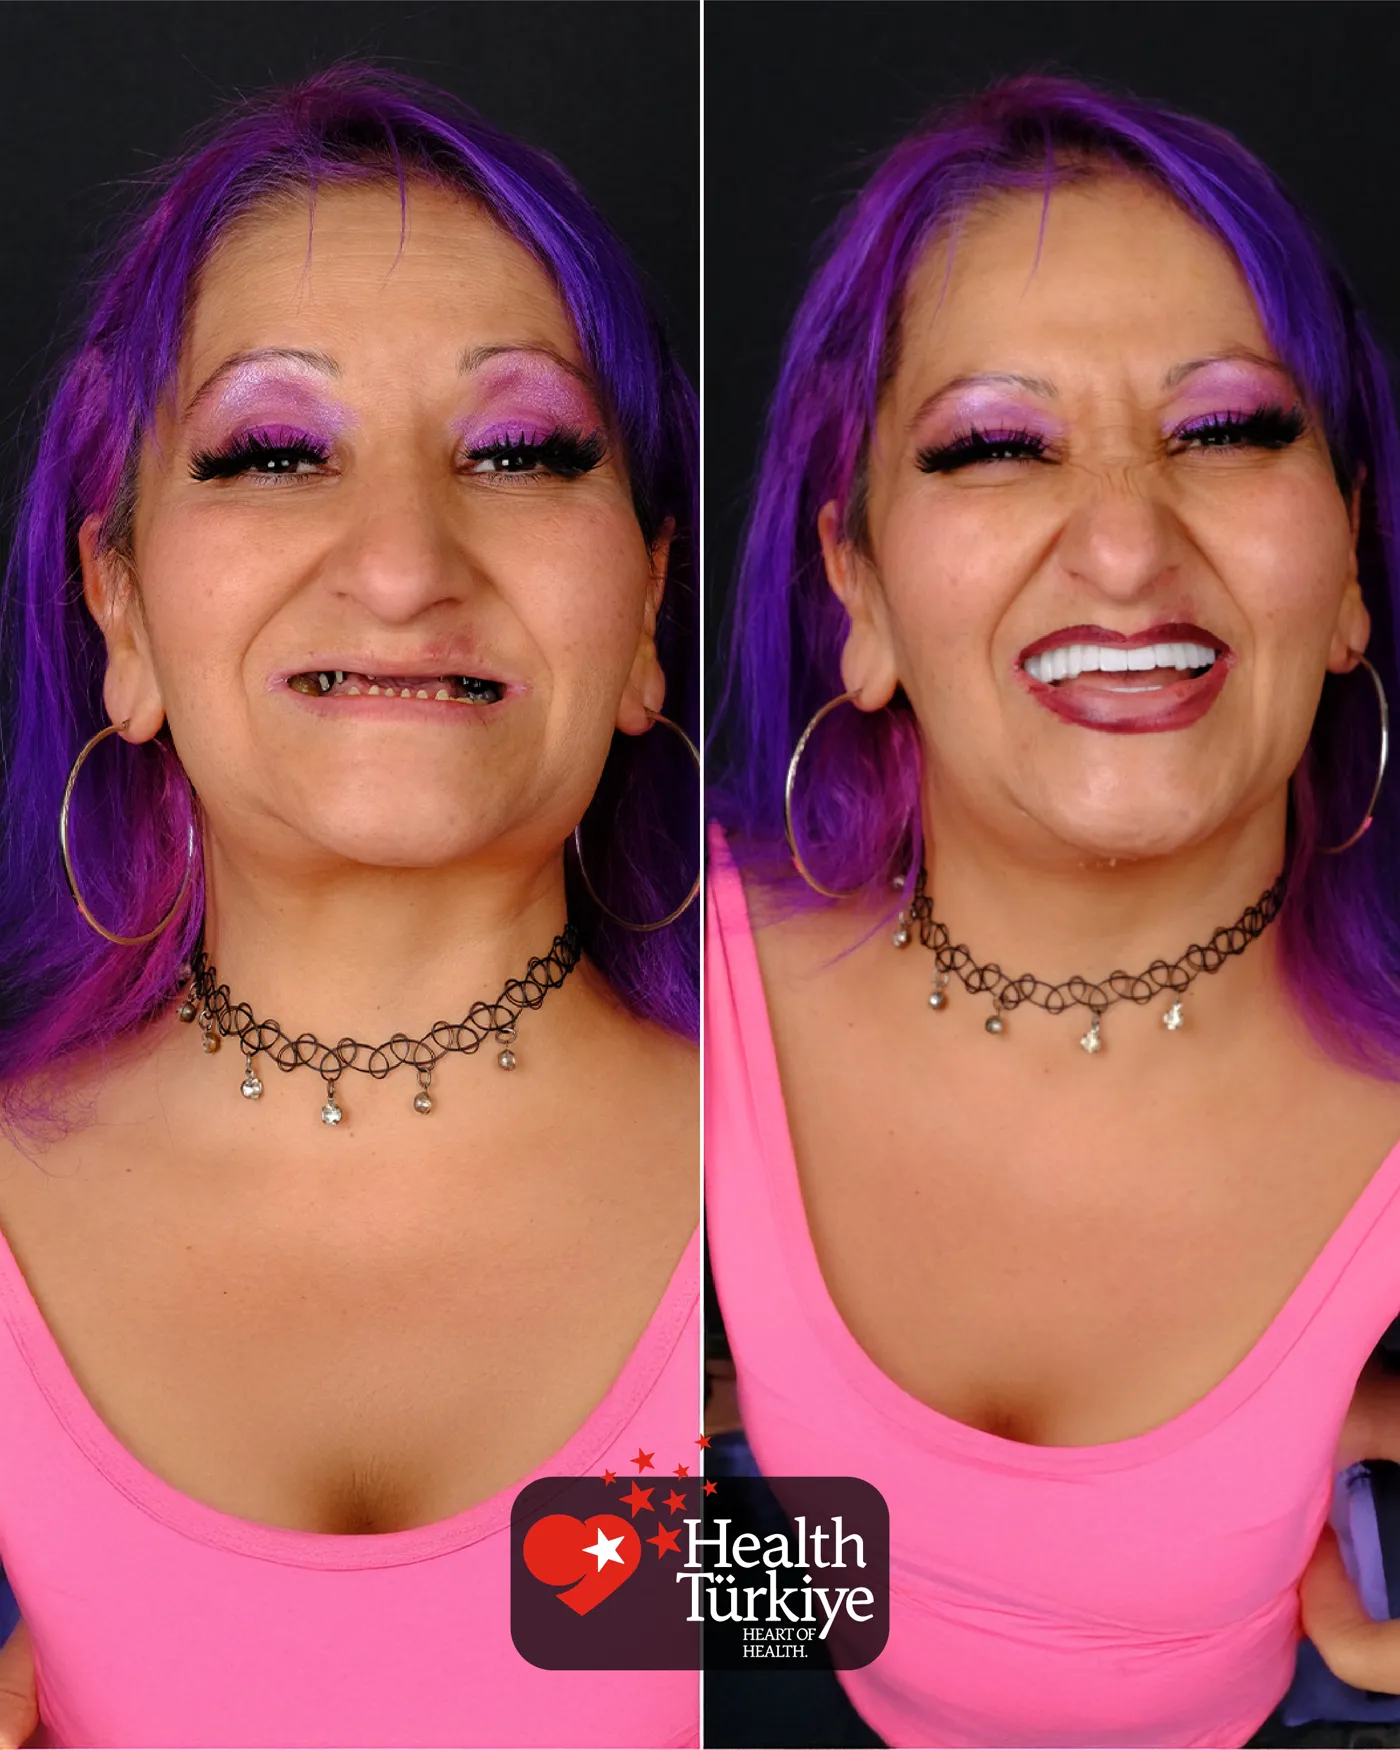
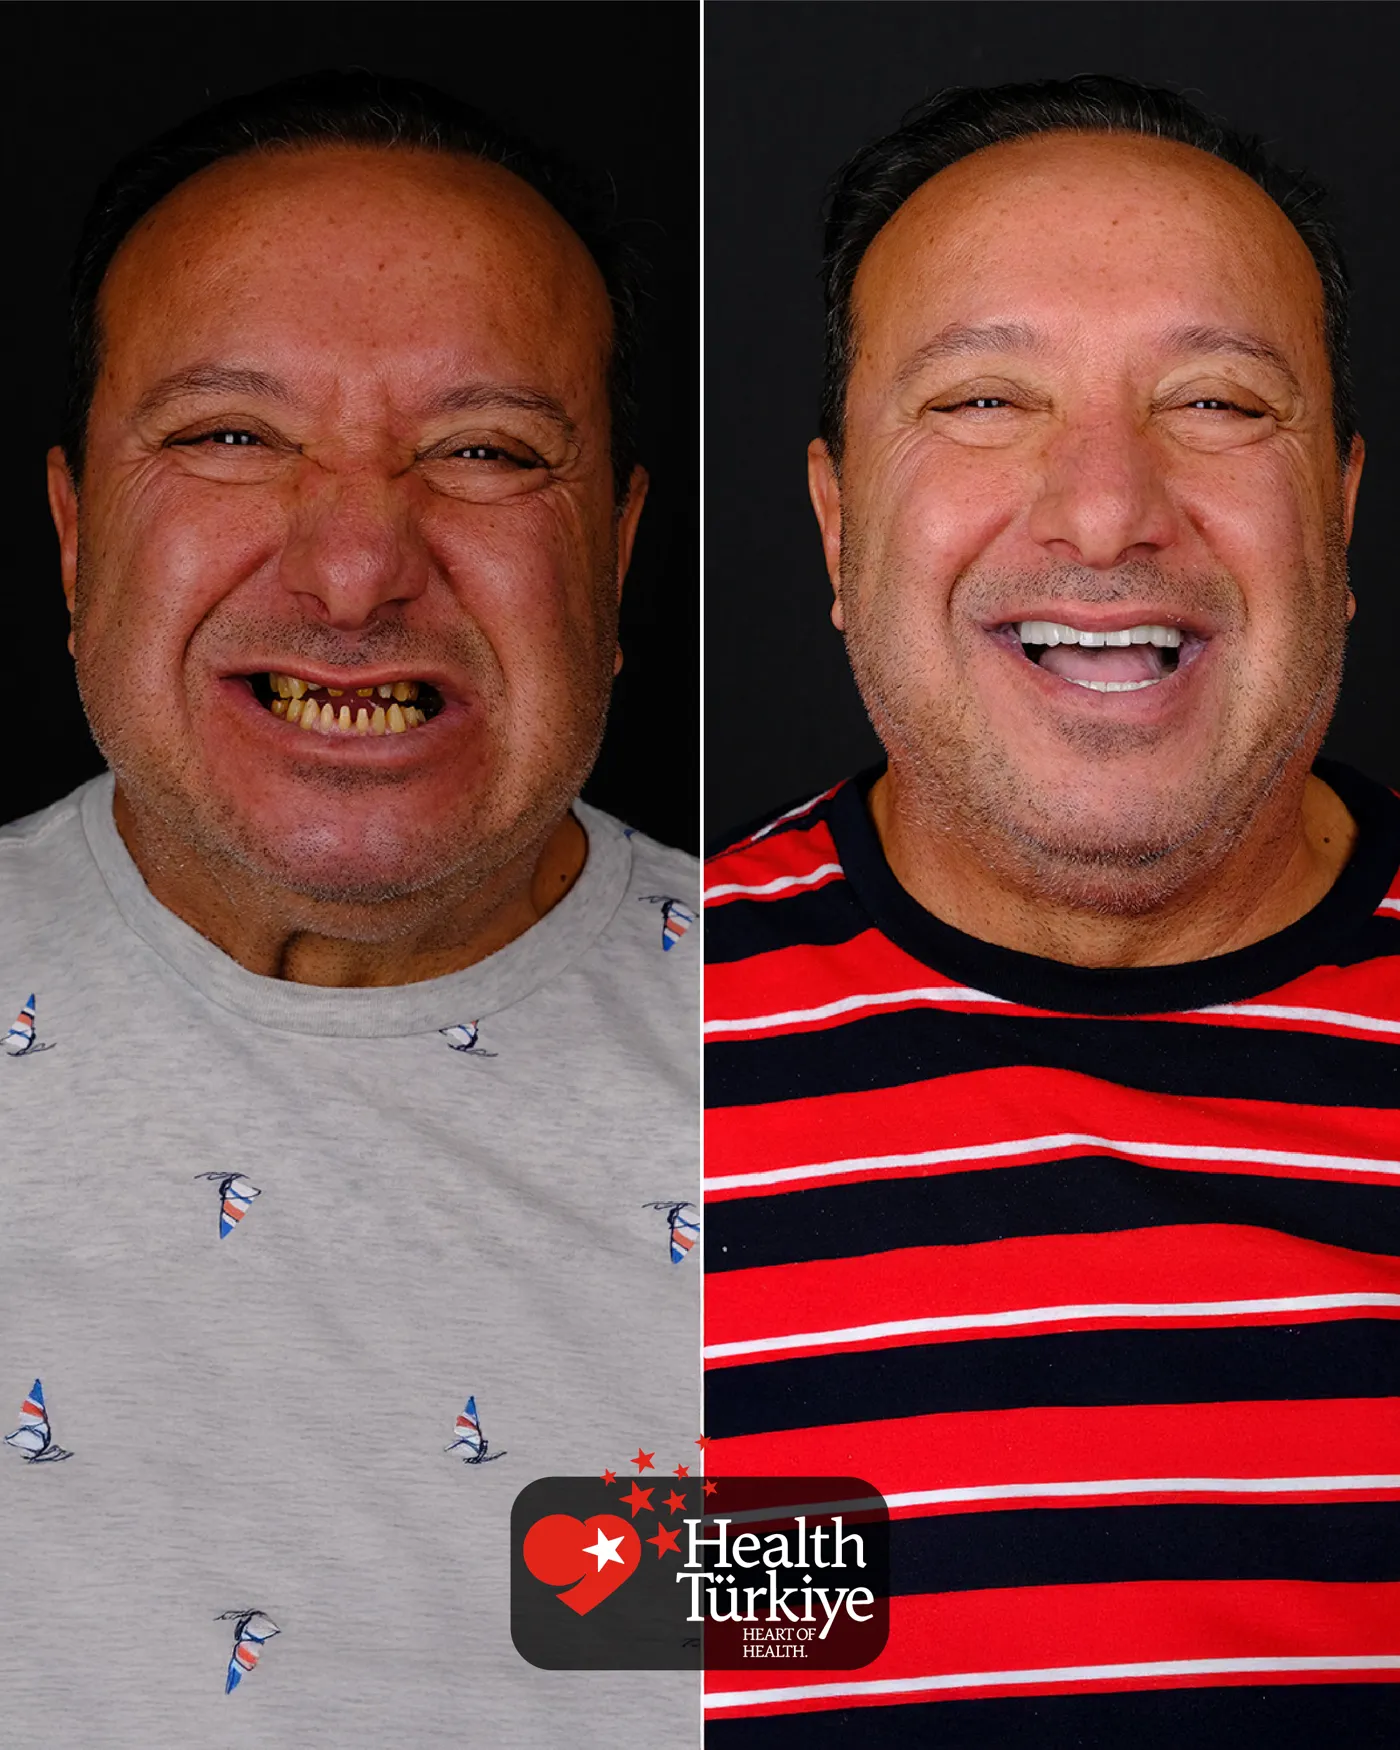
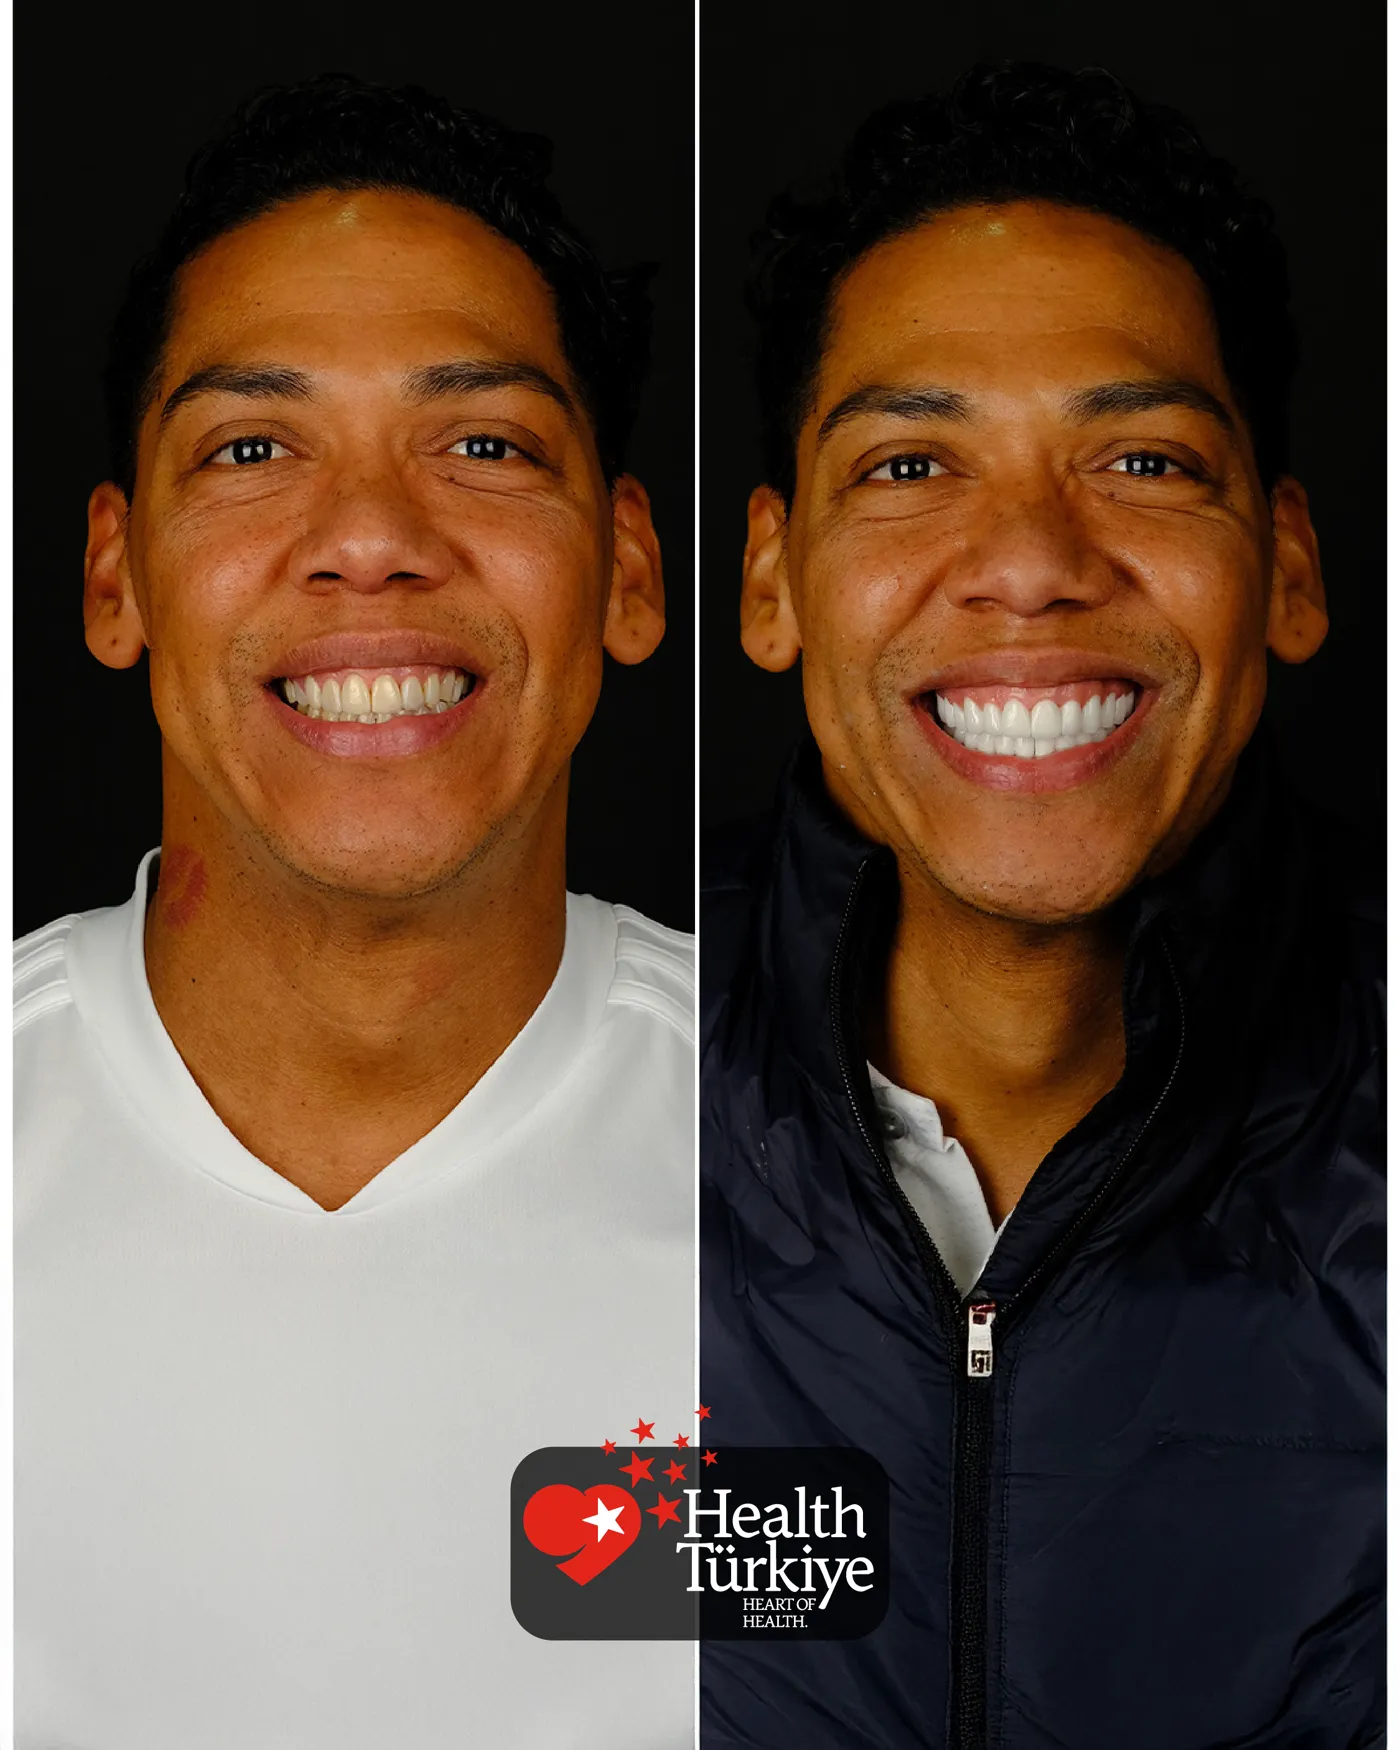
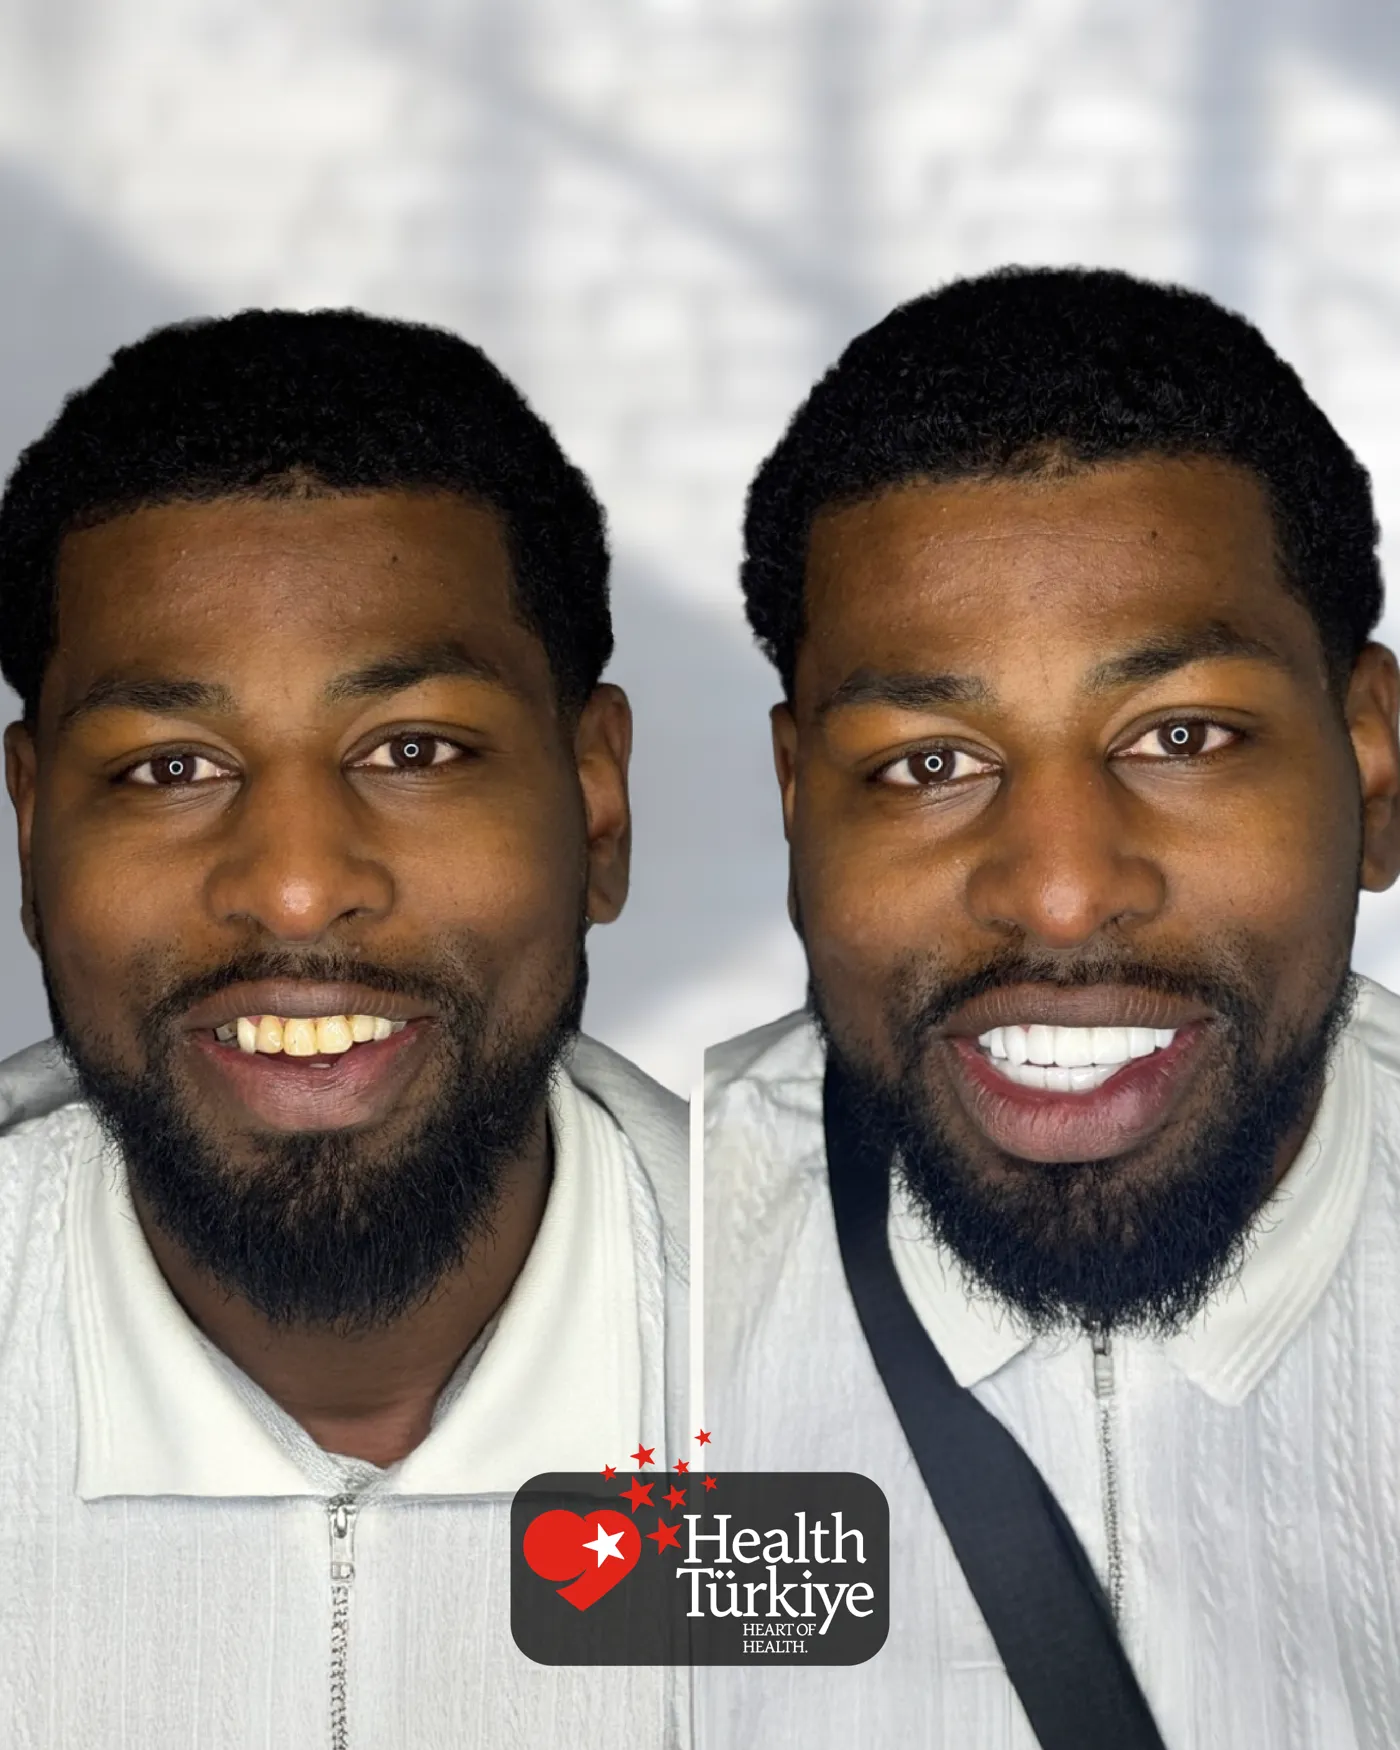
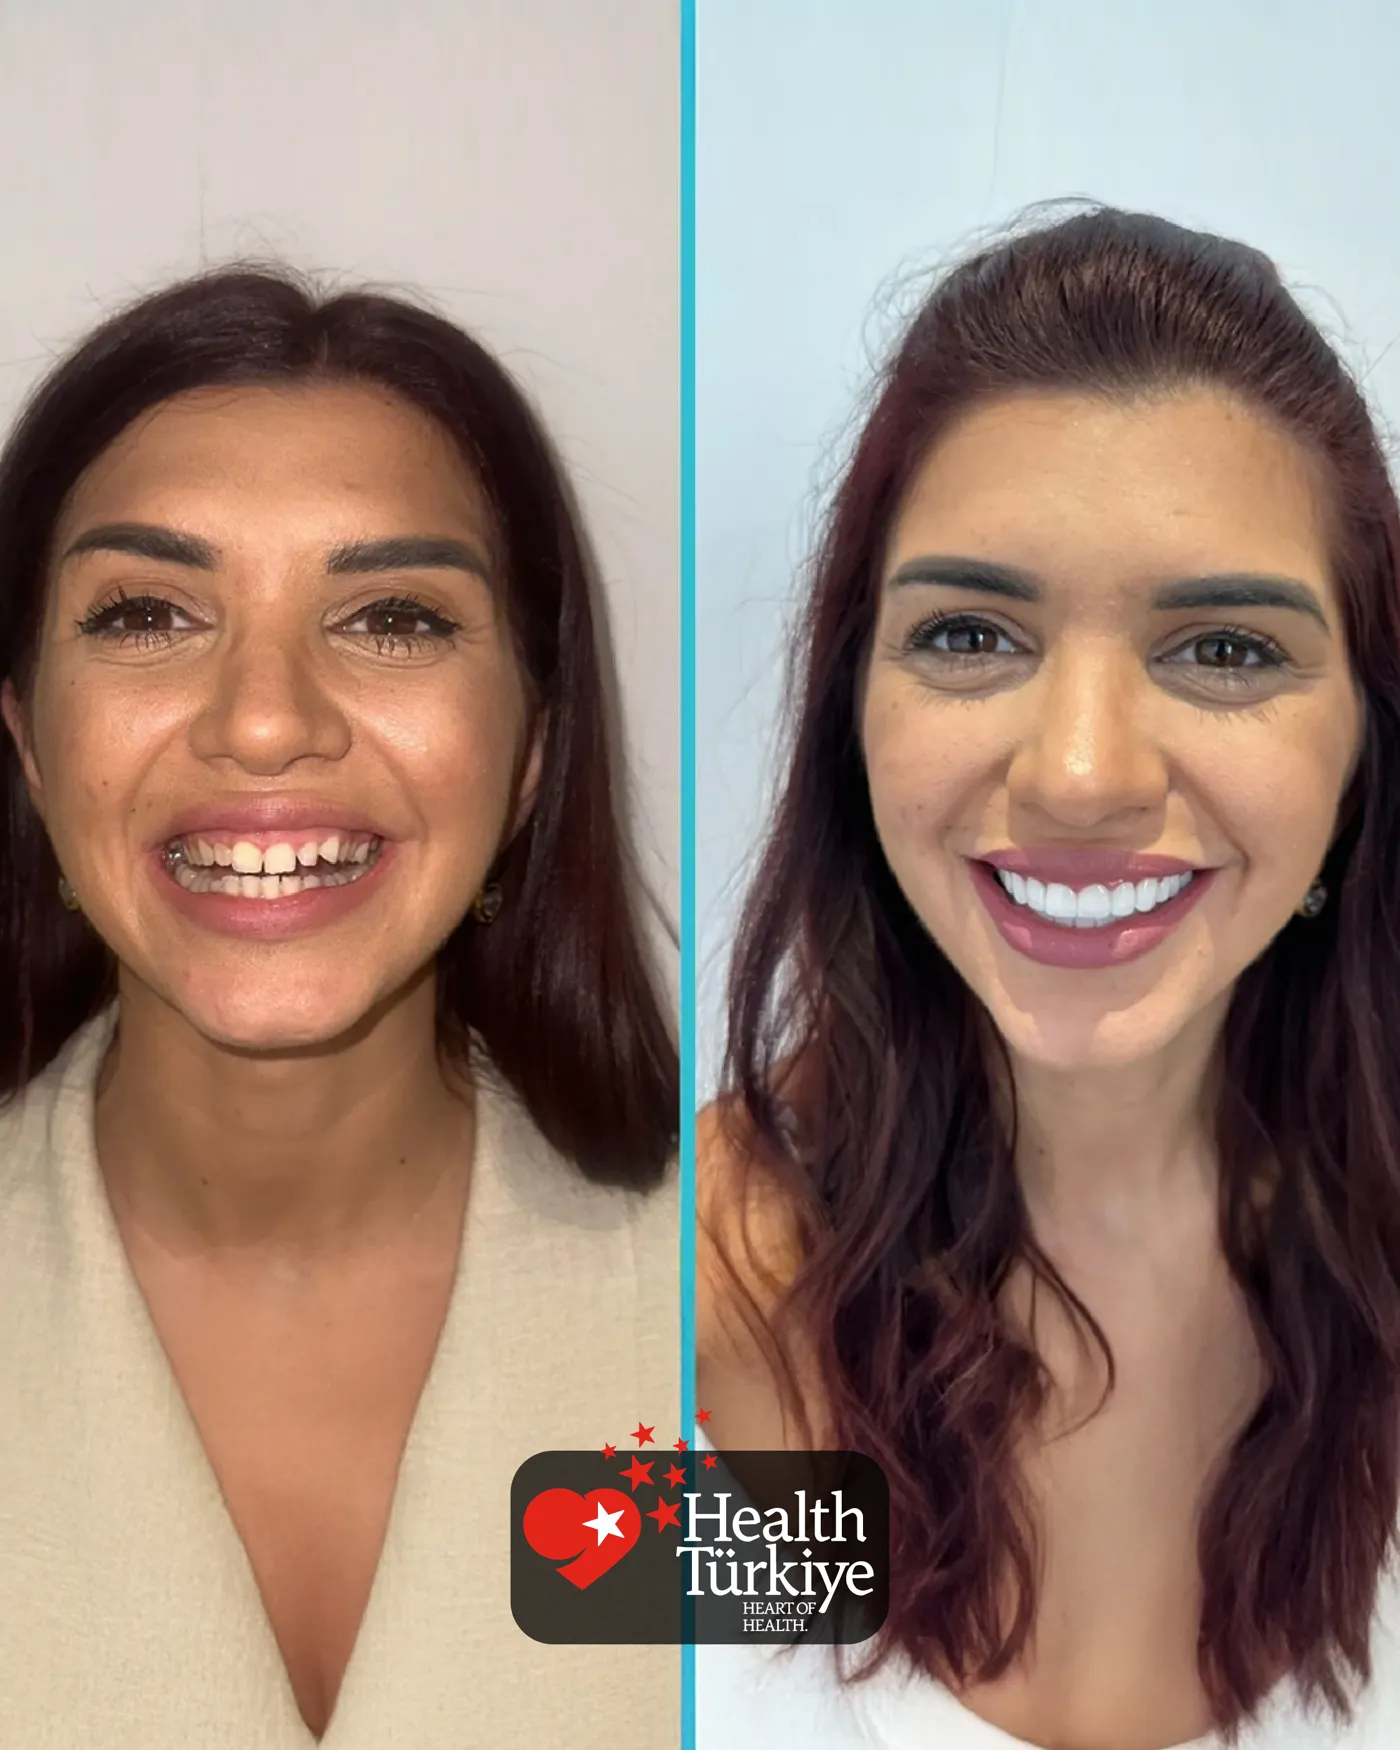
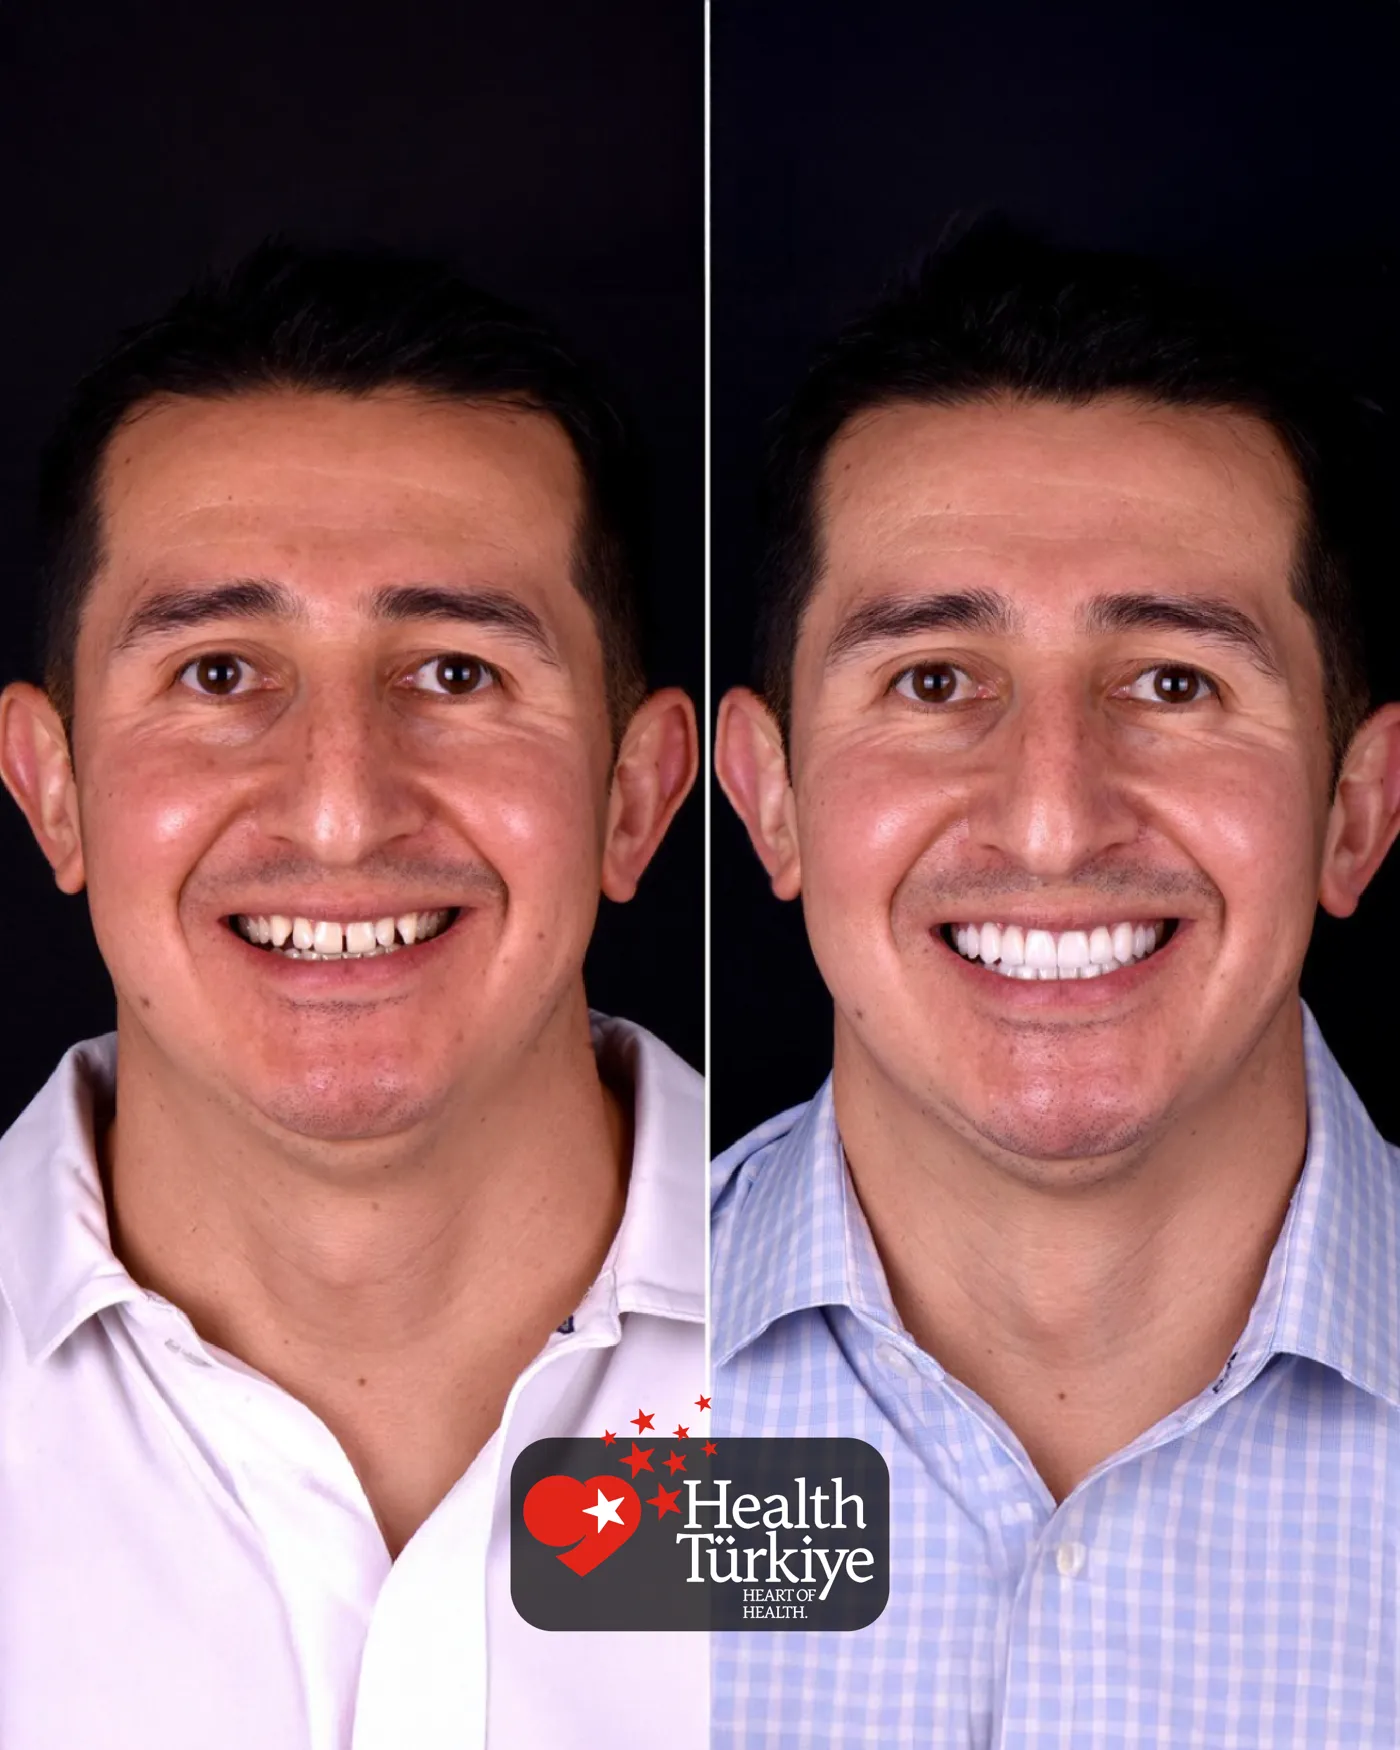
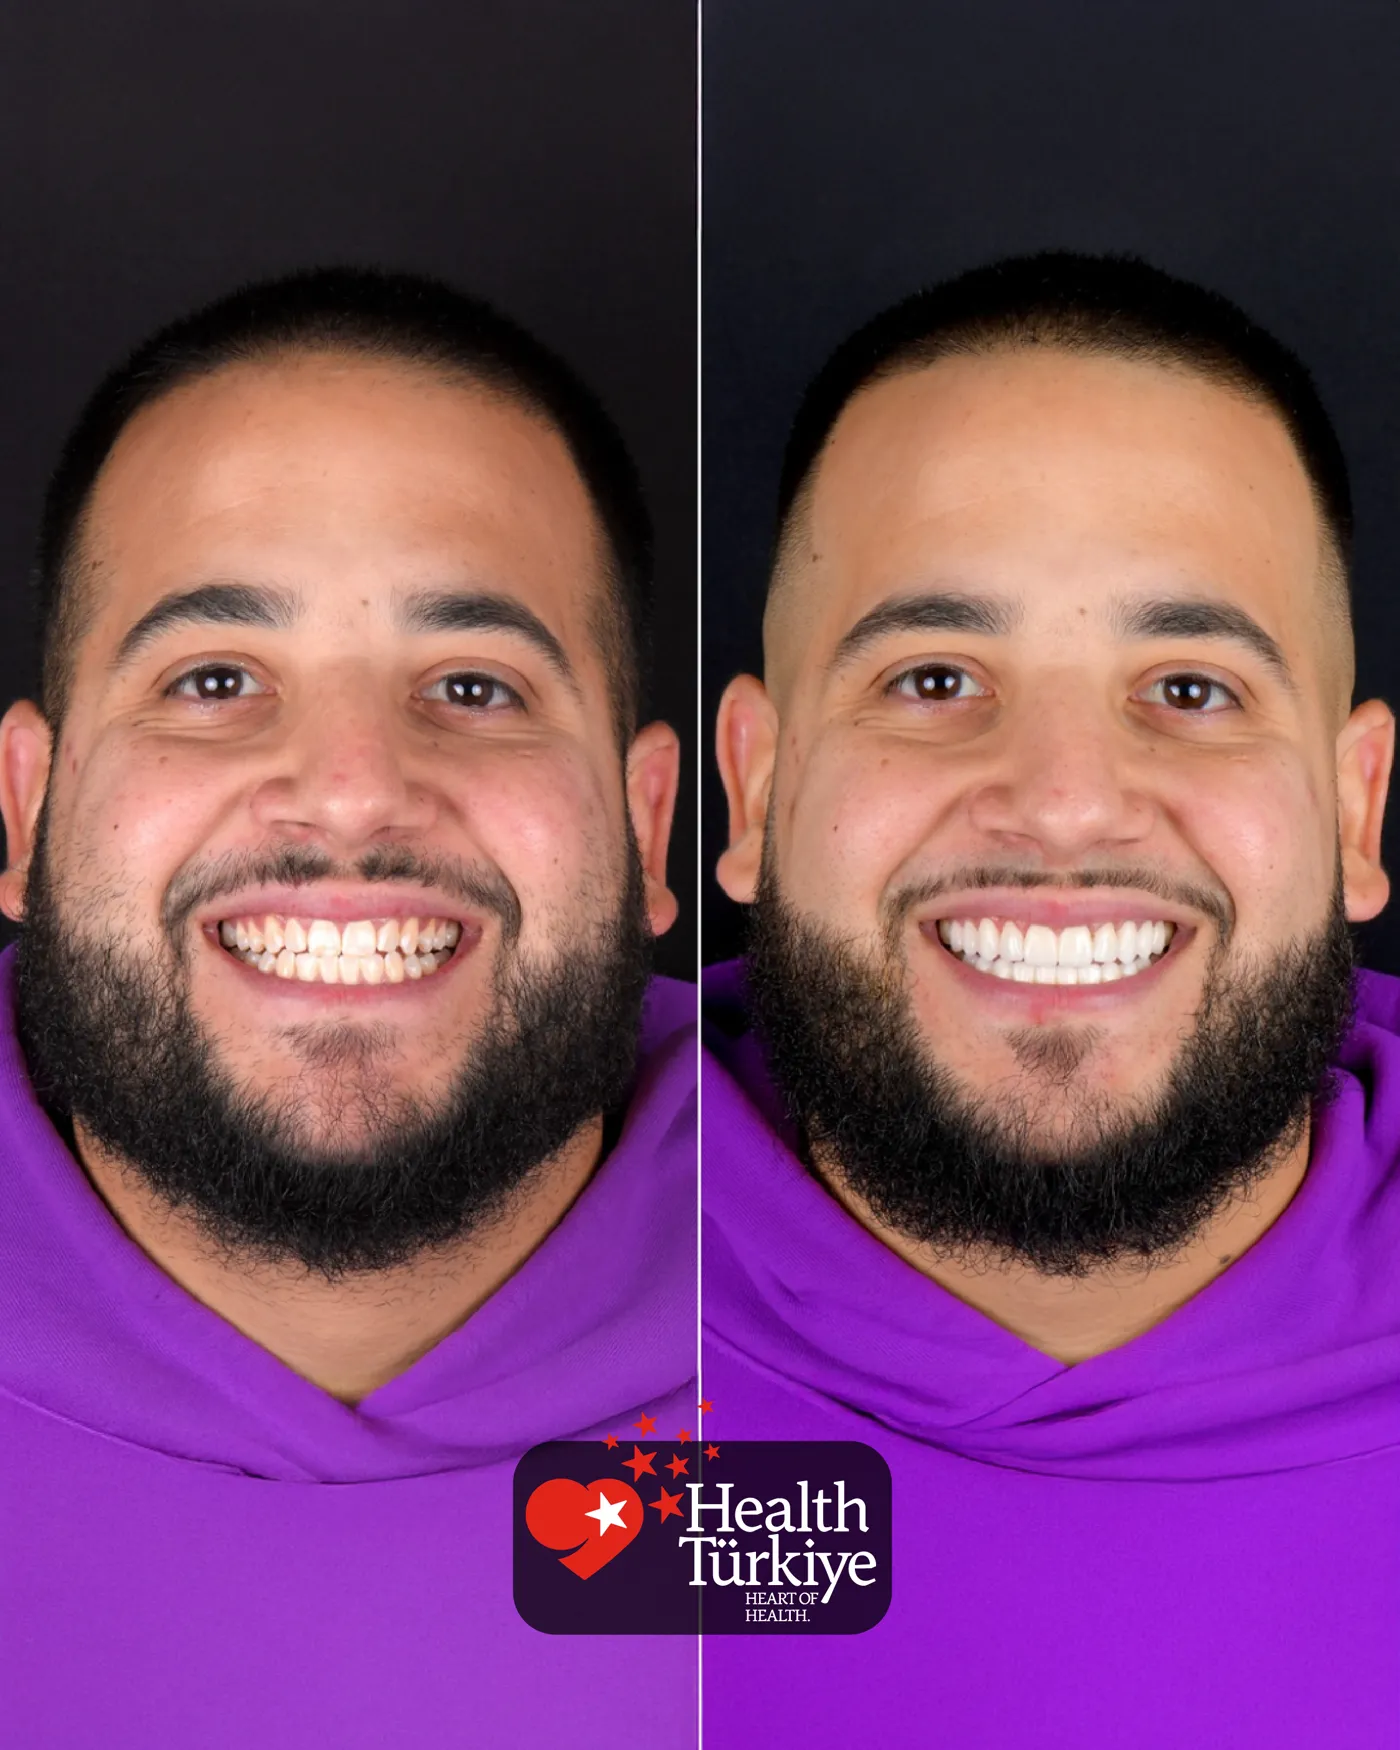
E-max porcelain veneers in Muratpasa, Antalya — covering only the front surface with minimal reduction.

✦ Our Patients

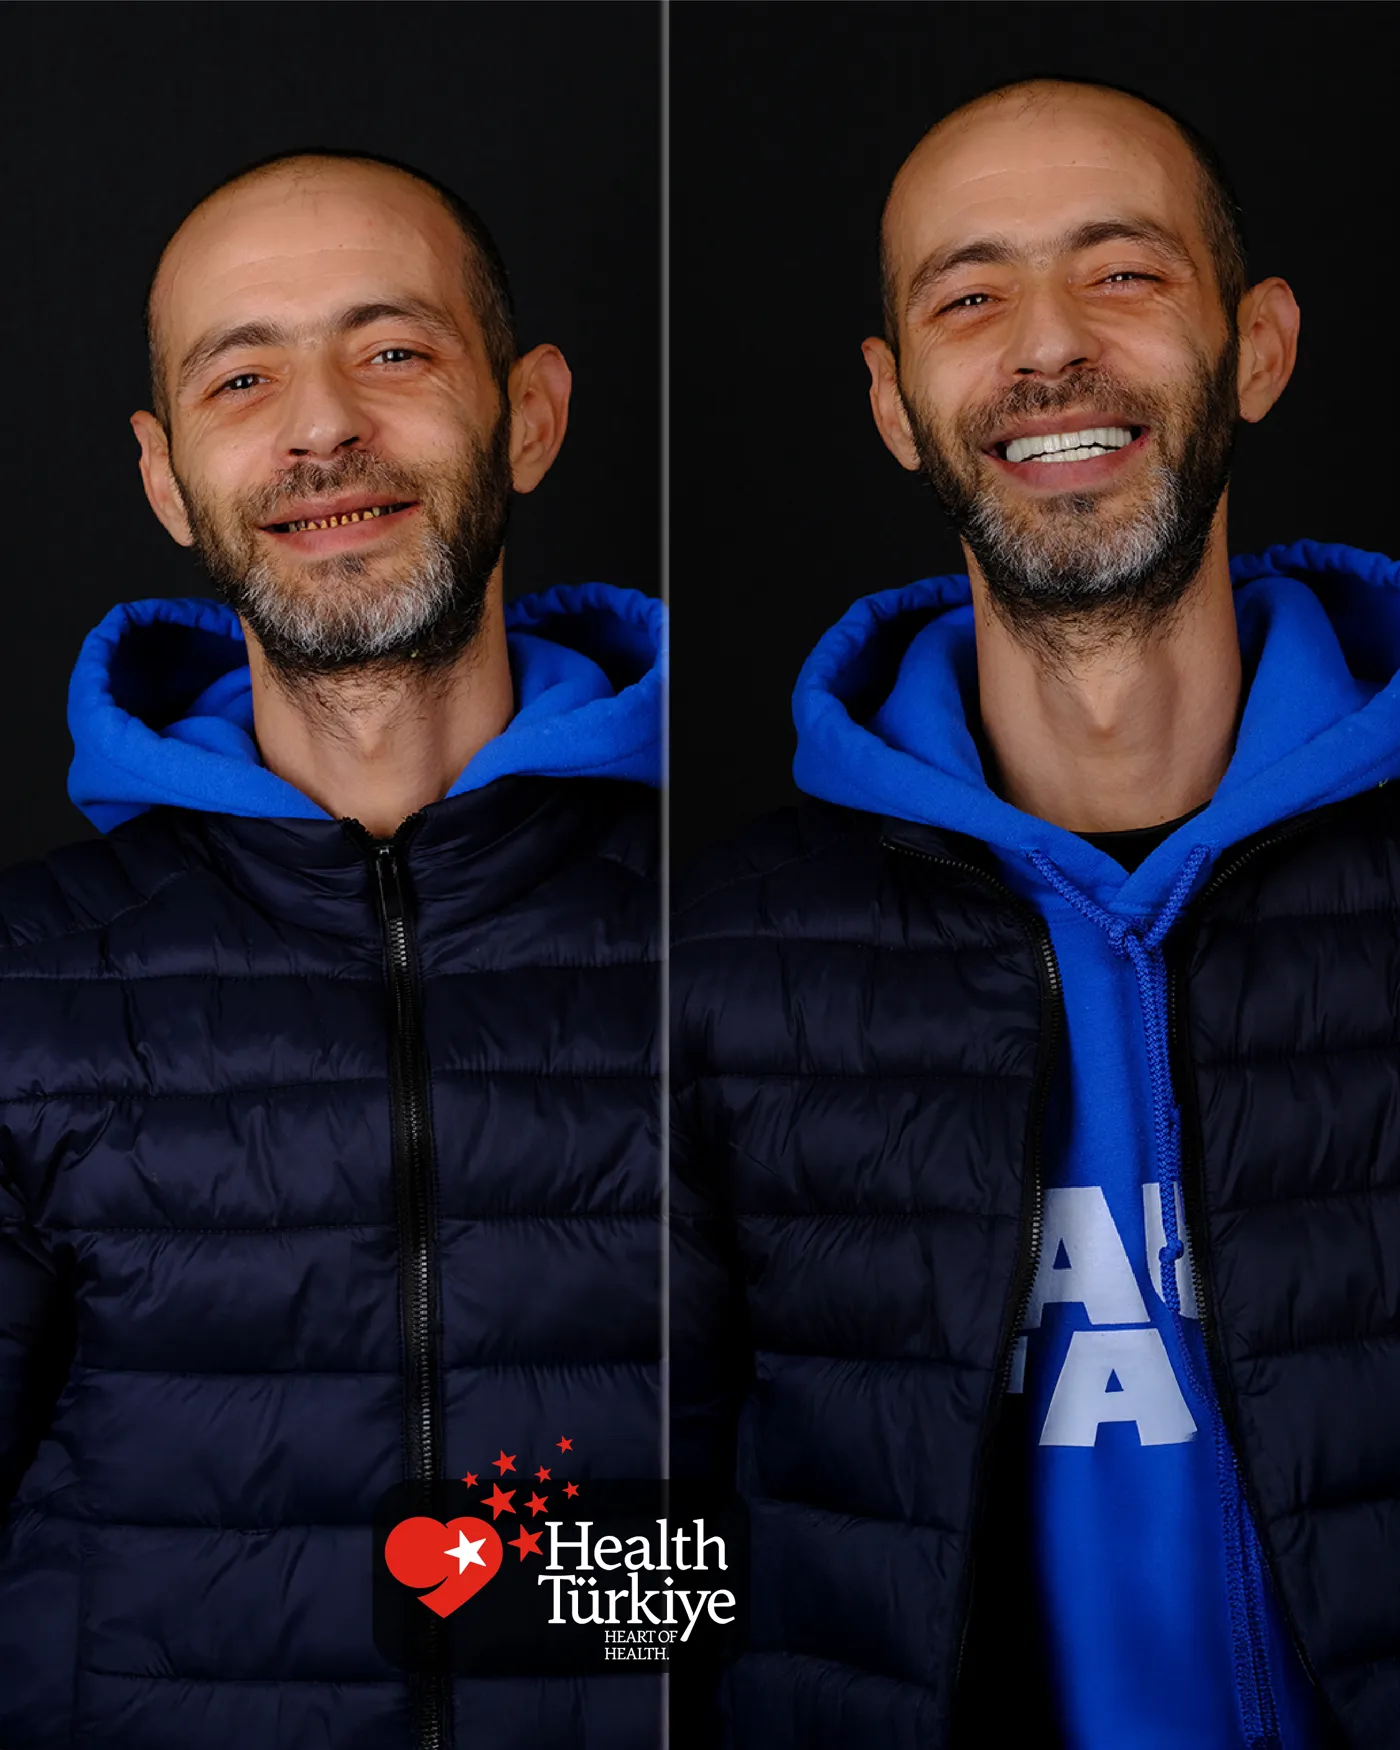
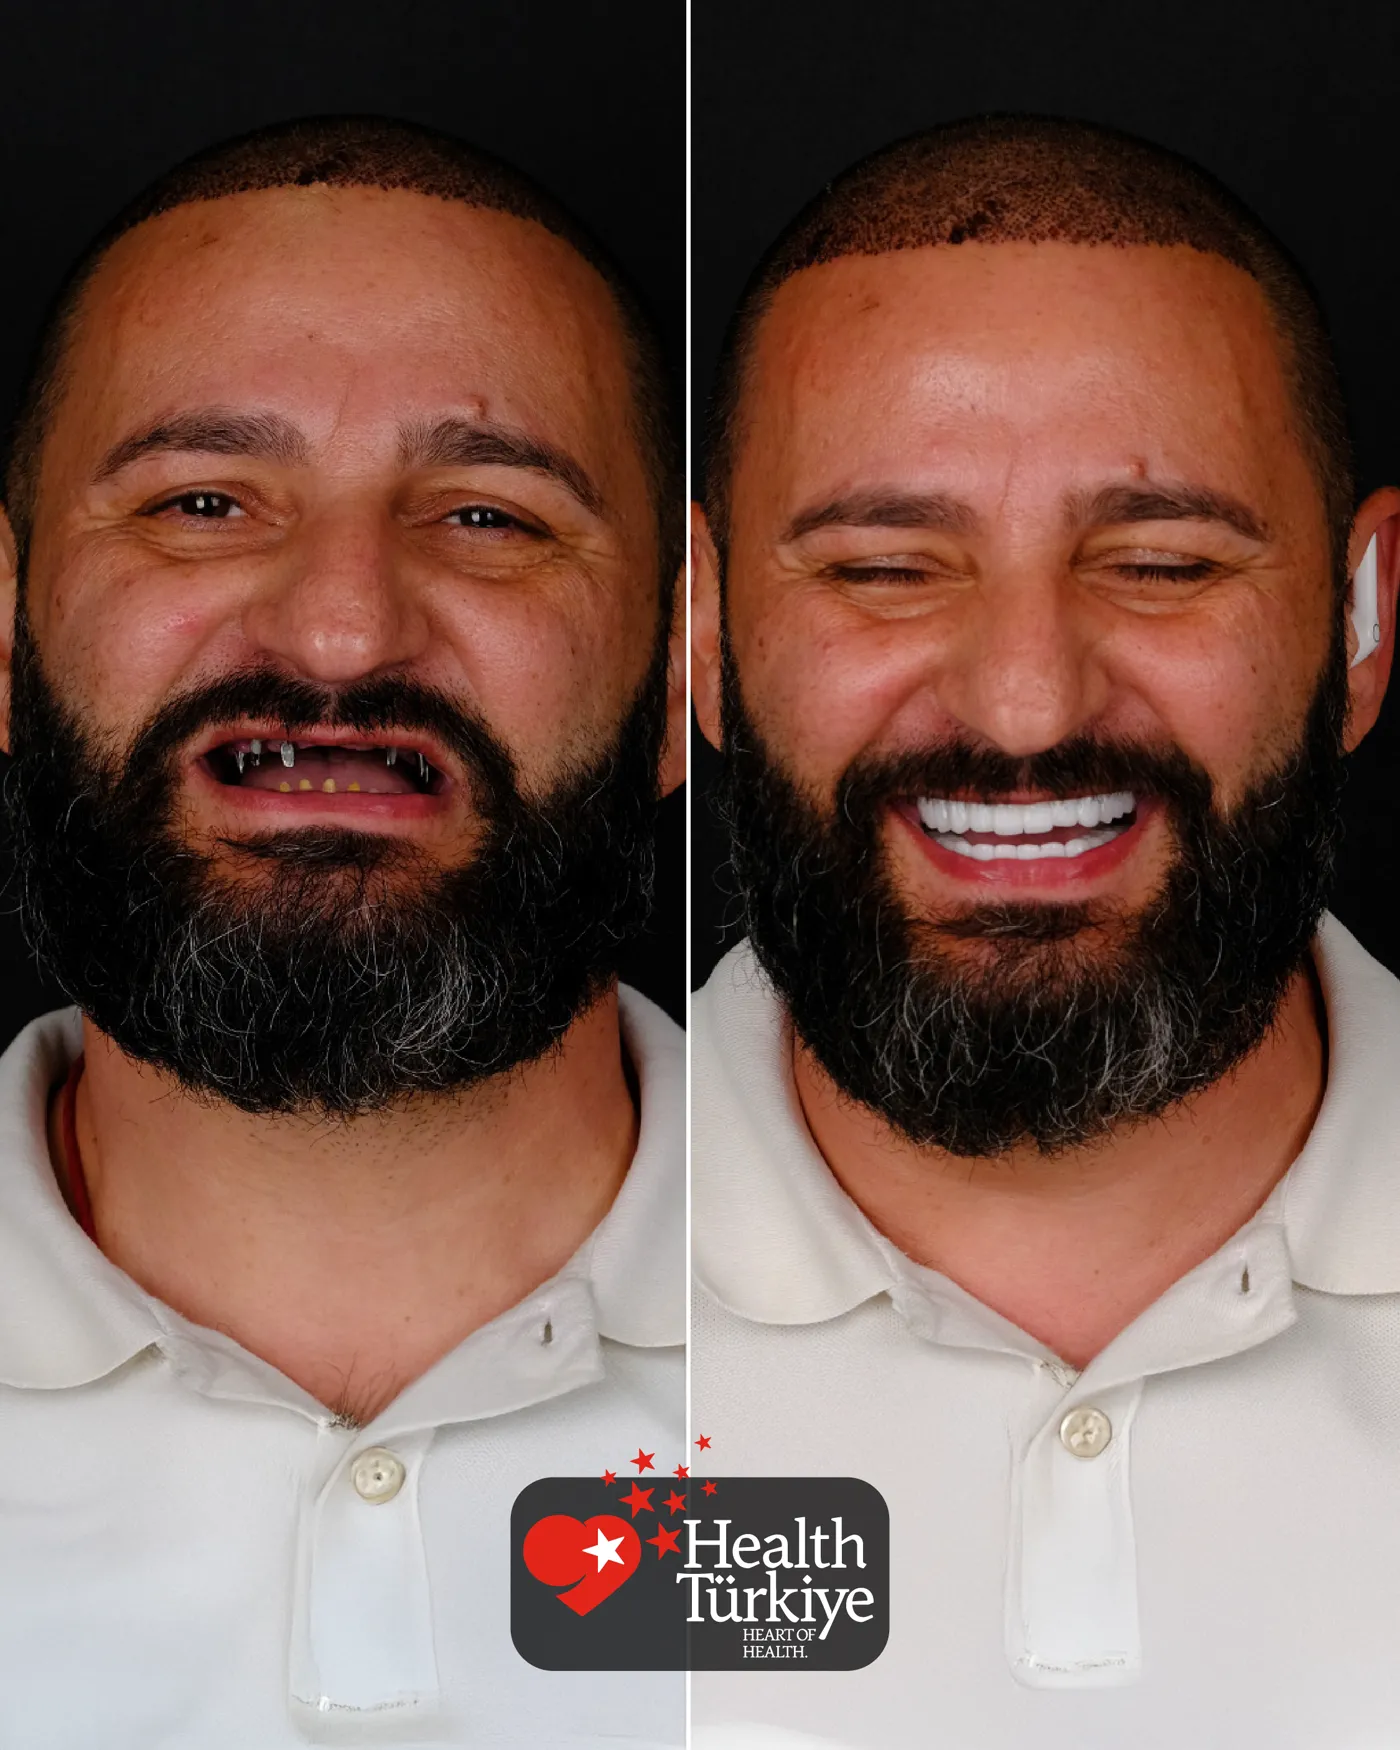
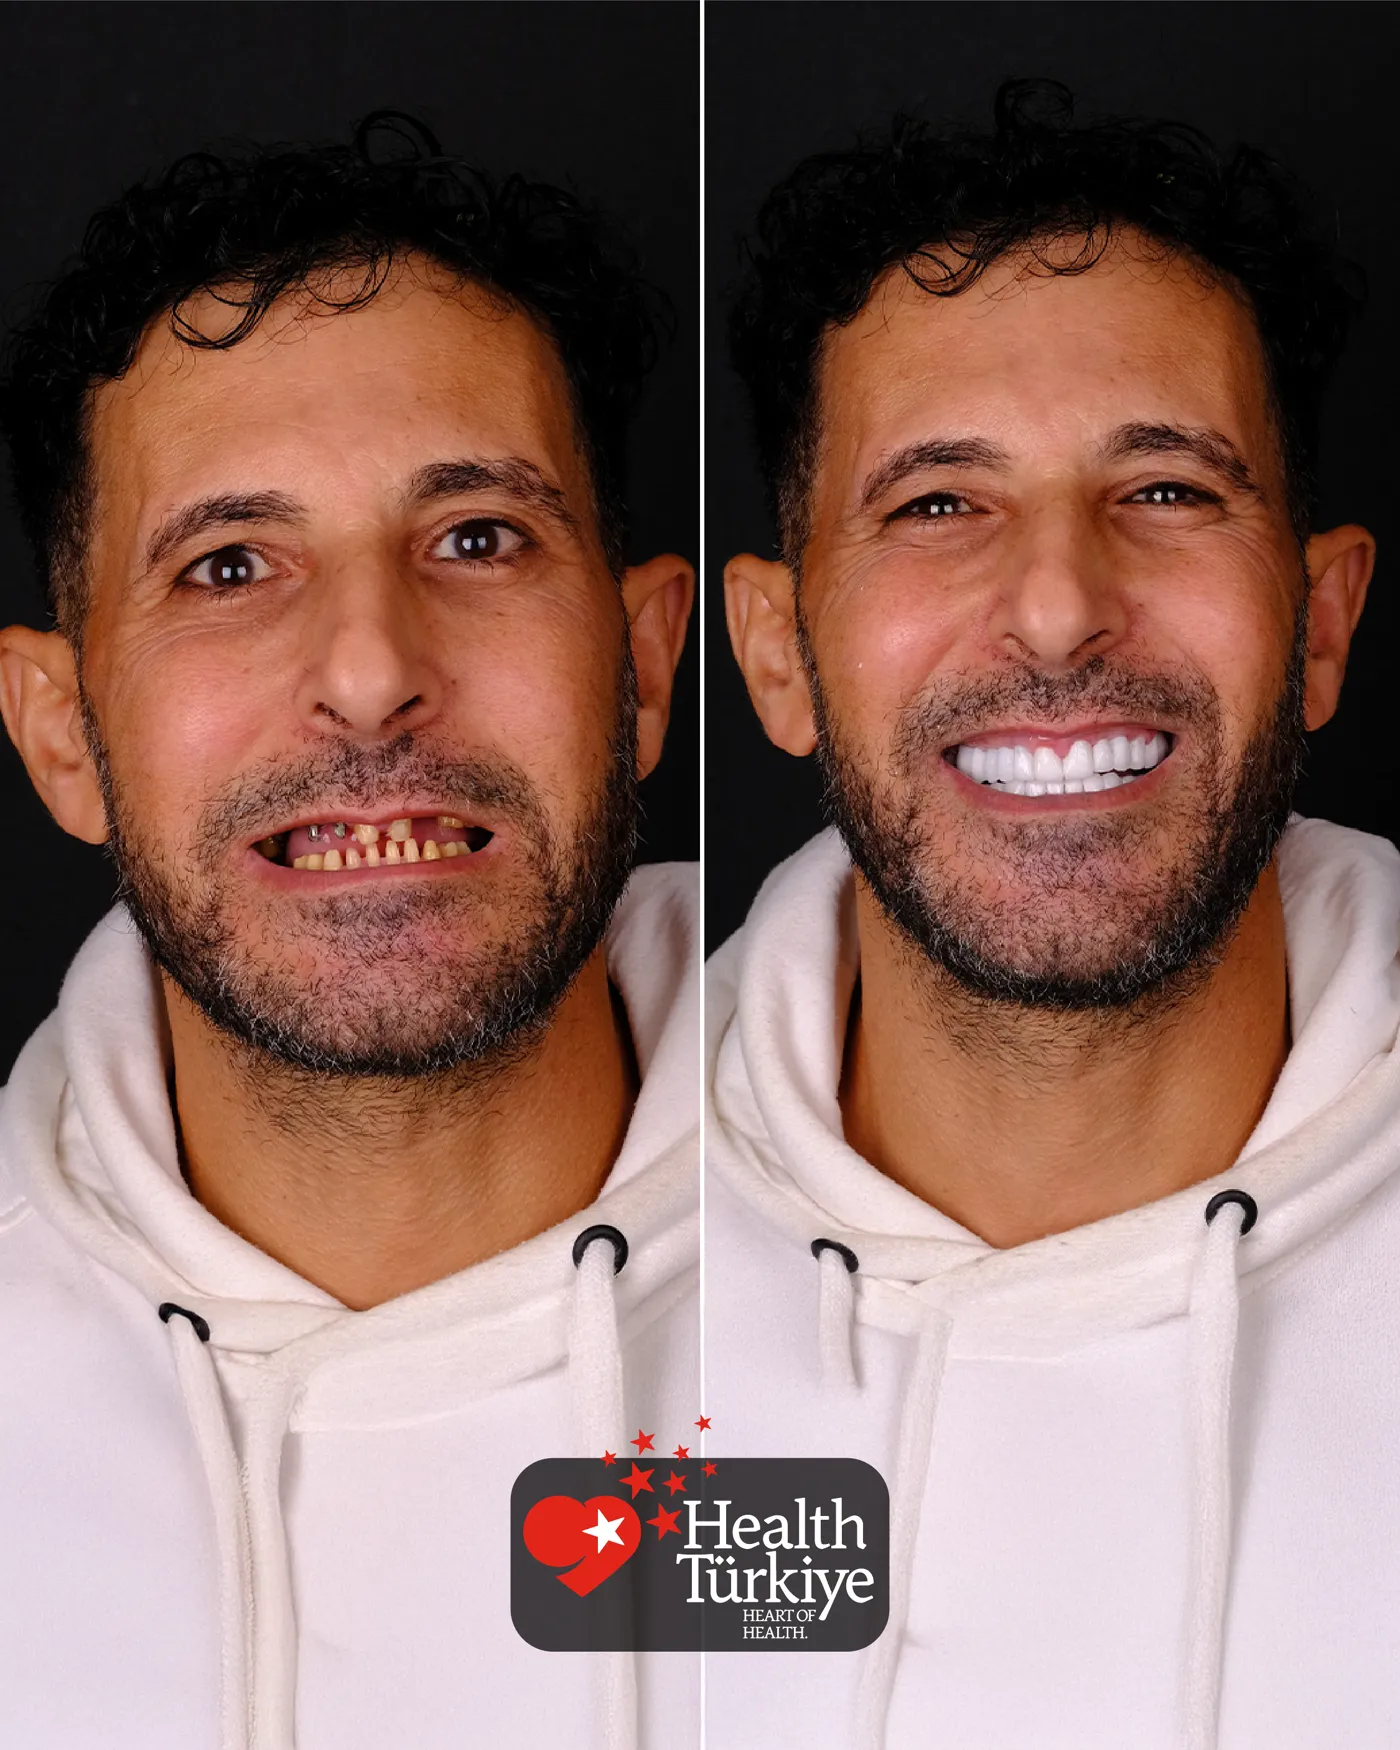
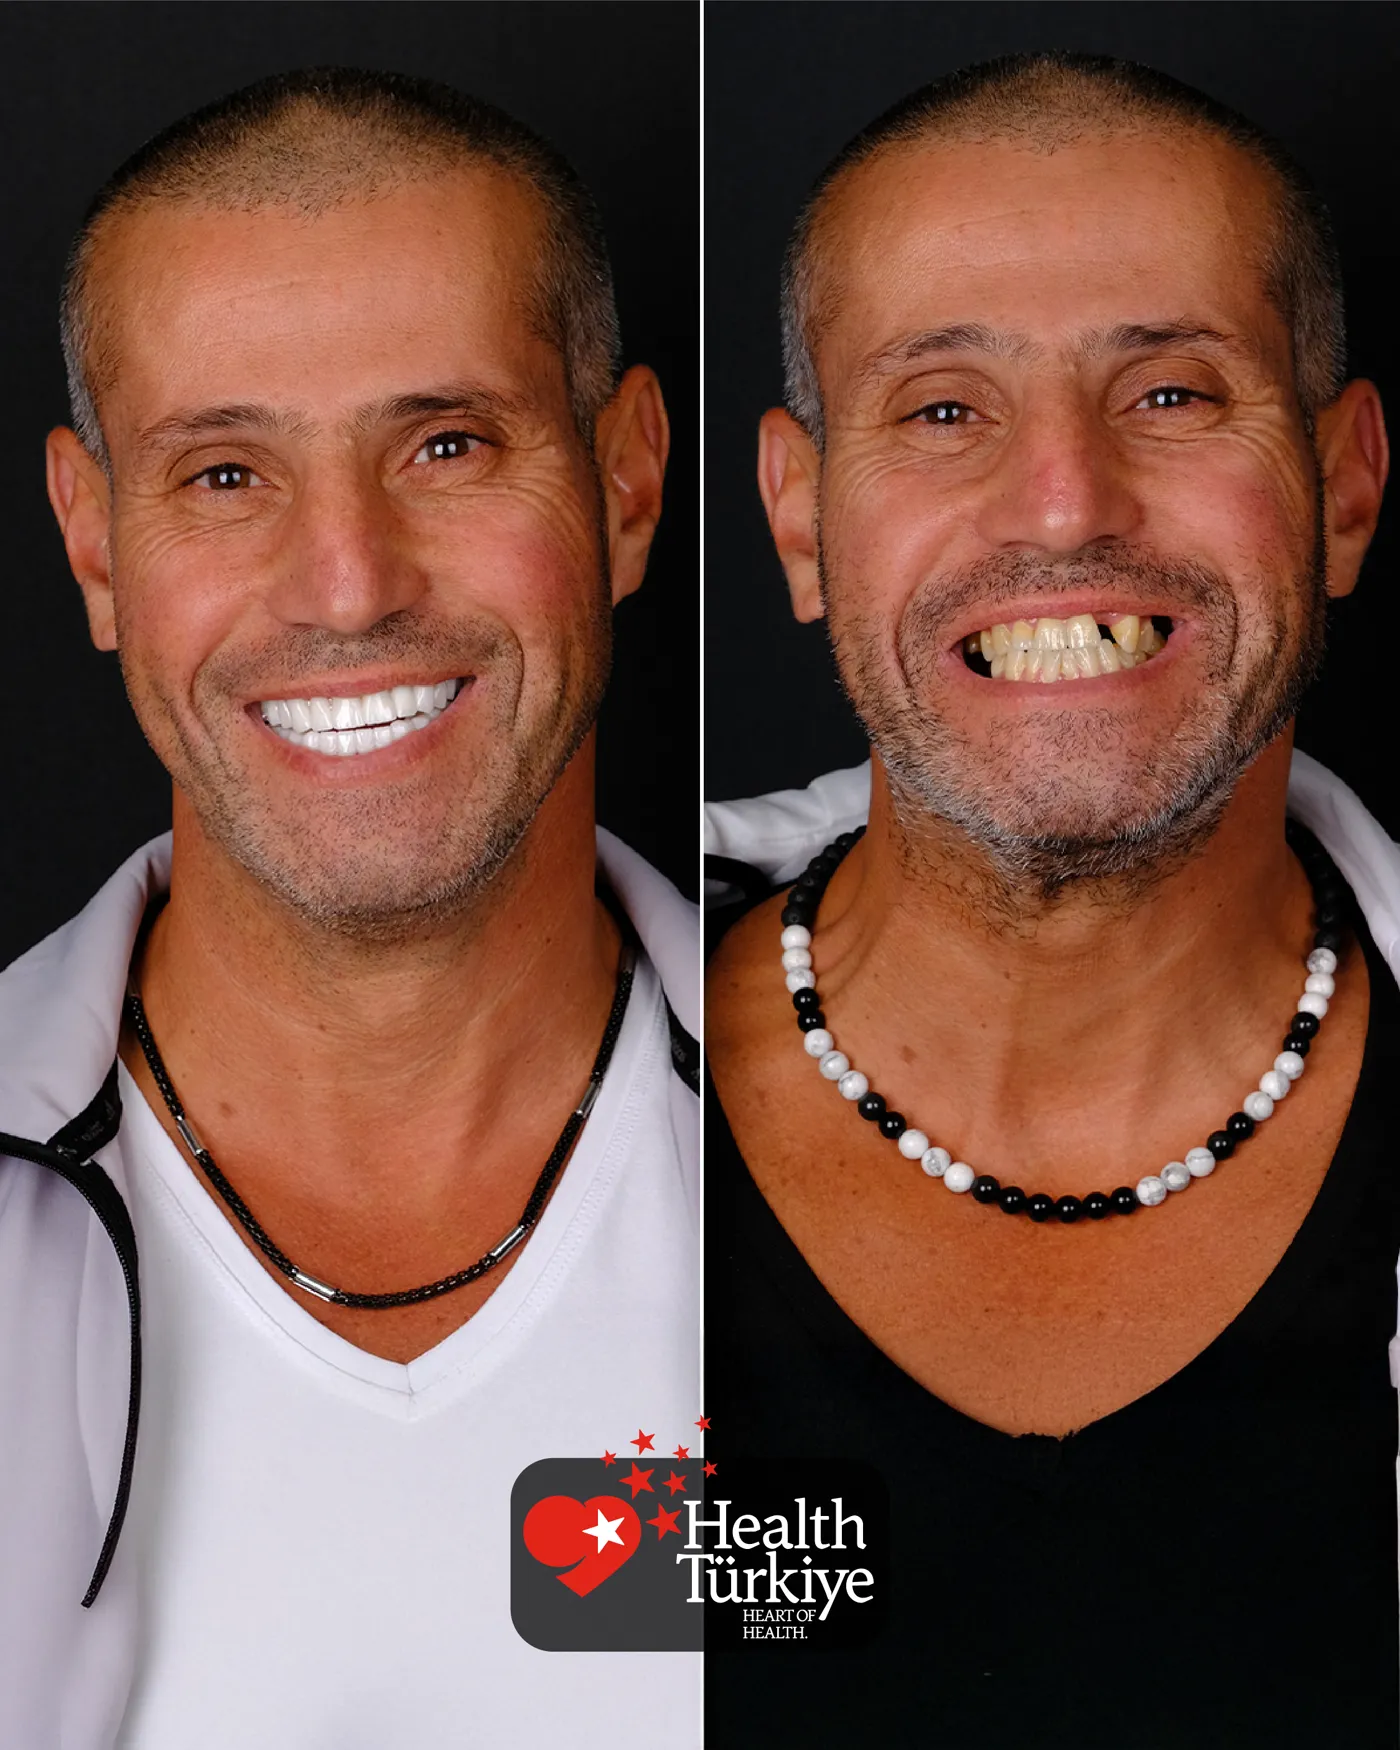
Photos from treatments performed at our clinic

Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
✦ Our Clinic
kliniğimiz
kliniğimiz
kliniğimiz
kliniğimiz

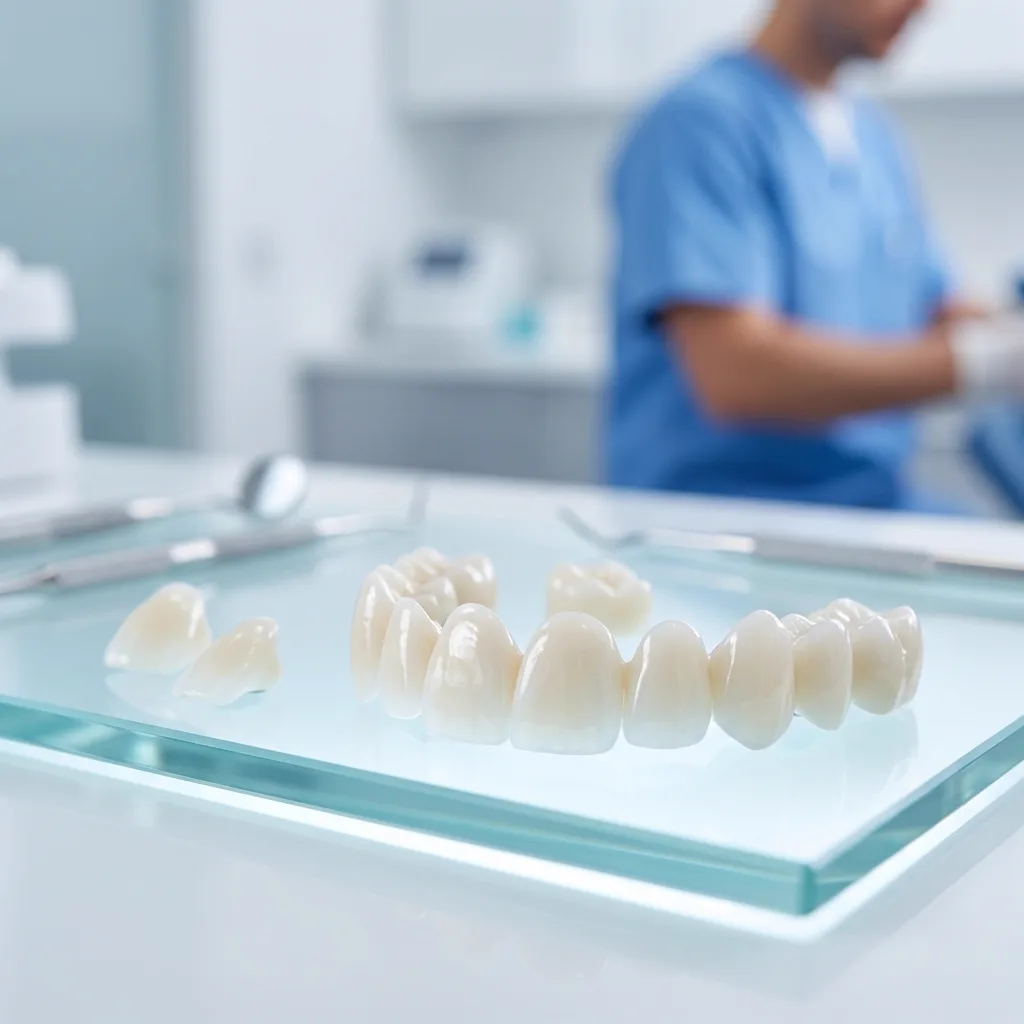
A porcelain veneer is a thin ceramic layer bonded to the front surface of a tooth, changing shape, colour and size without encircling it as a crown does.

The main advantage is tissue preservation: a crown requires significant reduction on every surface, whereas a veneer removes only a very thin layer from the front.

E-max is a lithium disilicate glass ceramic whose translucency closely matches natural enamel.

Who Are E-max Veneers Suitable For?

Veneers are an aesthetic solution requiring a sound underlying tooth — a distinction that determines success.

Suitable cases

  • Discoloration that does not respond to whitening
  • Gaps between front teeth
  • Minor shape and size irregularities
  • Small chips and wear at the incisal edges
  • Mild crowding where orthodontics is declined
  • Surface stains and enamel striations

When veneers are not appropriate

With extensive loss or after root canal treatment a veneer lacks support and a crown is needed. In significant crowding, veneering to mask misalignment requires excessive reduction — orthodontics comes first.

Veneer, crown or bonding?

The choice balances tissue loss against durability: bonding is least invasive but shorter-lived; a veneer gives a durable natural result with minimal reduction; a crown requires most reduction but is the only safe option for weakened teeth.

The E-max Veneer Process

The process usually takes two appointments with a laboratory stage in between.

Planning and mock-up

The new shape is planned digitally and trialled in the mouth with a temporary material — reversible, with no tissue loss.

Preparation and impression

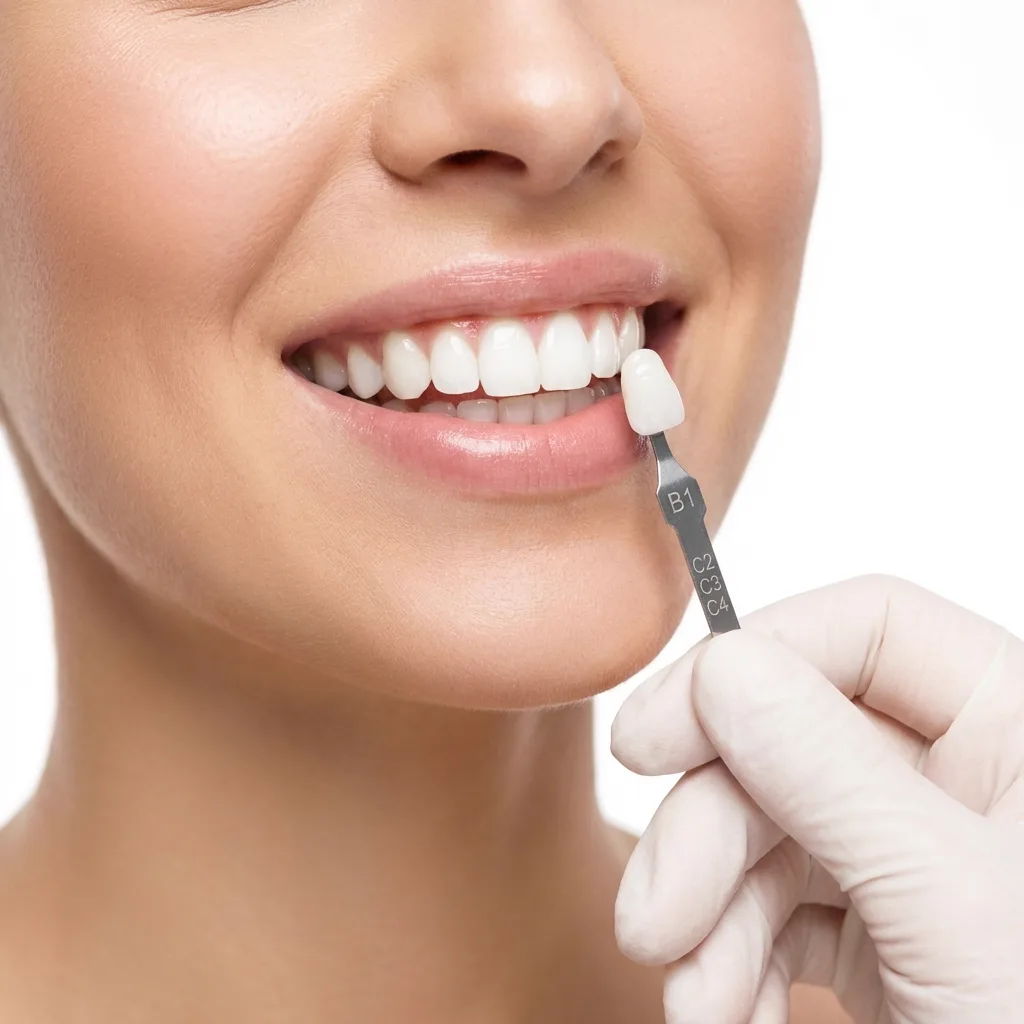
A very thin layer is removed from the front surface; in some cases no reduction is needed at all. An impression is taken and the shade matched to adjacent teeth.

Try-in and bonding

The veneers are tried in with temporary paste to check shade, fit and occlusion, then bonded with a specific adhesive system. The bonding technique is critical to longevity.

Aftercare and Longevity

Longevity depends most on controlling the forces applied to the veneers.

Habits to avoid

  • Biting nails, pen caps, ice and hard shells
  • Using teeth as tools to tear tags or thread
  • Uncontrolled grinding and clenching
  • Abrasive toothpaste and stiff brushes

Why a night guard matters

Grinding is the most common cause of veneer fracture; night-time forces far exceed conscious biting. For patients who grind, a night guard is part of the treatment, not optional.

Staining and cleaning

Porcelain stains far less than composite, though the margin between veneer and natural tooth can discolour. Regular cleaning and six-monthly professional maintenance reduce this.

Deciding Between E-max Laminates and the Alternatives

There is more than one route to the same aesthetic concern; the choice depends on how much tissue is involved and on what is expected from the result.

The Difference Between Bonding and Laminates

Composite bonding is shaping carried out with a filling material applied directly to the tooth; it is usually completed in a single visit and in most cases involves almost no reduction of tooth tissue. It suits small fractures, gaps and limited changes of shape.

An e-max laminate is a thin ceramic layer produced in a laboratory, giving a different result in terms of colour stability and surface lustre. It does, however, require some preparation, however slight, and is less reversible than bonding. For many people the right approach is choosing one or the other, or a combination, according to the size of the problem.

Situations That Call for a Crown Rather Than a Laminate

A laminate covers only the front surface and the incisal edge of a tooth, so it requires sound and sufficient tooth tissue behind it. Where there are large fillings, extensive loss of substance or a tooth weakened after root canal treatment, that support may not be enough.

In such cases a crown that encircles the tooth may be more suitable because it distributes forces more evenly. In severely discoloured teeth, a thin ceramic layer may also not fully mask the underlying colour. This assessment is made together with examination and radiographs; the decision rests on how much of the tooth remains sound.

How Orthodontics Relates to Aesthetic Restorations

Where there is marked crowding or a bite discrepancy, trying to mask it with restorations alone can mean removing more tooth tissue. If the teeth are aligned with orthodontic treatment first, the laminates placed afterwards can be far thinner and more conservative.

In some cases even short-term orthodontic preparation can reduce the number of restorations needed. The first question in aesthetic planning is therefore not which material to use, but whether correcting the position of the teeth would improve the result. After assessment, the route that suits you is explained in detail.

Misconceptions and Common Mistakes With Laminates

Most cases of dissatisfaction with laminates arise not from the material but from expectations that were never discussed and preparation stages that were skipped.

Setting Realistic Expectations for Colour and Size

A very light shade or teeth longer than they should be may look striking at first, but they leave an artificial impression when they do not match the features of the face. A natural result comes from assessing tooth length, the midline, lip movement and the gum line together.

Colour selection is therefore not a decision made from a shade guide alone. Skin tone, the whites of the eyes, lip fullness and age group are all considered. The trial stage known as a mock-up makes it possible to see how the chosen length and shade will look in the mouth before any preparation, minimising the gap in expectations.

Not Skipping Gum Health

The margins of laminates usually finish very close to the gum line. If they are placed while the gum is inflamed, the margin can become exposed once the tissue heals and the gum level changes, spoiling the result.

Gum treatment is therefore completed before the aesthetic stage, bleeding is resolved and the tissue is allowed to settle. Afterwards, flossing and regular professional cleaning continue. Healthy gums are the invisible frame that keeps a laminate looking as intended for a long time.

Frequently Encountered Misconceptions

  • The belief that laminates can be applied to any tooth in any condition
  • The idea that brushing is no longer needed once restorations are placed
  • The assumption that matching the shade of a single laminate is simple
  • The belief that a clenching habit will not affect ceramic
  • The idea that the trial stage is an unnecessary step
  • Expecting a laminate to stop gum recession
  • The notion that whitening will also change the colour of ceramic

✦ SSS

Frequently Asked Questions 30

01

How much of the tooth is reduced for a veneer?

Only a thin layer is removed from the front surface, roughly the thickness of the veneer, which is far less than a crown requires. The back surface and most of the incisal edge are untouched. In suitable cases there are types that can be placed with no reduction at all.
02

Can a veneer be repaired if it chips?

Small chips at the edge can be repaired with composite, but that is a temporary solution: the match in colour and gloss diverges over time. Larger fractures require the veneer to be remade. To prevent chipping, a night guard is needed where there is clenching, and habits such as nail biting must stop.
03

Is there sensitivity after veneers?

Where reduction has been done, mild sensitivity for a few days is normal and settles. Where none was needed it is usually absent. Sensitivity that persists or increases is not normal: there may be an opening at the bonding margin or a high spot in the bite, and it needs checking.
04

How many veneers should be made — are the front teeth enough?

The decision follows how many teeth show when you smile, which varies from person to person and is measured against the smile line. Veneering only the four front teeth can leave a visible colour difference with those beside them. The plan is therefore built around the visible whole rather than individual teeth.
05

Can the tooth beneath a veneer decay?

The veneer itself does not decay, but the natural tooth beneath and around it can, and the risk lies particularly at the bonding margin. That area should be cleaned daily with floss and checked regularly. Acting early when a margin begins to leak postpones the need to remake the veneer.
06

Is orthodontic treatment possible after veneers?

It is possible but difficult: brackets do not bond to a veneer surface as well as to natural enamel, and there is a risk of damaging the veneer on removal. The correct order is therefore orthodontics first, veneers second. If you are considering correcting your alignment, say so at the outset.
07

What is a mock-up, and is it essential before veneers?

A mock-up is a trial of the planned result in your mouth in temporary material: you see it in the mirror and judge it while speaking and smiling. It is a reversible stage. It is not compulsory, but most cases where expectation and result diverge occur when no mock-up was made, which is why it is recommended.
08

How long do veneers last in the mouth?

Care, the bite and habits decide. In a patient who does not clench, keeps the margins clean and attends reviews, veneers serve for many years. The main things that shorten their life are uncontrolled clenching, biting hard objects and untreated gum disease.
09

Do veneers look too white?

The shade is chosen with you, taking into account skin tone, the whites of the eyes and facial features for a natural look. Extremely white teeth of identical length look artificial. Good work is work that does not announce itself, so slight variations in colour and form are left deliberately.
10

Is gum contouring needed for veneers?

It is needed where the gum levels are uneven; otherwise the veneer margins sit at different heights and the symmetry is lost. After contouring, time is allowed for the tissue to settle before impressions are taken. If that wait is skipped, the level changes during healing and the margin is later exposed.
11

Will my teeth be heavily reduced?

No. Only a very thin layer is removed from the front surface, roughly the thickness of the veneer itself, which is far less than a crown requires. In some cases veneers can be placed with no reduction at all, depending on the position and shape of the teeth.
12

Will the veneers look obvious?

Not when planned properly. Artificiality usually comes from overly white shades and perfect symmetry rather than the material itself.
13

Can veneers come off?

Properly bonded they form a strong chemical bond; loss usually follows biting hard objects, trauma or grinding. Keep a detached veneer — it can often be re-bonded.
14

Can I have whitening after veneers?

Porcelain is unaffected by bleaching agents, so whitening has to be completed beforehand. If veneers are placed first and the natural teeth are lightened afterwards, a visible mismatch appears between them and the only remedy is to remake the veneers.
15

How is the cost determined?

Cost depends on the number of teeth, material and any additional procedures. Prices are not published; a plan is explained after planning.
16

Can a laminate be made for a single tooth?

It can be; the most demanding part of a single-tooth case is matching the colour and translucency of the neighbouring teeth. The surface texture, edge translucency and shade of the natural tooth are recorded in detail. In some cases a small adjustment to the adjacent tooth may be suggested for a more harmonious result.
17

Can a laminate be repaired if it fractures?

Small edge chips can sometimes be repaired temporarily with composite, but when ceramic fractures, replacing the laminate is usually preferred. The cause of the fracture is investigated; if a contact problem in the bite or a clenching habit is found, that is corrected first. Otherwise the same problem can recur.
18

Can laminates be placed while there is gum disease?

Gum treatment needs to be completed before aesthetic work. Bleeding from inflamed tissue interferes with taking impressions and bonding, and the gum level that changes after healing can expose the margin. Once treatment is complete, the aesthetic stage can proceed confidently.
19

Are follow-up appointments needed after laminates?

Yes. At the first review the fit of the margins, the response of the gum and the contacts in the bite are checked. Afterwards, reviews at least once a year allow both the ceramic surface and the condition of the tooth beneath it to be assessed. Regular professional cleaning is also planned at these appointments.
20

I take blood thinners. What should I do about bleeding in my mouth?

Use the same firm pressure technique, but expect bleeding to take longer to settle on these medicines. Never stop or change the dose on your own; that carries serious risks and is only done with the knowledge of the doctor who prescribed it. Call the clinic if bleeding continues despite pressure, as local measures usually control it. Always bring a list of your medicines.
21

I bit my lip and tongue when I fell and it is bleeding a lot. What should I do?

Clean the area gently with clean water, then apply steady pressure with clean gauze for about ten minutes; a cold pack on the outside limits swelling. Mouth wounds look dramatic because the tissue has a rich blood supply. If bleeding lasts beyond fifteen minutes, the cut is deep or gaping, or debris such as grit or glass is inside, stitches may be needed, so seek care at once.
22

My jaw stayed open while yawning and I cannot close it. What should I do?

A jaw stuck open can happen when the joint head slips forward out of its socket, and it needs urgent care. Do not force it shut or let someone yank it, as that worsens muscle spasm and tissue damage. Support the jaw with your hand or a soft bandage, talk as little as possible and come in. Repeated episodes should be investigated separately.
23

Will putting an aspirin on the aching tooth help?

No. Do not place a painkiller tablet on the gum or tooth. It does not relieve the pain and can cause a chemical burn, leaving a white, painful ulcer where it touched. Painkillers work when swallowed. The choice and dose should suit your own health, so ask your doctor if you have stomach problems, allergies, blood thinners or a pregnancy.
24

Should I put something hot or cold on my swollen face?

Avoid external heat when the swelling comes from a dental infection, because heat increases blood flow and can help it spread. After trauma or an extraction, intermittent cold packs during the first day reduce swelling and discomfort. Never put ice straight on the skin; wrap it in a cloth. Heat is mainly useful for muscular pain and when your dentist advises it.
25

If I get antibiotics from the pharmacy, will my dental abscess clear up?

Antibiotics alone rarely settle the problem for good, because the symptoms often return once the course ends if the source tooth is untreated. Taking them without an examination also masks the picture, contributes to resistance and risks needless side effects. The right order is examination, imaging when required, then the definitive step: drainage, root canal treatment or extraction.
26

What can I do at home to get through the night until I can reach the clinic?

Sleeping with your head raised on extra pillows eases the throbbing that worsens when lying flat. Do not bite on the painful side, and avoid very hot, very cold and sugary food. Warm salt-water rinses can soothe the area, and a painkiller you know suits you may be taken at the recommended dose. These are temporary measures, so call us if swelling, fever or worsening pain appears.
27

I keep hearing about on-call dentists. How does that system actually work?

On-call rotation means different centres stay open on different nights, so the patient must first find out whose turn it is. That search costs time during a painful night. On-call visits usually focus on stopping pain and bleeding, leaving definitive treatment to a later appointment.
28

What is the difference between going to an on-call centre and a clinic that is always open?

The main difference is predictability. With a rotation you must find out which centre is open tonight; with a permanently open clinic the address and hours never change. Our clinic works around the clock, so nights, weekends and holidays are handled by the same team with the same equipment.
29

My tooth started hurting badly on Saturday afternoon. Do I have to wait until Monday?

You do not have to wait; weekend visits are possible. Suppressing pain with tablets for two days is rarely wise, because the underlying infection does not stop, it only becomes less noticeable and may spread. A weekend examination usually identifies the cause and allows immediate relief.
30

A swelling like an abscess appeared on the second day of the public holiday. Can I find anywhere open?

Yes, you can be seen on public holidays; our clinic stays open. Swelling is a poor reason to wait, since an abscess does not resolve on its own and can spread across the face. Holiday visits focus on assessing the swelling, providing drainage if needed and starting suitable medication.

From Our Blog

✦ Our Brands
Straumann
Nobel Biocare
Astra Tech
Medentika
Bredent SKY
Straumann
Nobel Biocare
Astra Tech
Medentika
Bredent SKY
✦ Contact
Get in touch

Antalya Muratpaşa our central clinic

Sair Adem Dede St. No:31, 07030 Muratpasa / Antalya, Türkiye

Open in Google Maps