




























Patient Reviews 4.9/5 10.000+ Happy Patients 37 Countries

Clear Aligner Treatment in Antalya

✦ Tedaviler

Clear Aligner Treatment in Antalya

Clear aligner orthodontics in Muratpasa, Antalya — straightening teeth without brackets, removable and discreet.

✦ Our Patients

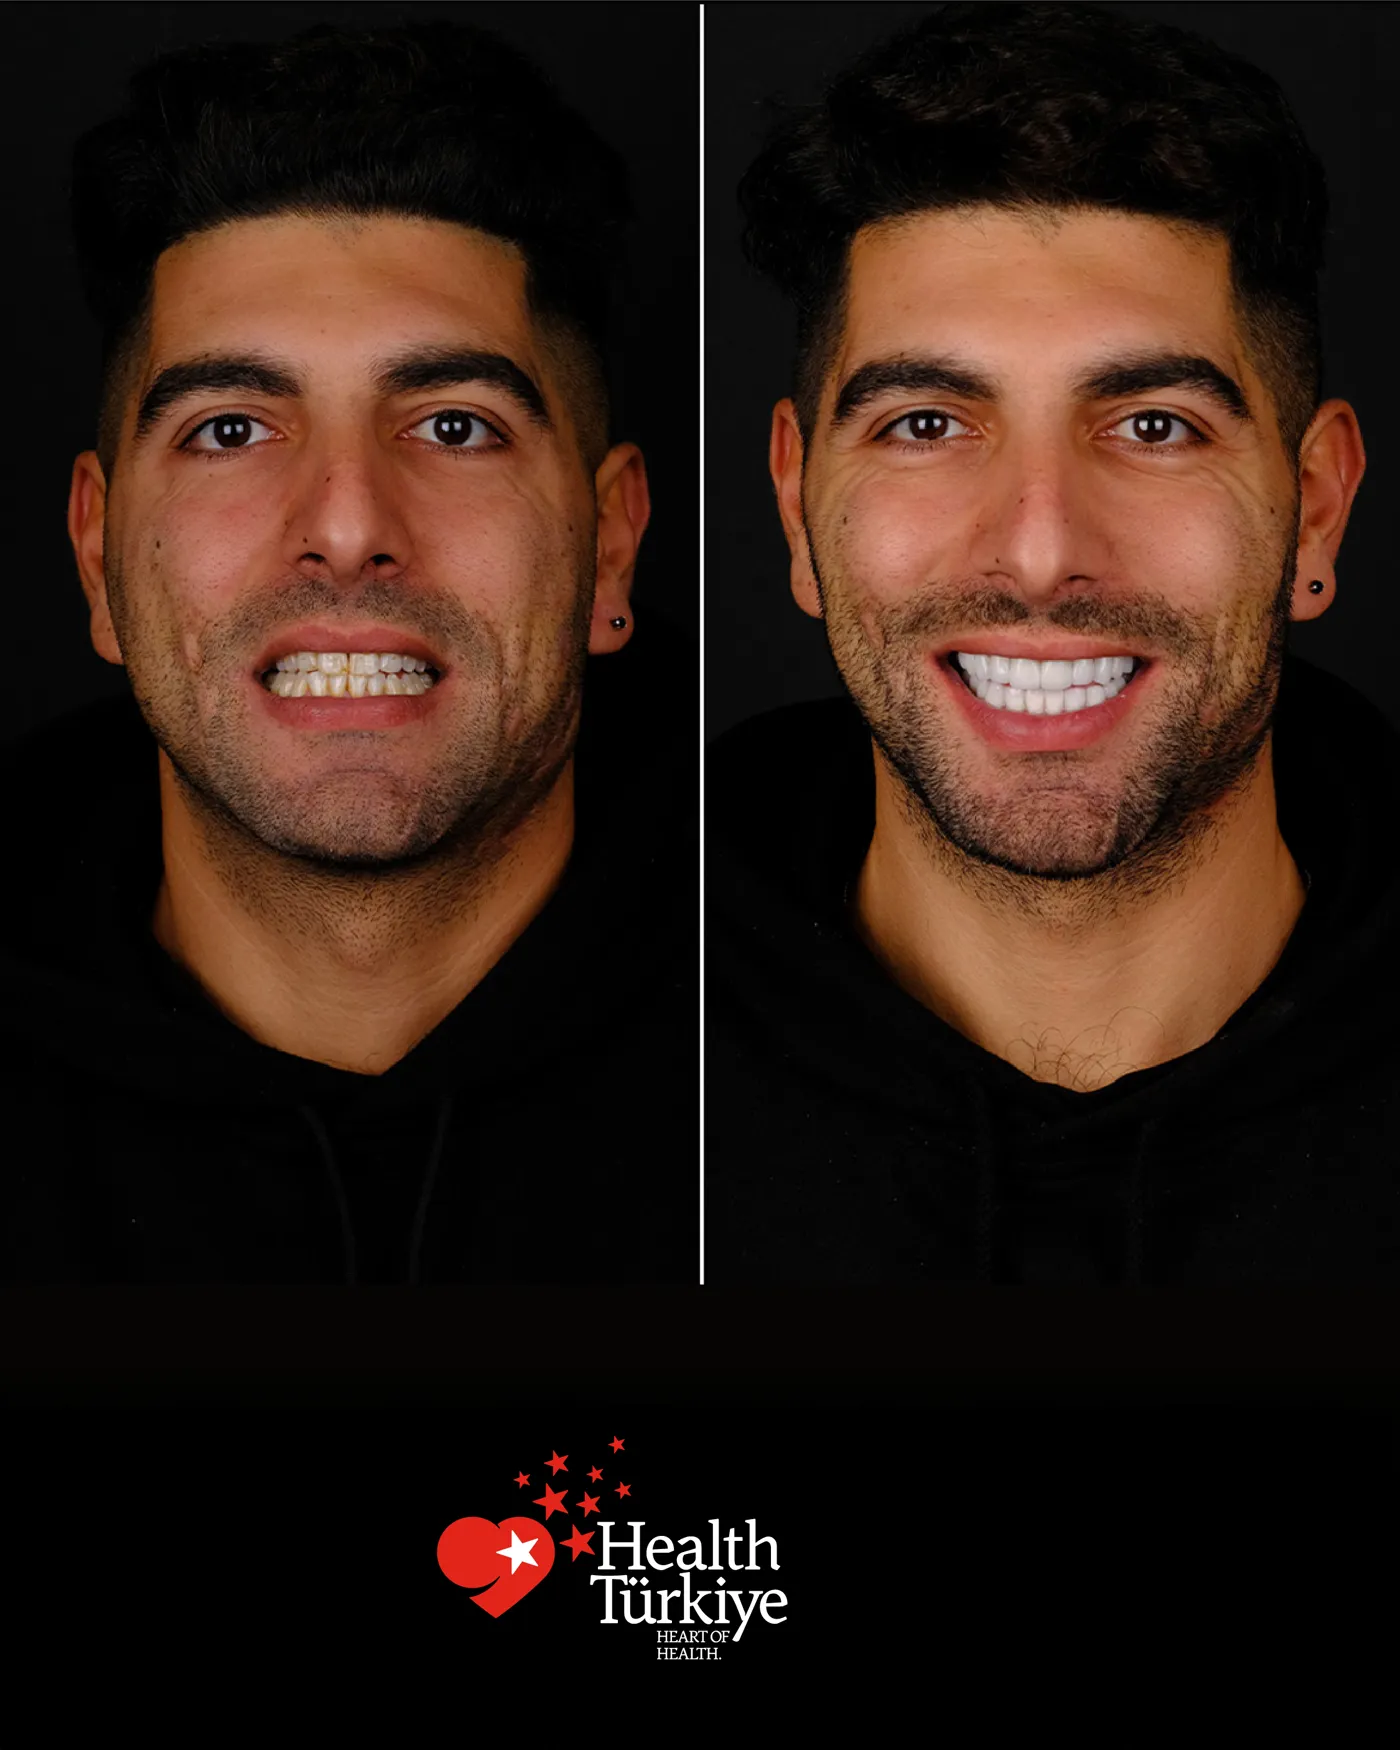
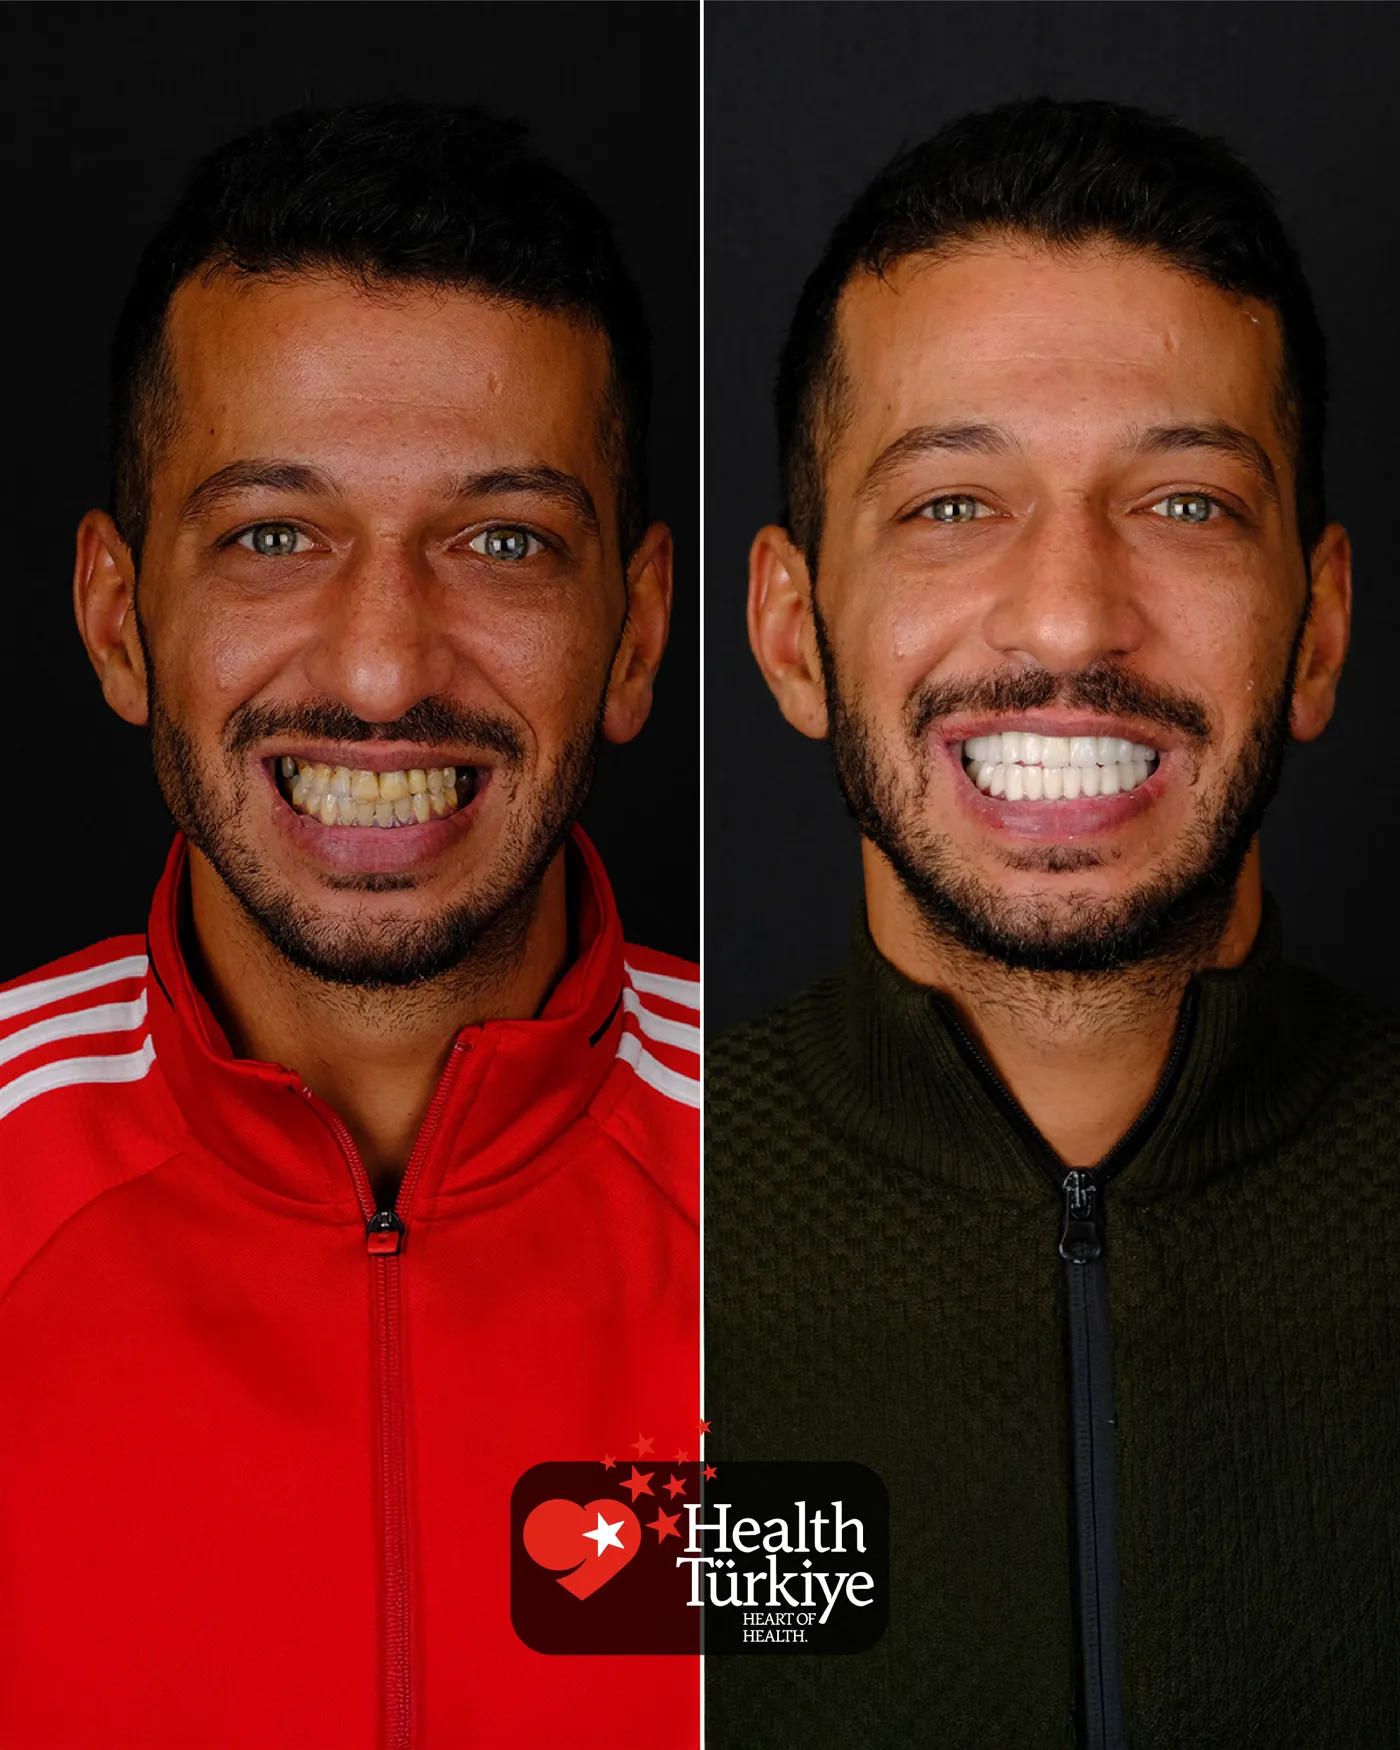
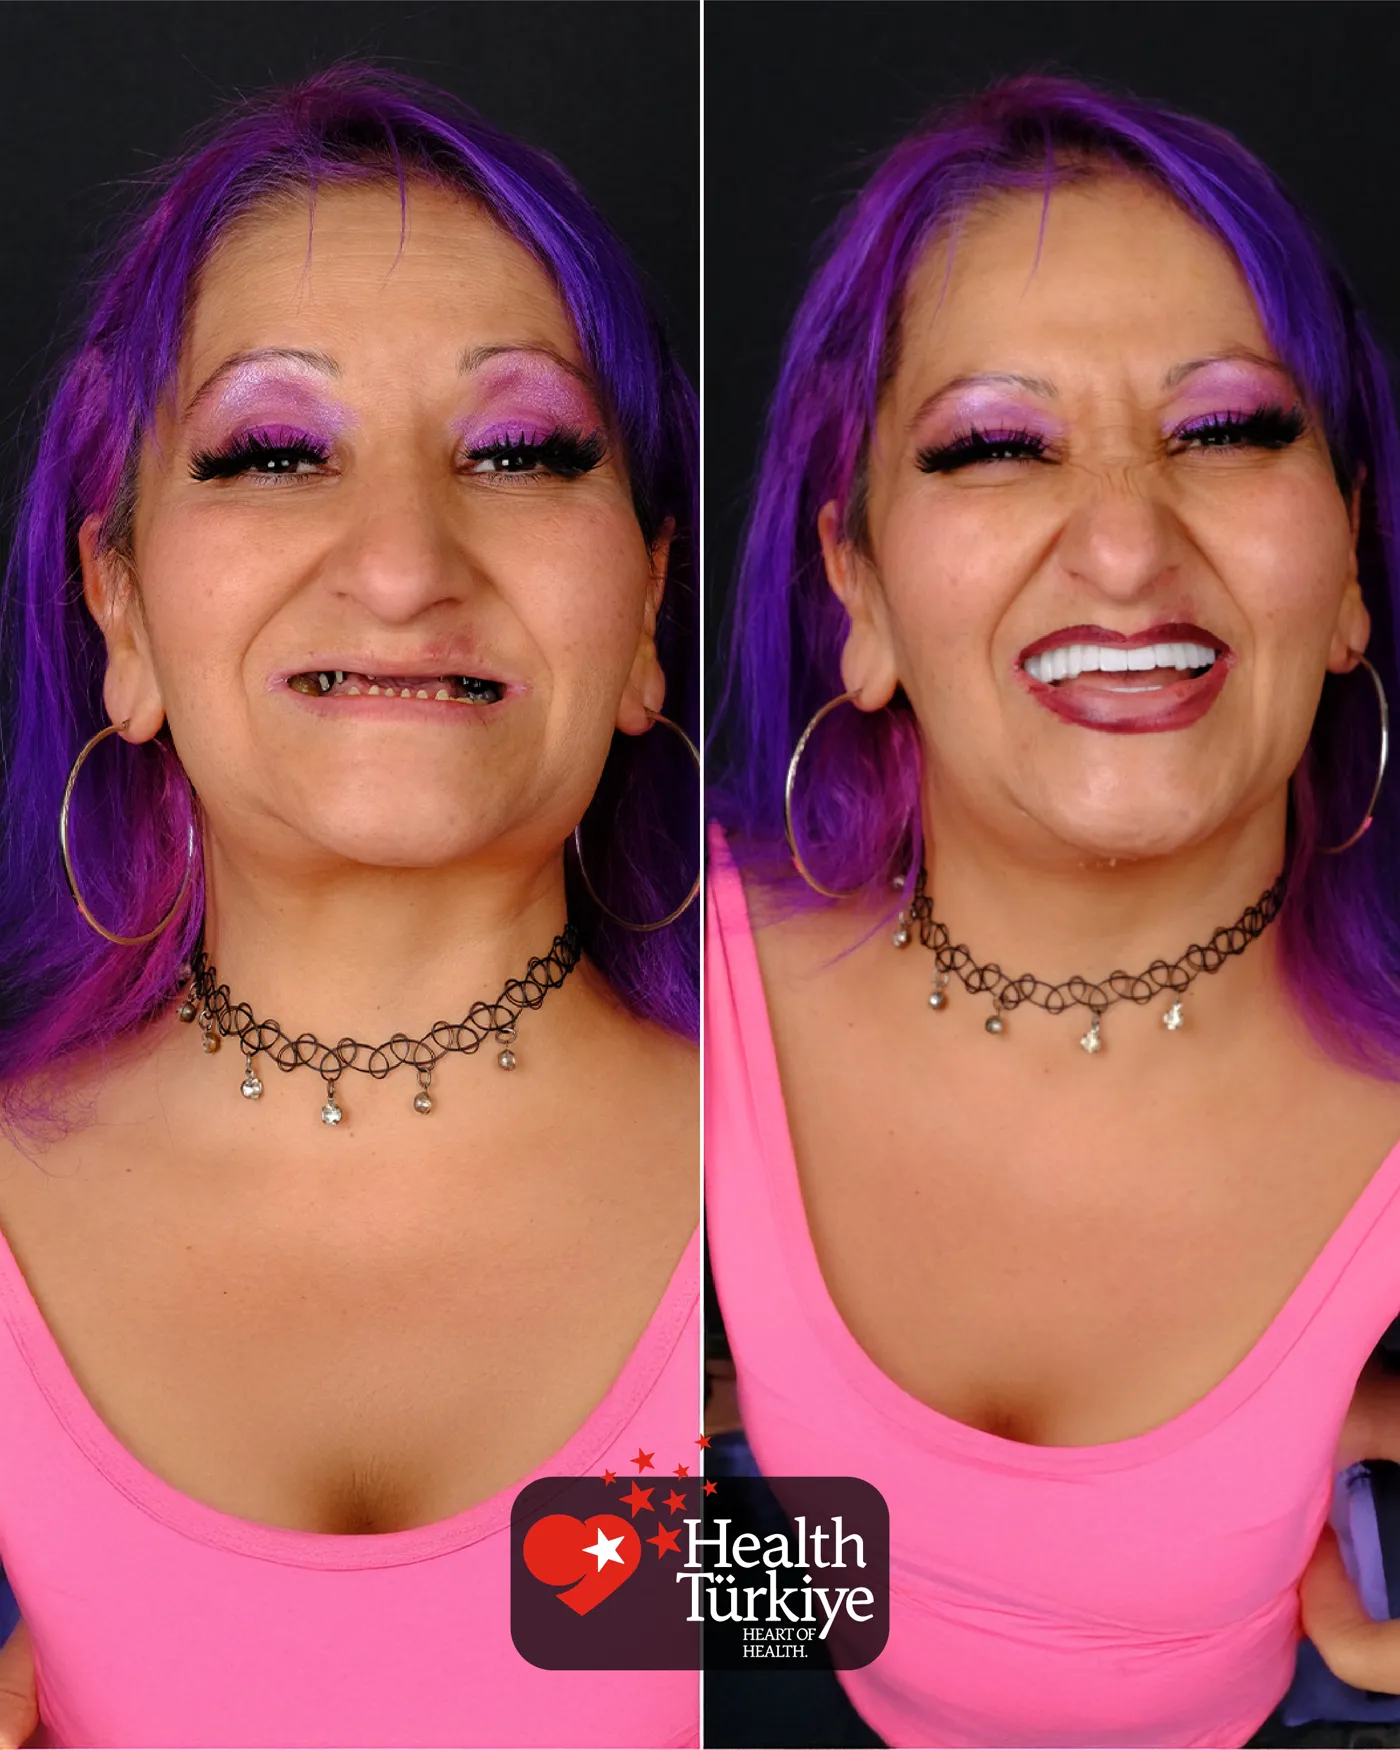
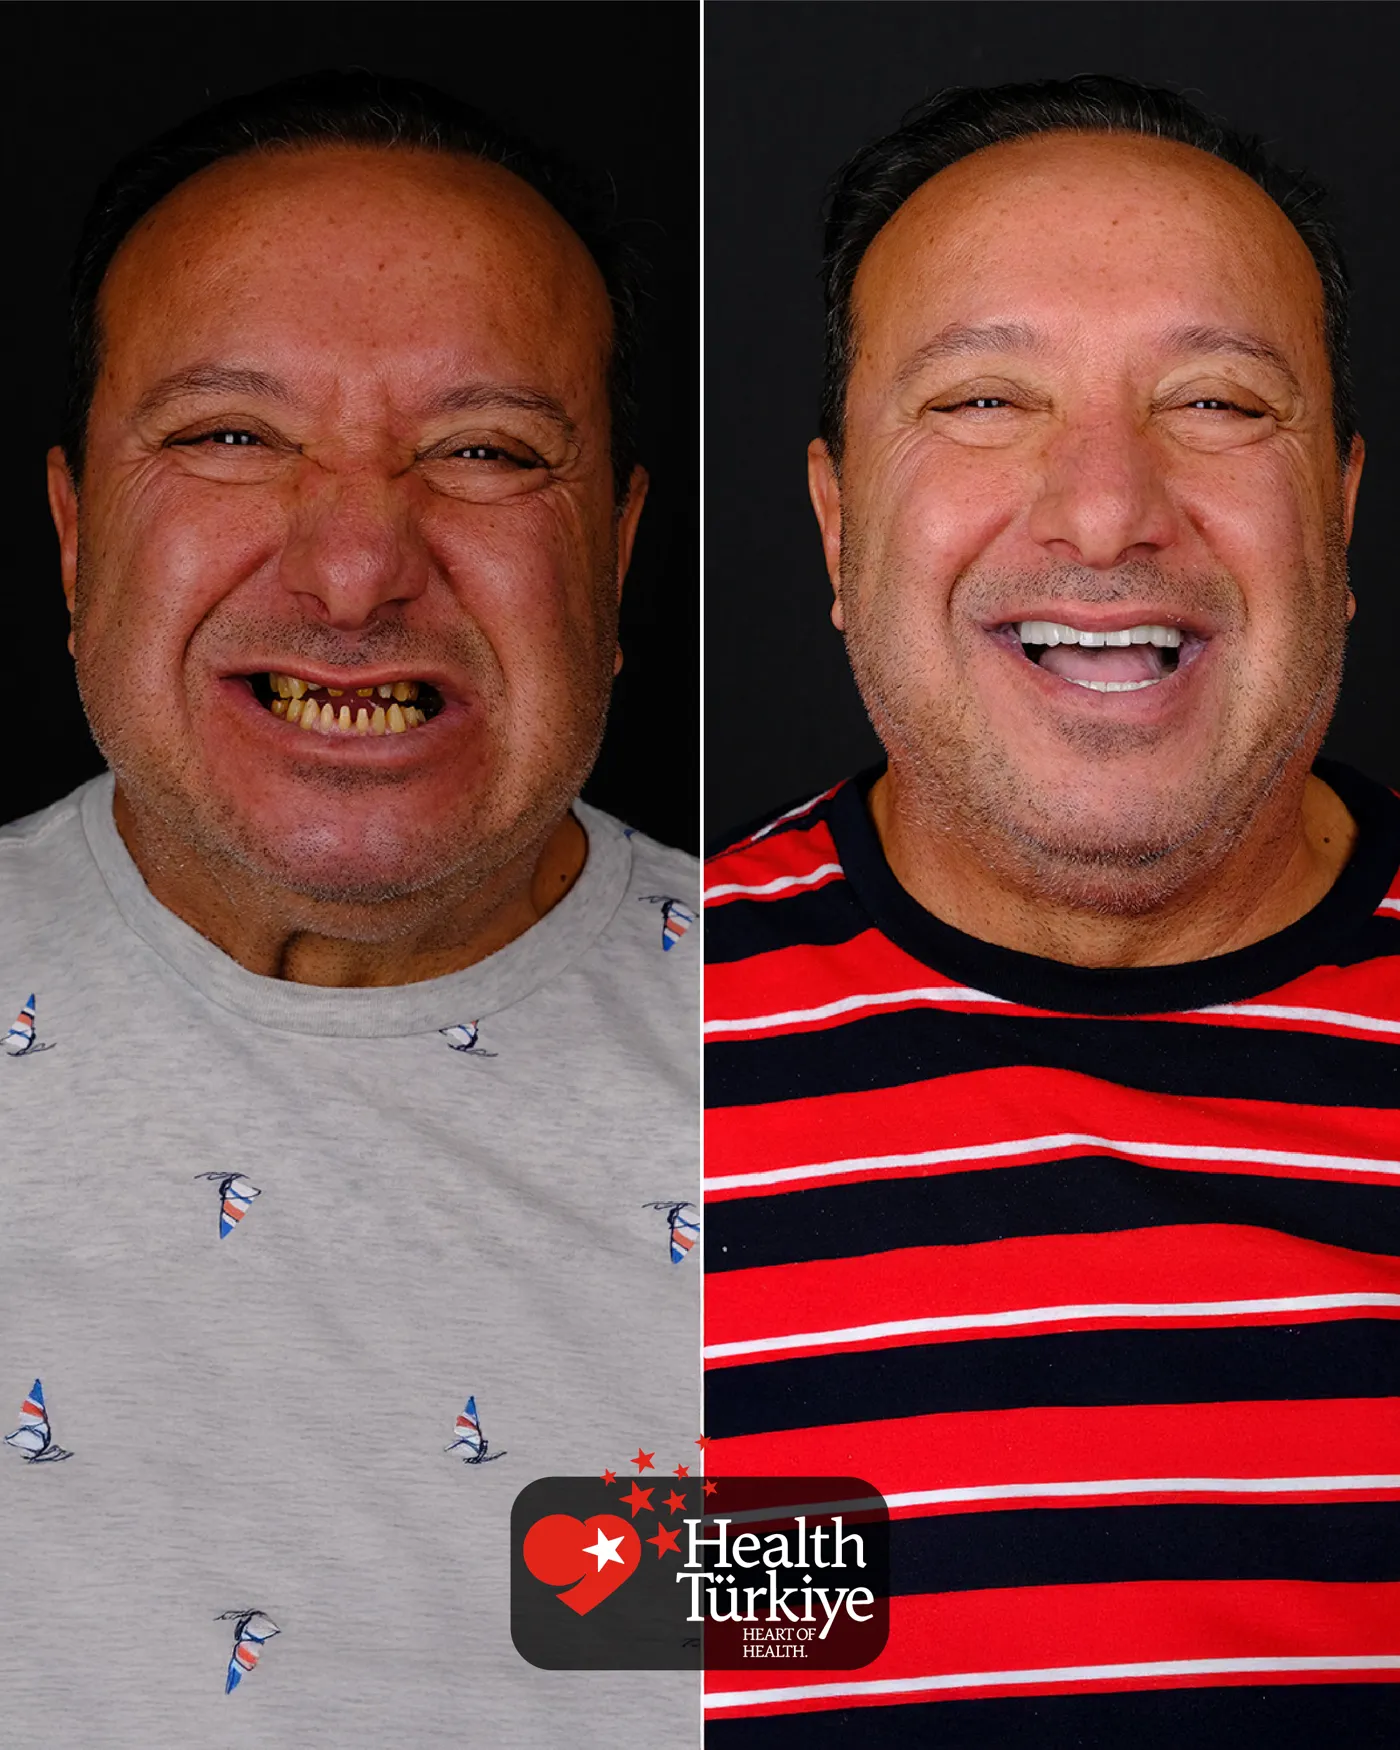
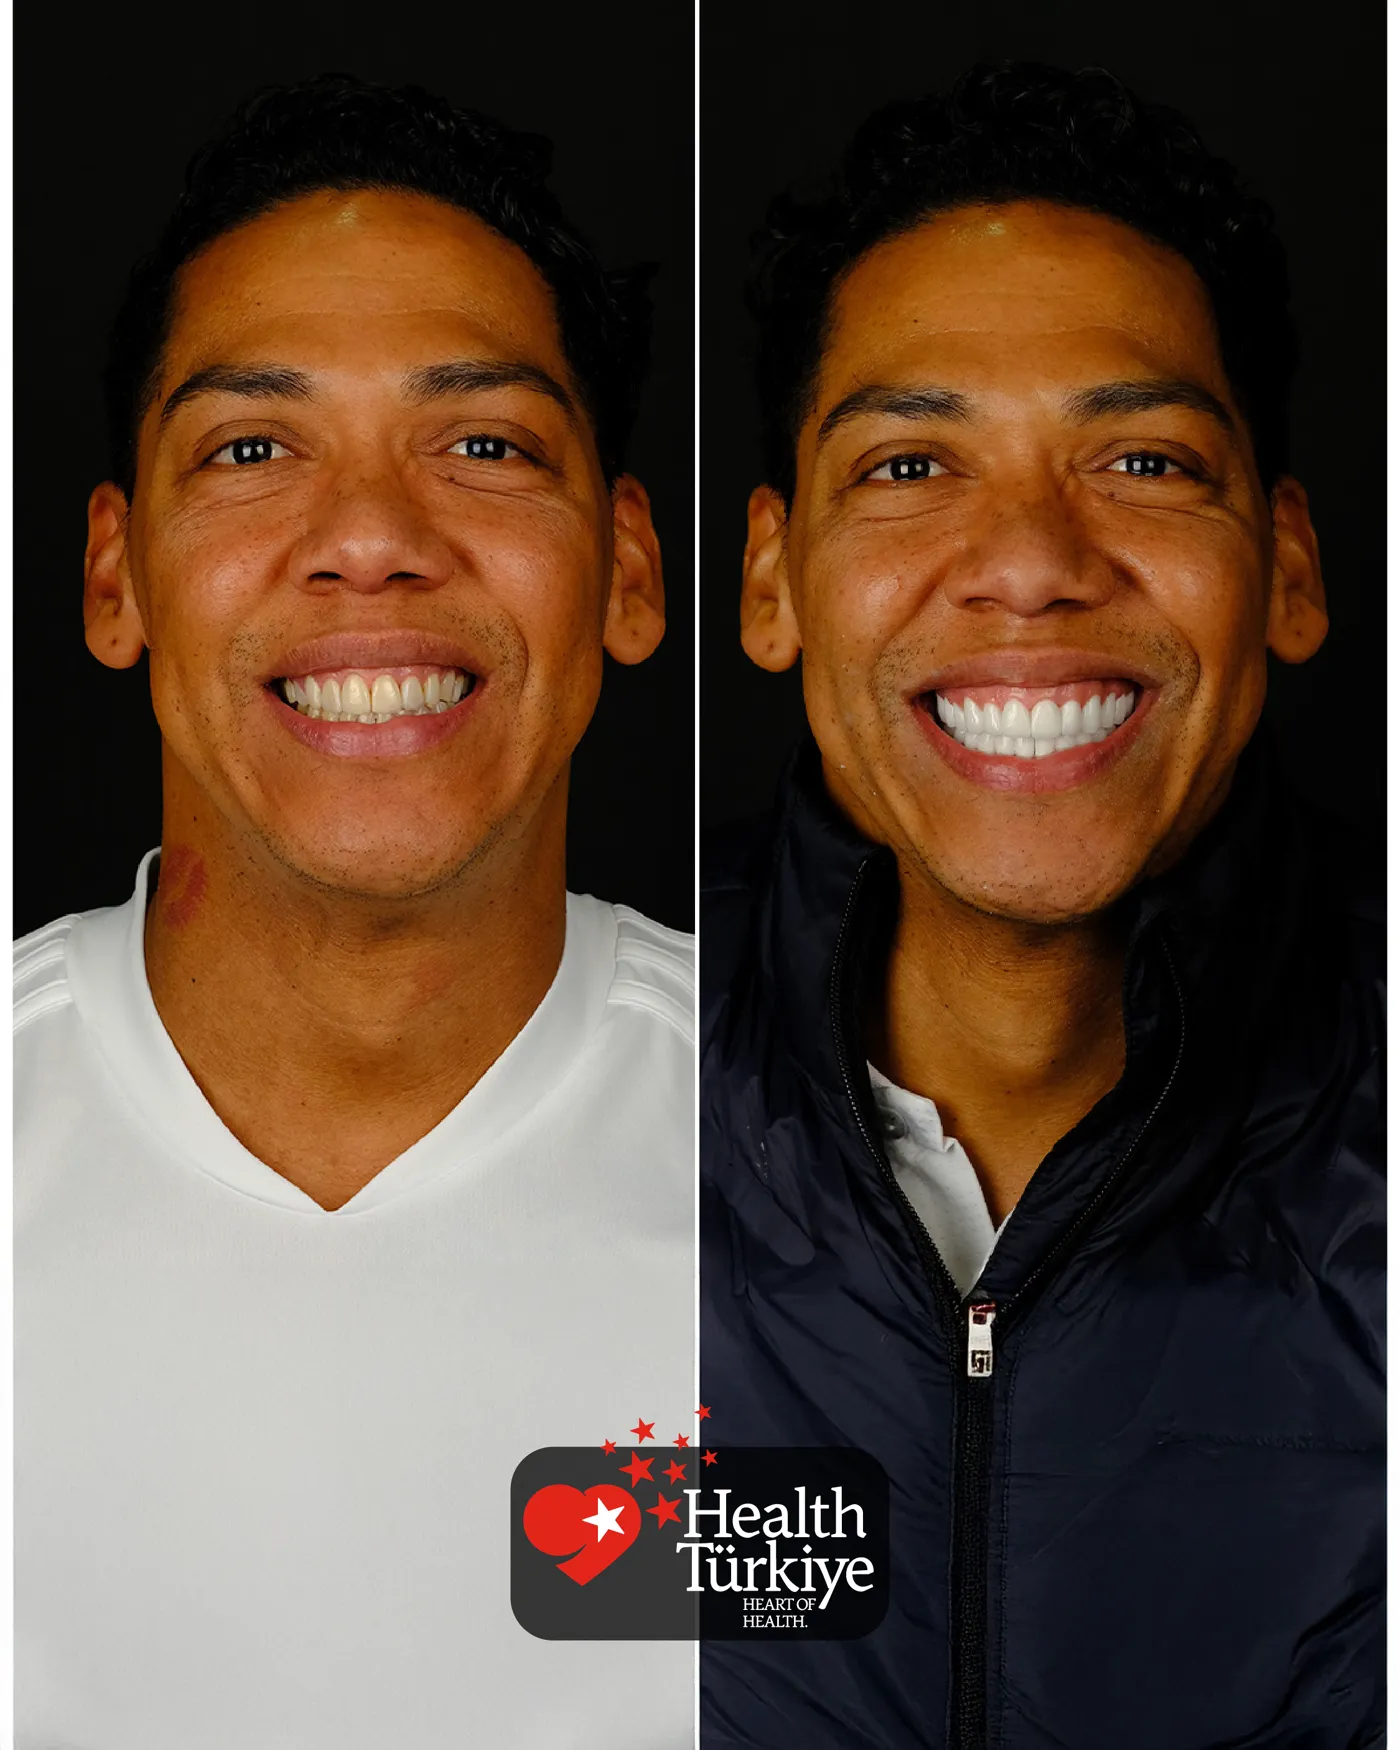
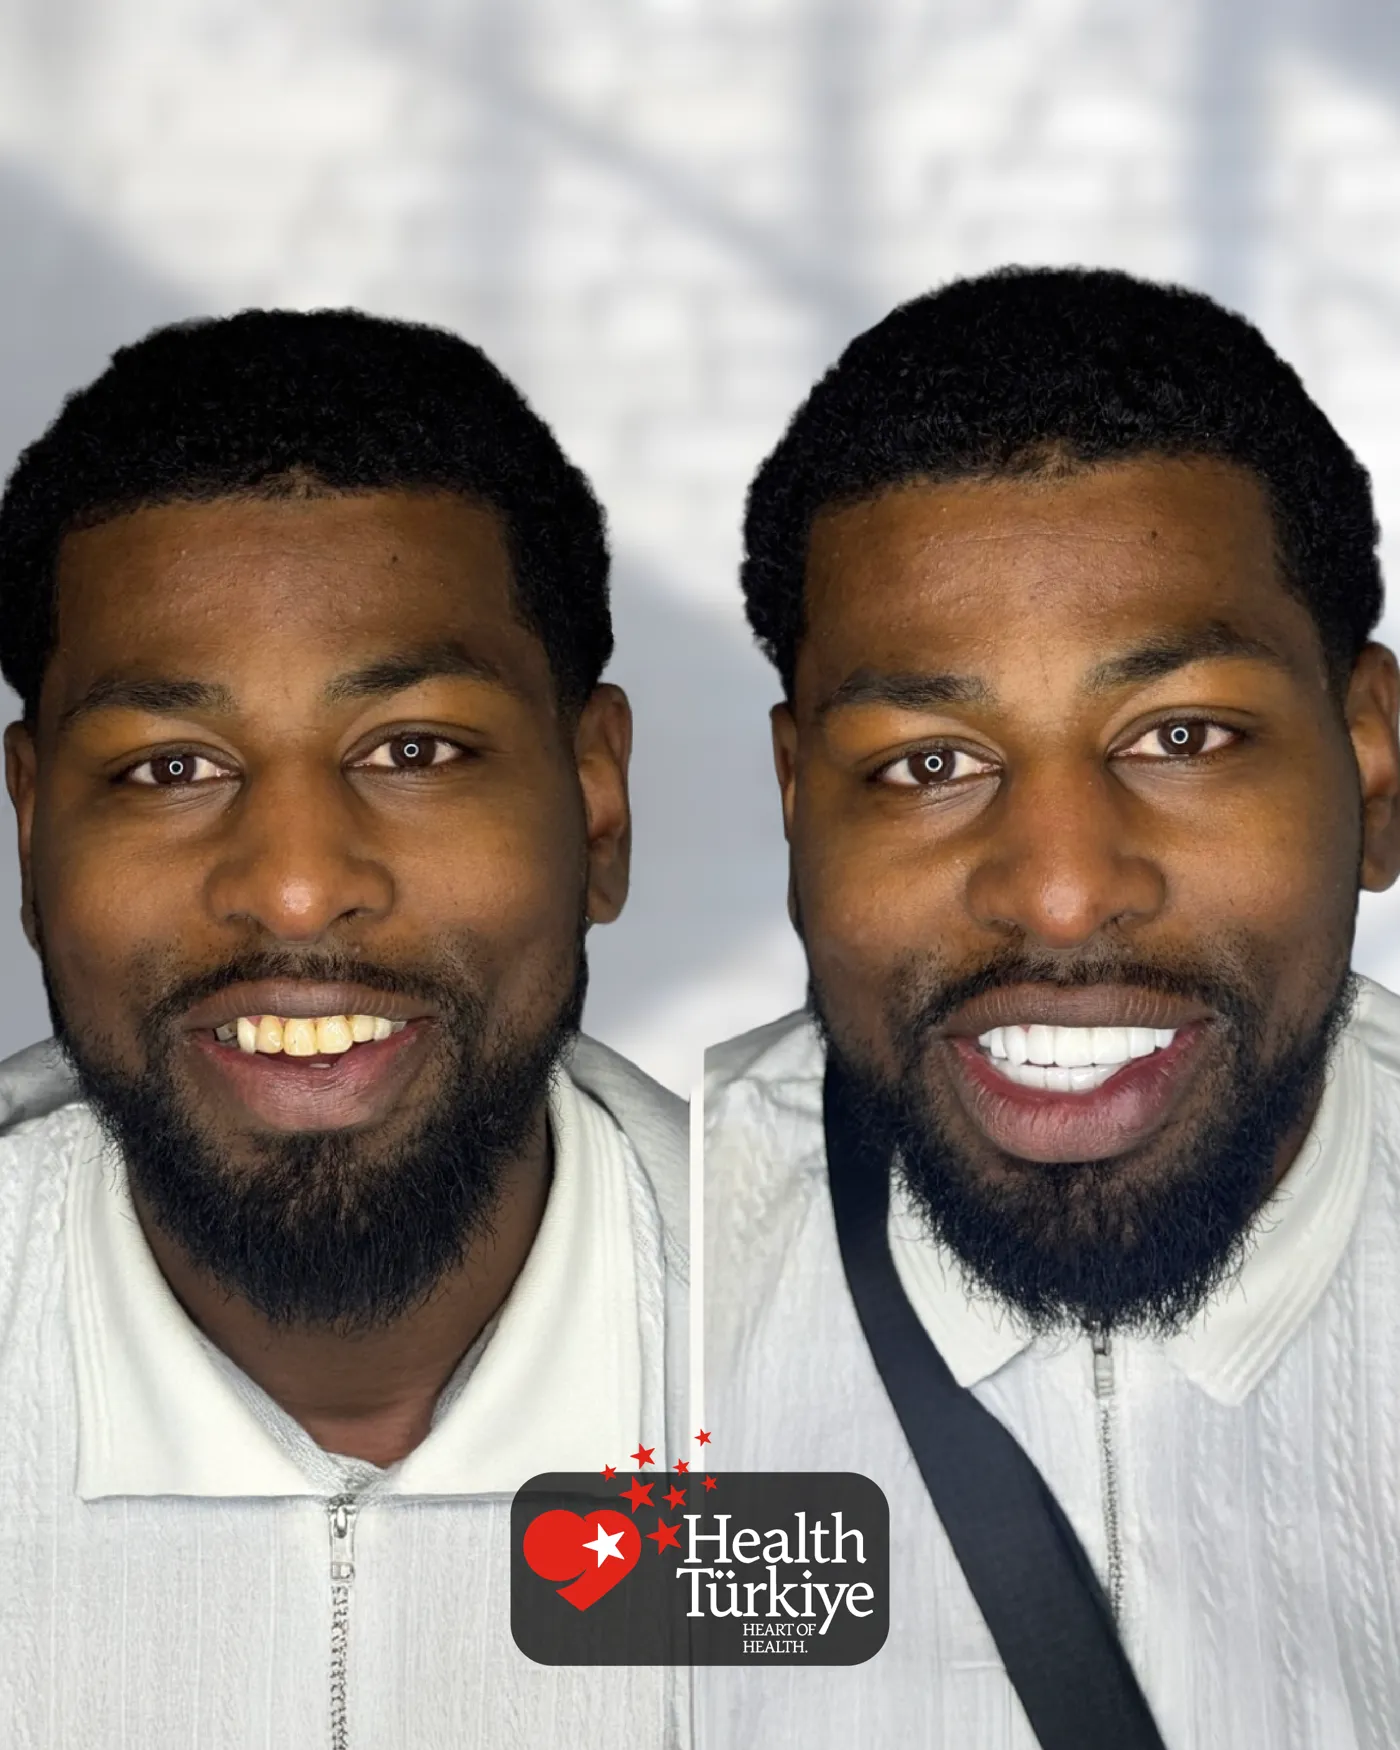
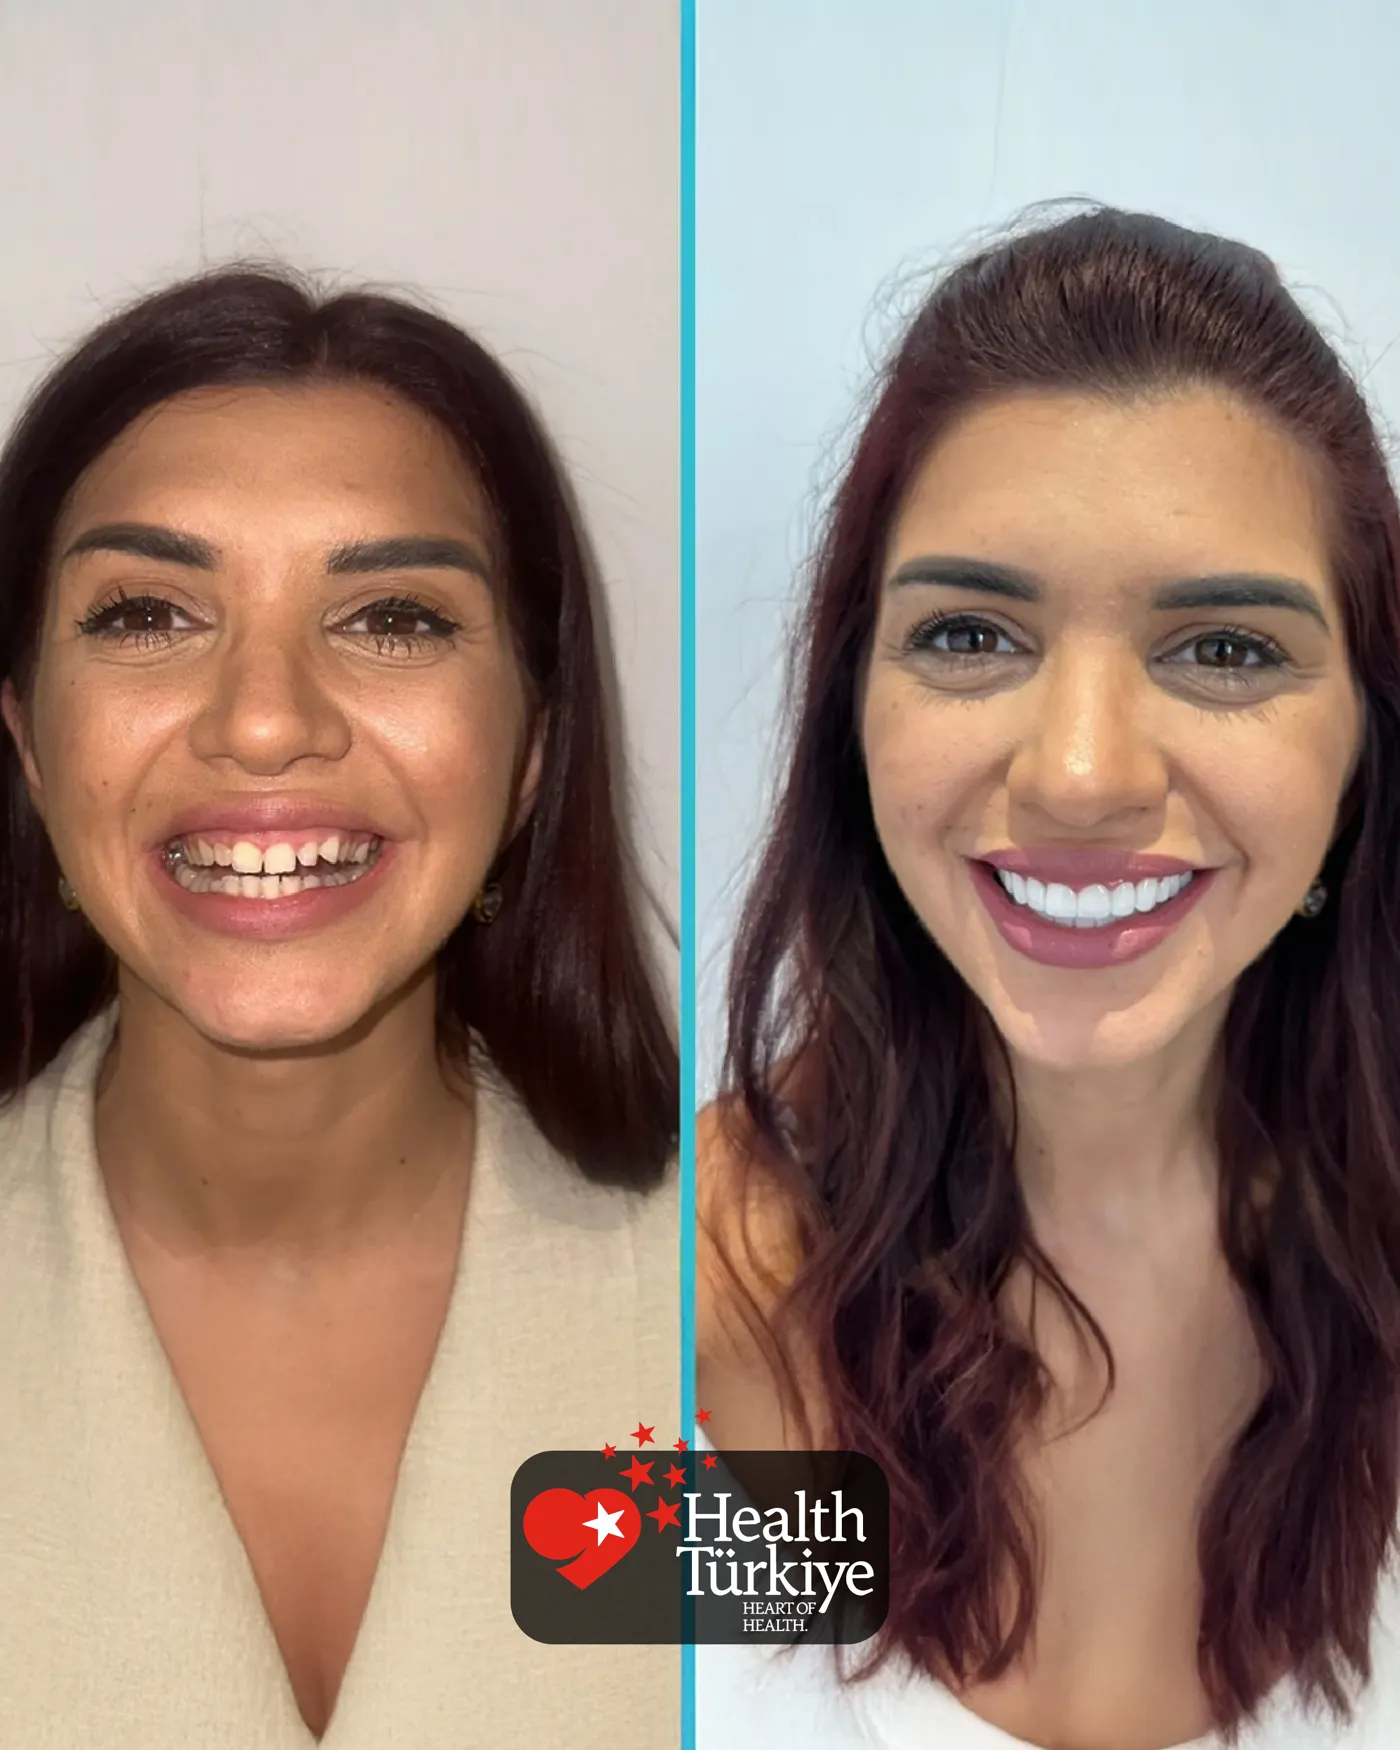
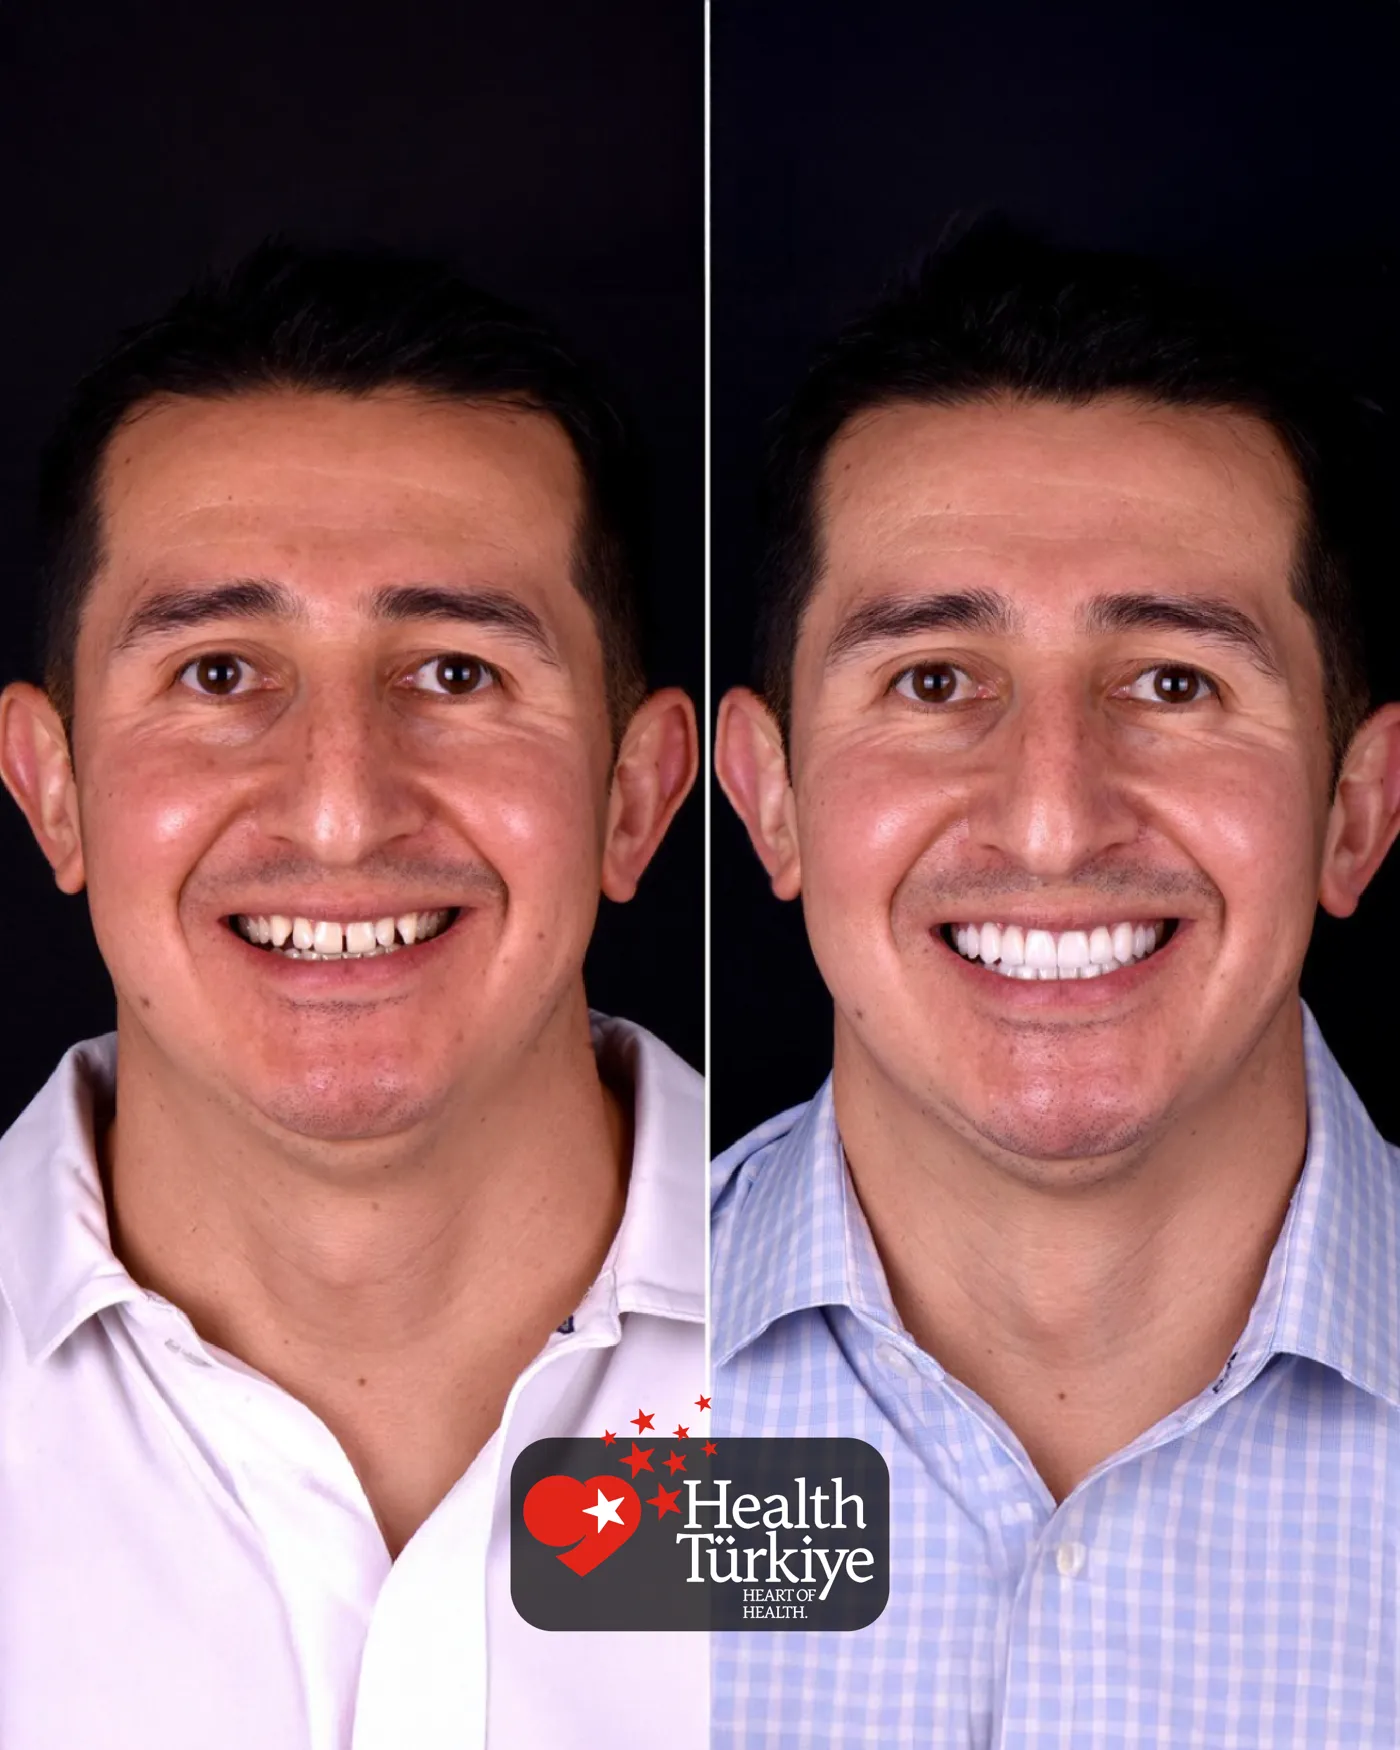
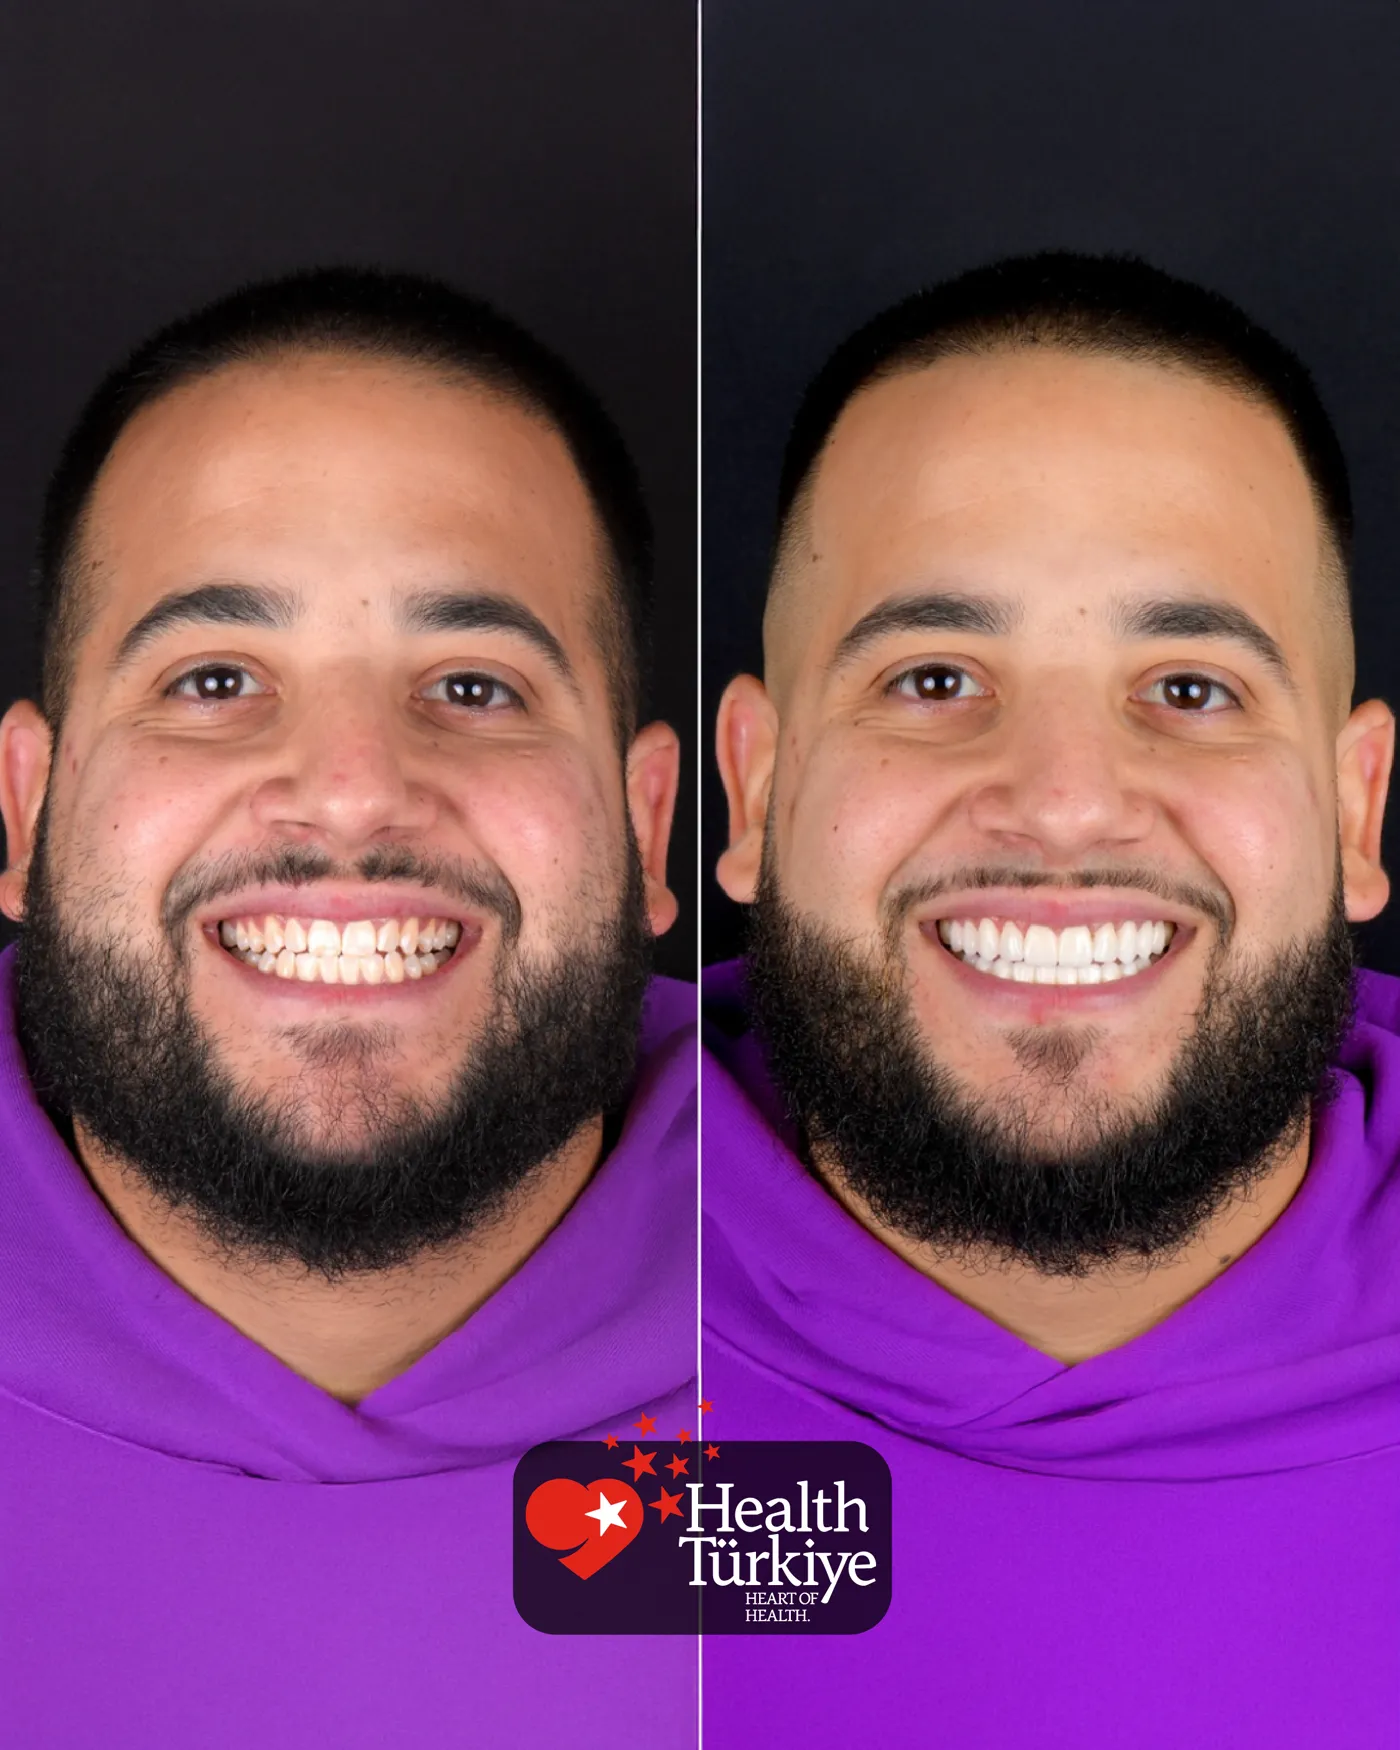
Photos from treatments performed at our clinic

Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
✦ Our Clinic
kliniğimiz
kliniğimiz
kliniğimiz
kliniğimiz

Clear aligners move teeth without brackets or wires, using a series of custom-made transparent trays, each advancing the teeth one step towards the planned position.

The principle is the same as conventional orthodontics — controlled continuous force remodels the surrounding bone — but the force comes from the tray's geometry rather than a wire.

The main advantage is that they are removable for eating and brushing, which makes oral hygiene far easier than with fixed appliances.

How Clear Aligner Treatment Works

Treatment begins with digital planning and proceeds through a calculated series of steps.

Digital scanning and planning

An intraoral scanner creates a 3D model without impression material. Software then plans the path each tooth will follow, determining the number of trays and the treatment duration, with a simulation of the result.

Attachments: small but critical

Some movements cannot be achieved by the tray alone, so small tooth-coloured composite attachments are bonded to give the aligner grip. They are removed at the end; if one comes off it must be re-bonded promptly.

Wearing the aligners

Each tray is worn for one to two weeks in numbered sequence — skipping disrupts the planned movement. They must be worn 20–22 hours a day, removed only for eating, drinking anything but water, and brushing.

Reviews and completion

Regular reviews check progress against the plan, with additional trays if needed. At the end, attachments are removed and retention begins — as important as the treatment itself.

Who Are Clear Aligners Suitable For?

Aligners are effective in many cases but cannot solve every orthodontic problem; an honest assessment prevents mid-treatment disappointment.

Cases that respond well

  • Mild to moderate crowding
  • Spacing between teeth
  • Mild bite discrepancies
  • Relapse after previous orthodontic treatment
  • Adults who decline visible braces for aesthetic reasons

When fixed braces are more appropriate

Severe crowding, skeletal discrepancies, extraction cases and large tooth movements are more predictable with fixed braces. Aligners also depend on patient compliance, so fixed appliances are safer for those who would not wear them consistently.

Prerequisites

Decay must be treated and gum health established first; force applied over inflamed gums can accelerate bone loss. Scaling and any periodontal treatment come before starting.

Clear Aligners Versus Fixed Braces

Both use the same biological mechanism; the difference is in delivery, and the choice depends on the case and on compliance.

Visibility and comfort

Aligners are not noticeable from a distance and avoid the cheek irritation and poking wires of brackets. Each new tray brings a few days of pressure, which is normal and shows the teeth are moving.

Hygiene and eating

This is the clearest advantage: brushing and flossing around brackets is difficult, raising the risk of decay and permanent white spot lesions. With aligners the teeth are brushed normally and there are no dietary restrictions.

Duration and predictability

In suitable cases durations are similar, but aligner success depends directly on wear time. Fixed braces remove that risk and give more predictable movement in complex cases.

Retention After Treatment

This is the most neglected — and most costly to skip — stage of orthodontic treatment.

Why do teeth relapse?

When teeth move, the surrounding bone and periodontal fibres remodel, but this takes months and the fibres retain memory that pulls teeth back. Without retention, noticeable relapse occurs within months.

Retention options

A fixed retainer is a thin wire bonded behind the front teeth — invisible and independent of compliance, though it needs special floss. A removable retainer is a clear tray usually worn at night. Retention periods vary and can be very long.

Attachments, Enamel Reduction and Auxiliary Procedures

In most cases clear aligner treatment is carried out not with the trays alone but with small auxiliary procedures that guide the movement.

What Attachments Do

An attachment is a small composite bump bonded to the tooth surface so the aligner can grip it. On a smooth tooth surface the tray can slip; the attachment lets it transfer force in the intended direction from the intended point. They are used particularly for demanding movements such as rotation, uprighting and moving a tooth about its own axis.

The position and shape of the attachments are determined digitally during planning and placed in a single visit. Because they closely match tooth colour they are not obvious from a distance. At the end of treatment they are removed and the surface polished; this does not create permanent loss of tooth structure.

What Interproximal Reduction (IPR) Is

Interproximal reduction means smoothing a very thin layer of enamel from the sides of the teeth to gain space. In cases with limited crowding it makes room without extractions. It is carried out with strips or fine burs, and how much space is gained between which teeth is decided at the planning stage.

When performed within the limits of enamel thickness and in a measured way, it does not compromise dental health; the surface is then polished and fluoride applied where indicated. Cleaning these areas matters, because the surface contour has changed. Whether it is needed depends on the amount of crowding and on tooth dimensions.

Other Auxiliaries Used During Treatment

  • Elastics attached to the trays to help correct the jaw relationship
  • Small buttons bonded to the tooth surface so elastics can be anchored
  • Integrated features such as hooks and cut-outs on the tray itself
  • Chewies used to help the tray seat fully
  • Files used to smooth a tray edge that causes irritation
  • Removal aids that make taking the trays out easier
  • A mid-treatment rescan and the planning of an additional set of trays

Wear Discipline, Hygiene and Follow-Up With Aligners

The single most important variable determining progress with clear aligners is how many hours a day the trays are actually worn.

Why Daily Wear Time Is Decisive

Each tray is designed to move the teeth to the next planned position, and that movement requires continuous, regular force. If the tray is out of the mouth for much of the day, the next tray is started before the movement is complete, which means poor seating and a delayed treatment.

The trays are therefore removed only for eating and brushing, and removal is also advised for drinks other than water. Keeping wear time consistent allows tray changes to proceed as planned and makes the overall duration predictable.

Cleaning the Trays and Oral Hygiene

Because the trays envelop the teeth, food debris and sugary drinks remain in prolonged contact with the tooth surface. Brushing before putting the tray back in, or at least rinsing thoroughly with water when that is not possible, is therefore advised. Otherwise the risk of decay and gum inflammation under the tray increases.

The trays themselves are cleaned with lukewarm water and a soft brush; hot water distorts them, and coloured or scented cleaners can leave marks. Whenever they are out of the mouth they should go into their case. Wrapping them in a napkin is the commonest reason trays are lost.

What Review Appointments Check

  • Whether the tray seats fully against the tooth edges
  • Whether attachments are still in place, and replacing any that have come off
  • How far the planned movement has been achieved, and a rescan if needed
  • Gum health, bleeding and plaque accumulation
  • The cleanliness and surface condition of areas where enamel was reduced
  • Wear compliance and button condition where elastics are used
  • Handing over the next set of trays and updating the change schedule

✦ SSS

Frequently Asked Questions 30

01

How long does aligner treatment take?

It depends on complexity: simple corrections may take a few months, comprehensive cases over a year. The duration is calculated at planning.
02

Will aligners affect my speech?

A slight lisp is possible in the first days while the tongue adapts to the thickness of the aligner. It usually resolves completely within a few days, and reading aloud for a short while each day speeds that up. It returns briefly with each new tray at first, then stops happening.
03

Can I eat with the aligners in?

No. Remove them for eating and for drinking anything other than water; hot drinks deform them and coloured drinks stain them.
04

I lost an aligner — what should I do?

Revert to the previous aligner and contact us promptly. Time without an aligner allows the teeth to drift back. Never wear a cracked aligner.
05

Are aligners painful?

What people describe is pressure rather than pain. Each new tray brings mild tenderness for the first couple of days, which is the sign that the teeth are actually moving. A simple painkiller is enough if you need one, and the sensation settles as the tray is worn.
06

Will my teeth relapse afterwards?

They will move back if retention is not used. This is why wearing a retainer after treatment is not an optional extra but an integral part of it — the bone and fibres around the teeth need time to reorganise around the new positions. How long it is needed depends on the case and is explained to you.
07

How is the cost determined?

Cost depends on complexity, the number of trays and the duration. Prices are not published; a plan is explained after digital planning.
08

Are attachments noticeable from outside?

Attachments are made of tooth-coloured composite and are small; at conversational distance they generally go unnoticed. Seen close up they may be visible as a slight raised area on the tooth. They are removed at the end of treatment and the surface is polished.
09

Does interproximal reduction harm the tooth?

When carried out within the limits of enamel thickness and to the planned amount, it does not compromise dental health; the surface is then polished and fluoride applied where indicated. Cleaning the reduced contacts regularly with floss is important. Whether it is needed is decided by assessing the crowding and tooth dimensions.
10

Do the trays discolour, and how are they cleaned?

Discolouration can build up if coloured drinks are consumed while the trays are in, which is why removing them for anything other than water is advised. Cleaning is done with lukewarm water and a soft brush, as hot water distorts the tray. Abrasive toothpaste scratches the surface and dulls it.
11

Can I skip a tray or move on early?

Because each tray is designed to complete a specific movement, skipping one or changing early leads to poor seating and movement that does not follow the plan. Rather than shortening treatment, this may require a rescan and additional trays. Follow the change interval only as instructed by your clinician.
12

My dentist said the tooth could be root treated or extracted. How should I decide?

The general aim is to keep a tooth that can be kept, since your own tooth best preserves the bone and the alignment of neighbouring teeth. The decision looks at how much sound structure remains, the state of the root and surrounding bone, any cracks, and whether a solid restoration can be built. If the tooth is badly broken down or the root is cracked, extraction with a replacement plan may make more sense.
13

A root treated tooth has no nerve left. Can it still decay?

Yes, it can. Root canal treatment removes the nerve and blood vessels inside the tooth, but the outer surface and the surrounding gum stay in the same bacterial environment. Because there is no nerve, decay progresses without warning pain and is often noticed only when a filling breaks or on a check-up X-ray. Daily cleaning and regular check-ups matter even more for these teeth.
14

My root treated front tooth has darkened over time. What can be done about it?

Darkening is a known outcome after root canal treatment: pigments left from the nerve tissue and blood soak into the dentin, so the tooth greys from the inside. Ordinary external whitening often is not enough. Options include internal bleaching, composite bonding, or a veneer or crown for heavier discolouration. The choice depends on how much tooth structure is left and the state of the root filling.
15

Does the type of toothache, throbbing or aching, tell the dentist anything?

Yes, the character of the pain is an important clue. Sharp pain triggered by cold or sweet that fades within seconds usually points to sensitivity or decay that has not reached the nerve. Spontaneous, spreading, minutes-long throbbing suggests an inflamed pulp. Dull, well-localised pain on biting or tapping may mean the tissues around the root tip are involved. Describing timing and triggers really helps.
16

My pain eases during the day but gets worse when I lie down at night. Why?

There are a few reasons. Lying down increases blood flow and pressure in the head, and an inflamed pulp trapped inside hard tooth structure feels that pressure directly as pain. At night there are also fewer distractions, so the pain seems stronger. Spontaneous pain that wakes you usually means the pulp is seriously involved and is unlikely to settle on its own, so get examined soon.
17

Hot tea makes my pain worse and cold water relieves it. What does that mean?

This is a familiar sign and usually suggests the pulp is severely inflamed, with part of it losing vitality. Heat expands gases and fluid inside the tooth and raises the pressure, while cold briefly reduces it, which is why cold soothes. Painkillers give only short relief at this stage and the condition does not resolve by itself. Root canal treatment is usually needed, so have it assessed promptly.
18

Cold food makes my tooth sting for a few seconds and then it passes. Is that decay?

Not necessarily. Brief stinging that stops as soon as the trigger is removed is most often caused by exposed root surfaces from gum recession, enamel thinned by hard brushing or acidic drinks, wear from clenching, or tiny gaps at a filling margin; early decay can do the same. An examination, with an X-ray if needed, tells them apart. Desensitising toothpaste and a soft brush may help meanwhile.
19

My tooth hurts sharply only when I bite; otherwise there is no problem. What could cause that?

This description most often suggests a cracked tooth, especially if the sharp pain comes as you release the bite rather than while pressing down. Other possibilities are a high filling, inflammation at the root tip, decay under a restoration, or a chewing-muscle problem. Bite tests, removing the filling to inspect underneath, dyes, magnification and X-rays help sort it out. Avoid hard food on that side meanwhile.
20

I suspect a crack in my tooth but was told it does not show on the X-ray. How is it diagnosed?

Cracks often run parallel to the X-ray beam, so they do not show on film; the diagnosis relies mainly on symptoms and clinical tests. The dentist bites each cusp separately, shines a strong light through the tooth, examines it under magnification, may use a dye, and can remove a filling to look underneath. Treatment depends on the direction and depth, from a cuspal-coverage onlay or crown to other plans when the crack reaches the root.
21

Painkillers help but the pain returns after a few hours. Should I increase the dose?

Do not raise the dose on your own; that carries stomach, liver and kidney risks. Painkillers mask the perception of pain, not its source. Toothache usually comes from inflamed tissue inside the tooth or infection at the root tip, which medication cannot remove, so the pain returns and responds less over time. Treat painkillers as a temporary bridge until you are seen, and book an appointment without delay.
22

If I get an antibiotic from the pharmacy, will my toothache go away?

No, and antibiotics should only be used on prescription. In most toothaches the problem is infected tissue inside the canal, where the blood supply cannot carry the drug effectively, so nothing is solved until the source is cleaned out. Unsupervised use can mask symptoms, delay diagnosis and promote resistance. Antibiotics have a role in spreading infection or certain medical conditions, as judged by your dentist.
23

My face has swollen on one side along with the toothache and I have a fever. What should I do?

Do not delay this; it needs to be assessed the same day. Spreading facial swelling with fever can mean the infection has moved into the surrounding tissues. If you have difficulty swallowing or breathing, cannot open your mouth, the swelling reaches your eye, or you are deteriorating quickly, go to the nearest hospital emergency department immediately. Otherwise contact our clinic, avoid heat on the area and do not self-medicate.
24

A pimple-like bump appeared on the gum near my aching tooth and the pain eased. Am I getting better?

Unfortunately not. That bump is usually a sinus tract: pus from the root tip has found a way out, and the pain eased because the pressure dropped. The infection has gone quiet, not away, and it keeps affecting the surrounding bone. Most such cases need root canal treatment or retreatment, after which the tract usually closes. Do not try to pop it; have the tooth examined soon.
25

You can see which tooth hurts, so why do you still want an X-ray?

Because much of the problem develops where the eye cannot reach. An X-ray shows decay between teeth and under fillings, how close it is to the pulp, inflammation and bone loss at the root tips, the number and shape of canals, and the state of any old root filling. It also helps tell whether the pain is referred from a neighbouring tooth, so the plan is based on real findings.
26

Is having dental X-rays taken often harmful?

The radiation dose in dental radiographs is among the lower ones in medical imaging, and digital sensors have reduced it further. Even so, the principle is to take only images that genuinely add to diagnosis or treatment planning. Protective measures are used and the beam is limited to a small area. Always tell your dentist if you are pregnant, may be pregnant, or have had recent imaging elsewhere.
27

My tooth hurt badly for a few days and then went quiet on its own. I no longer need treatment, right?

Unfortunately silence after severe pain is usually not healing. In most cases it means the nerve inside the tooth has died, so the structure that carried the pain is gone. The infection, however, keeps travelling along the canal and can cause bone loss at the root tip, returning later as swelling or an abscess. An X-ray shows the real situation, and timely treatment is the safer path.
28

I am pregnant and my tooth hurts. Should I wait until after birth or can I be treated?

You do not need to wait; an untreated dental infection is a bigger problem for you and your baby than the pain itself. Necessary dental treatment can be carried out during pregnancy with suitable precautions, and the second trimester is usually the most comfortable period. Tell us how many weeks pregnant you are, which medicines you take and any advice from your doctor, so anaesthesia and imaging decisions are planned accordingly.
29

My child has decay in a baby tooth, but it will fall out anyway. Should I still have it filled?

Yes, treatment is recommended. Baby teeth matter for chewing, speech development and for holding space for the permanent tooth beneath; losing one early lets neighbouring teeth drift and can create crowding later. Their enamel and dentin are thinner, so decay progresses fast and may cause pain, an abscess or damage to the developing permanent tooth. The plan is chosen according to your child's age and the depth of decay.
30

My gums bleed when I brush. Should I stop brushing?

Do not stop brushing. Bleeding usually signals gum inflammation, and stopping makes it worse. Plaque left along the gumline swells the tissue, so it bleeds at the slightest touch. Brush gently twice a day with a soft brush angled about 45 degrees to the gumline, and clean between the teeth. If bleeding has not eased within two weeks, have your gums examined and the tartar removed.

From Our Blog

✦ Our Brands
Straumann
Nobel Biocare
Astra Tech
Medentika
Bredent SKY
Straumann
Nobel Biocare
Astra Tech
Medentika
Bredent SKY
✦ Contact
Get in touch

Antalya Muratpaşa our central clinic

Sair Adem Dede St. No:31, 07030 Muratpasa / Antalya, Türkiye

Open in Google Maps