

















































When a Bridge Is the Right Choice
Bridges and implants suit different situations; the decision depends on the site, the neighbouring teeth and the bone.
When a bridge is suitable
- The neighbouring teeth already need crowns or have large fillings
- Bone volume is insufficient for an implant and grafting is not wanted
- Surgery is not appropriate for medical reasons
- The patient prefers to avoid surgery
- A shorter overall treatment time is needed
When an implant is preferable
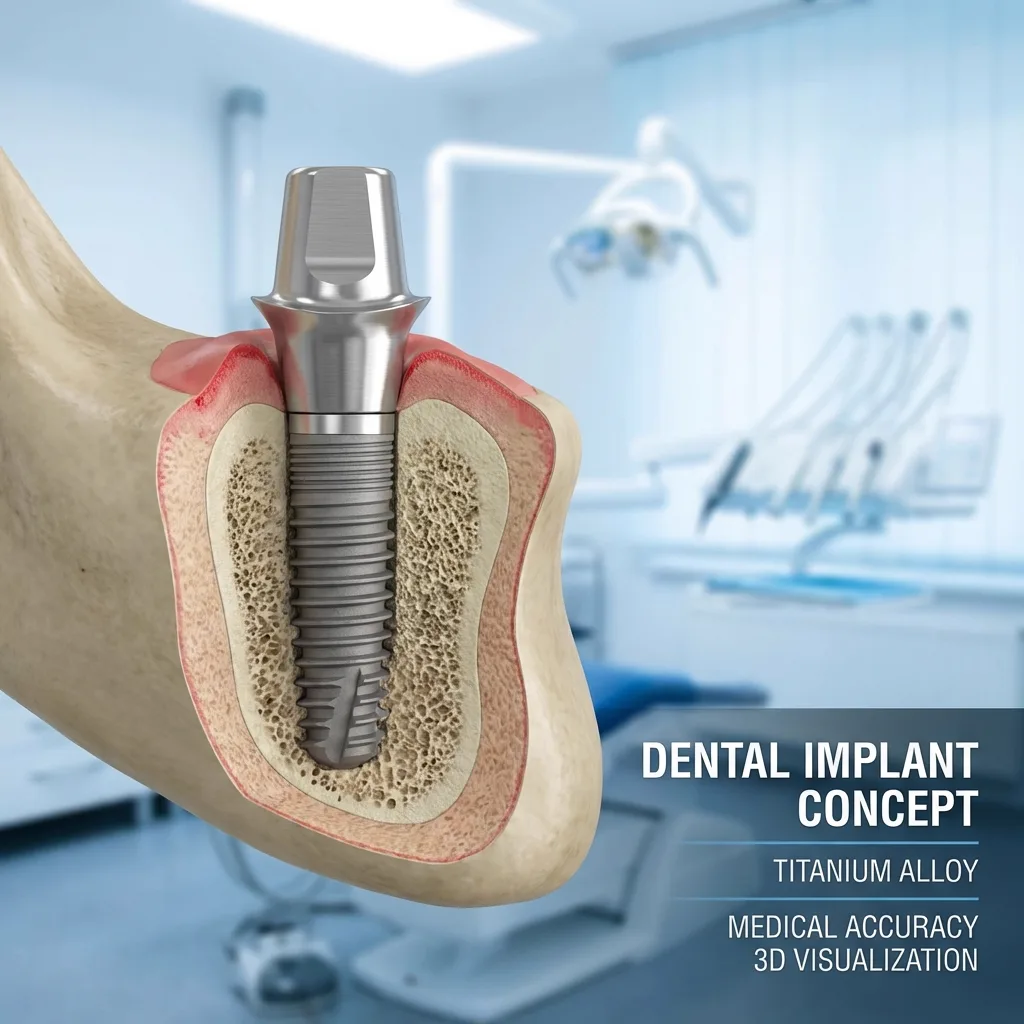
If the neighbouring teeth are untouched, reducing them is a permanent loss. Implants also stimulate the bone, whereas bone under a bridge pontic continues to resorb, which can leave a visible gap in time.
What happens if the gap is left
A gap left open lets neighbours tip in and the opposing tooth over-erupt, disturbing the bite and creating areas that cannot be cleaned. Closing it is preventive, not cosmetic.
Bridge Types and Materials
Bridges vary by how they are supported and what they are made of.
Conventional bridges
The most common type: crowns on both sides carry the pontic between them as a single unit, distributing chewing forces to two abutments.
Maryland bridges
Wings bonded to the inner surfaces of the neighbouring teeth with almost no reduction. The most conservative option, but suited to the low-load front region.
Cantilever bridges
Supported from one side only, used in limited situations; the leverage on the single abutment requires careful planning and it is avoided in the back.
Zirconia and metal-ceramic bridges
Metal-ceramic bridges are durable but can show a grey line as the gum recedes. Zirconia has no metal substructure, transmits light more naturally and avoids that problem.
The Process and Long-Term Care
A bridge is usually completed in two main visits, and its lifespan depends largely on care.
Preparation and impression
The abutments are reduced under local anaesthesia by the thickness of the crown, then an impression is taken and the shade selected in natural light.
Temporary bridge
A temporary bridge protects the prepared teeth and gum contour. If it comes off it must be replaced promptly, or the teeth may move and the final bridge will not fit.
Try-in and cementation
The finished bridge is tried in to check fit, bite and shade before being cemented; report any feeling of a high bite.
Cleaning under the pontic
This single habit determines the bridge's lifespan. Ordinary floss cannot enter under the pontic, so superfloss is threaded beneath it; interdental brushes and a water flosser also help. Neglect here causes decay at the abutment margins — the most common reason bridges fail.
Assessment Before a Bridge and Situations Where It Is Not Suitable
The longevity of a bridge is directly related to how much load the abutment teeth on either side of the gap can carry.
The Load-Bearing Capacity of Abutment Teeth
A bridge is a design that transfers the load of the missing tooth to the neighbouring teeth. The root length, number of roots, proportion of bony support and mobility of the abutment teeth are therefore examined in detail. Overloading a tooth with short roots or reduced support can eventually lead to losing that tooth as well.
The length of the gap is also decisive. In long spans the pontic is exposed to greater bending forces; in that case increasing the number of abutments or moving to a different treatment option comes onto the agenda. The decision is made together with radiographic assessment and bite analysis.
The Role of Gum and Bone Support
If there is gum inflammation or advanced bone loss, a bridge is not placed straight away; that condition is treated first. A restoration made on inflamed tissue loses its marginal fit, gum bleeding continues and the area beneath the bridge becomes impossible to clean. Once the tissues have settled after periodontal treatment, the impression stage is far more accurate.
Gum thickness and ridge height at the edentulous site determine how the pontic relates to the gum. Where there is marked collapse, hard-to-clean voids can form between pontic and gum; the pontic form is then designed accordingly, or preparation of the site is planned in advance.
When a Bridge Is Deferred or Considered Unsuitable
- Untreated decay or root canal infection in the teeth intended as abutments
- Active gum disease and the marked loss of support that accompanies it
- Advanced mobility in the abutment teeth
- Absence of a tooth behind the gap to act as a posterior abutment
- Very long spans where a single bridge would be overstretched
- An uncontrolled clenching or grinding habit
- An extraction site where healing is not yet complete
Managing Problems and Long-Term Follow-Up With a Bridge
Most problems with a bridge can be solved with a smaller intervention when they are noticed early.
A Loose or Dislodged Bridge
If the bridge feels slightly mobile, this usually means the cement has failed or that there is a problem with one of the abutment teeth. Food and bacteria accumulate under a loosened bridge, so the complaint should not be postponed. Trying to press it back into place by biting hard strains the abutment tooth.
If the bridge has come away completely, it should be kept in a clean container and brought to the appointment. Where the abutments are sound, the bridge can sometimes be cleaned and re-cemented; if there is decay or a fracture in an abutment, that tooth is treated first. Only clinical and radiographic examination can make this distinction.
Decay and Root Canal Problems in an Abutment
Decay in an abutment beneath a bridge usually begins at the crown margin, at the gum line, and is not easily seen. This is an area that both the brush and the tongue struggle to reach. For that reason these margins are checked specifically at follow-up visits and evaluated radiographically when necessary.
If hot and cold sensitivity, pain on biting or gum swelling develops in an abutment, root canal treatment may be required. In some cases this can be carried out through the crown without removing the bridge; in others the bridge has to be removed. Presenting early increases the chance of preserving the bridge.
What Follow-Up Focuses On
- The fit of crown margins at the gum line and plaque accumulation there
- Whether cleaning under the pontic is genuinely being achieved
- Sensitivity, mobility and pain on biting in the abutment teeth
- Bleeding, recession or persistent redness of the gum
- Premature contacts in the bite, since load concentrated on one point strains the bridge
- Cracks, chips or noticeable wear on the porcelain surface
- Signs of night-time clenching and, where indicated, use of a protective splint