




























Patient Reviews 4.9/5 10.000+ Happy Patients 37 Countries

Composite Bonding in Antalya — Aesthetic Restorations

✦ Tedaviler

Composite Bonding in Antalya — Aesthetic Restorations

Composite bonding in Muratpasa, Antalya: chips, gaps and shape corrections in a single visit without cutting the tooth.

✦ Our Patients

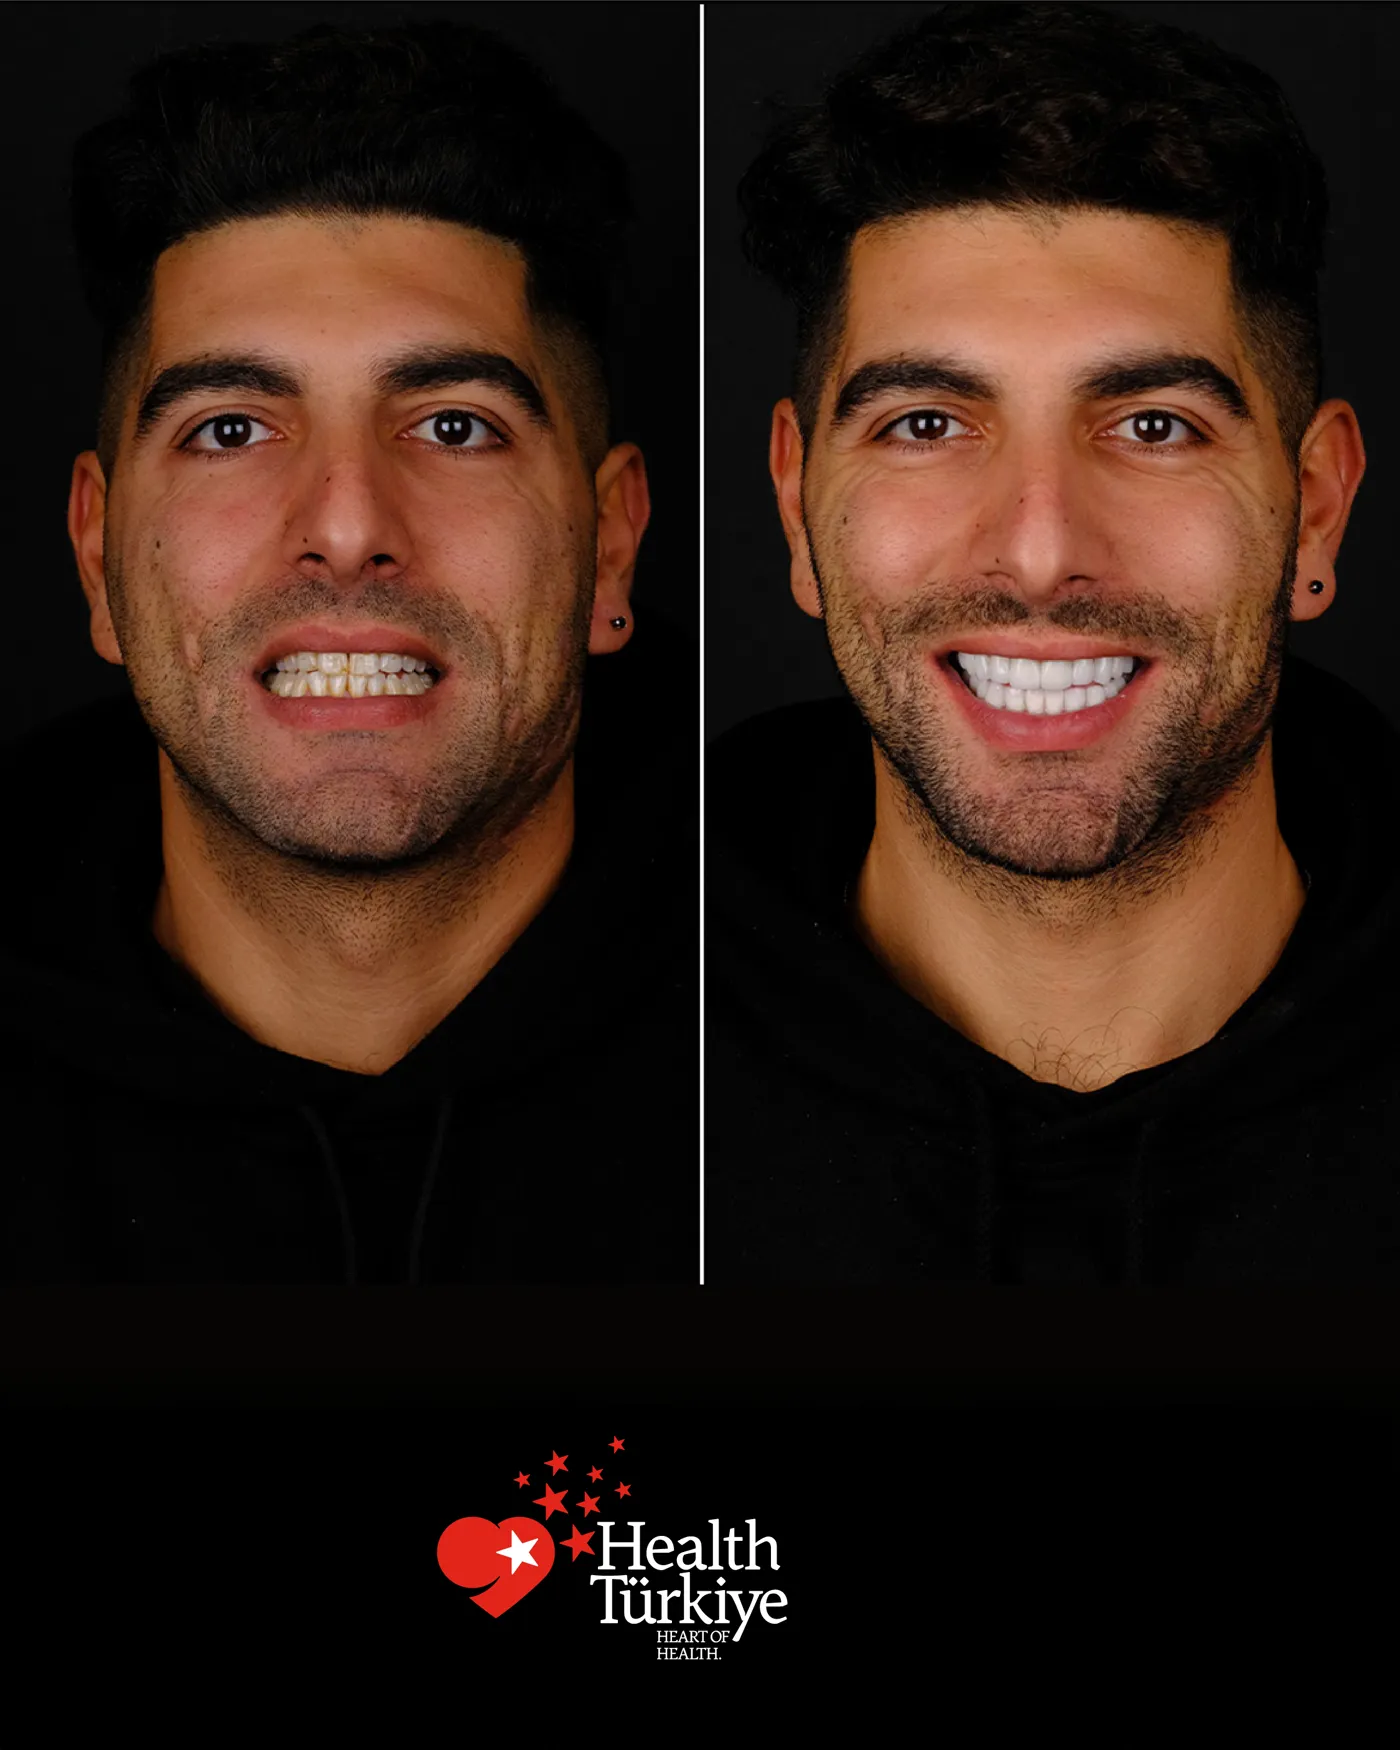
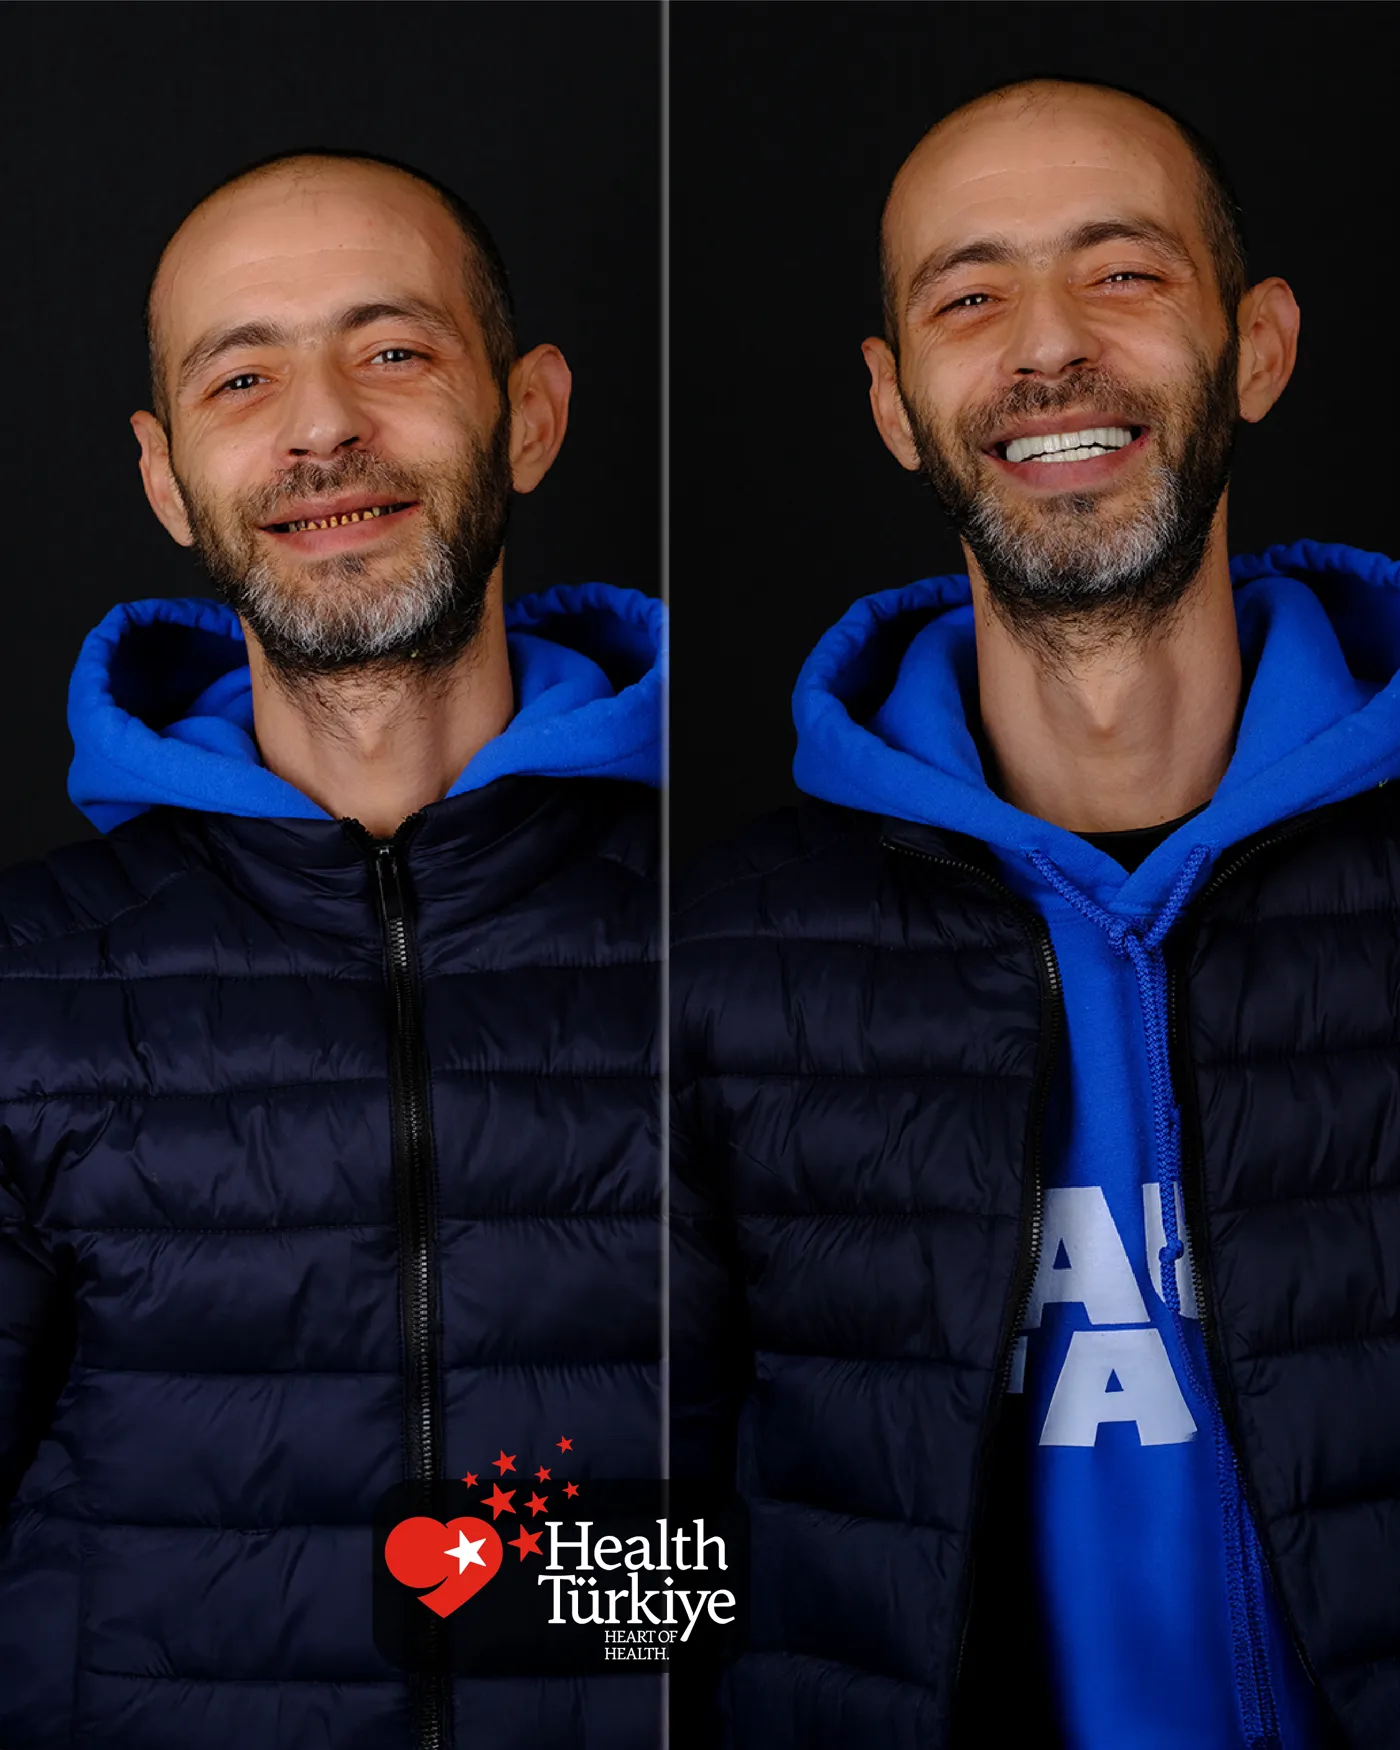
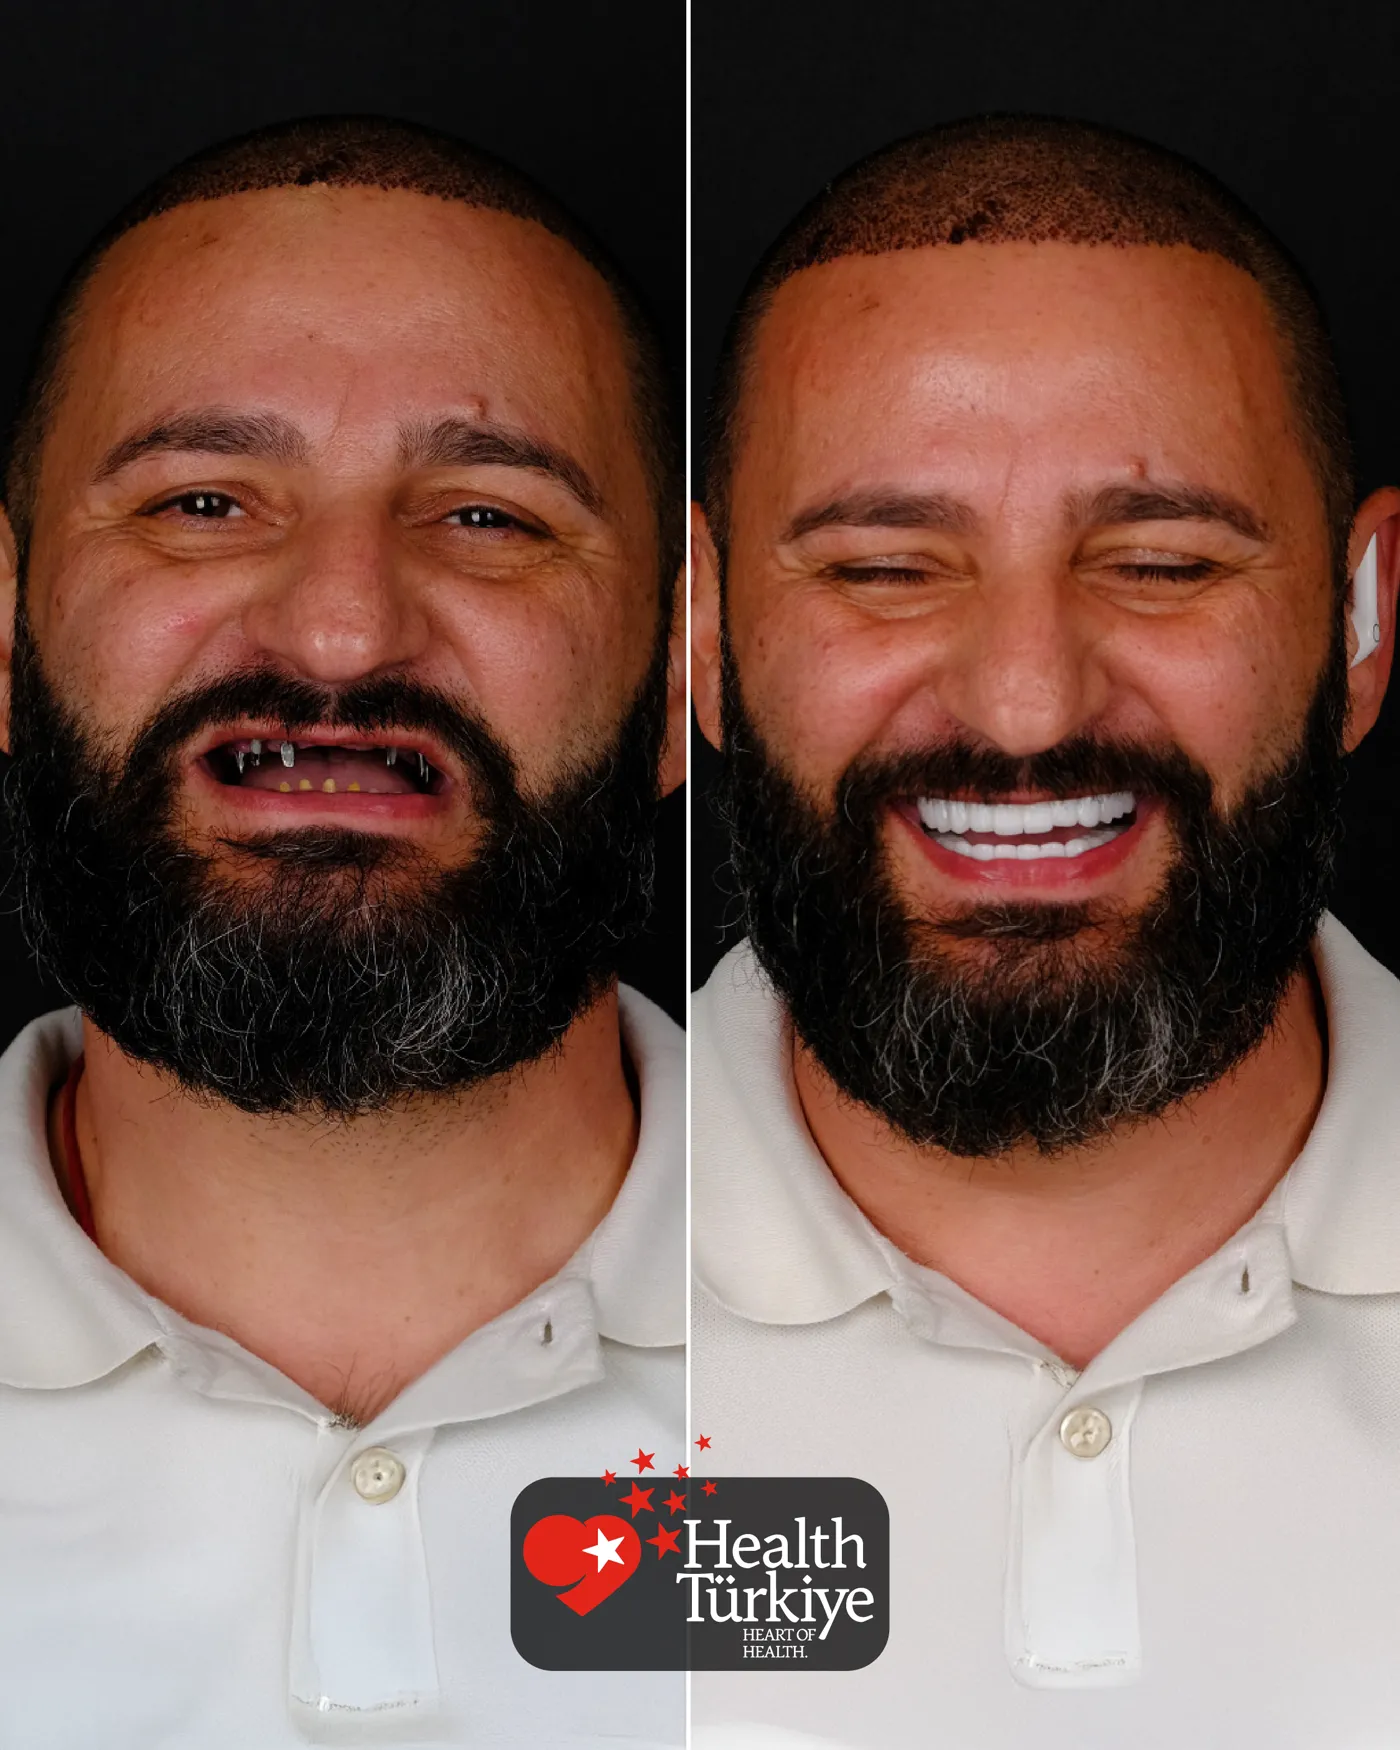
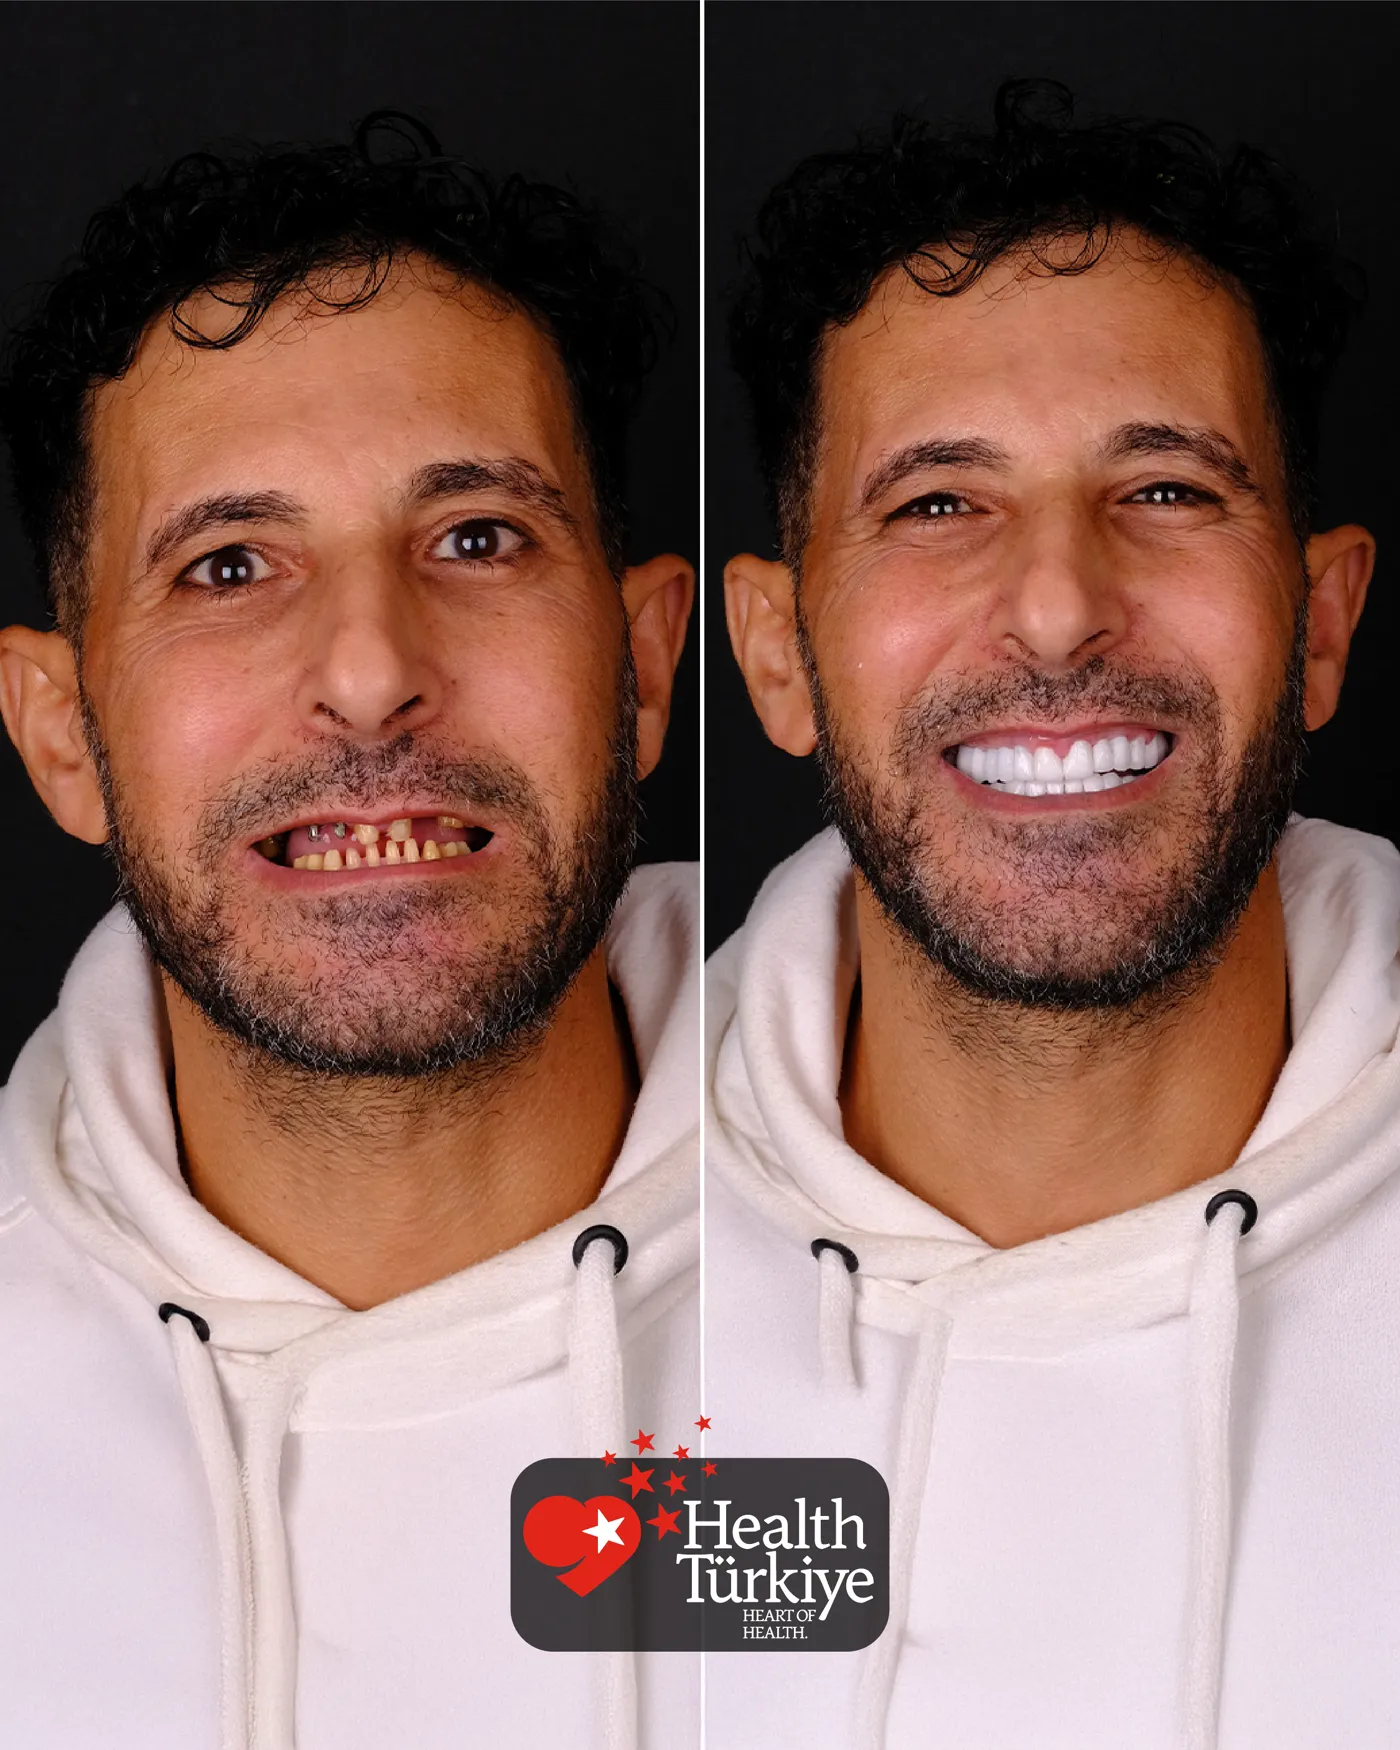
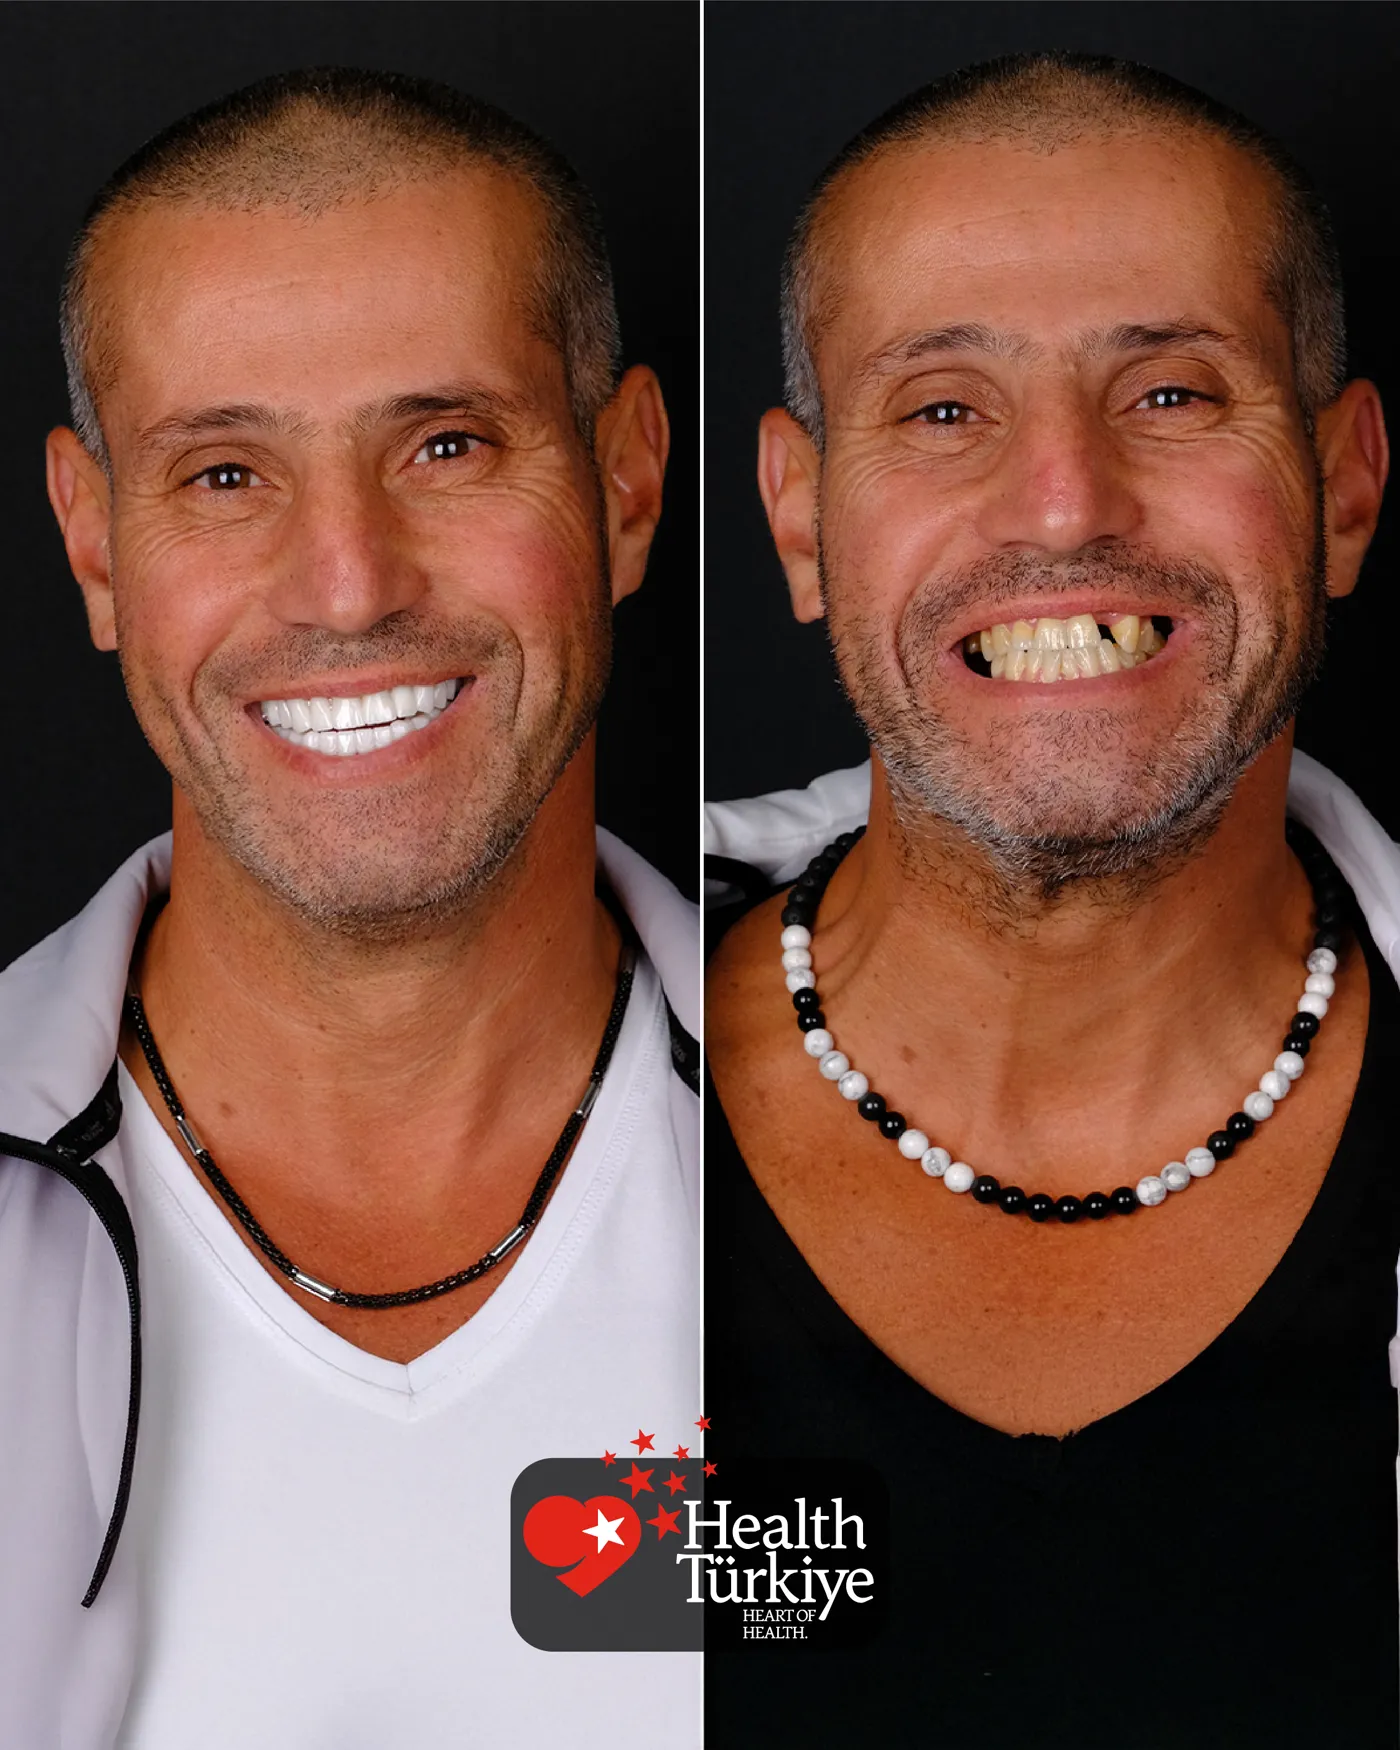
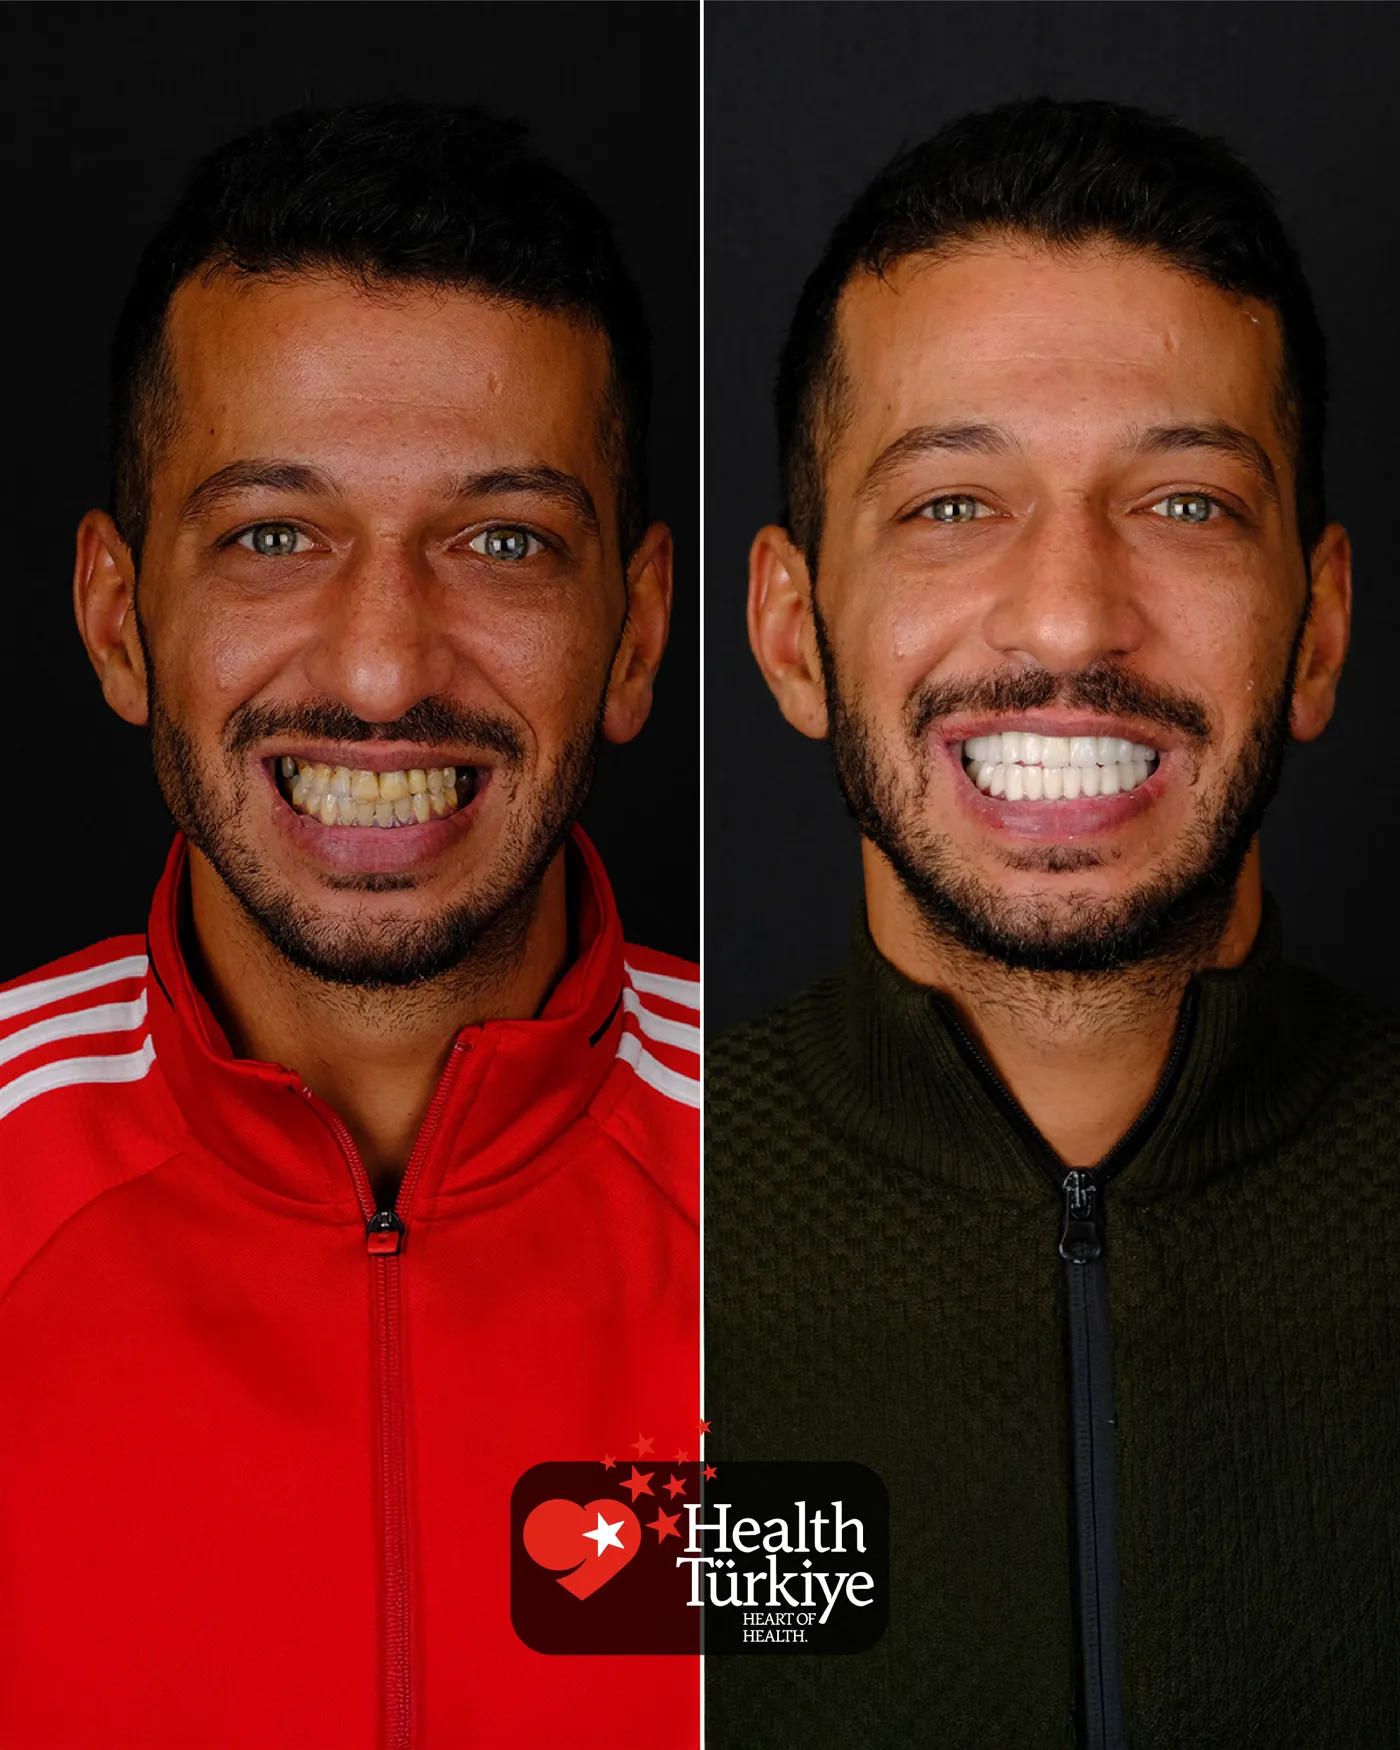
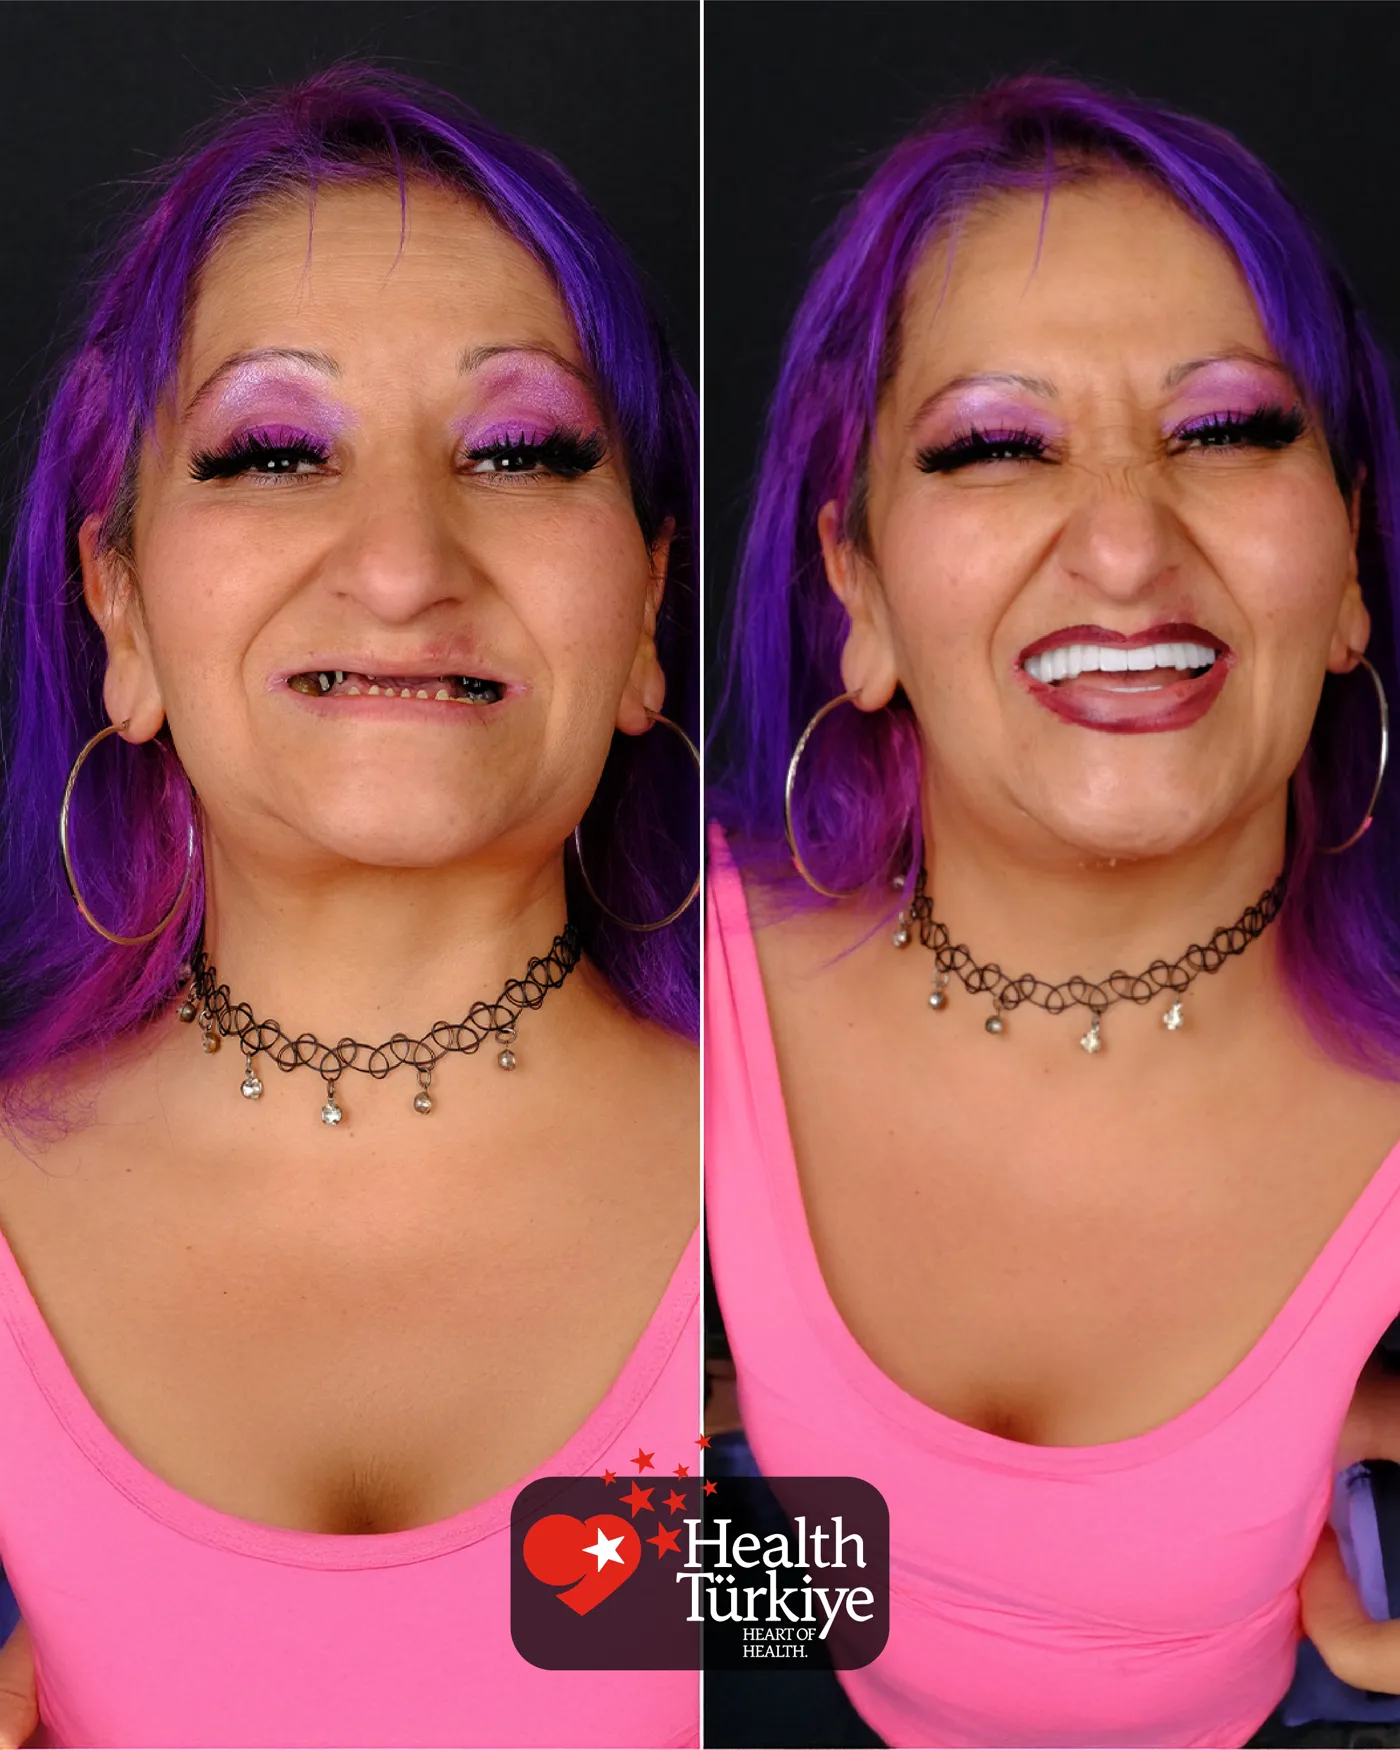
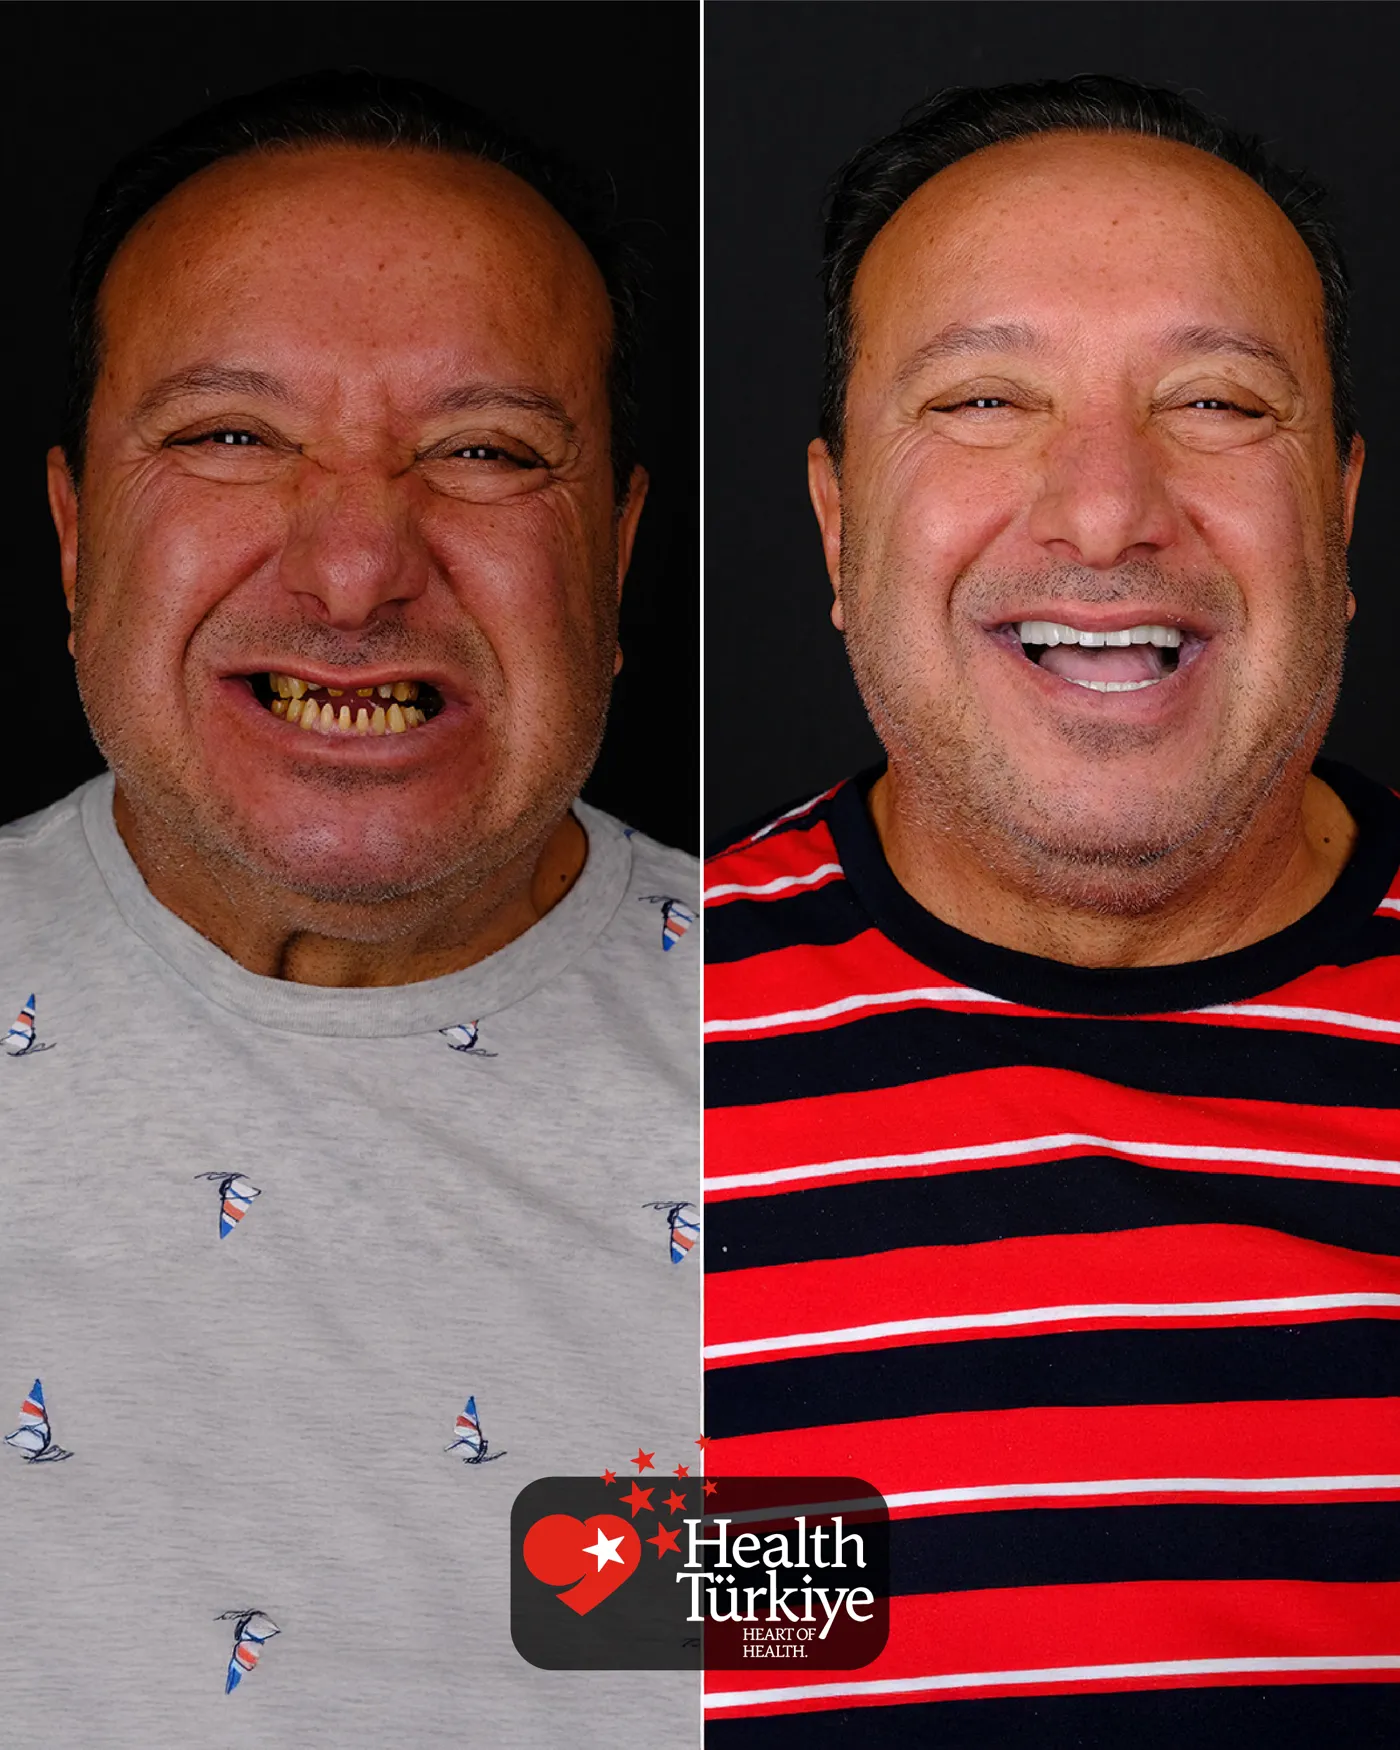
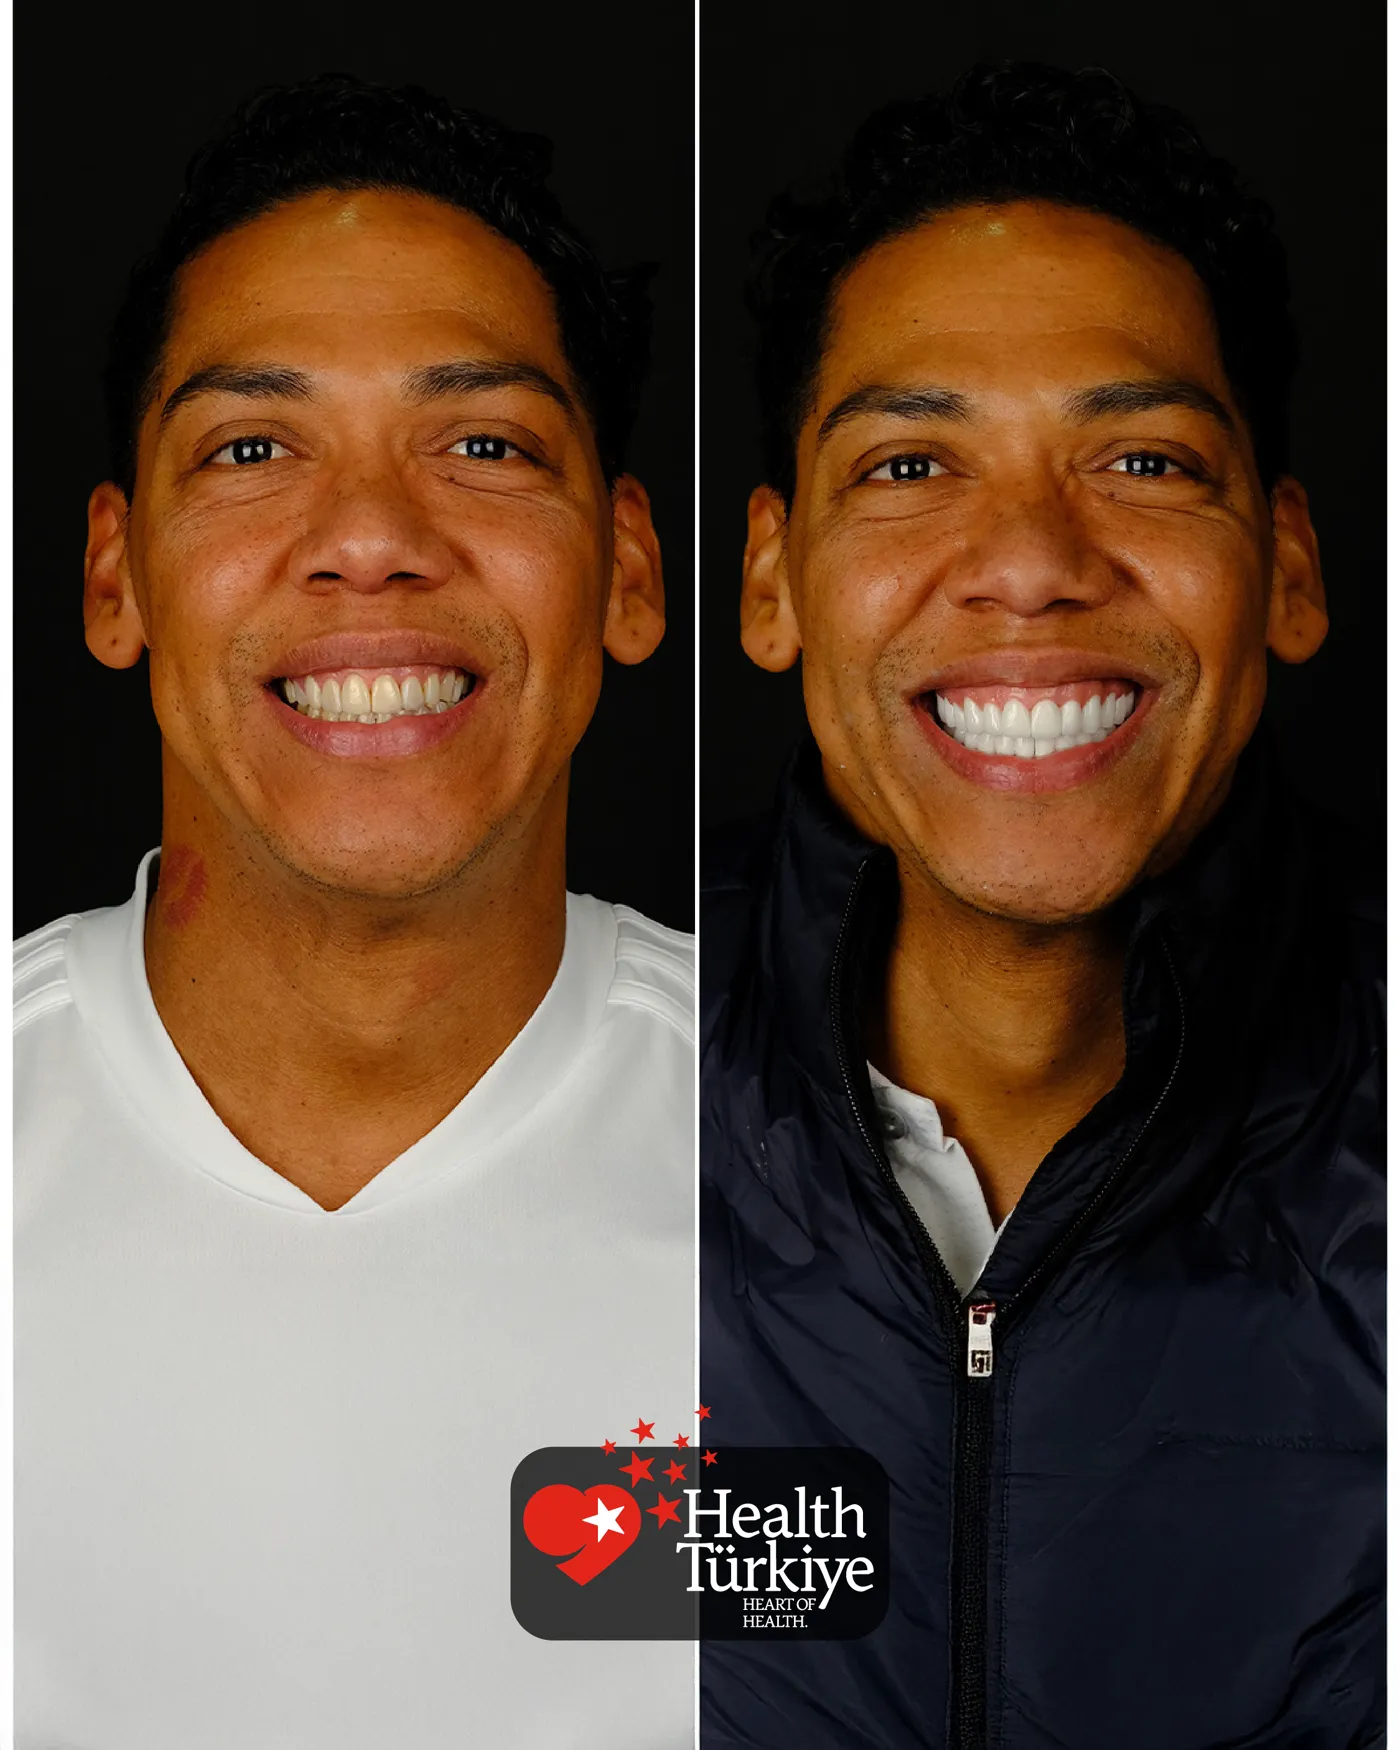
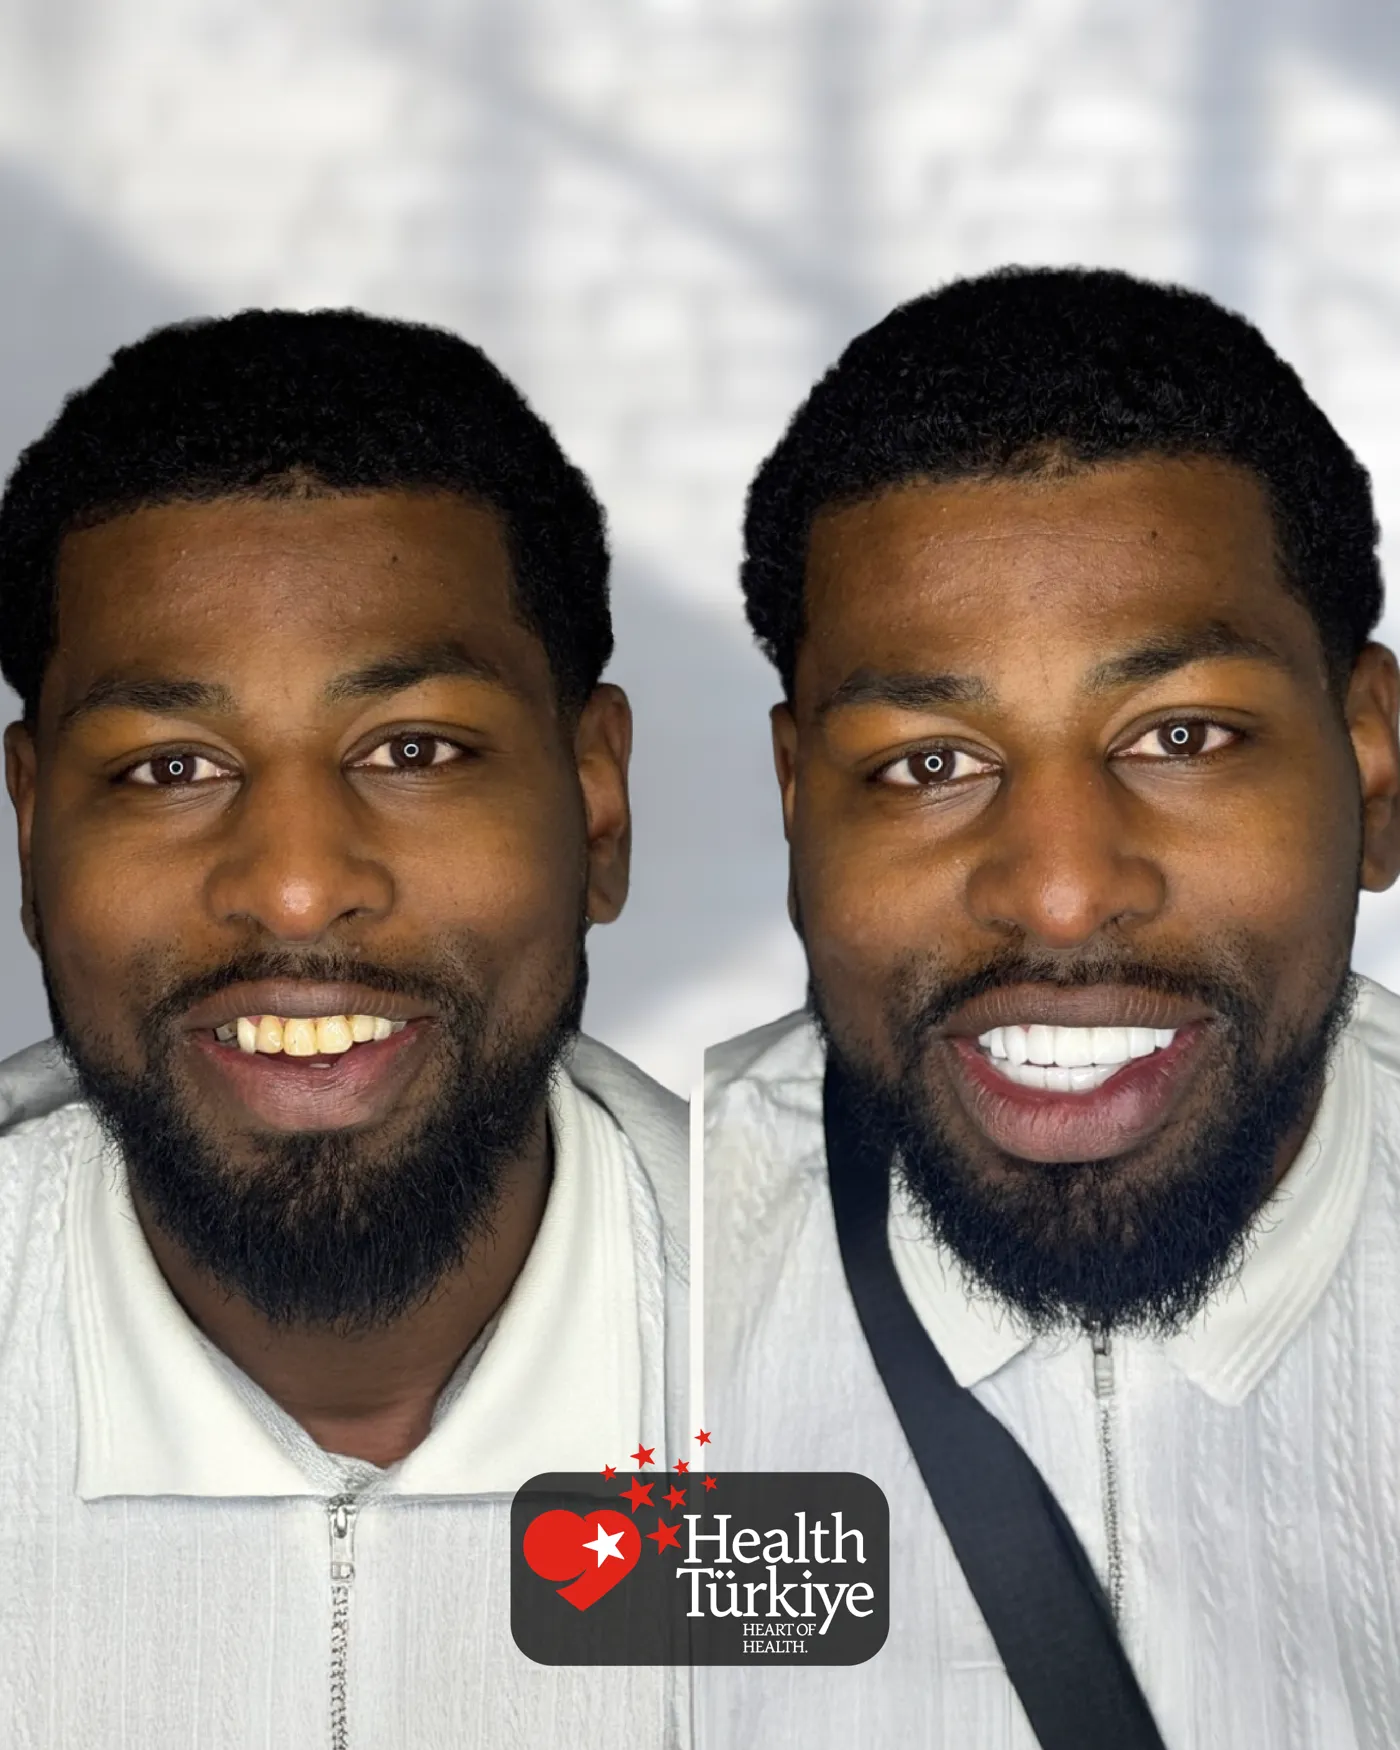
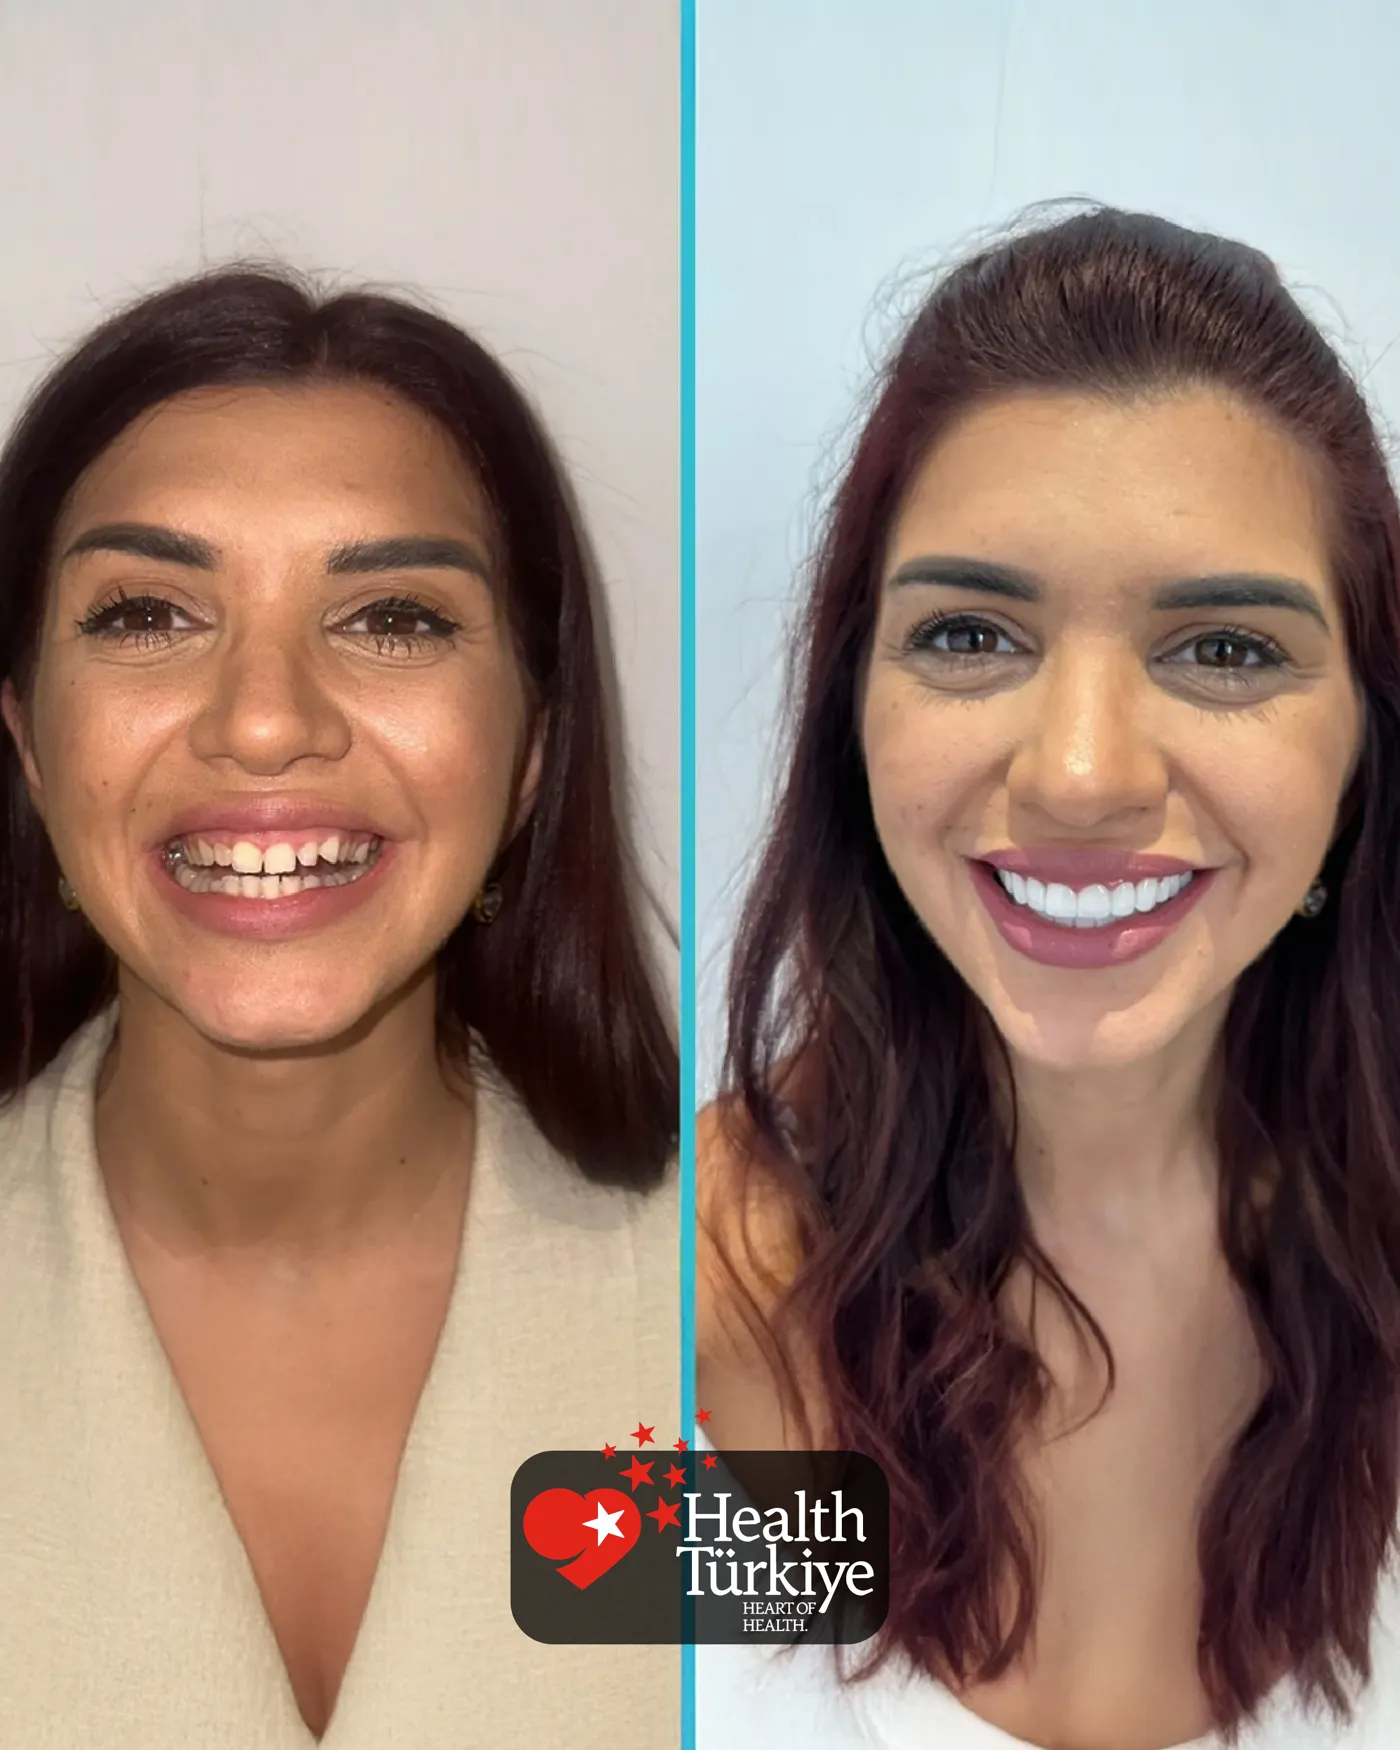
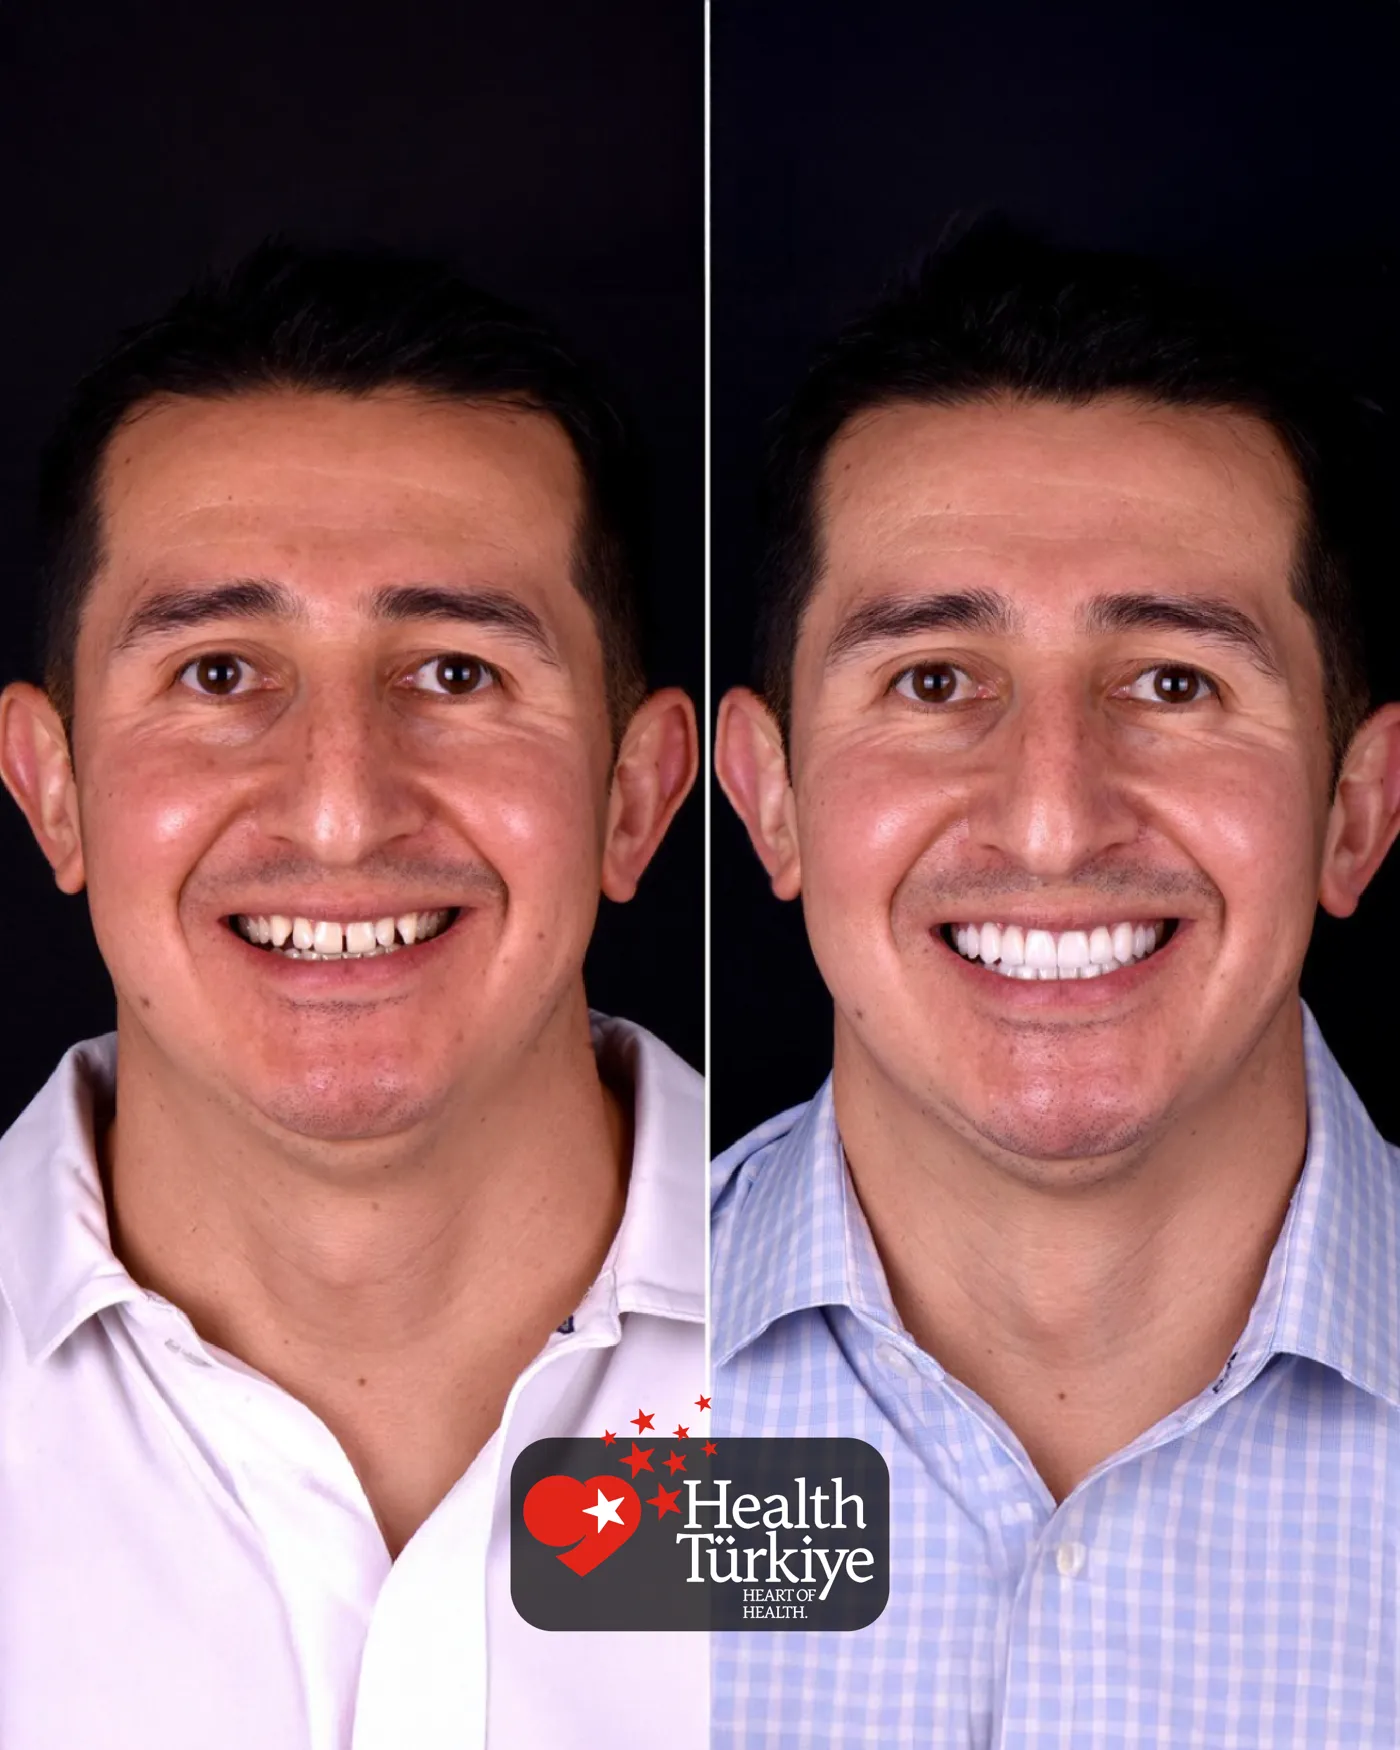
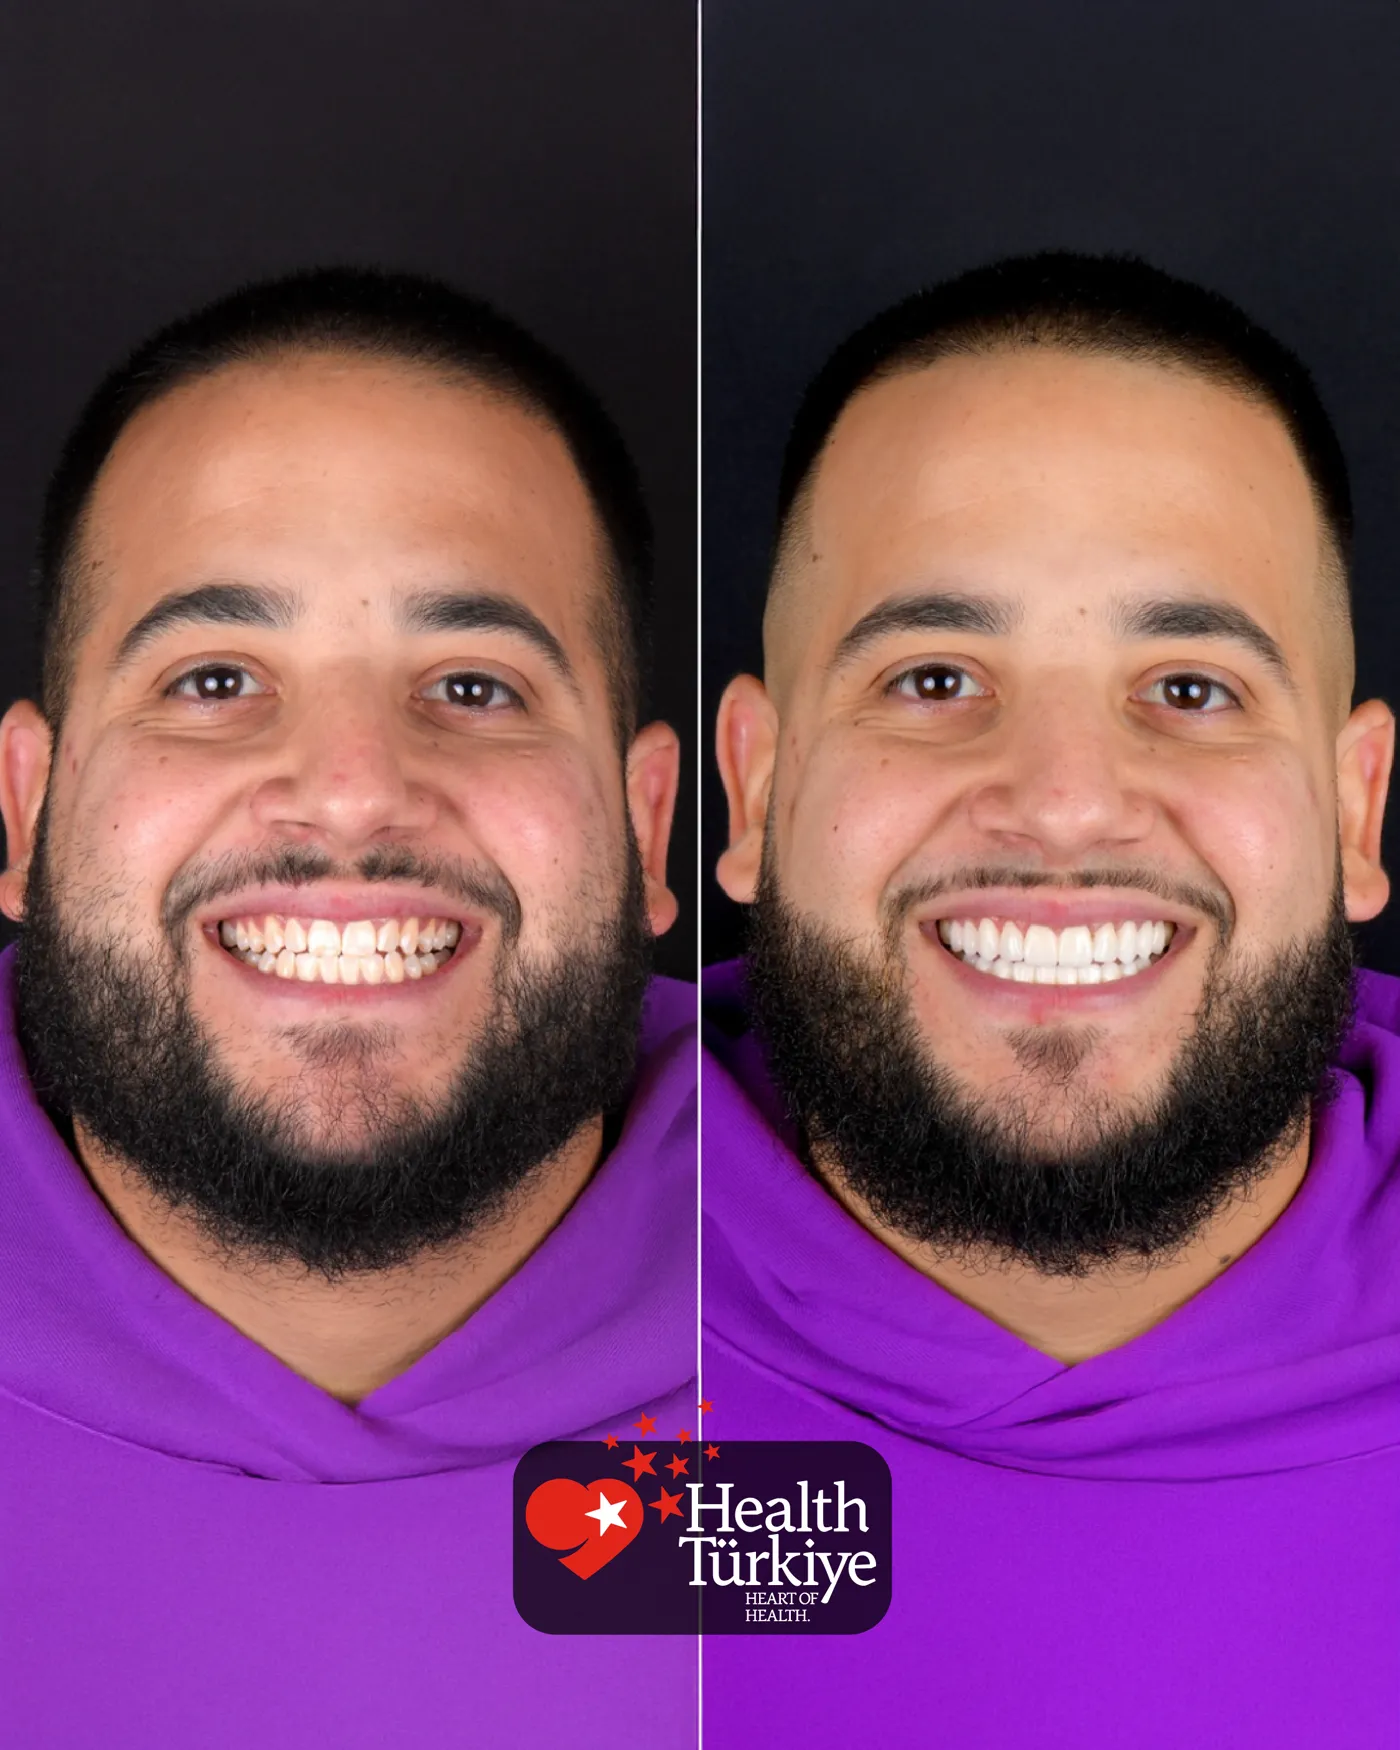
Photos from treatments performed at our clinic

Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
✦ Our Clinic
kliniğimiz
kliniğimiz
kliniğimiz
kliniğimiz

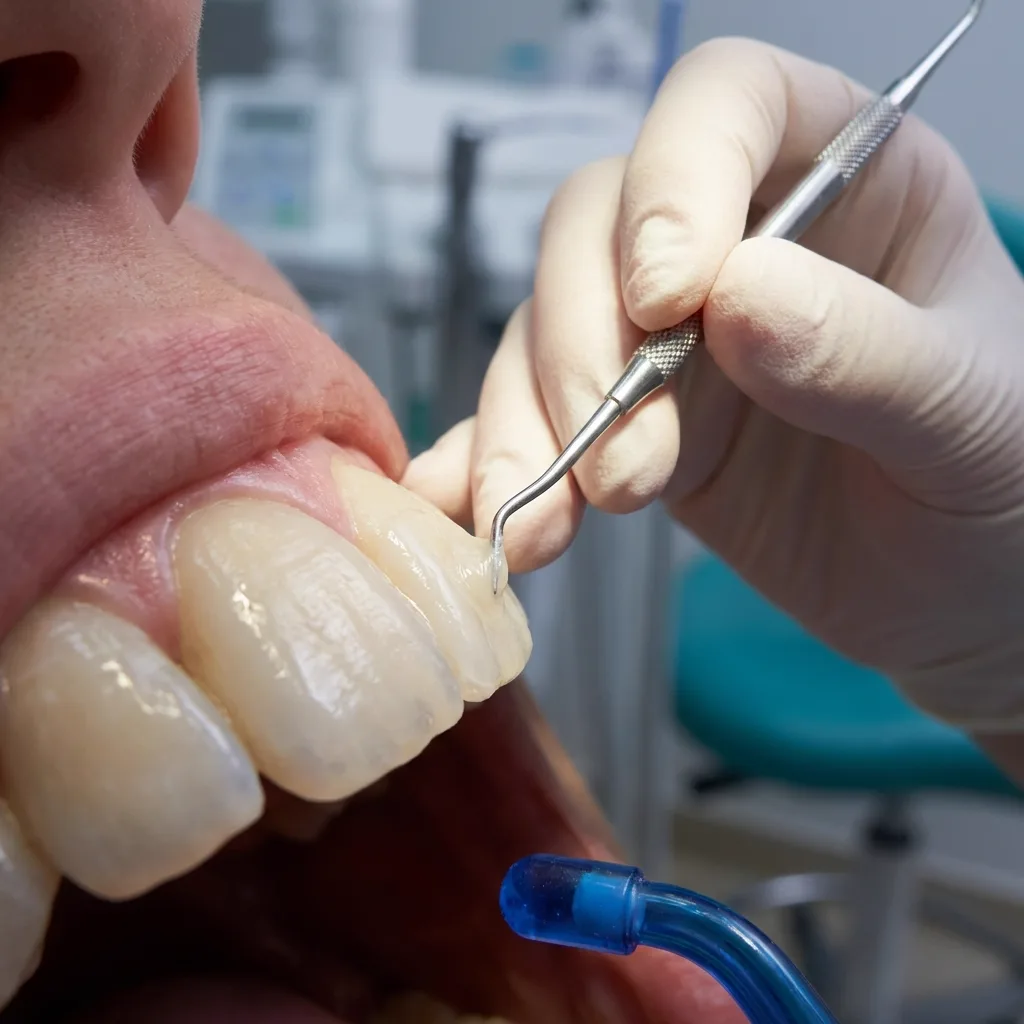
Bonding is the direct application of tooth-coloured composite resin, shaped by hand and cured with light — the least invasive aesthetic treatment.

Its defining feature is that the tooth is not cut. Veneers and crowns remove structure permanently; bonding only etches the surface and adds material on top.

This makes it reversible: if you change your mind, the tooth is still intact. It is often the first option for younger patients and for anyone not ready for a permanent decision.

What Bonding Can Correct

Bonding gives fast results for a limited but very common group of aesthetic problems.

Where it is used

  • Small chips and cracks in the front teeth
  • Closing gaps between teeth
  • Correcting the shape and length of a tooth
  • Masking a single discoloured tooth
  • Restoring wedge-shaped wear at the gum line
  • Camouflaging slight irregularity

Closing gaps

Closing a midline gap is the most common use. The key is proportion: simply filling the space can make the teeth look too wide, so width-to-length ratio must be preserved. Wide gaps may be better assessed orthodontically first.

When bonding is not enough

Large losses, severe discolouration, significant crowding and heavy clenching are not suited to bonding; veneers, crowns or orthodontics are more predictable.

How Bonding Is Applied

The procedure is completed in one visit and usually needs no anaesthesia.

Planning and shade selection

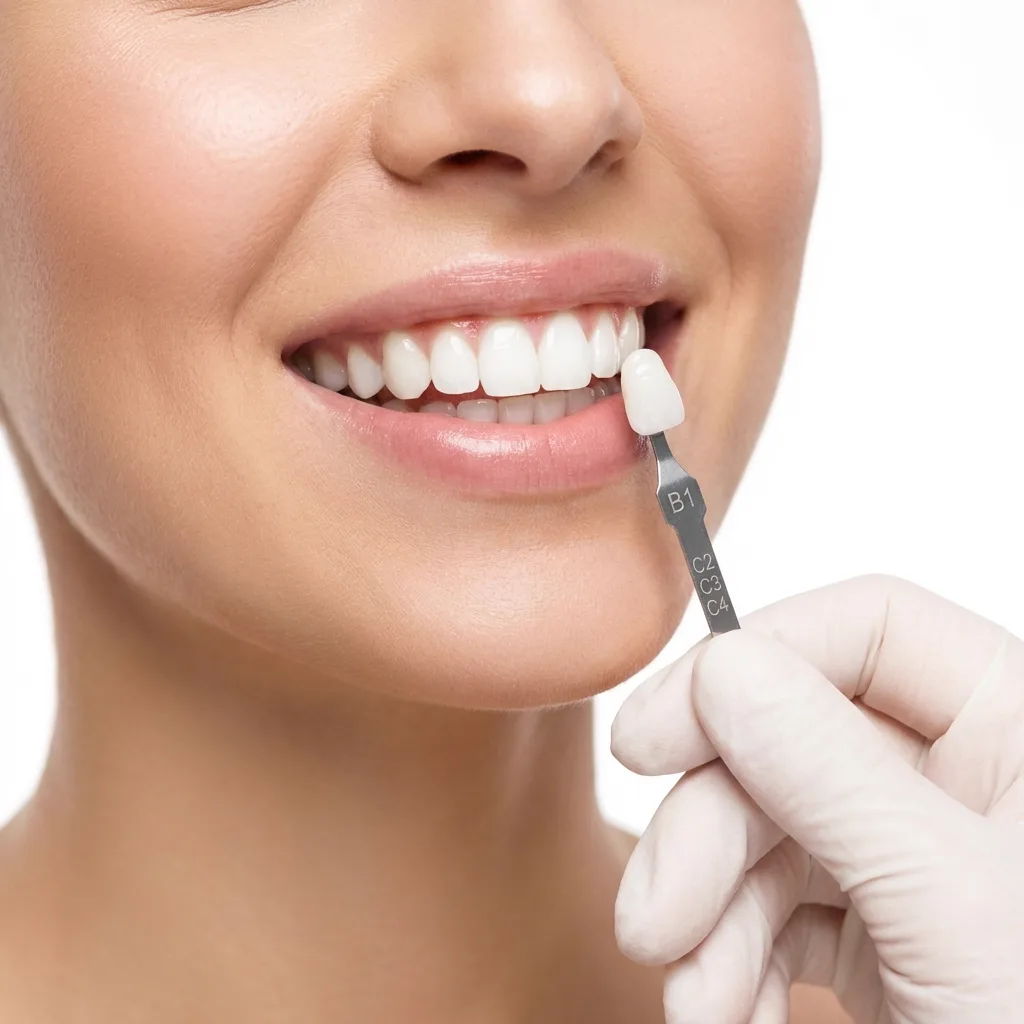
The existing form, smile line and lip support are assessed, then the shade selected in natural light. Layering composites of different opacity reproduces natural depth; a single-shade application looks artificial.

Surface preparation

The surface is cleaned and briefly etched to create microscopic retention, then a bonding agent is applied. No tooth is cut and the process is painless.

Shaping and polishing

Composite is placed and cured in layers, shaped by hand in the mouth. Final polishing determines the outcome: a well-polished surface reflects light naturally and resists plaque, while a poorly polished one looks matt and stains quickly.

Aftercare and Longevity

Bonding is not a permanent material but a surface maintained by care.

The first 48 hours

Composite sets immediately but the surface is more receptive to pigment on the first day; avoiding coffee, tea, red wine and smoking for two days helps long-term colour stability.

Habits to avoid

  • Nail biting and pen chewing
  • Opening packaging or nuts with the teeth
  • Biting ice or very hard food with the front teeth
  • Smoking, which markedly accelerates staining
  • Night-time clenching; a night guard may be needed

Staining and refreshing

Composite is more porous than porcelain and can pick up colour — a property, not a fault. Surface staining is largely removed by professional polishing, and chips can be repaired locally without redoing the whole restoration.

Bonding or veneers?

Bonding is single-visit, non-invasive and reversible but stains more easily; veneers are more durable and colour-stable but permanently remove tooth structure.

Who Is Suitable for Bonding and Who Is Not?

Bonding is strong for small and moderate aesthetic corrections; its limits are drawn by the remaining tooth tissue and the forces in the bite.

Situations Where Bonding Gives Good Results

Small edge fractures on front teeth, narrow gaps between teeth, mild irregularities of shape and limited surface staining are the situations where bonding is used most effectively. Because the material is applied directly to the tooth, in most cases almost no tooth tissue is sacrificed.

It also stands out as a reversible option in younger patients, where the gum level and smile line have not yet settled. Even if a different treatment is considered in the long run, a correction made with bonding does not close off that route.

Where the Limits of Bonding Are Stretched

Where loss of substance covers a large part of the tooth surface, where there are extensive old fillings or severe discolouration, the long-term success of composite decreases. Likewise, in a deep bite or edge-to-edge contact, the forces on the front teeth can stress thin composite margins.

Placing bonding while there is untreated decay, active gum inflammation or an unmanaged clenching habit makes the result short-lived. This does not mean bonding cannot be done; it means the underlying problem is addressed first and the aesthetic stage follows.

What Is Assessed Before Treatment

  • The condition of decay and old fillings on the tooth surface
  • Gum health and whether there is any bleeding
  • The type of bite and the direction of force on the front teeth
  • Habits such as clenching or nail biting
  • Whether the tooth shade would change with whitening
  • The surface texture and translucency of the neighbouring teeth
  • How frequent staining habits such as coffee, tea and smoking are

How the Choice Between Bonding, Laminates and Crowns Is Made

The decision is based on the balance between reversibility, expected durability and the size of the problem being corrected.

Reversibility and Tissue Preservation

The clearest advantage of bonding is that in most cases the tooth tissue is preserved. If the result is not liked, or a different plan becomes appropriate over time, the composite can be removed and the tooth stays largely close to its original state.

With ceramic restorations, however thin they may be, some preparation is carried out and that is irreversible. For younger patients or where a decision is not yet settled, trying a stage with bonding first can be a sensible approach. If needs change over time, the route to ceramic remains open.

The Balance of Durability and Colour Stability

Composite has a more porous surface than ceramic and is therefore open to staining over time from coffee, tea and smoking. Regular polishing can largely refresh its appearance, but it calls for periodic maintenance.

A ceramic surface is more stable in colour and keeps its lustre longer. If it fractures, however, repairing it in place is harder than with composite. The question when deciding is this: does attending maintenance intervals regularly suit you, or a solution that needs intervention less often but more preparation at the outset?

Summary of the Decision Criteria

  • How much of the tooth the area to be corrected covers
  • How much of a priority preserving tooth tissue is
  • How pronounced staining habits are
  • The routine of attending maintenance and polishing appointments
  • How many appointments the treatment is expected to take
  • How the forces in the bite are transmitted to the front teeth
  • Whether a change to a different treatment is being considered later

✦ SSS

Frequently Asked Questions 30

01

Which problems can bonding solve?

Small chips, narrow gaps, worn edges, slight irregularities of shape and limited colour corrections can be solved with bonding. Where there is widespread discoloration, advanced wear or a bite discrepancy, bonding is not enough and veneers, crowns or orthodontics are considered instead.
02

Is bonding reversible?

Yes, and that is its most important advantage. Because the tooth is not cut — only the surface is etched and material added — your tooth remains in its natural state if you later want a different solution. This makes bonding a sensible starting point, particularly in young patients and when you are undecided.
03

How many years does bonding last?

It depends on its position, the chewing forces and habits. Bonding at an incisal edge chips sooner with habits such as nail biting and biting hard objects. Regular polishing protects the surface. When it does chip, the whole restoration is not usually replaced — only that area is repaired.
04

When can I drink coffee after bonding?

For the first 48 hours the composite surface has not yet fully stabilised, so dark drinks and foods are best avoided. After that there is no restriction, though in the long term coffee, tea, red wine and smoking accelerate surface staining, which polishing removes.
05

What is the difference between bonding and veneers?

Bonding is done in the mouth, in one visit, without cutting the tooth; a veneer is made in a laboratory, needs a thin reduction and takes two visits. Veneers are superior in colour stability and surface gloss; bonding is reversible and less invasive. The choice follows your expectations and the state of the tooth.
06

Does closing a gap with bonding look natural?

If the gap is narrow and the proportions of the teeth allow, the result looks natural. With wide gaps, narrowing it orthodontically first or distributing it equally between both neighbours avoids making the teeth look too wide. This is assessed beforehand and can be shown to you with a mock-up.
07

Does bonding cause decay?

The material itself does not decay, but if the margin is not polished properly it holds plaque and decay can start there. Polishing after bonding and regular review therefore matter. You should continue using floss in the treated area; the material withstands it.
08

Can whitening be done after bonding?

It can, but composite does not lighten; once the natural teeth are whiter the bonding looks dark and has to be redone. The correct order is whitening, a wait of a few weeks for the shade to settle, then bonding. If whitening is part of your expectation, saying so at the outset changes the plan.
09

How many teeth can be done in one session?

Because there is no laboratory stage, several teeth can be done in one session, though each needs careful shaping and polishing so the appointment lengthens. At the front, where symmetry matters, the teeth are shaped as a whole rather than one at a time.
10

Is a chipped bonding an emergency?

It is usually not an emergency; when the material chips, the tooth beneath is not damaged. If a sharp edge is irritating the tongue or lip, however, or it bothers you aesthetically, book soon. The repair is usually completed quickly in a single visit.
11

Is the tooth cut for bonding?

No. The tooth surface is only etched to give the material something to grip, and composite is added on top. That makes bonding a reversible treatment: if you later want a different solution, the tooth underneath is still in its natural state.
12

How many visits does it take?

Usually a single visit, because there is no laboratory stage — the material is shaped and set in your mouth on the day. If several teeth are being treated the appointment takes longer, but it can still generally be completed in one sitting.
13

How long does bonding last?

It depends on hygiene, diet and clenching; staining is polished away and chips repaired. Smoking and grinding shorten its life.
14

Does bonding discolour?

Composite is more porous than porcelain and can take up colour over time. Coffee, tea, red wine and smoking accelerate that. Regular polishing at review appointments removes most surface staining and restores the finish, which is part of maintaining bonding rather than a sign it has failed.
15

Can bonding be combined with whitening?

Whitening has to come first. Composite does not respond to bleaching gel, so if the bonding is placed beforehand it will be left darker once the natural teeth lighten, and it would have to be redone. The correct order is whitening, then a short wait for the shade to stabilise, then bonding.
16

Is bonding painful?

No. Because the tooth is not cut, anaesthesia is usually unnecessary. Local anaesthetic may be preferred where the work extends to the gum margin, but for most bonding it is not needed at all, which makes it a good starting point for anxious patients.
17

Can bonding be repaired or renewed?

Yes, and this is one of the most practical aspects of composite. A small edge chip or a stained area can be repaired by adding the same material without removing the whole restoration. When the surface becomes dull over time, polishing largely refreshes its appearance.
18

Does bonding harm the gums?

Bonding that is finished correctly and well polished does not harm the gums. Problems arise if composite is left overhanging at the gum margin; that area retains plaque and can lead to inflammation. The finish at the margin is therefore checked after treatment and flossing is recommended.
19

Is bonding done after orthodontic treatment?

It is done frequently. Orthodontics aligns the teeth, but small differences in tooth size or edge shapes can become more noticeable once alignment is complete. Bonding is a suitable finishing step for such refinements. Its timing is considered together with the retention plan.
20

Can someone who wears a night guard have bonding?

Yes; in fact wearing a night guard helps protect the life of bonding in people who clench. After treatment the fit of the guard is checked again and it is remade if necessary. Not wearing it consistently increases the likelihood of chipping at the composite margins.
21

How many stages does implant treatment take, and what happens at each one?

Implant treatment usually runs in three stages. First an examination with radiographs, and tomography when needed, to assess the bone and plan the space. Then the implant is placed in the jawbone under local anaesthesia, which is normally short and comfortable. After healing, impressions are taken and the crown or prosthesis is fitted. Total time varies with your bone and healing.
22

How long until the tooth goes on my implant, and why the wait?

In most cases it is a few months, often shorter in the lower jaw. The wait allows bone to bond to the implant surface, a process called osseointegration. Loading the screw before that bond forms can loosen or lose the implant. A temporary solution can be planned meanwhile, and your check-ups decide the exact timing.
23

When can I eat normally after implant surgery?

Wait until the anaesthesia wears off, then start with warm, soft foods. For the first days avoid very hot, hard or spicy items and chew on the other side. Most patients return to a normal diet gradually once the area settles and sutures are removed. Straws and smoking are discouraged early because they can disturb healing.
24

My face swelled and aches after the implant. Is that normal?

Swelling, slight bruising and throbbing during the first two or three days are expected and usually fade. Cold packs, keeping your head raised and taking prescribed medication help. If swelling increases after day four, or you have fever, discharge, bad odour or severe ongoing pain, that is not expected. Our clinic is open around the clock, so call us and come in.
25

My tooth was pulled years ago. Can you tell if I have enough bone?

We measure it rather than guess. Alongside the examination, a three-dimensional scan shows bone height, width and distance to the nerve and sinus. Long-standing gaps often show bone loss, but that rarely rules implants out. Where bone is thin, grafting or sinus elevation can prepare the site, and we explain your options afterwards.
26

They said bone powder will be added. What does a graft actually do?

A graft is bone-building material used to rebuild missing volume so an implant has solid support. It may come from your own bone or from biocompatible ready-made materials. It acts as a scaffold that your own cells gradually turn into real bone, so healing can take a little longer. Sometimes graft and implant are done in one session.
27

They said my sinus is too close in the upper back. Can I still have an implant?

Usually yes. When upper back teeth are missing the sinus can expand downwards, leaving less bone height. A procedure gently lifts the sinus floor and places graft material underneath to create room for the implant. Depending on remaining bone this is done in the same session or separately, guided by your scan and general health.
28

Can an implant and tooth be placed the same day as the extraction?

Sometimes, but not for everyone. If the socket is free of infection, the bone walls are intact and the implant achieves good initial stability, placement can be done at the same visit. In the smile zone a temporary tooth kept out of heavy biting is often fitted, with the final crown made later. Infection or bone loss makes waiting safer.
29

How long do implants last? Are they permanent once placed?

Implants are designed as long-term solutions, though no treatment can be promised for life. What matters most is the health of the surrounding gum and bone. Daily brushing, interdental cleaning and regular check-ups with professional cleaning support longevity. Smoking, uncontrolled diabetes, clenching and neglected maintenance raise the risk, and the crown itself may need renewal.
30

Do I brush an implant like a normal tooth, or is extra care needed?

Yes, brush it twice daily with a soft brush and paste, but do not stop there. Implants cannot decay, yet the gum around them is more sensitive to inflammation, so cleaning between teeth matters. Use floss, interdental brushes or a water flosser daily, avoid scraping with hard tools, and keep regular check-up and cleaning appointments.

From Our Blog

✦ Our Brands
Straumann
Nobel Biocare
Astra Tech
Medentika
Bredent SKY
Straumann
Nobel Biocare
Astra Tech
Medentika
Bredent SKY
✦ Contact
Get in touch

Antalya Muratpaşa our central clinic

Sair Adem Dede St. No:31, 07030 Muratpasa / Antalya, Türkiye

Open in Google Maps