




























Patient Reviews 4.9/5 10.000+ Happy Patients 37 Countries

Children's Dentist in Antalya — Paediatric Dentistry

✦ Tedaviler

Children's Dentist in Antalya — Paediatric Dentistry

Paediatric dentistry in Muratpasa, Antalya: milk tooth treatment, preventive care, fissure sealants and fluoride in a child-friendly setting.

✦ Our Patients

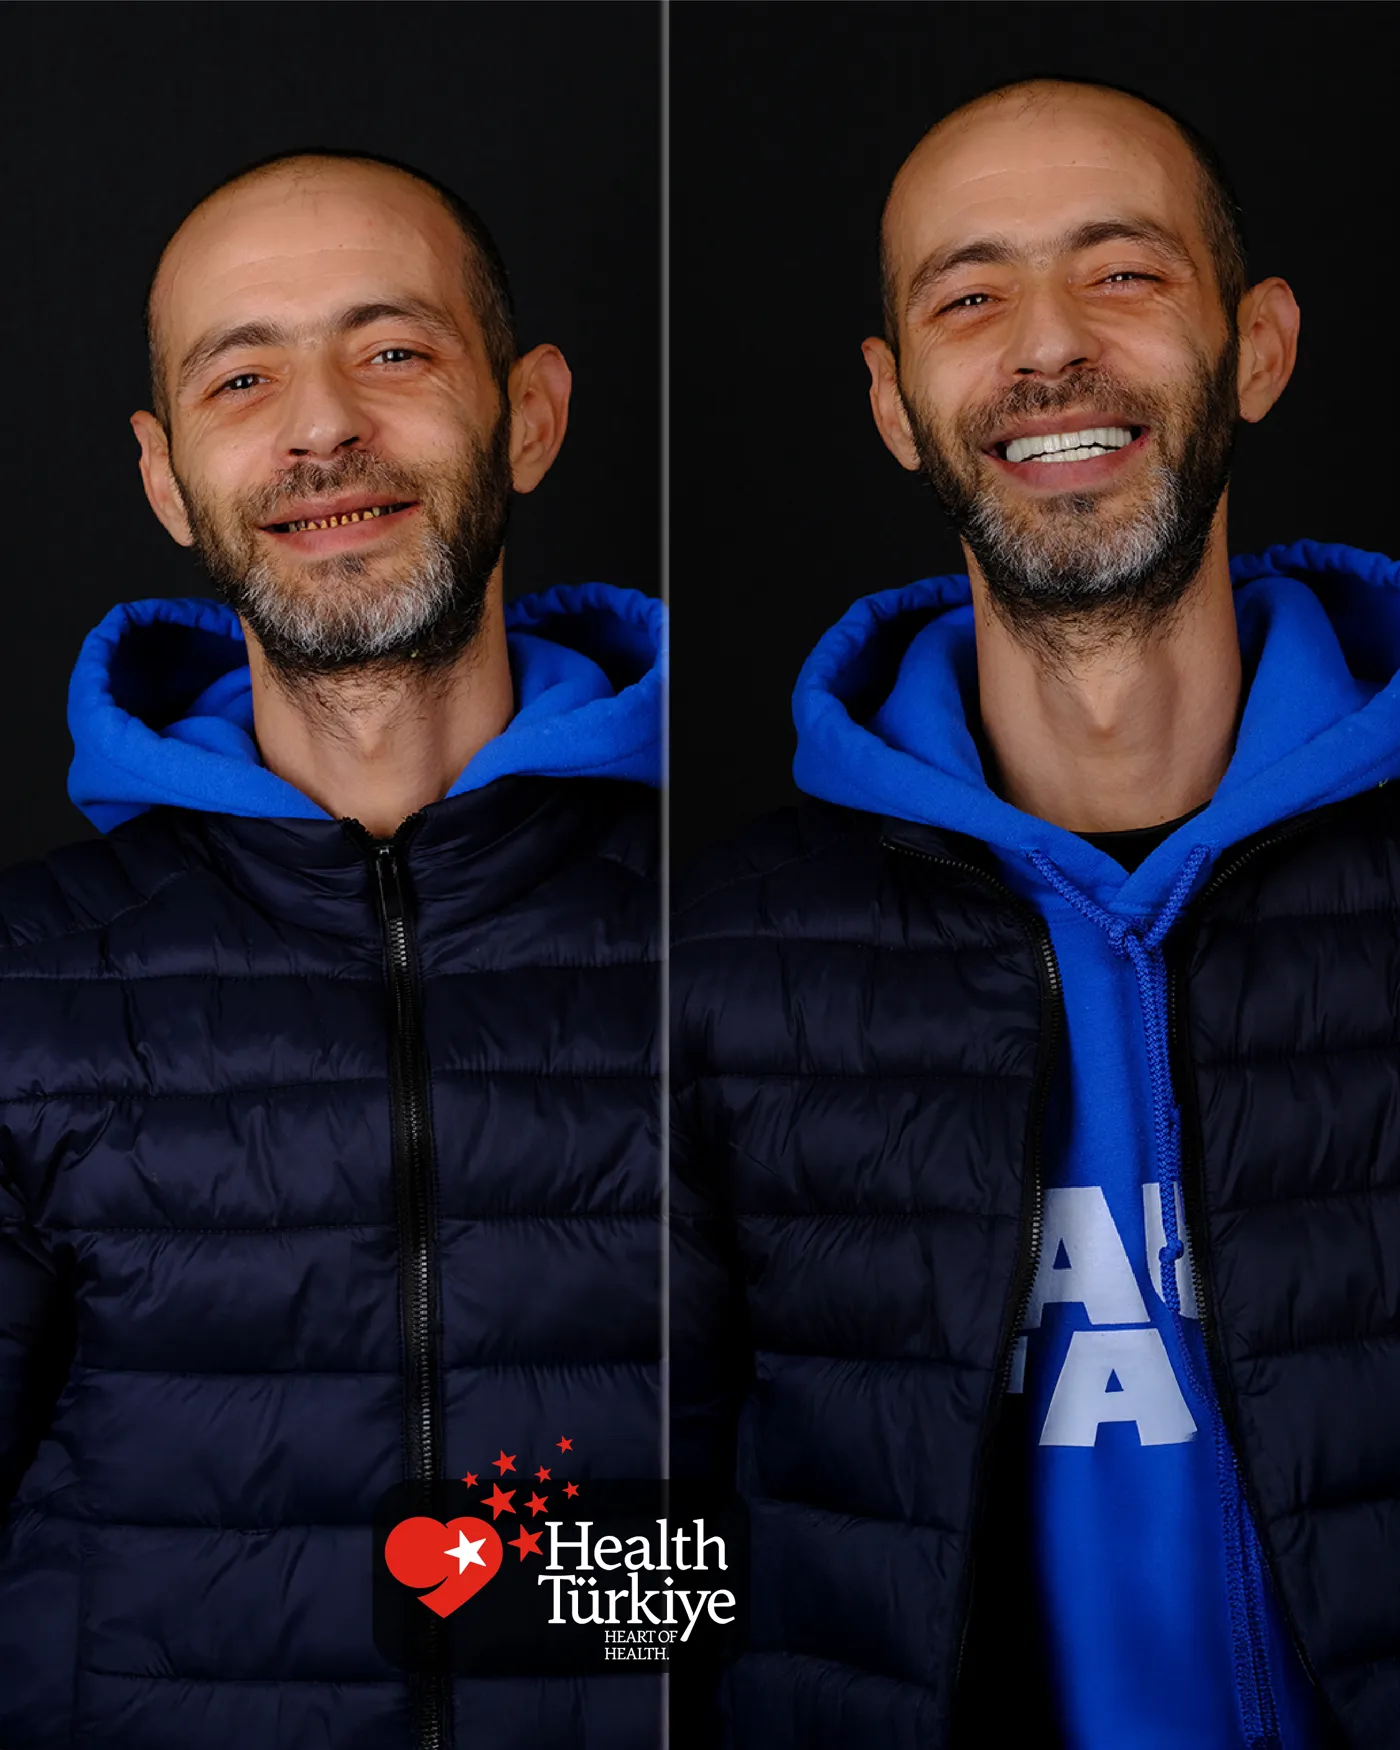
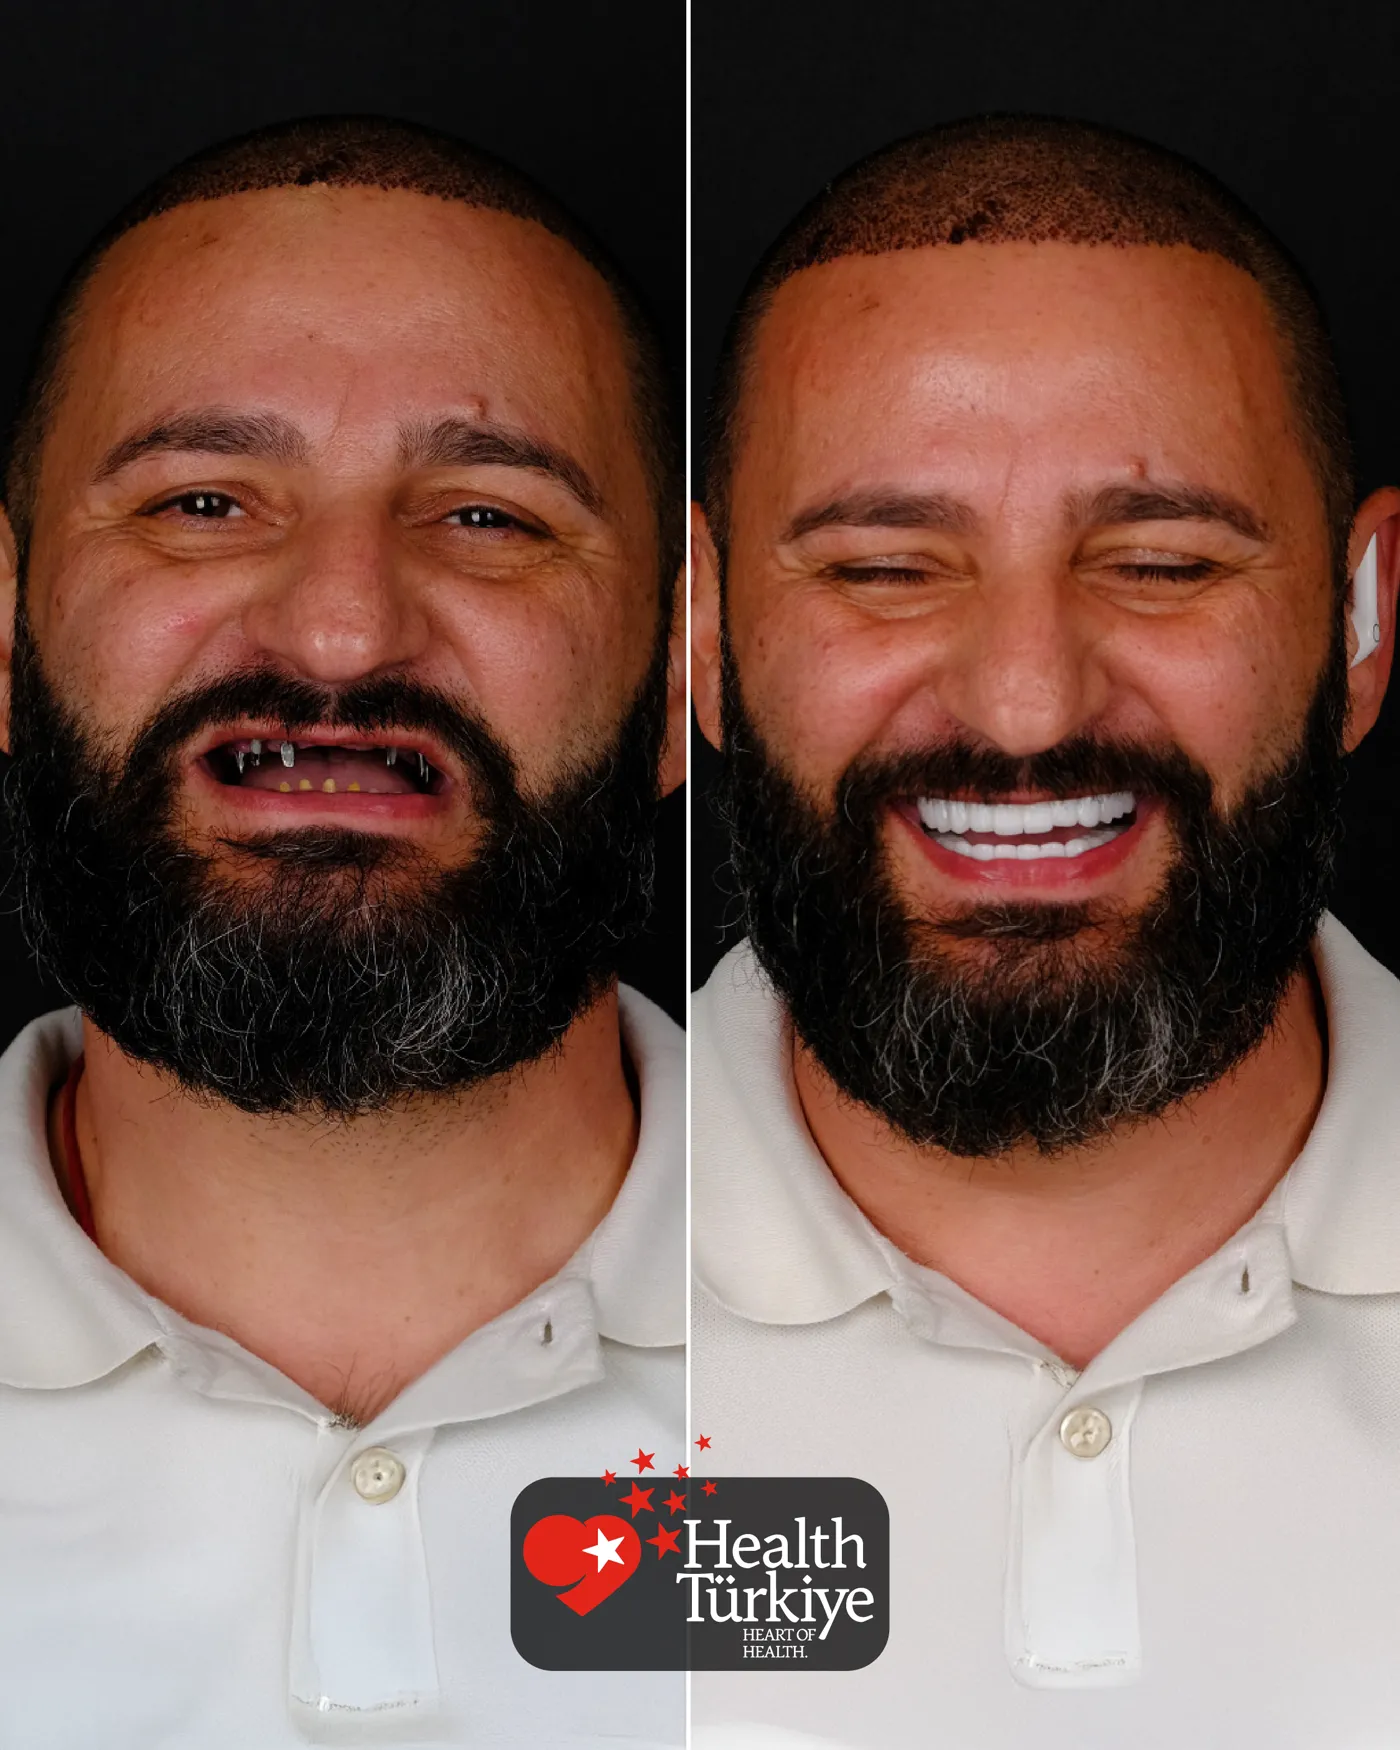
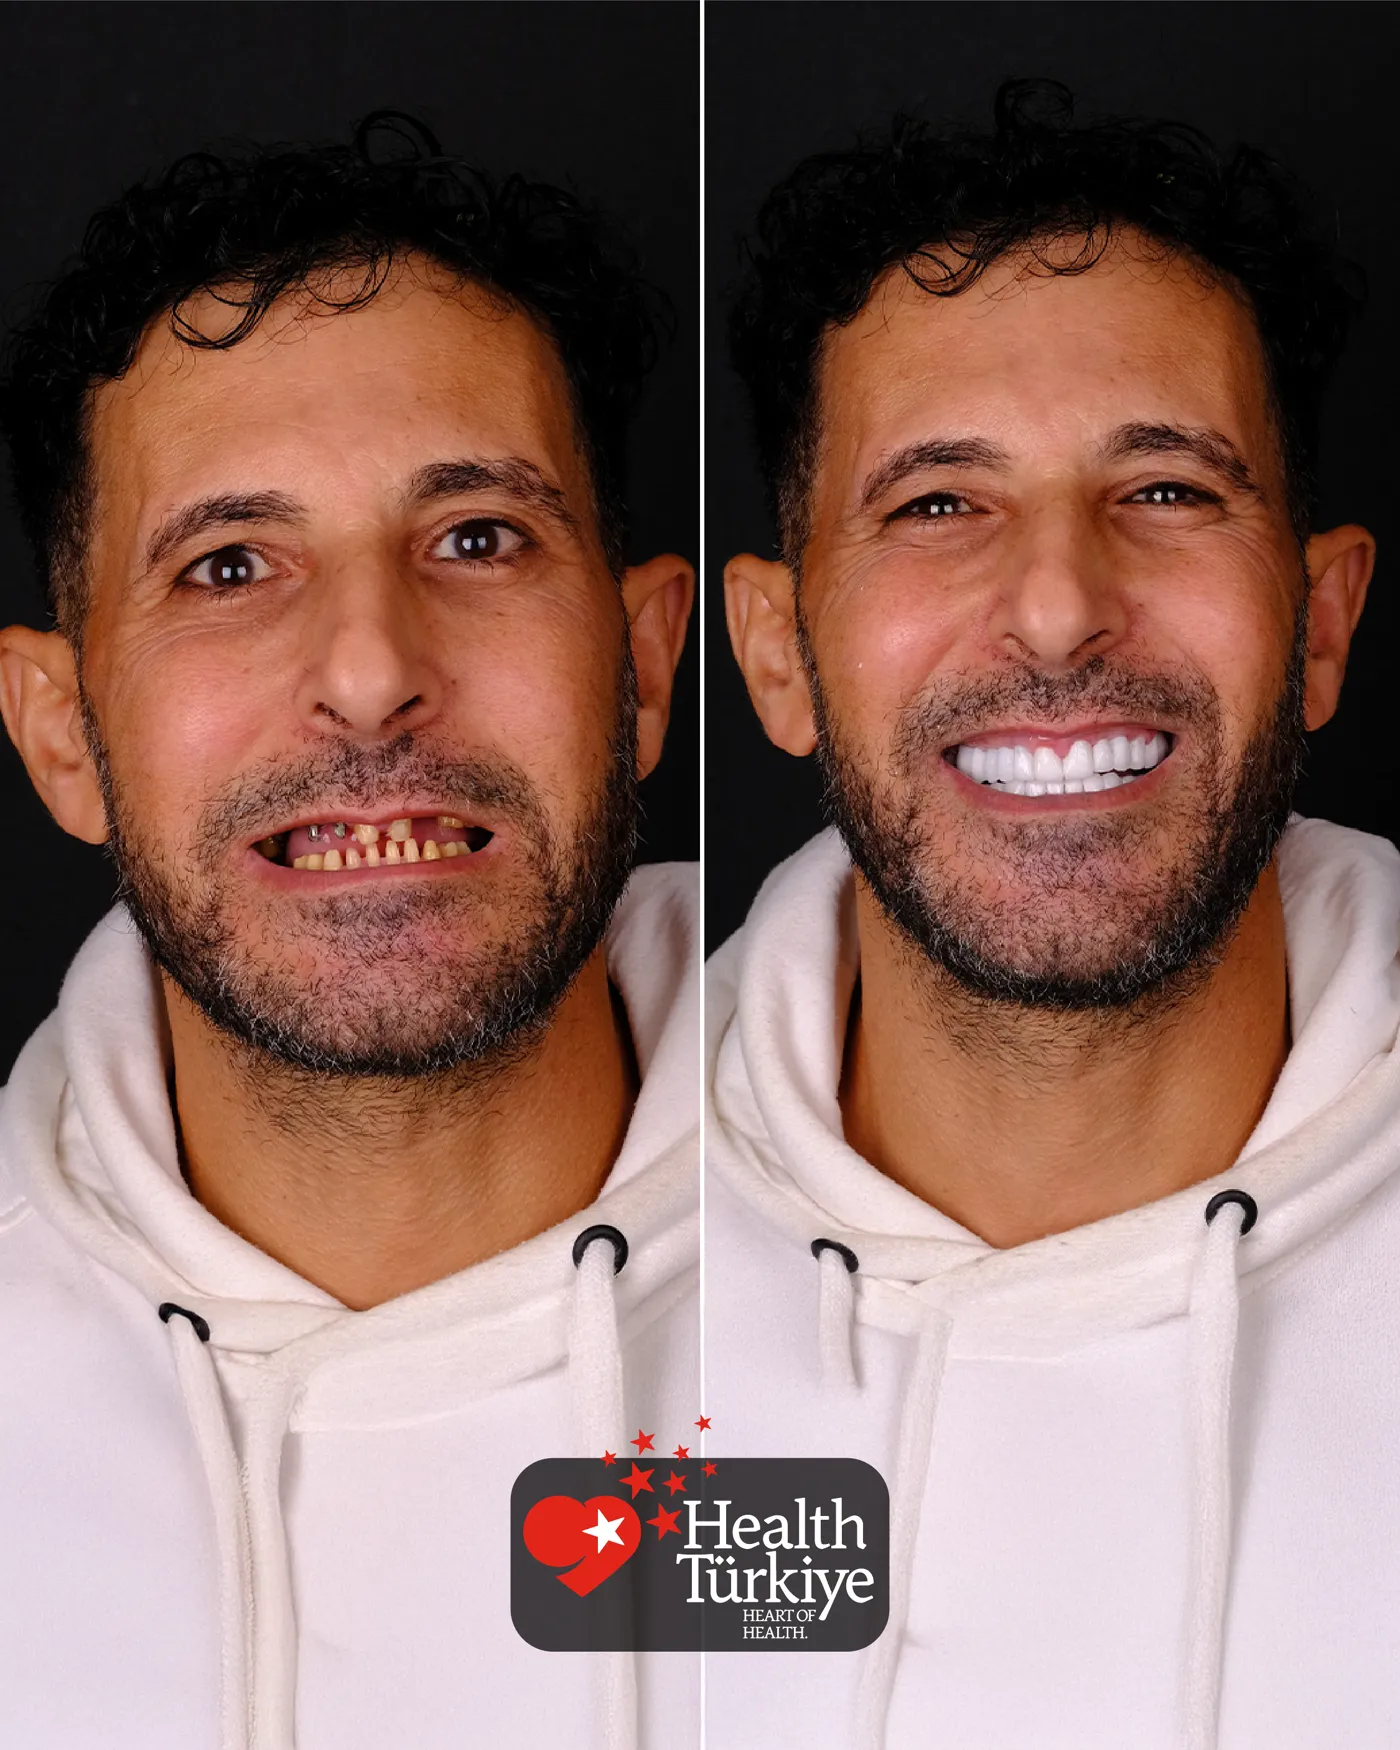
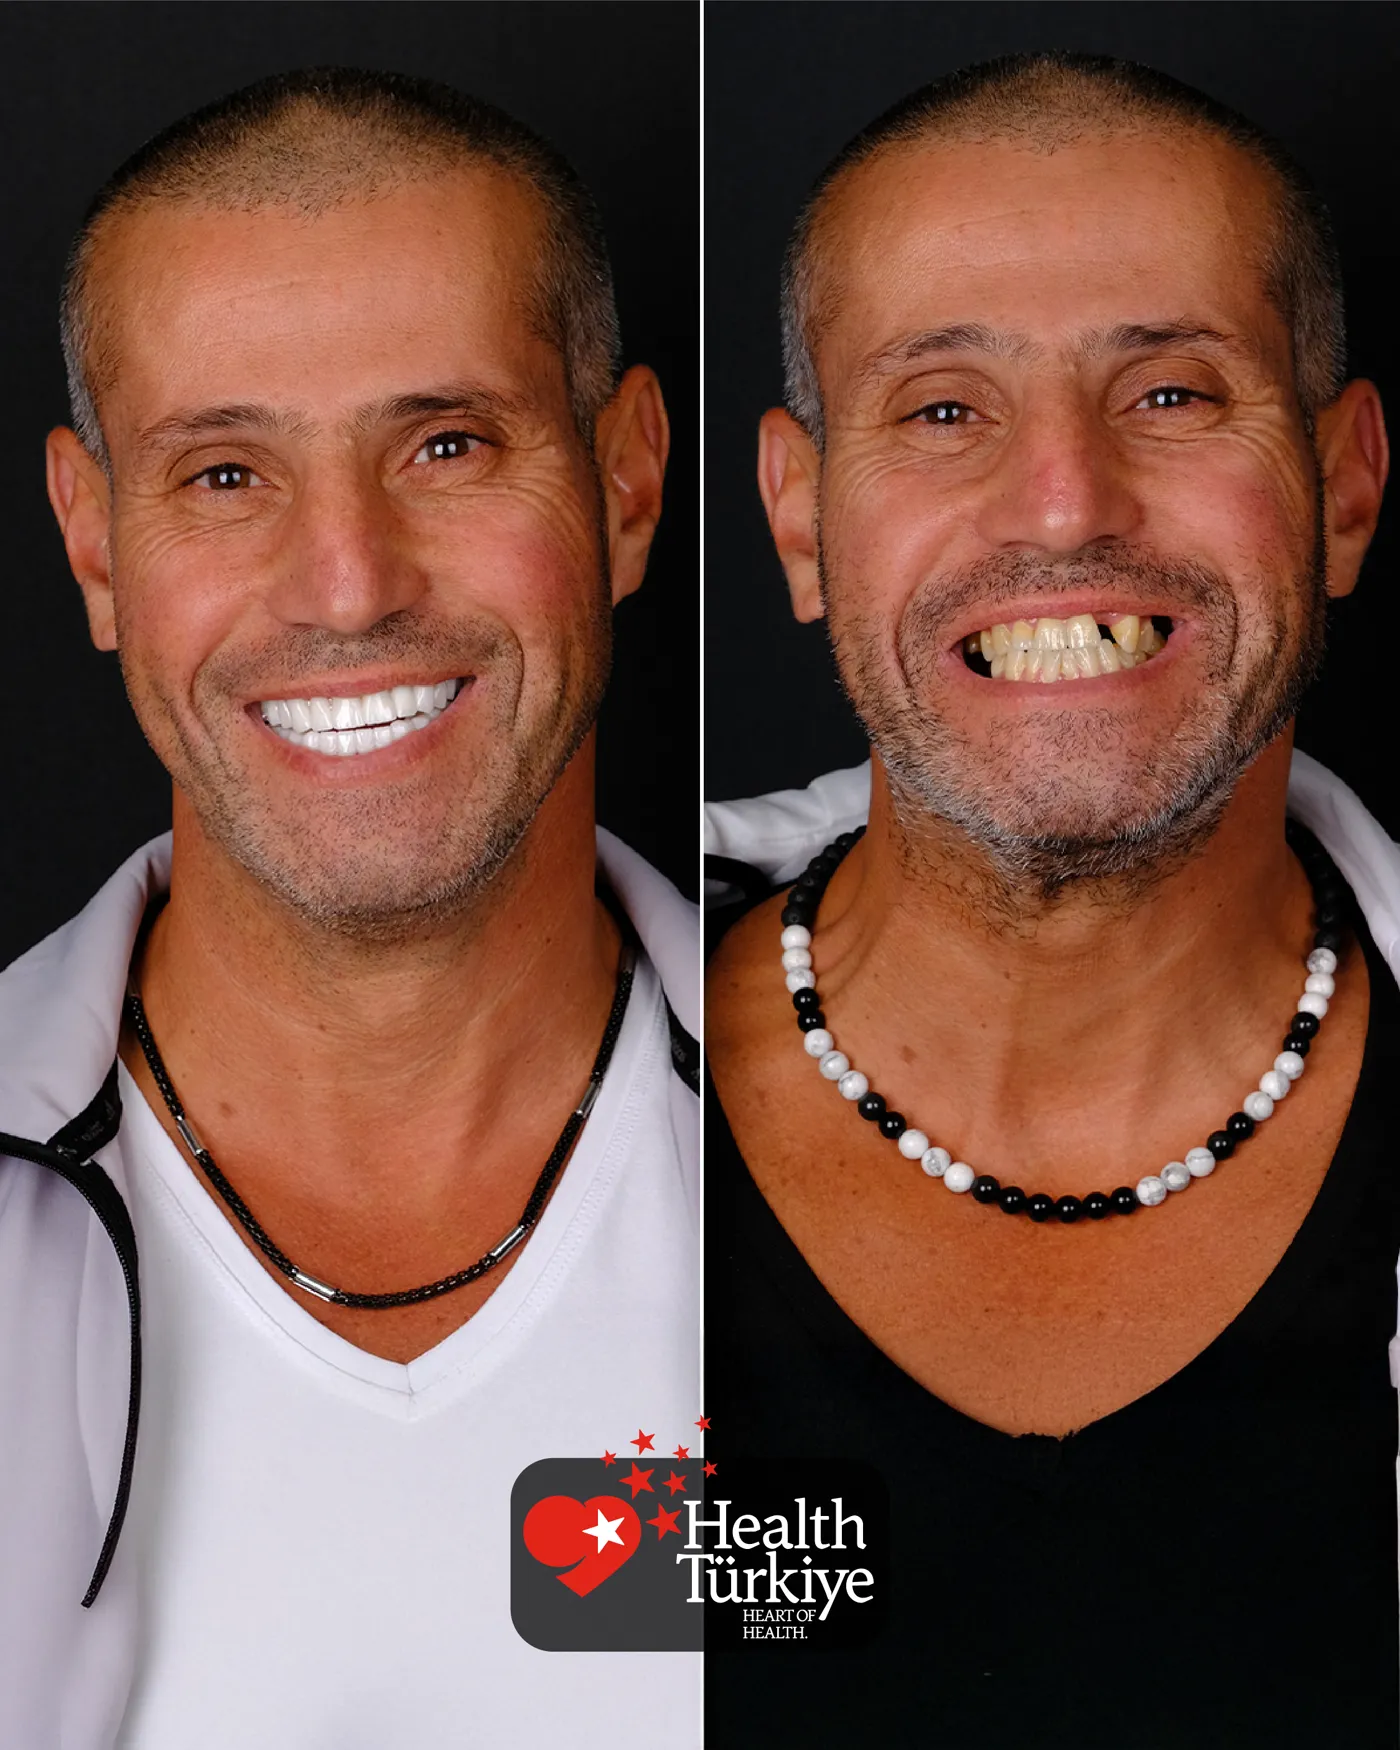
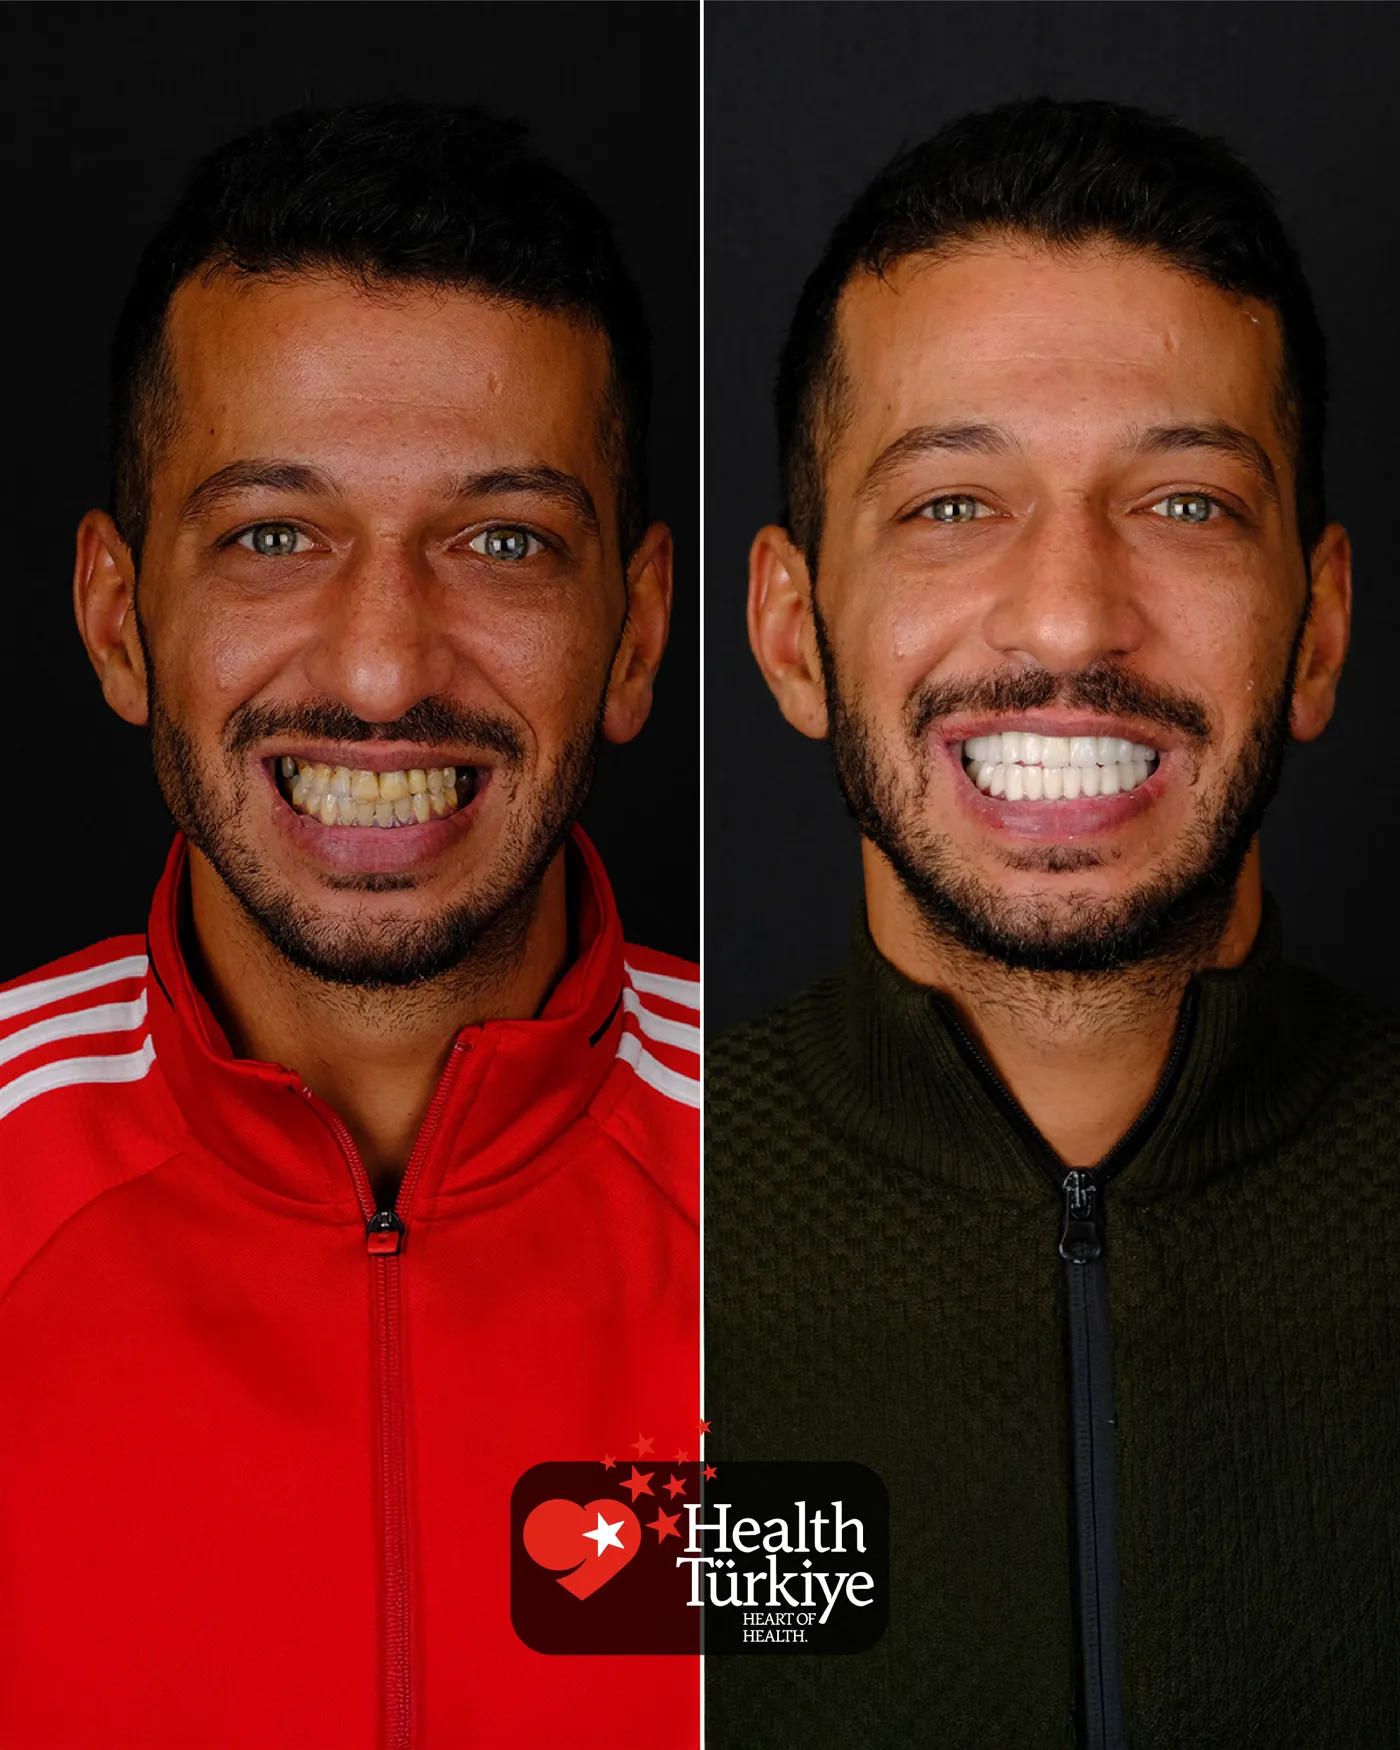
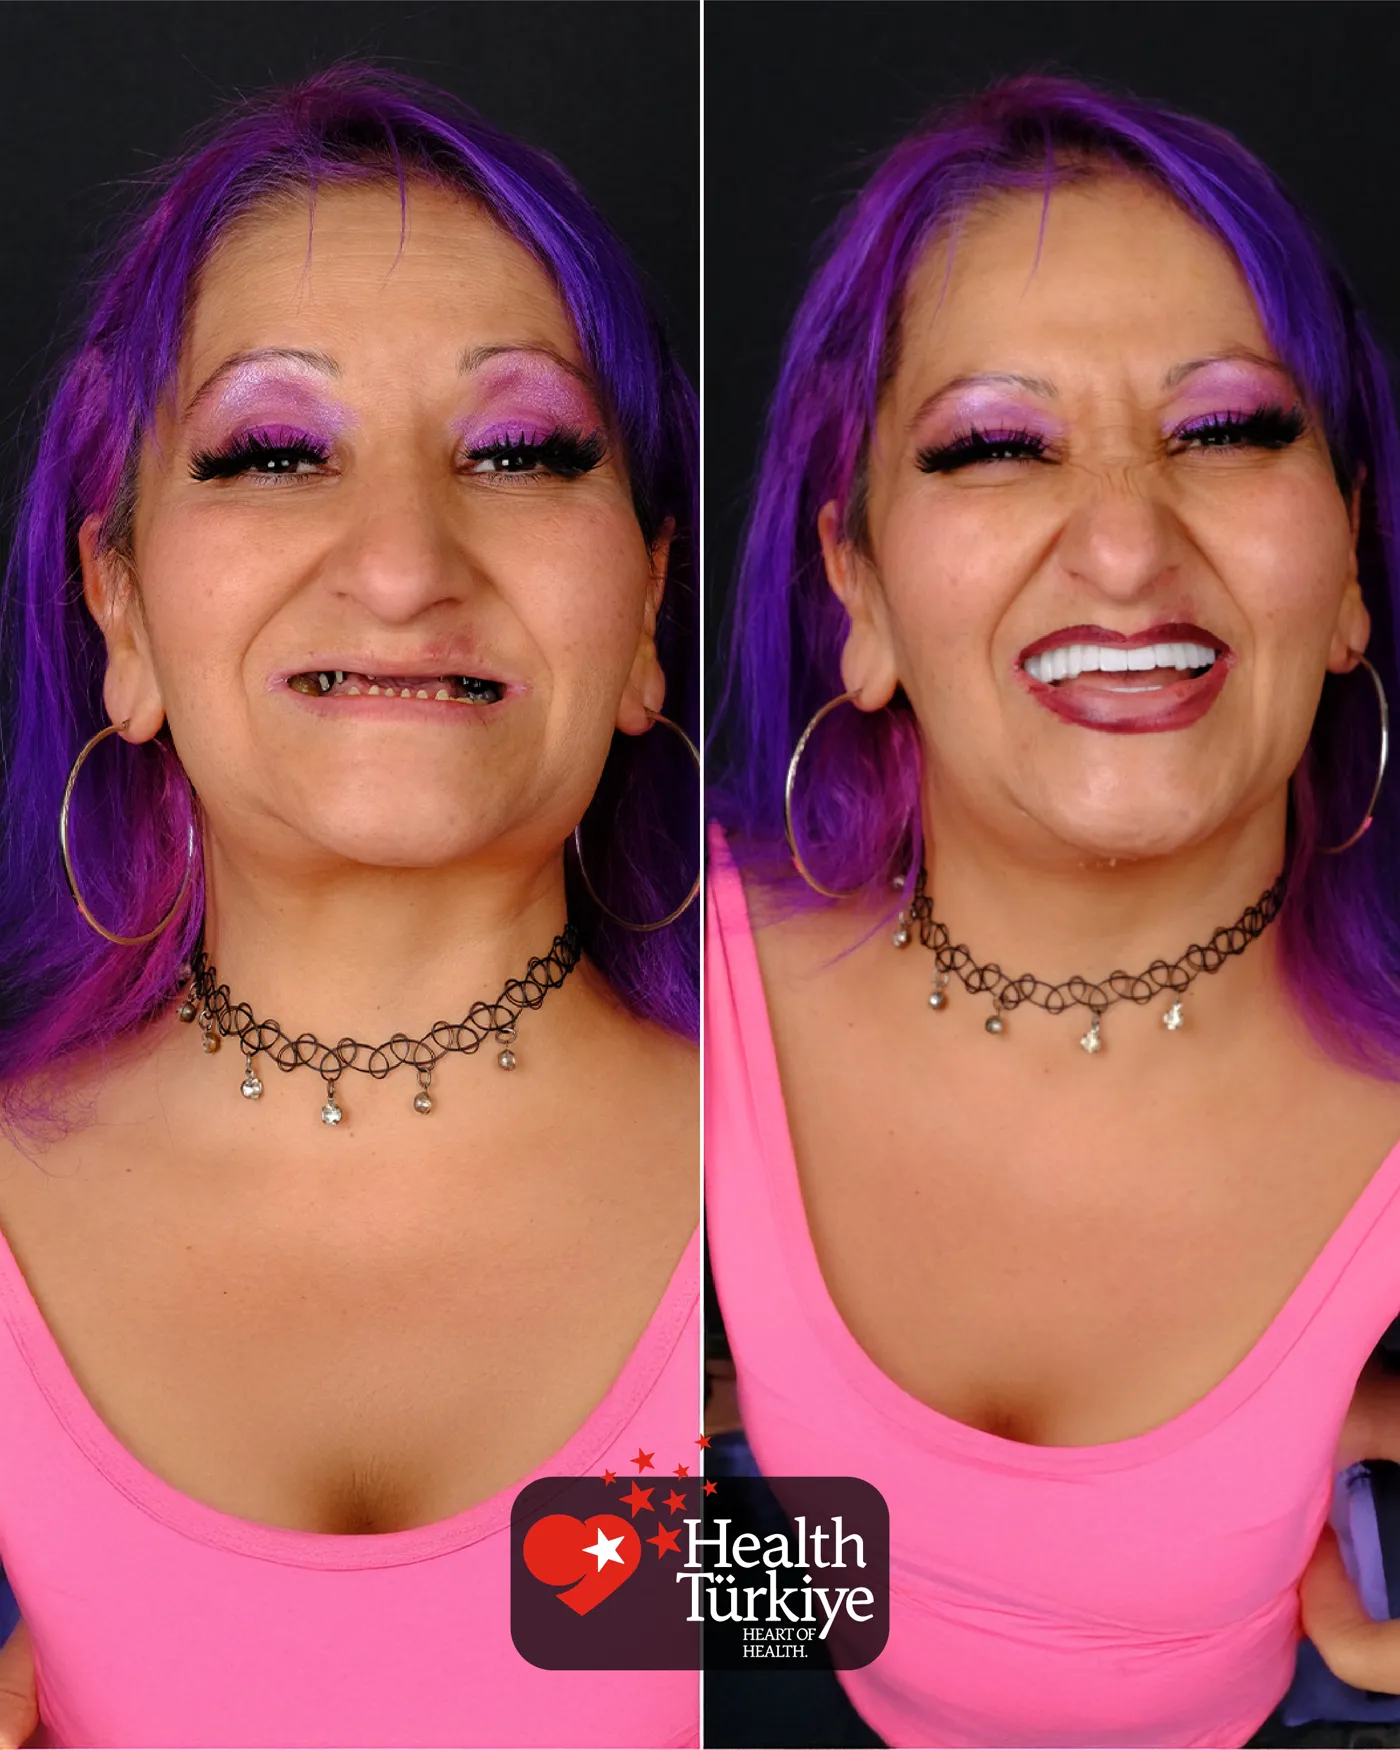
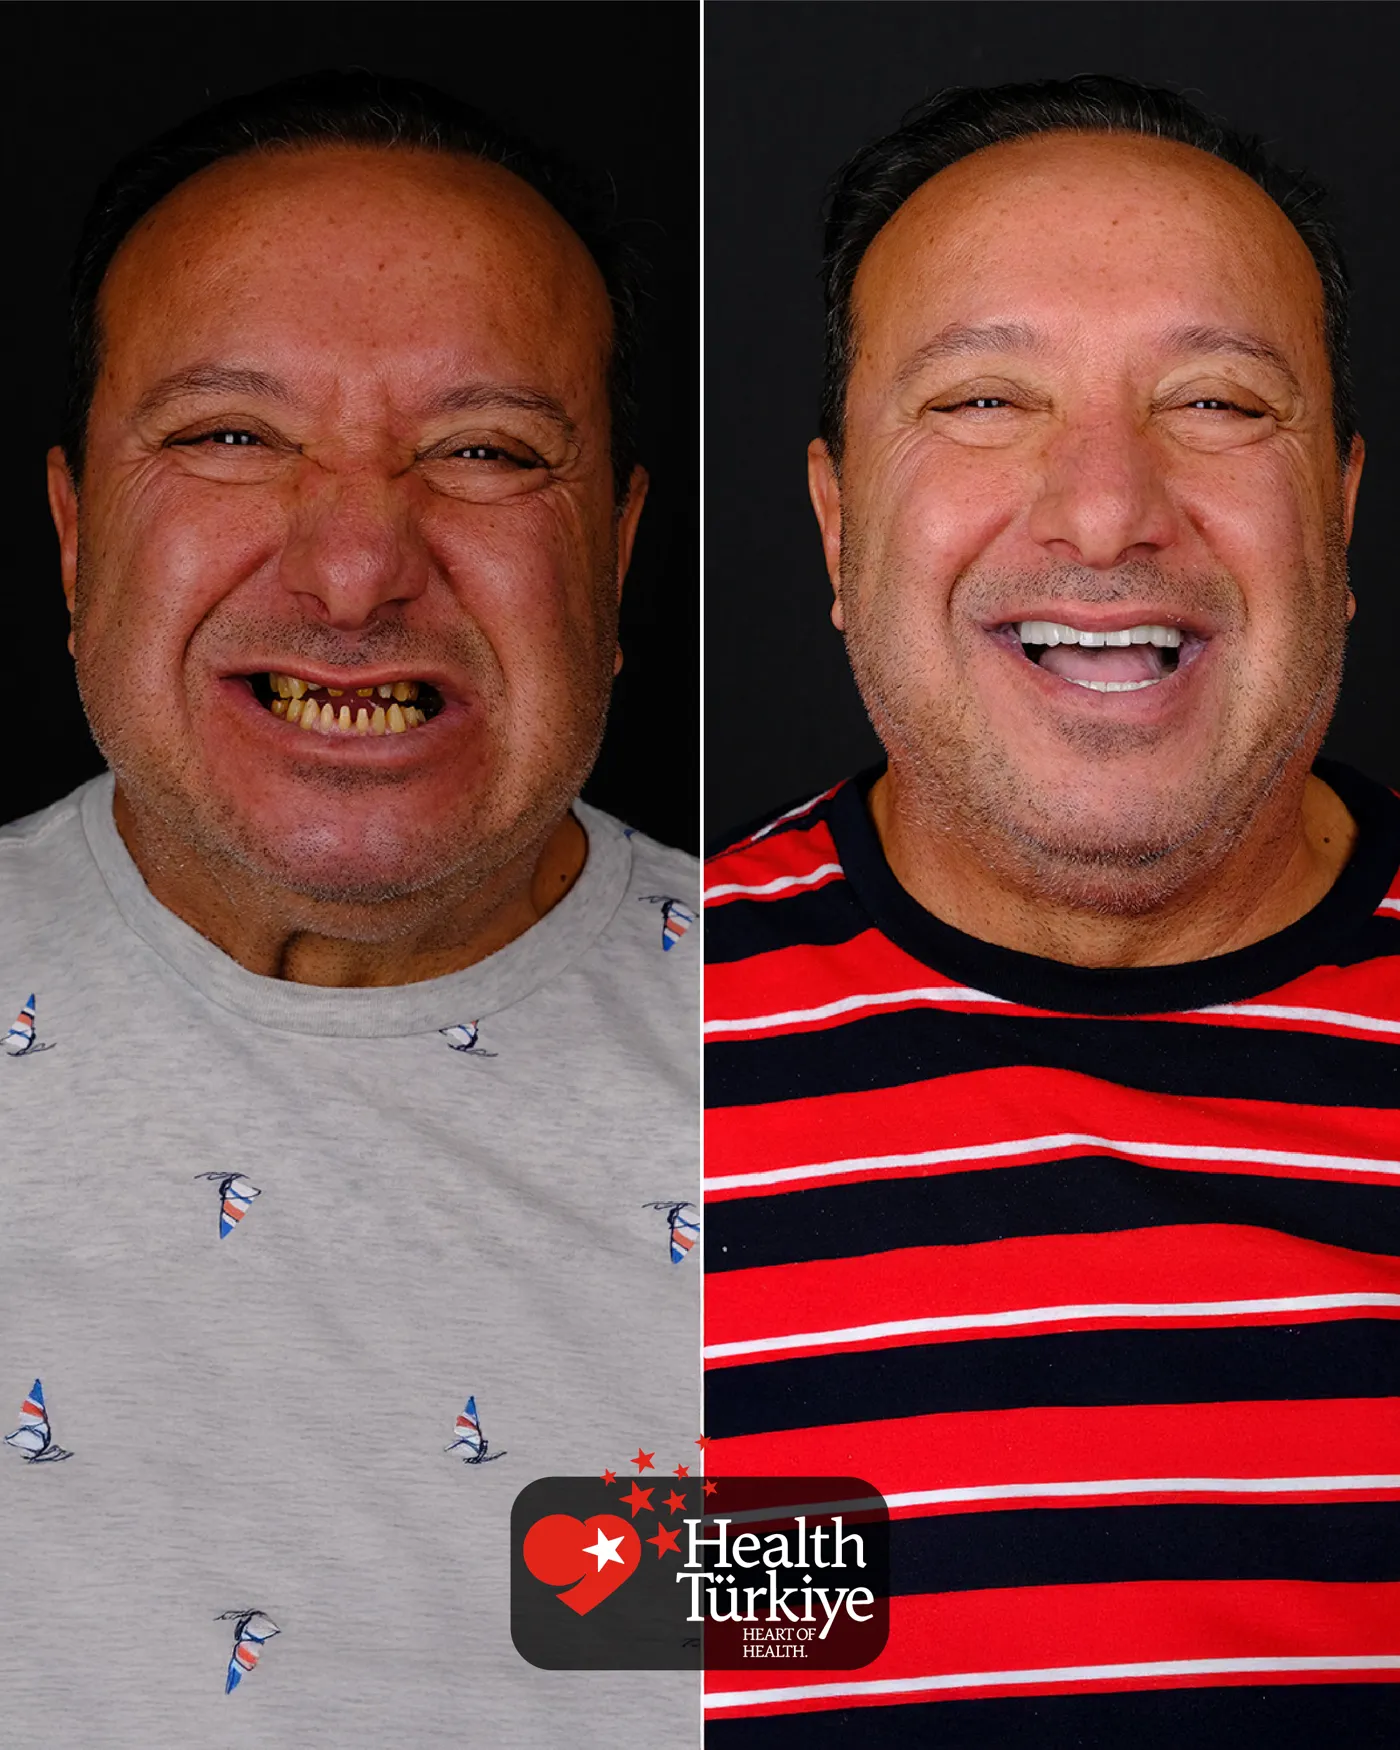
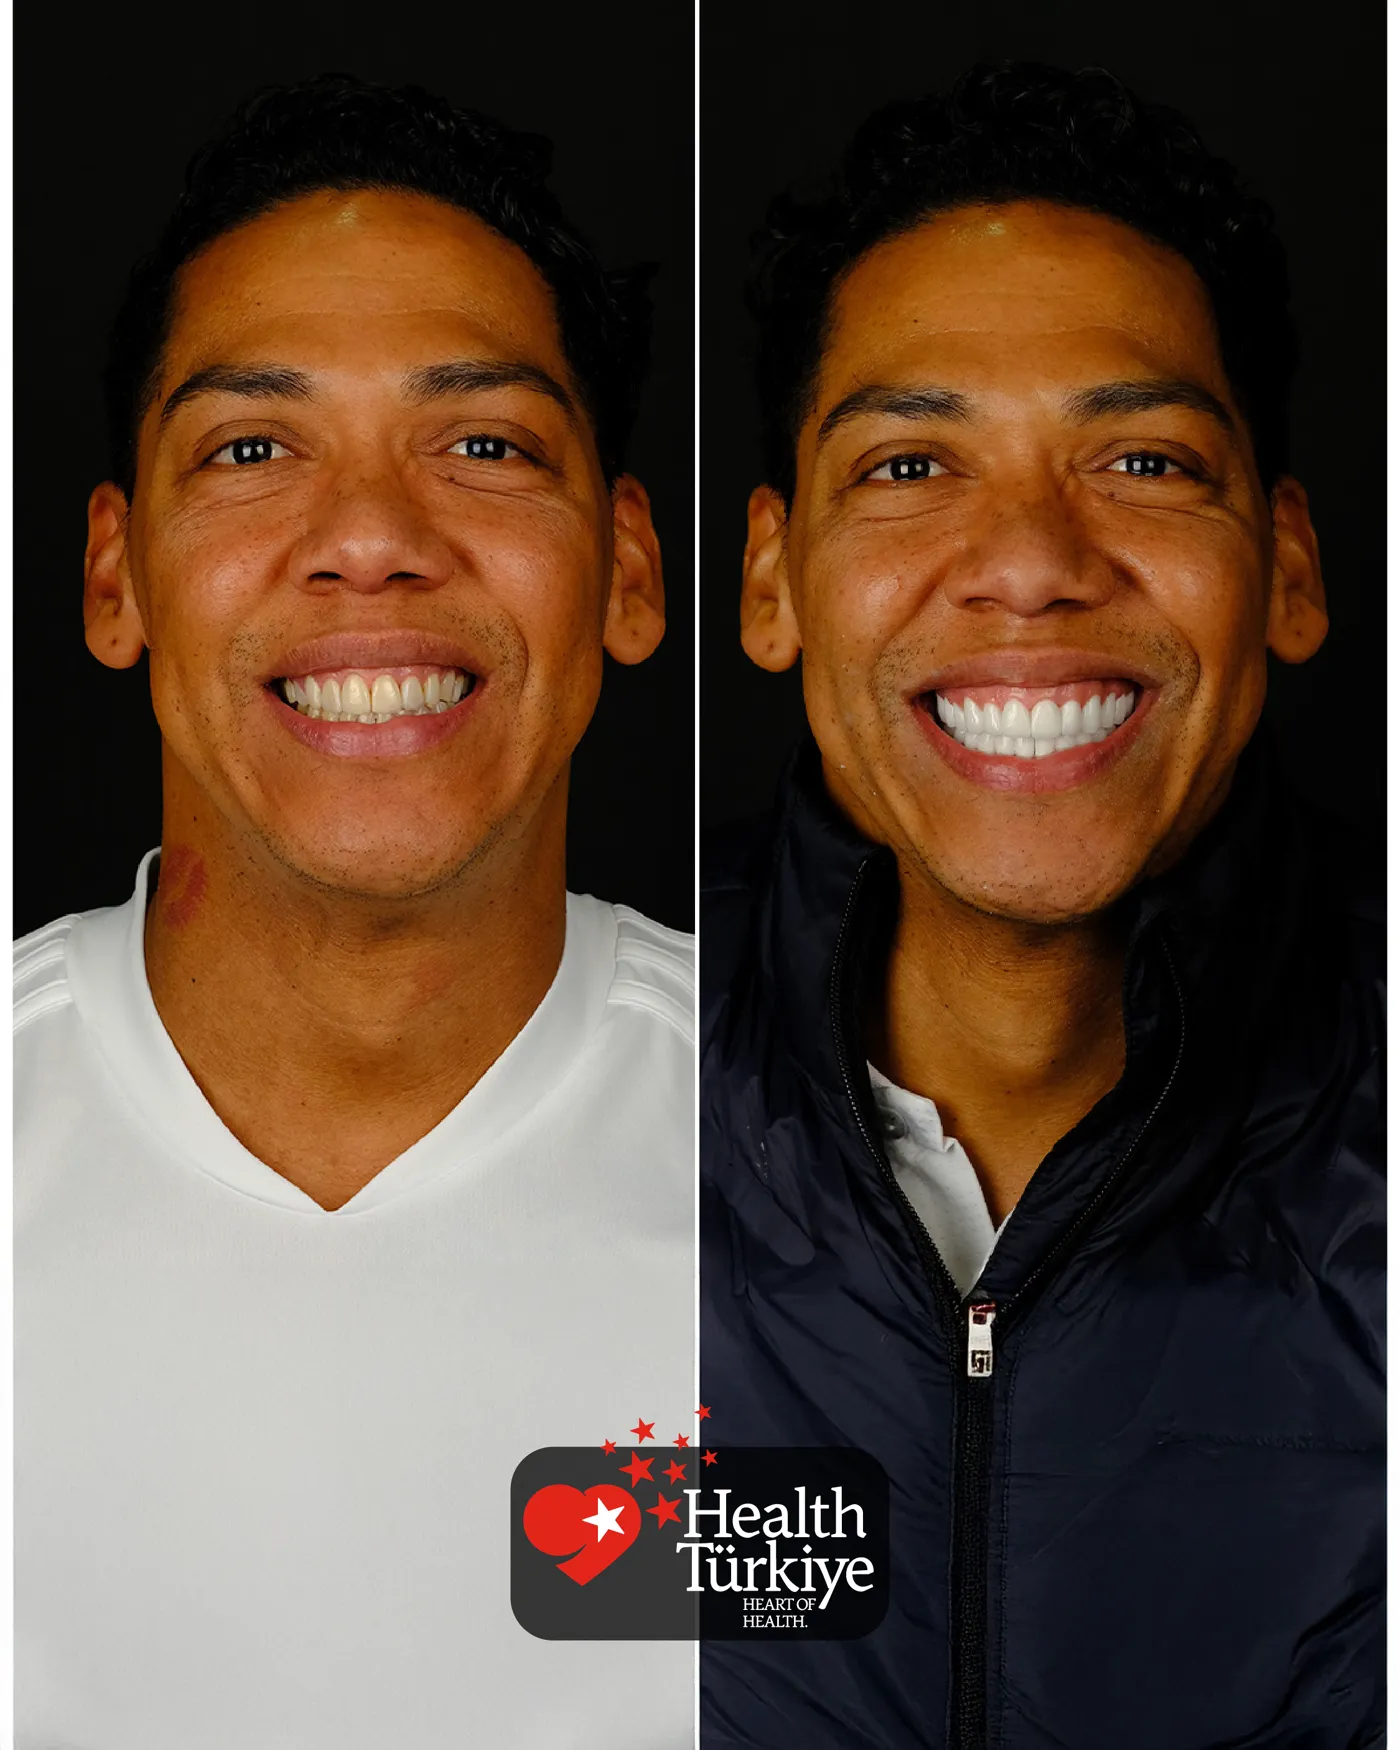
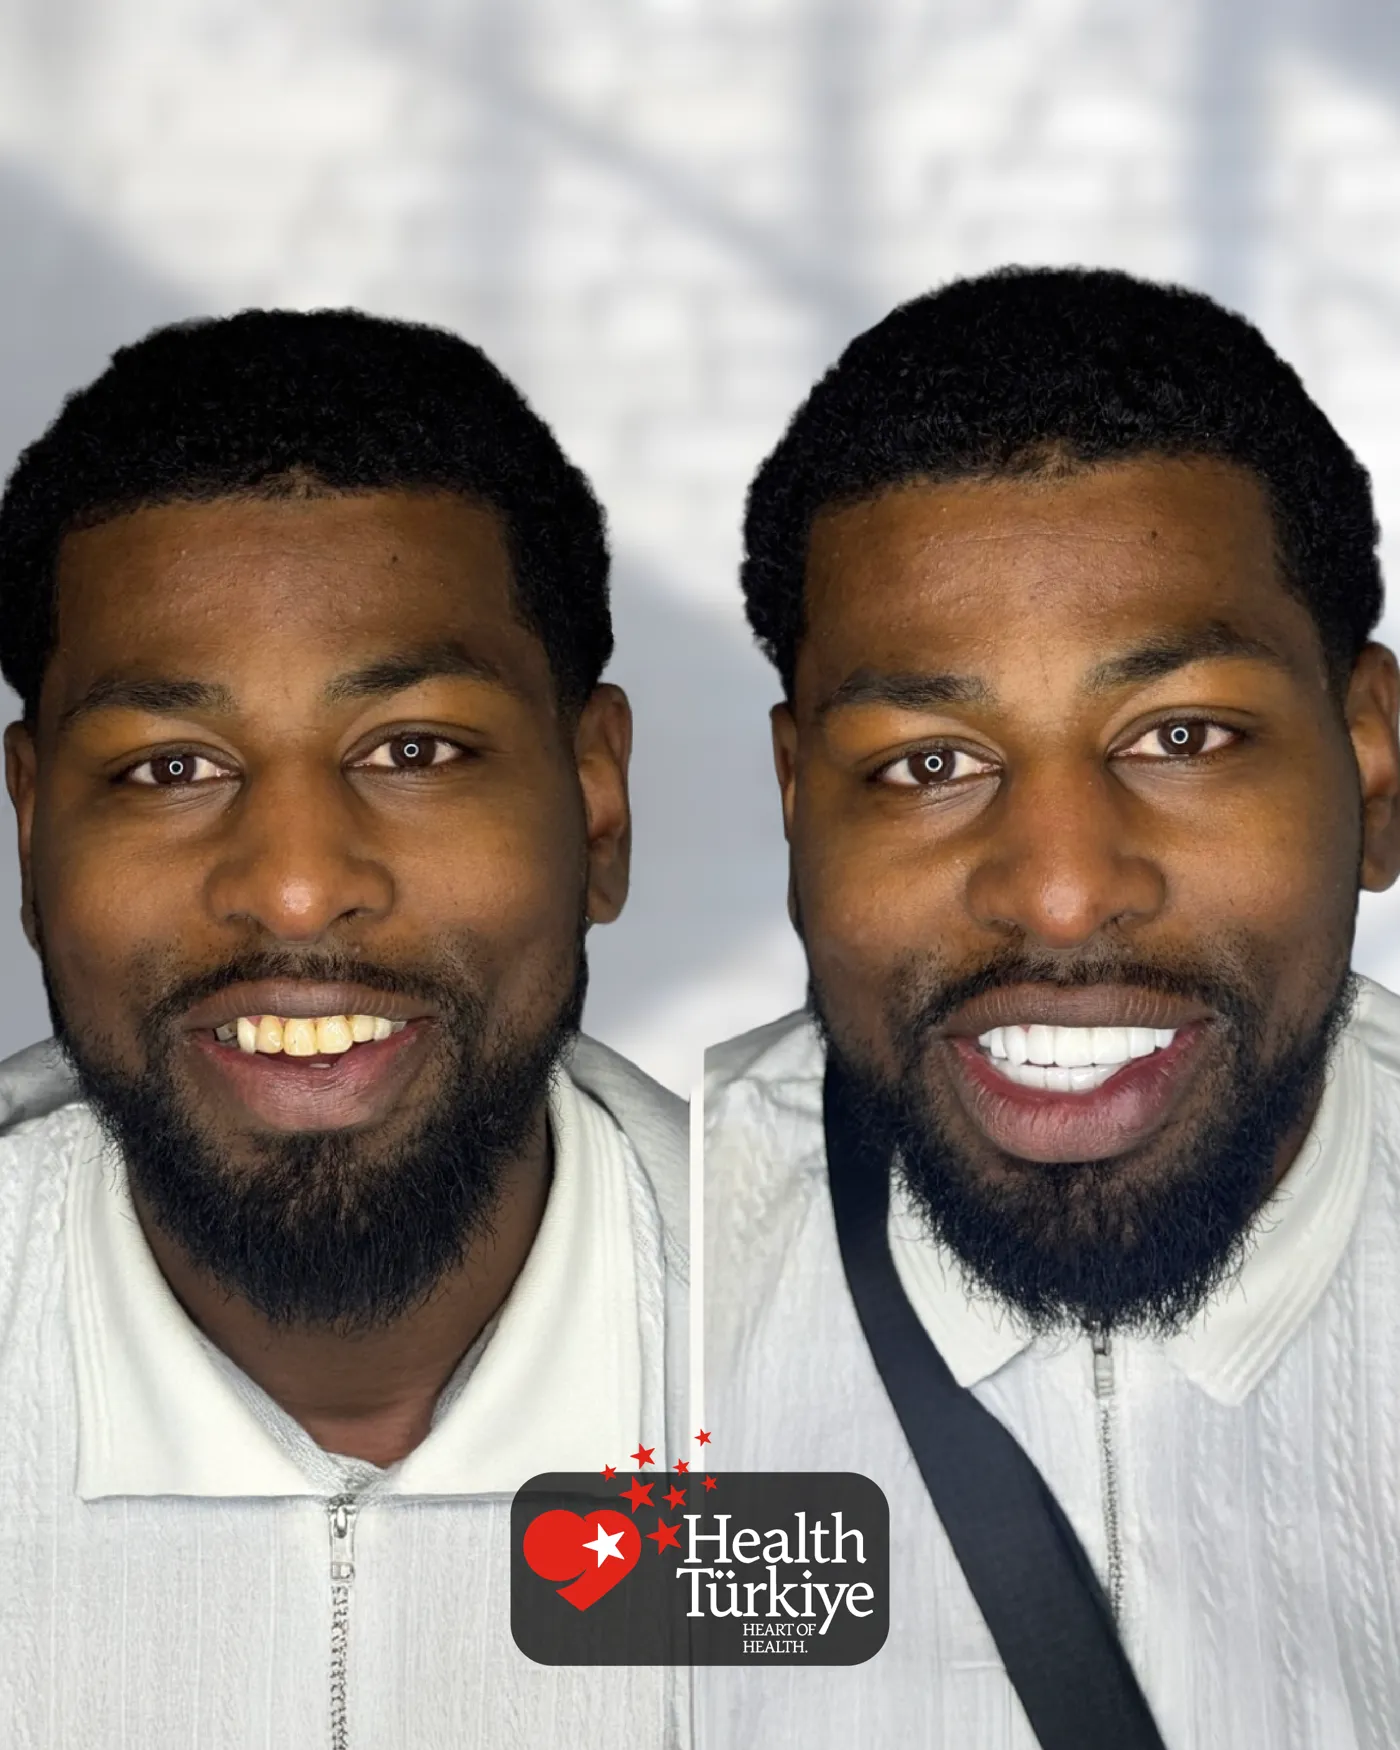
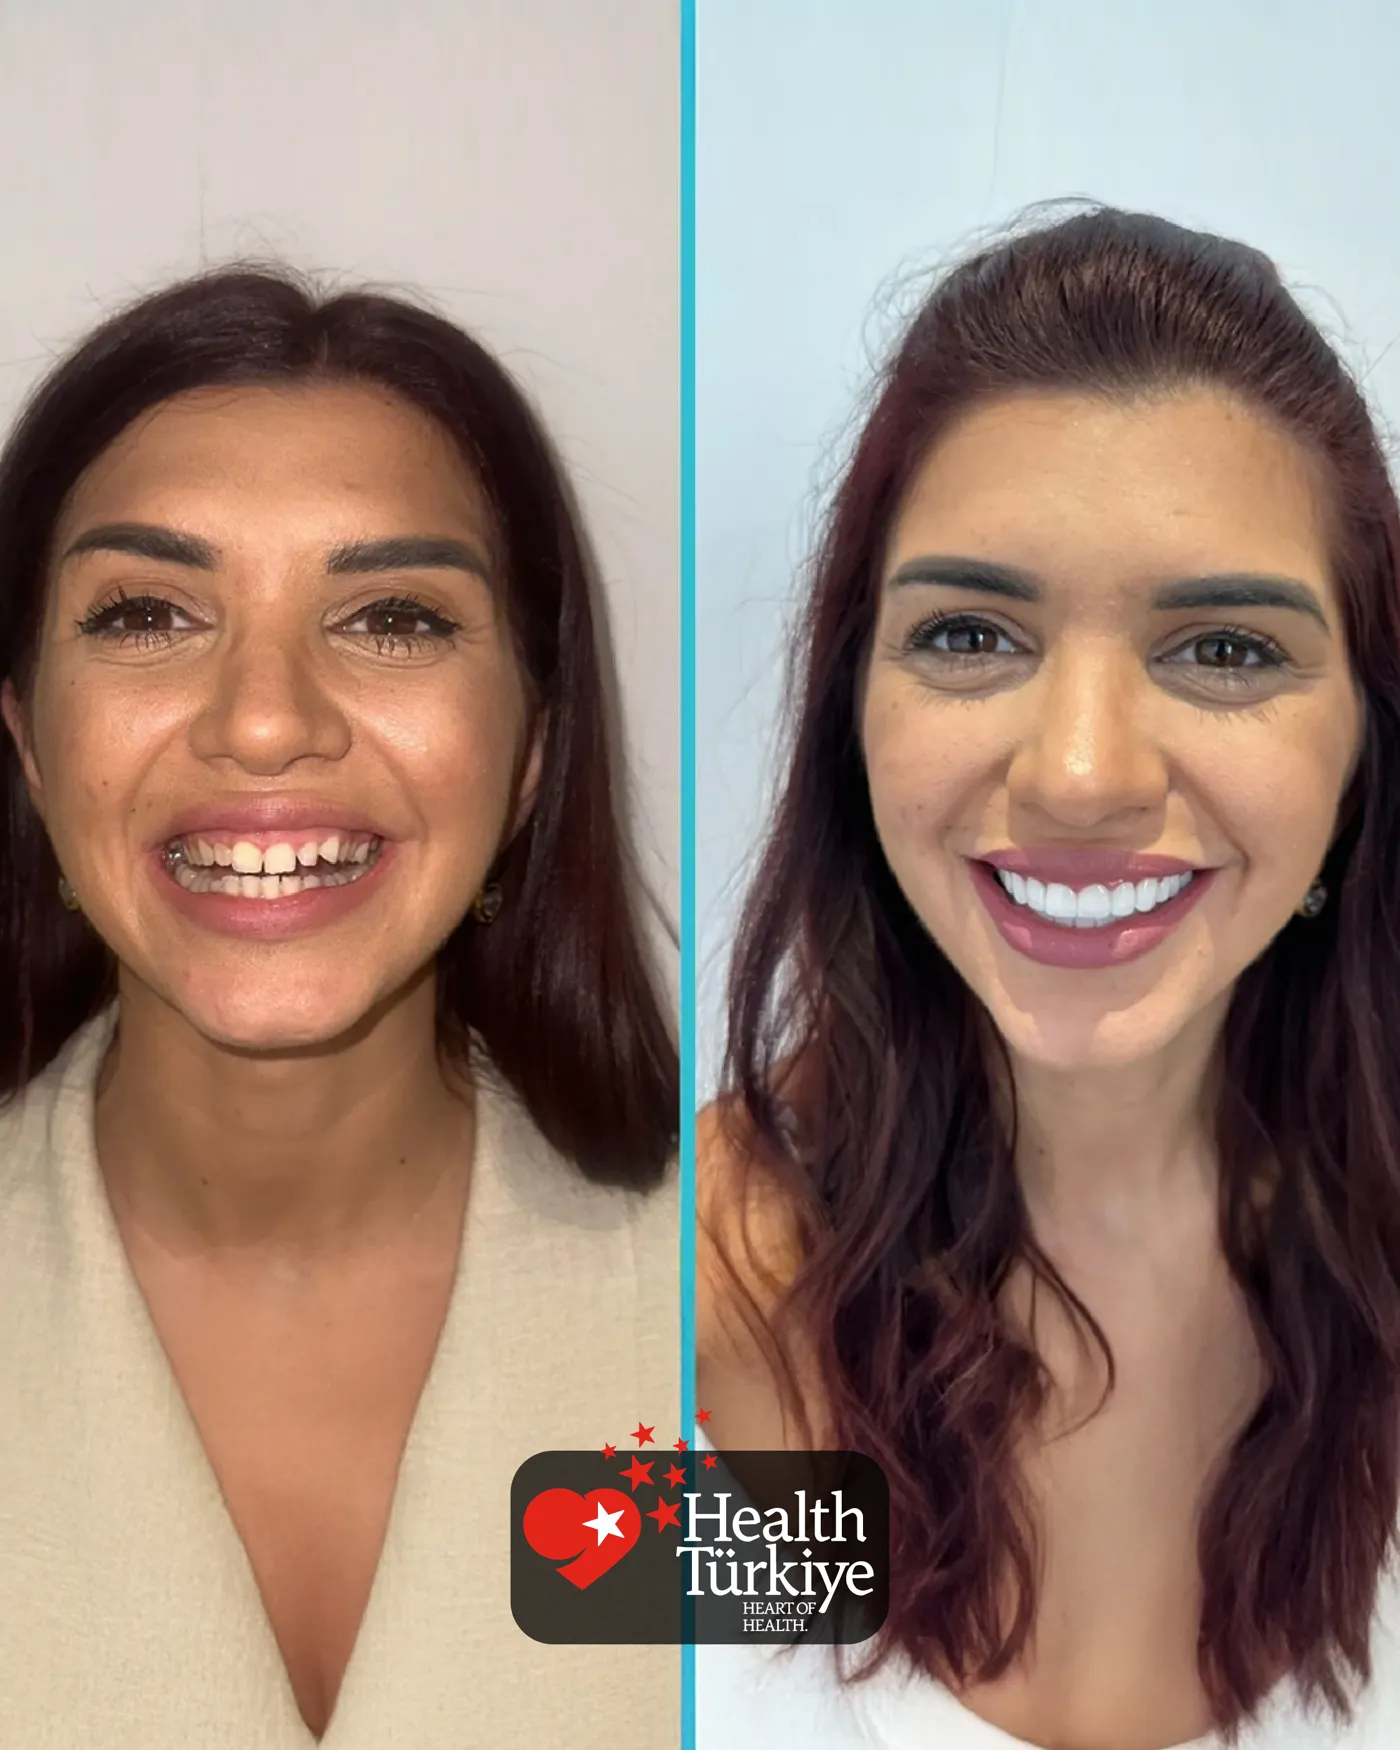
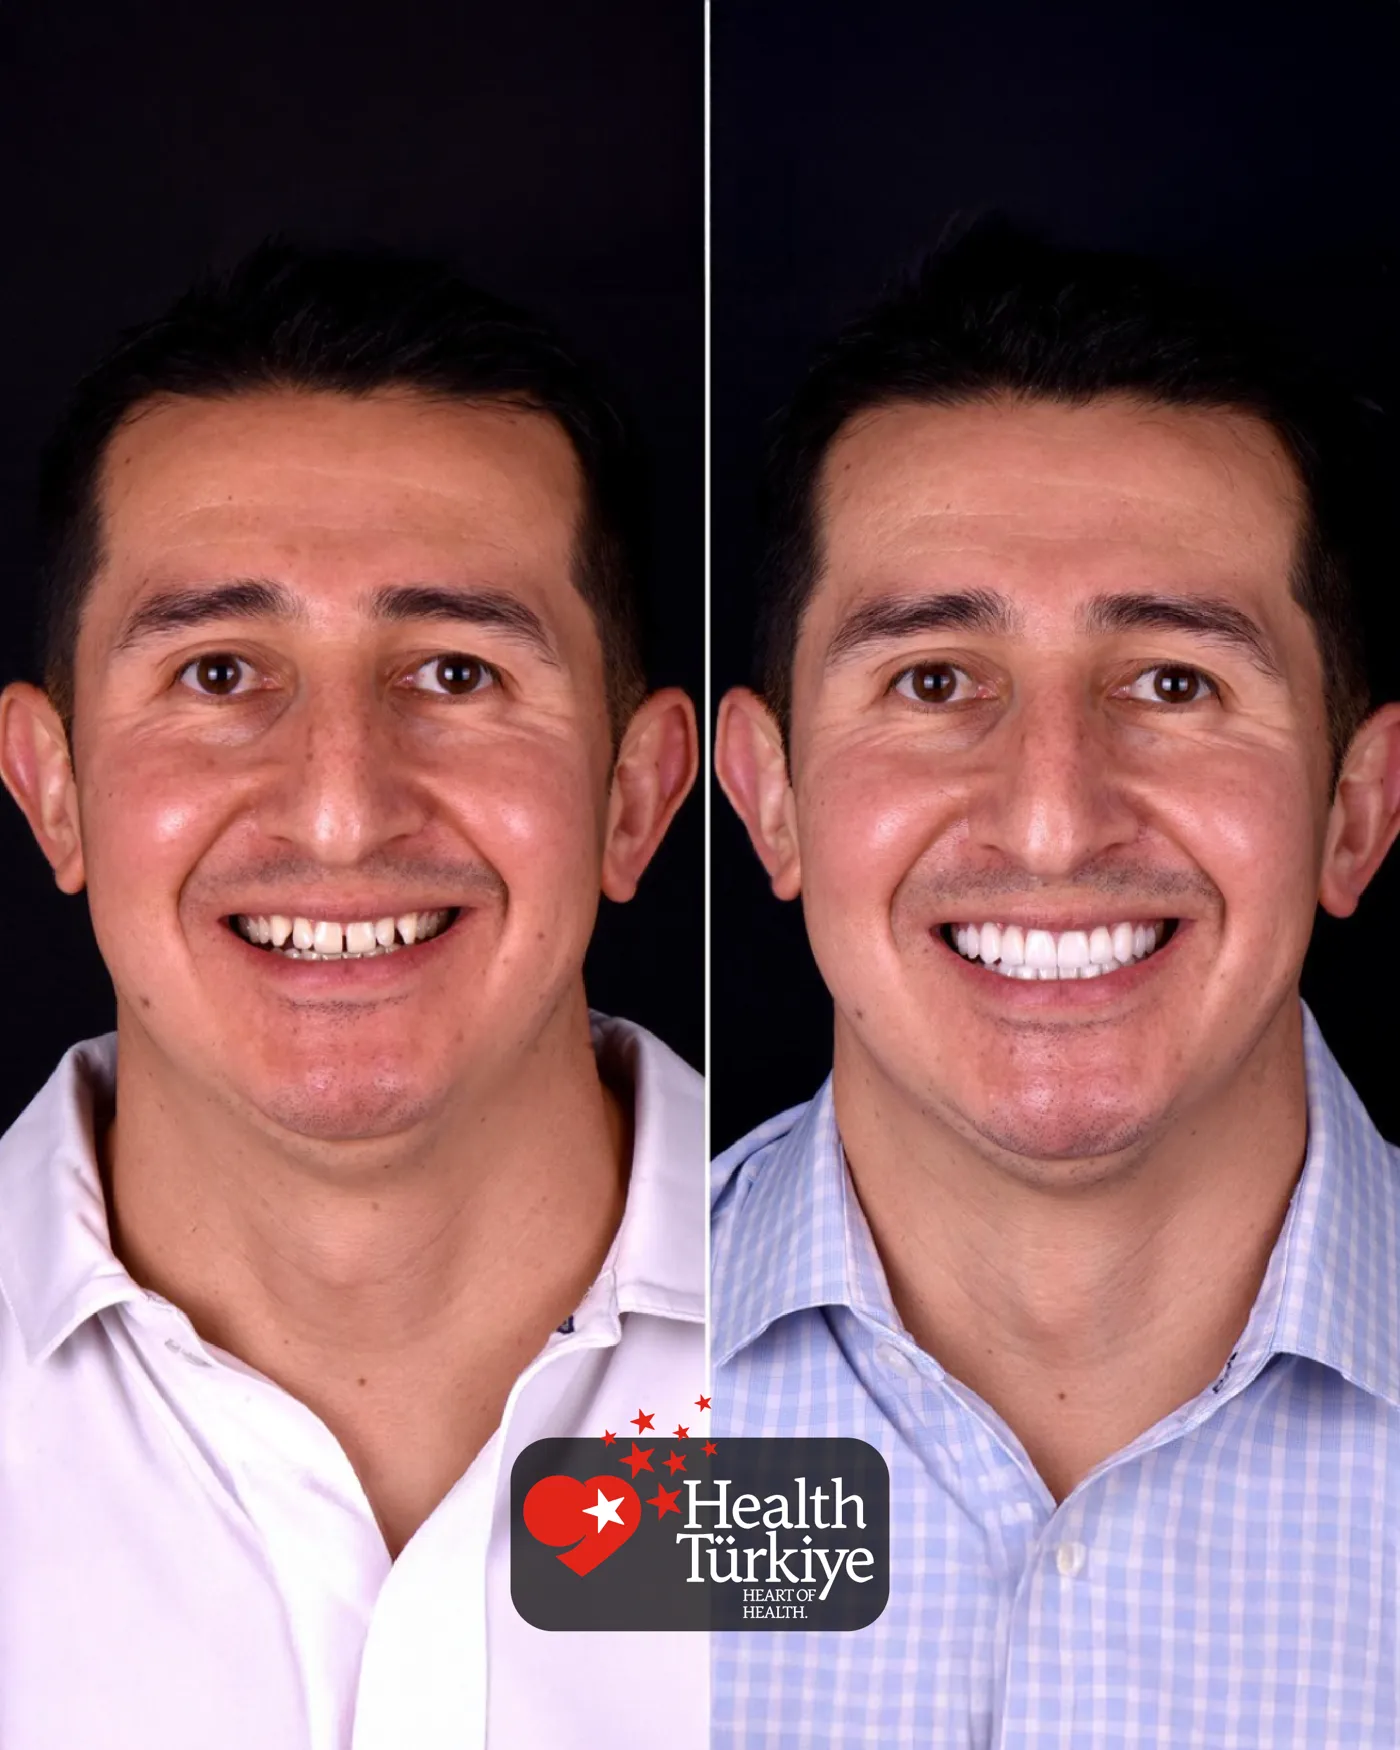
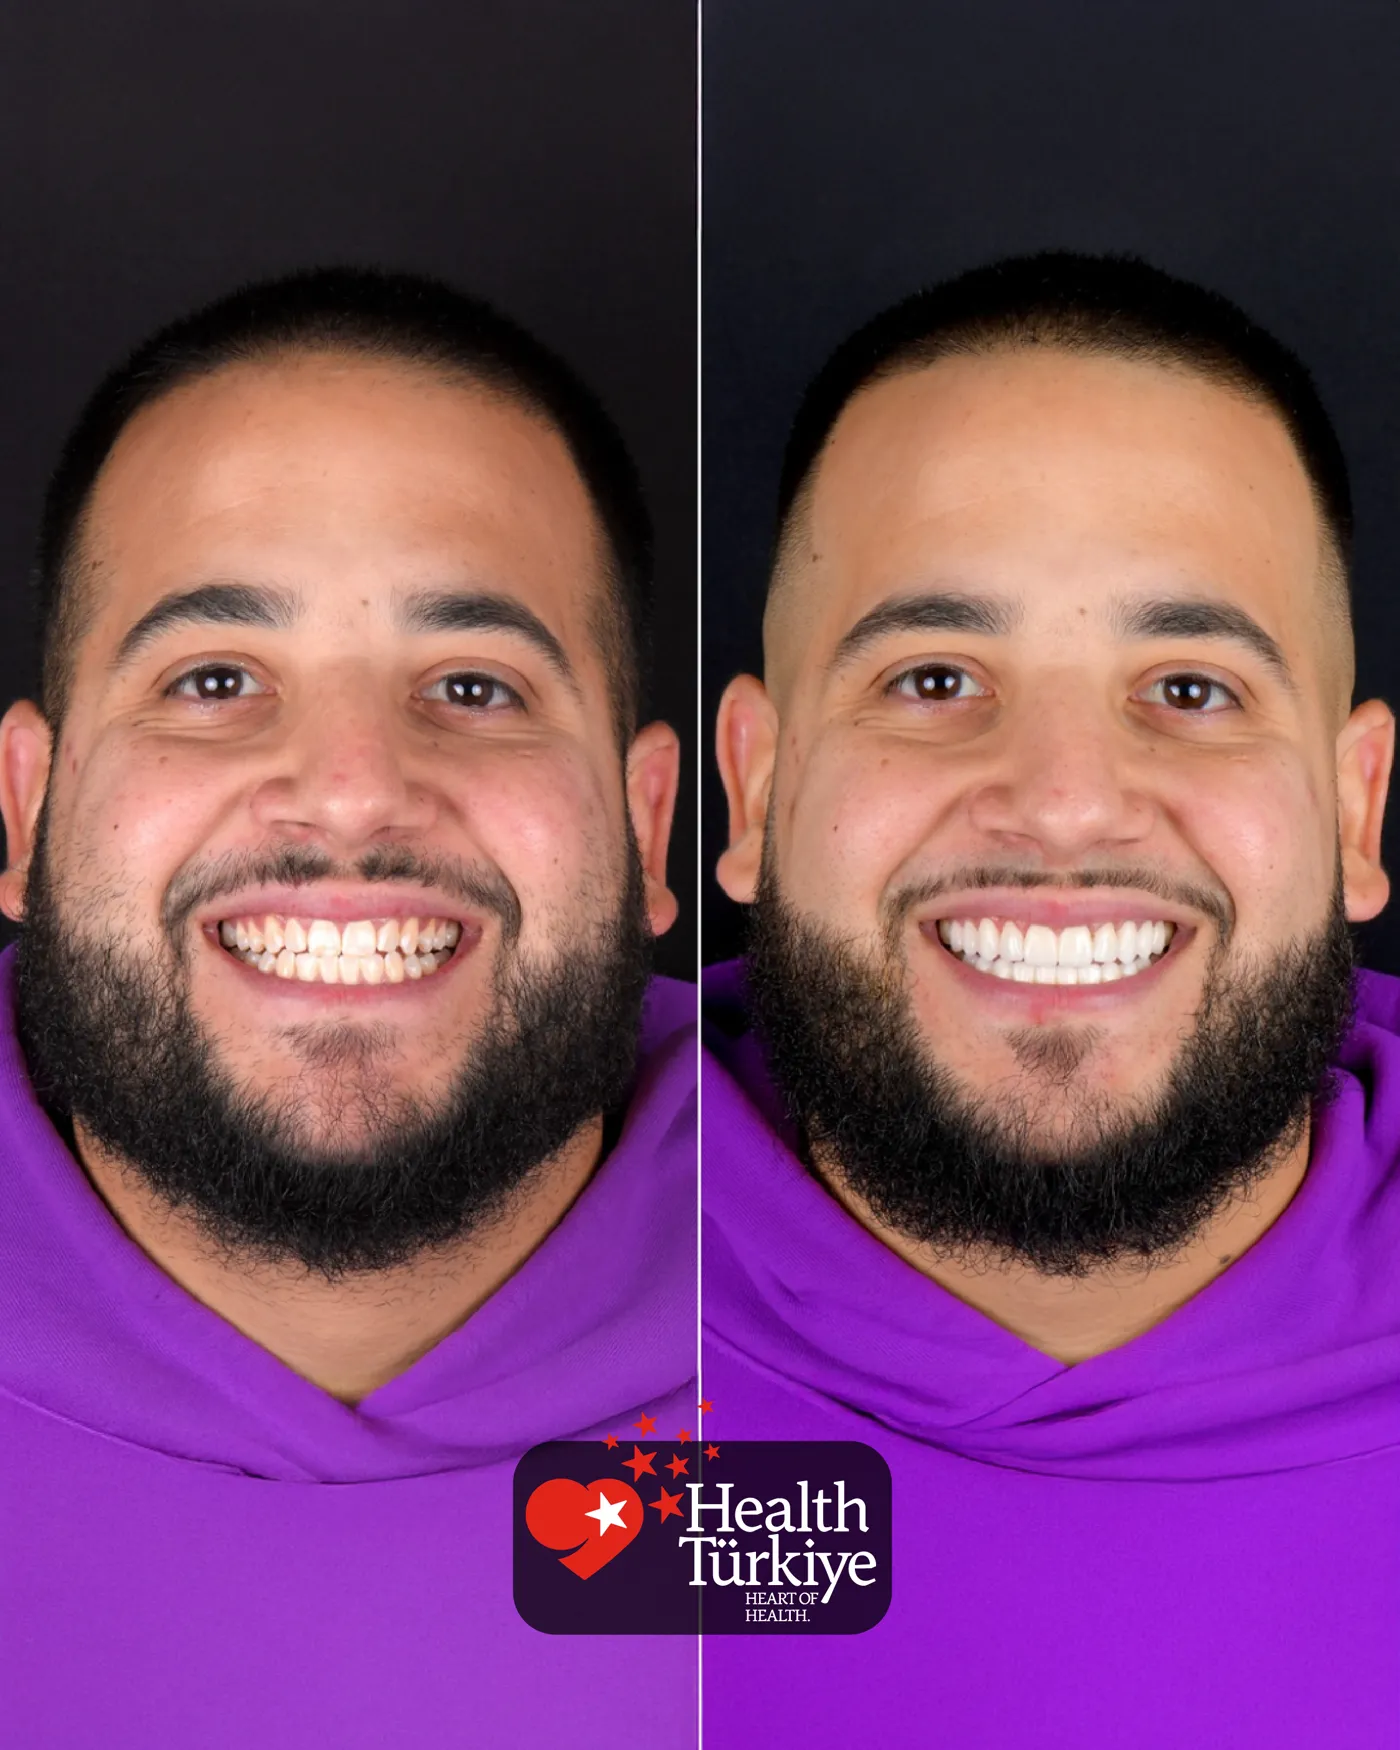
Photos from treatments performed at our clinic

Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
Klinik görseli
✦ Our Clinic
kliniğimiz
kliniğimiz
kliniğimiz
kliniğimiz

Paediatric dentistry is not a scaled-down version of adult treatment: milk teeth differ in structure, decay advances far faster, and the child's cooperation is a subject in itself.

The phrase we hear most is "they will fall out anyway" — the belief behind the biggest problem in children's dental health. Milk teeth are needed for speech development and, critically, to reserve space for the permanent teeth.

Our clinic in Muratpasa is also open 24/7 for falls and trauma.

Why Milk Teeth Matter

Being temporary does not make milk teeth unimportant; they have four functions, each affecting the permanent dentition.

Reserving space for permanent teeth

This is the critical function: each milk tooth holds space for its successor. If lost early, neighbours drift into the gap and the permanent tooth becomes impacted or erupts crowded — hence space maintainers.

Chewing and nutrition

A child with painful or missing teeth cannot chew properly, avoiding firm and fibrous foods for soft, carbohydrate-rich ones — reducing nutritional quality and creating a vicious circle.

Speech development

The front milk teeth are involved in producing certain sounds correctly; early loss during the peak of speech development can lead to persistent difficulties.

Infection risk

Advanced decay can form an abscess that affects the developing permanent tooth bud beneath, leaving lifelong enamel defects — the most serious cost of neglect.

Preventive Dentistry for Children

The strength of paediatric dentistry lies in prevention rather than treatment.

Fissure sealants

The deep grooves on molar chewing surfaces cannot be reached by brush bristles. A sealant is a flowable material that smooths these grooves, applied painlessly without anaesthesia or tooth reduction, ideally soon after the molars erupt.

Fluoride application

Fluoride strengthens enamel against acid attack; professionally applied gel or varnish provides far greater protection than toothpaste, repeated according to the child's risk level.

Building good brushing habits

Brushing should start when the first tooth appears, done by the parent in young children — manual dexterity is usually insufficient until around age seven or eight.

Diet and sugar frequency

What matters most is the frequency of sugar, not the amount: each exposure raises acid levels and enamel stays vulnerable while saliva neutralises it. Grazing all day is far worse than the same amount at once, and bottles at bedtime cause rapid decay in the front teeth.

Preparing Your Child for the Dentist

The first experience shapes a lifelong relationship with dentistry, so the first visit should ideally happen at a calm time rather than in an emergency.

When should the first visit be?

When the first tooth appears, or by around age one. This visit usually involves no treatment, so the child does not associate the clinic with pain from the outset.

Words to avoid

Children fear uncertainty more than pain, and some well-meaning phrases increase anxiety.

  • "Do not be afraid, it will not hurt" — introduces the idea of pain
  • "They will not give you an injection" — introduces the concept
  • "If you behave I will buy you a present" — turns it into a negotiation
  • Sharing your own dental fears
  • Using the dentist as a threat

What to say instead

Simple, neutral phrasing such as "they will count your teeth" is enough. Book the appointment when the child is rested, and bring a favourite toy.

Treatments Applied in Children

Like permanent teeth, primary teeth can be restored with fillings, crowns, pulp treatment and, where needed, space maintainers.

Fillings and crowns for primary teeth

Primary enamel and dentine are thinner, so decay progresses faster. Early lesions are restored with fillings in short appointments; where tissue loss is extensive, preformed crowns cover the whole tooth and maintain function and space until exfoliation.

Pulp treatment in primary teeth

When decay reaches the pulp, the tooth is not simply extracted: the coronal pulp may be removed and the radicular tissue medicated, or the canals cleaned and filled with a resorbable material so the root can resorb naturally as the permanent tooth erupts.

What space maintainers do

If a primary tooth is lost early, neighbouring teeth drift into the gap and the permanent successor may lack space. A fixed or removable space maintainer holds the gap until eruption and requires regular review as the jaw grows.

Habits, Mouth Breathing and Dental Alignment

Certain persistent habits and breathing patterns in childhood can influence jaw growth and dental alignment.

Thumb sucking, dummies and bottles

Sucking is normal in infancy and usually fades. If it continues while the front teeth are erupting, an open bite and narrowing of the upper arch may develop. The approach is gradual reduction rather than punishment; mild changes often self-correct after the habit stops.

Mouth breathing and its effect on dentition

A child who cannot breathe comfortably through the nose keeps the mouth open; with the tongue away from the palate, the upper jaw may not widen properly and crowding can follow. An ENT assessment is needed alongside dental evaluation.

Signs that warrant early orthodontic assessment

  • No spacing at all between the primary teeth
  • The lower jaw sitting ahead of the upper jaw
  • Front teeth not meeting when biting
  • A permanent tooth erupting behind the primary one
  • The jaw shifting to one side on closing
  • Losing a primary tooth much earlier than expected
  • Thumb sucking that persists beyond four years of age

✦ SSS

Frequently Asked Questions 30

01

Should decay in milk teeth be treated?

Definitely. Milk teeth hold the space for the permanent teeth that follow; if one is lost early the neighbouring teeth drift into the gap and the permanent tooth has nowhere to come through. Infection spreading from decay can also affect the developing permanent tooth bud directly beneath it.
02

When should my child first see a dentist?

When the first tooth appears, and by around the first birthday at the latest. That visit usually involves no treatment at all: it assesses the risk of decay, establishes brushing habits and lets the child meet the clinic in a calm setting. Children who start that way find later appointments far easier.
03

Are fissure sealants painful?

No. Fissure sealants need no anaesthetic and no drilling. The tooth surface is cleaned and dried, the flowable material is run into the grooves and set with a light. For a child it is one of the easiest procedures there is, and it protects exactly the surfaces where decay usually starts.
04

My child is very afraid of the dentist.

We build trust first and do not push treatment at the first visit. Letting the child see the room, handle an instrument and learn each step in advance usually reduces the fear markedly. If there has been a bad experience before, tell us beforehand — it changes how we approach the appointment.
05

Is bottle-feeding at bedtime harmful?

Yes. Saliva flow drops during sleep and sugary liquid stays in contact for hours, causing rapid decay in the front teeth. Limit night bottles to water.
06

My child's tooth was knocked out or broken.

Never replant a milk tooth — it can damage the permanent tooth bud. A permanent tooth should be brought in milk, held by the crown; the first 30 minutes are critical.
07

What happens if a primary tooth is lost early?

Adjacent teeth can drift into the gap, reducing space for the permanent successor and leading to crowding or impaction. Depending on timing and site, a space maintainer may be fitted, so an assessment after early loss is important.
08

My child grinds their teeth — is treatment needed?

Night grinding is common in children and often decreases with growth; mild wear alone is not a concern. Marked wear, morning jaw pain, headaches or disturbed breathing during sleep should be assessed so the underlying cause can be addressed.
09

There are gaps between my child's front teeth — is that a problem?

Spacing between primary teeth is usually a good sign, since permanent teeth are wider and need that room. A complete lack of spacing is more likely to signal future crowding, though features such as a low frenulum are checked at examination.
10

Which toothpaste should I use for my child?

Both the age-appropriate fluoride level and the amount matter: a rice-grain smear for toddlers and a pea-sized amount at preschool age, with adult supervision. Your dentist may advise differently according to your child's caries risk.
11

What is the difference between going to an on-call centre and a clinic that is always open?

The main difference is predictability. With a rotation you must find out which centre is open tonight; with a permanently open clinic the address and hours never change. Our clinic works around the clock, so nights, weekends and holidays are handled by the same team with the same equipment.
12

My tooth started hurting badly on Saturday afternoon. Do I have to wait until Monday?

You do not have to wait; weekend visits are possible. Suppressing pain with tablets for two days is rarely wise, because the underlying infection does not stop, it only becomes less noticeable and may spread. A weekend examination usually identifies the cause and allows immediate relief.
13

A swelling like an abscess appeared on the second day of the public holiday. Can I find anywhere open?

Yes, you can be seen on public holidays; our clinic stays open. Swelling is a poor reason to wait, since an abscess does not resolve on its own and can spread across the face. Holiday visits focus on assessing the swelling, providing drainage if needed and starting suitable medication.
14

I have no appointment but I cannot bear the pain. Would I be turned away if I just come?

Walk-in visits are accepted for emergencies and no one is turned away. A short phone call before setting off still helps, because knowing your complaint in advance allows preparation. Waiting time depends on how busy the clinic is, but severe pain, bleeding and swelling are prioritised.
15

Why do you ask me so many questions on the phone? Can I not simply come in?

The questions are for preparation, not delay. We ask when the pain began, whether there is swelling, fever or difficulty swallowing, your medications and known conditions. This helps distinguish a dental emergency from a situation needing hospital emergency care, and lets the right clinician and materials be ready.
16

If I describe my symptoms on the phone, can you tell me which tooth is the problem?

No firm diagnosis is made by phone, only guidance. Dental pain often radiates, so a lower tooth may be felt in the ear and an upper tooth in the temple, and patients frequently point to the wrong tooth. Identifying the culprit needs examination and usually a radiograph.
17

If I photograph my mouth and send it, would that give you an idea before I come?

A photo can help but does not replace examination. Swelling, gum colour changes or a fractured edge may be visible, yet the depth of decay, infection at the root tip and bone condition are not. Images assist in triage, they do not determine the treatment plan.
18

Is there anything I should do at home before setting off at night?

Call the clinic and describe the problem briefly. If there is bleeding, keep firm pressure with clean gauze on the way. For swelling apply cold to the cheek, never heat. Bring your medication boxes and note when you last took a painkiller; if possible, come with someone.
19

What should I take with me when going for emergency dental care?

Bring your ID, the boxes or a written list of your regular medicines, any previous dental radiographs and your removable denture. Also bring a broken fragment or a crown that came off, since these can sometimes be re-attached. The name and dose of blood thinners or diabetes medicines matter most.
20

I had an X-ray taken six months ago elsewhere. Is there any point in bringing it?

Yes, bring it. An older image shows the previous state of the area, so the clinician can compare and see how fast the problem progressed, which is useful for root-tip infections and bone loss. A new image is usually still needed; a digital copy or phone photo is fine.
21

Can I go for emergency care alone at night, or must someone come with me?

Most people can come alone. A companion is advised if you have a known heart or diabetic condition, a history of fainting, if sedative medication will be used, or if bleeding is expected after the procedure. Children and elderly patients should always be accompanied.
22

Can I drive myself home after a night-time procedure?

After local anaesthesia alone most patients can drive, since it numbs the area without affecting consciousness. If sedation or a sedating medicine was given, or after longer surgery, do not drive and travel with someone. A painful, sleepless night also reduces alertness.
23

What happens step by step when I arrive? Is my tooth treated straight away?

Usually a short history comes first: duration of symptoms, medical conditions and medicines. Then an intra-oral examination and, when needed, a radiograph. Treatment is planned after that, because treating the right tooth correctly is rarely possible without an image. The aim is to control pain and infection.
24

Someone who arrived after me was seen first. How is the order decided?

Order depends on urgency, not arrival time. Swelling that affects breathing or swallowing, uncontrolled bleeding, infection with high fever and an avulsed tooth are seen first, because minutes change the outcome. More stable complaints are seen after a short wait; tell the team if your condition changes.
25

They said we should take an X-ray right away. Is a rushed radiograph harmful?

Dental radiographs use a low dose limited to a small area, reduced further by digital sensors and shielded with a lead apron and thyroid collar. Without an image, root-tip infection, fractures or impacted teeth cannot be seen, so skipping it usually carries the greater risk. Always mention possible pregnancy.
26

I am pregnant and in severe pain. Would a dental X-ray harm the baby?

Dental radiographs can be taken during pregnancy when necessary; the beam is aimed at the jaw and not at the abdomen, and a lead apron with thyroid collar is used. Imaging is still limited to cases that change the treatment decision. Always state your pregnancy and week.
27

My treatment was not completed at the emergency visit. Why was it left unfinished?

Emergency care aims to control pain and infection; definitive treatment is a separate stage. An infected tooth is usually opened, cleaned and sealed temporarily, since closing it while infection persists can bring the pain back. Crowns, bridges and implants also need laboratory stages.
28

My pain is gone. When should I come back for the definitive treatment?

Pain relief does not mean the problem is solved; pressure drops, but the underlying condition remains. Definitive treatment is best planned within the following days. Temporary fillings wear down and an exposed canal can become re-infected, so keep the review date even if you feel fine.
29

Do I really need a follow-up visit after emergency treatment if I feel well?

The follow-up checks whether healing is progressing as expected: tissue closure, the temporary filling and signs of infection. Feeling well is not a substitute, because some root-tip infections progress painlessly for a long time. Review visits are short and catch problems early.
30

Hours after my extraction the bleeding still has not stopped. What should I do?

Roll clean gauze, place it over the socket and bite firmly for about half an hour without checking, since that disturbs the clot. Sit upright and avoid hot drinks, smoking, rinsing and suction. If bleeding continues despite pressure, come in, and mention any blood thinners.

From Our Blog

✦ Our Brands
Straumann
Nobel Biocare
Astra Tech
Medentika
Bredent SKY
Straumann
Nobel Biocare
Astra Tech
Medentika
Bredent SKY
✦ Contact
Get in touch

Antalya Muratpaşa our central clinic

Sair Adem Dede St. No:31, 07030 Muratpasa / Antalya, Türkiye

Open in Google Maps